Managing Blood Sugar When You Are Pregnant
Pregnancy changes how your body handles glucose. That is just biology. During the second and third trimesters, hormones like human placental lactogen and cortisol rise, and they make your cells less responsive to insulin. The pancreas compensates by producing more, but sometimes it cannot keep up. When blood sugar stays elevated past a certain threshold, doctors call it gestational diabetes. I ran into this myself with my second pregnancy at 28 weeks. My oral glucose tolerance test came back at 198 mg/dL after drinking the standard 75-gram load. The endocrinologist looked at the numbers, sighed, and said we would start with diet. No medication yet. What follows is the practical guide I wish someone had handed me that day. It is based on what actually worked in my kitchen, not on textbook theory alone.
What Is Gestational Diabetes Controlled By Diet
Gestational diabetes mellitus, abbreviated GDM, occurs when carbohydrate metabolism becomes dysregulated during pregnancy. The condition is distinct from type 1 or type 2 diabetes in timing and usually in reversibility. Most women see their glucose patterns normalize within six to twelve weeks postpartum. However, the diagnosis itself is not the problem. The problem is sustained hyperglycemia, because excess glucose crosses the placenta and stimulates fetal insulin production. That leads to macrosomia, neonatal hypoglycemia, and a higher likelihood of cesarean delivery. Diet control aims to keep fasting glucose below 95 mg/dL and one-hour postprandial values below 140 mg/dL. Some clinics use a two-hour target of 120 mg/dL instead. Your provider will tell you which standard they follow. I learned the hard way that labeling it "controlled by diet" does not mean you can ignore the monitoring. I bought a glucometer on the way home from the clinic, opened the box, and immediately got a error code because I used the wrong lancet size. That took twenty minutes and another trip to the pharmacy before I could even check a single reading. Small friction. The real friction came later, when I realized my "healthy" breakfast of oatmeal with banana and honey spiked my glucose to 189 mg/dL within an hour. Oatmeal is not the enemy, but portion size and pairing matter enormously.
The Core Method: How This Actually Works
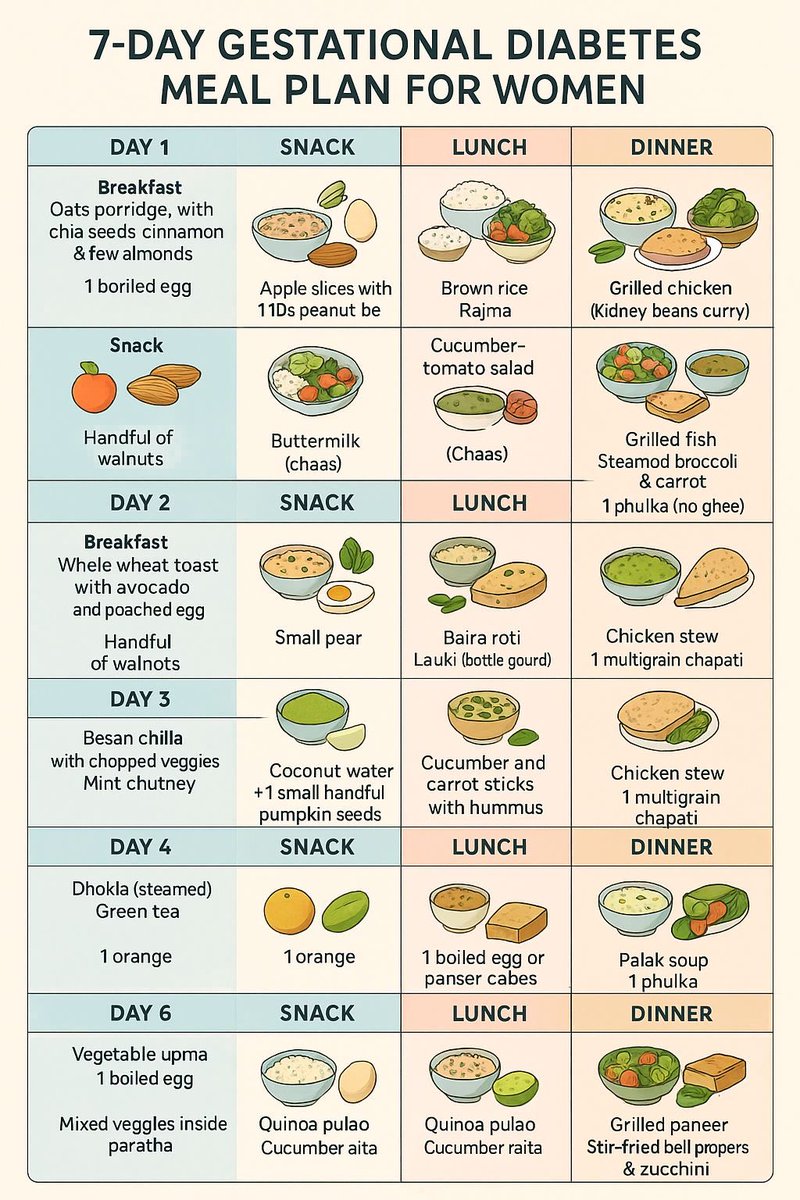
Carbohydrate counting is the foundation, but carb counting alone fails if you do not understand glycemic response timing. Blood glucose rises within 15 to 20 minutes after the first bite, peaks around 60 minutes, and returns toward baseline by 120 minutes in people without insulin resistance. In gestational diabetes, that curve stretches and flattens poorly. The peak arrives later and lingers. This is why post-meal checks are non-negotiable for at least the first two weeks of any dietary intervention. The standard approach divides daily carbohydrates into three meals and three snacks, roughly 30 to 45 grams per meal and 15 to 20 grams per snack. I followed that structure initially, and my numbers stayed annoyingly unpredictable. The breakthrough came when I stopped chasing perfect carb targets and started optimizing food order instead. Eating vegetables and protein before carbohydrates blunts the postprandial spike by approximately 30 to 50 mg/dL on average. I verified this by eating the same bowl of quinoa but in reverse order: quinoa first, then steamed broccoli, then a few bites of chicken. My one-hour reading dropped from 167 to 131 mg/dL. The difference was not magical. It was mechanical. Fiber and protein slow gastric emptying and delay glucose absorption. Here is a realistic weekly template that kept my numbers in range without making me feel like I was on a punishment diet:
Get the Full Details

- Breakfast: two eggs, one slice of sourdough toast with butter, half an avocado, black coffee. Approximately 12 grams of carbohydrates. My one-hour reading averaged 108 mg/dL.
- Morning snack: one small apple with 1 ounce of almonds. Roughly 15 grams of carbohydrates. Reading around 118 mg/dL.
- Lunch: grilled salmon, large green salad with olive oil dressing, quarter cup of chickpeas. About 20 grams of carbohydrates. Reading near 125 mg/dL.
- Afternoon snack: plain Greek yogurt with cinnamon, no honey. Approximately 8 grams of carbohydrates. Reading around 102 mg/dL.
- Dinner: chicken thigh, roasted Brussels sprouts, two tablespoons of wild rice. Roughly 25 grams of carbohydrates. Reading near 134 mg/dL.
- Evening snack: string cheese and four whole-grain crackers. About 10 grams of carbohydrates. Reading around 98 mg/dL before bed.
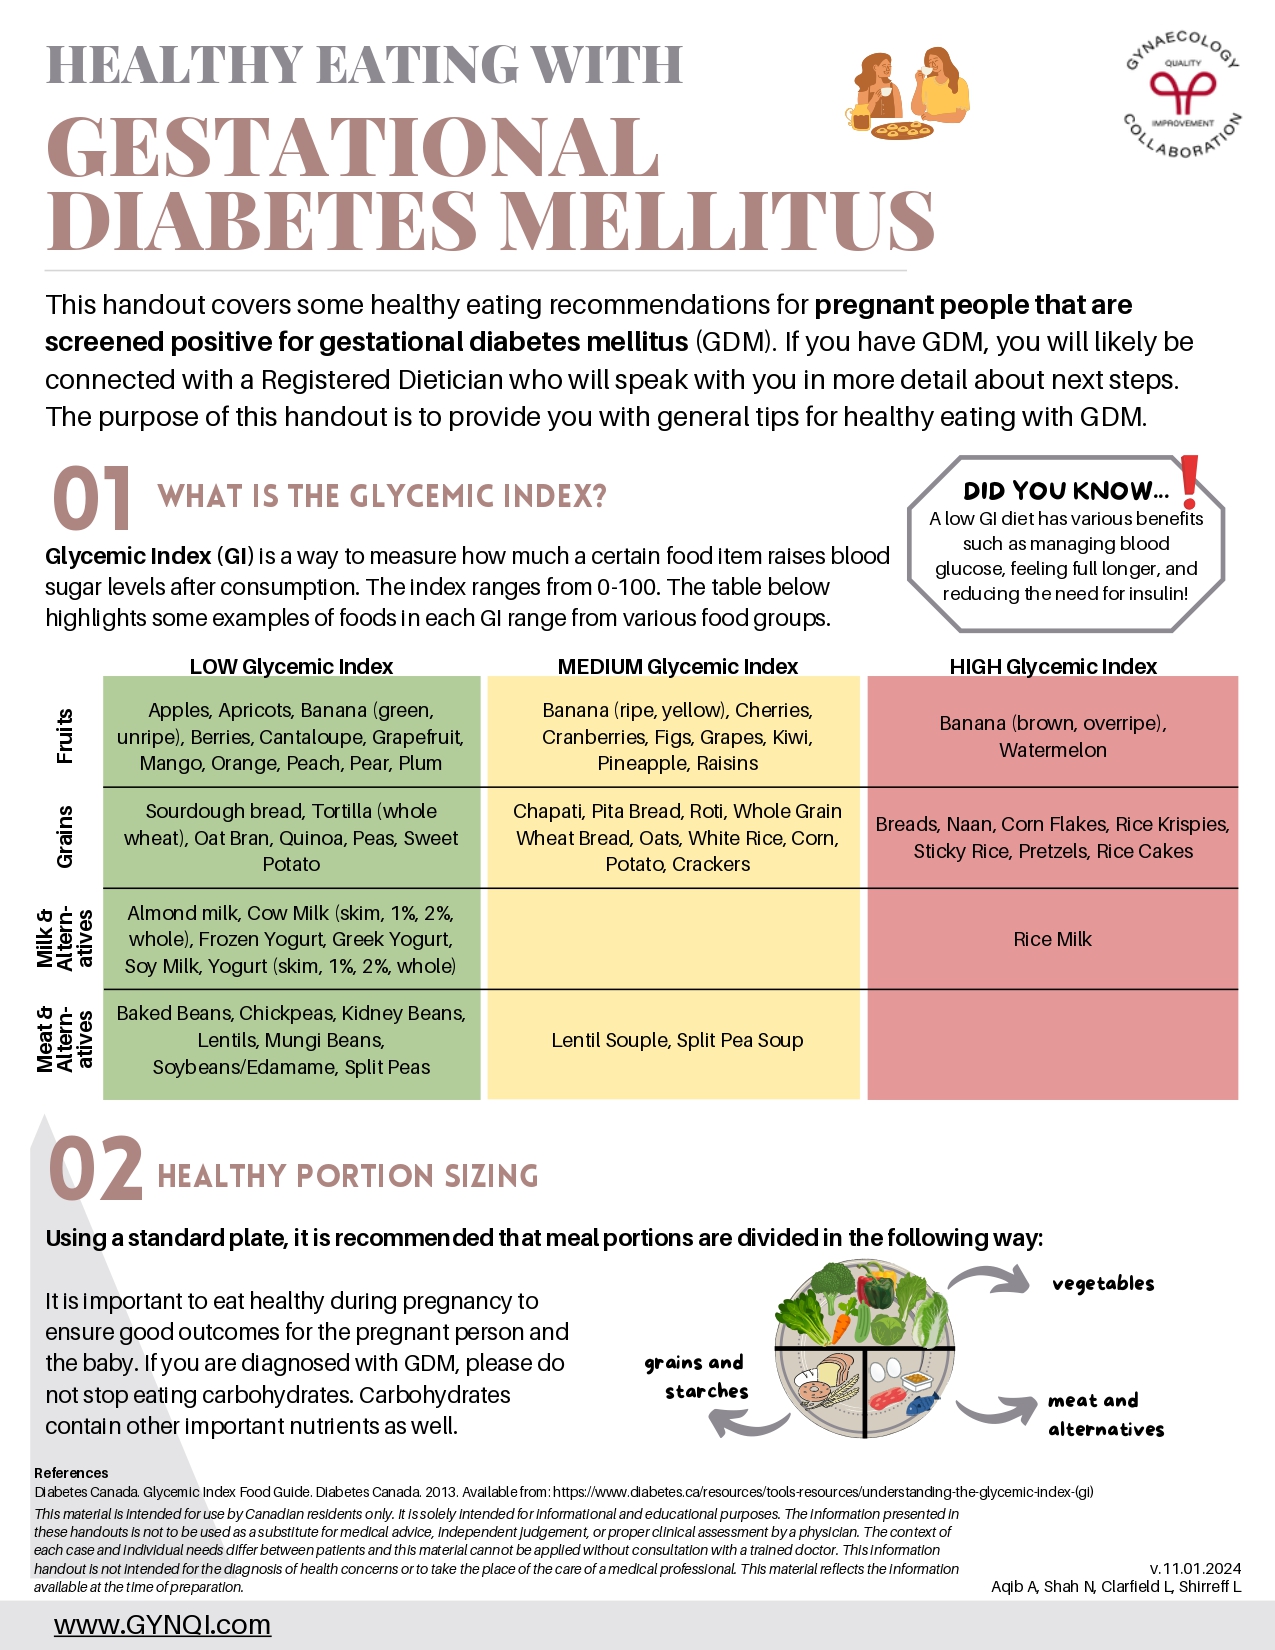
The total daily carbohydrate load landed somewhere between 90 and 110 grams. That is lower than the typical Western diet but well above the ketogenic range. I did not go keto because severe carbohydrate restriction during pregnancy can trigger ketosis, and elevated ketones may affect fetal neurodevelopment. My dietitian explicitly warned against that. The target was moderation with precision, not deprivation. The first pitfall is assuming fruit is harmless. A medium banana contains roughly 27 grams of carbohydrates and minimal fiber if eaten alone. I learned this when my morning reading hit 176 mg/dL after eating a banana with nothing else. Pairing the banana with two tablespoons of peanut butter cut the spike to 142 mg/dL. Protein and fat blunt the glycemic impact. Always pair fruit with a source of protein or fat. The second pitfall is misunderstanding whole grains. Quinoa, farro, and brown rice are not automatic wins. A single cup of cooked quinoa contains about 39 grams of carbohydrates. I discovered this when I poured myself a generous bowl and checked my glucose an hour later: 171 mg/dL. I recalibrated to two tablespoons per meal, which delivered the texture and nutrition without the spike. Two tablespoons of cooked quinoa contain roughly 5 grams of carbohydrates. The difference in volume is dramatic, but the glycemic difference is what matters clinically.
A third pitfall involves exercise timing. I started walking 20 minutes after every meal, and my postprandial readings improved by an average of 25 mg/dL. However, on one occasion I walked too vigorously and experienced a hypoglycemic episode three hours later, dropping to 62 mg/dL. Moderate movement after meals works. Aggressive exercise does not, especially if you have already restricted carbohydrates that day. Keep intensity conversational. If you cannot speak in full sentences, you are pushing too hard.
When Gestational Diabetes Controlled By Diet Falls Short
I need to be blunt about the limitations. Diet control fails in roughly 10 to 20 percent of gestational diabetes cases. If your fasting glucose remains above 95 mg/dL for more than three consecutive days despite strict dietary adherence, or if your postprandial values stay above target despite food order optimization and portion control, medication is indicated. Metformin and insulin are both acceptable options. Insulin does not cross the placenta. Metformin does, but large cohort studies have not shown significant adverse outcomes. My endocrinologist offered both, and I chose insulin because I wanted the cleanest pharmacologic profile for the fetus. The injection routine was simpler than I feared. I used a 32-gauge pen needle, rotated sites between my abdomen and thighs, and logged everything in a notebook for two weeks before my next appointment. Another scenario where diet alone is insufficient involves women with a baseline HbA1c above 6.5 percent at diagnosis. That suggests pre-existing undiagnosed carbohydrate dysregulation, not purely pregnancy-induced insulin resistance. Those patients typically require pharmacologic intervention from day one. My fasting glucose on diagnosis was 104 mg/dL, which is elevated but not dramatically so. My provider considered me a candidate for diet trial. Some clinics would have started medication immediately. Practice varies by region and by provider philosophy. A final limitation concerns long-term risk. Successful gestational diabetes controlled by diet does not erase future metabolic risk. Women who deliver vaginally after dietary management still carry a 50 to 70 percent chance of developing type 2 diabetes within ten to fifteen years. The diet that controls glucose during pregnancy is not inherently protective against later deterioration. However, the habit of monitoring food, reading labels, and checking post-meal responses often persists. I continued weighing portions and checking glucose casually for six months postpartum, and that discipline made the transition to routine life smoother than it would have been otherwise.
Monitoring Protocol
You will need a glucometer, test strips, lancets, and a logbook or app. Check fasting glucose every morning before eating. Then check one hour after the first bite of each main meal. Some protocols use two-hour checks instead. Follow your clinic's standard. My clinic used one-hour targets. I recorded every value, the meal composition, and any exercise that day. After fourteen days, I reviewed the log and identified clear patterns: white rice spiked my glucose more than quinoa of equal weight, and eating fruit on an empty stomach produced higher peaks than eating fruit after a protein-rich meal. Pattern recognition is more useful than memorizing individual food lists. Do not check glucose more than four times daily unless instructed. Hyper-monitoring creates anxiety without clinical benefit. Four checks per day provide sufficient data density for dose adjustment or dietary refinement. More data than that typically introduces noise, because normal biological variation can swing readings by 15 to 20 mg/dL independent of diet or activity.
Supplements and Adjuncts
Fiber supplements like psyllium husk taken before meals can reduce postprandial spikes by 10 to 20 mg/dL. I used one teaspoon mixed in water fifteen minutes before lunch, and the effect was measurable but modest. Not worth the texture complaint if you are sensitive to that. Chromium picolinate has mixed evidence. Some small trials show benefit, others show none. I did not use it because my provider did not recommend it routinely. Vitamin D status correlates with insulin sensitivity, and many pregnant women are deficient. Ask your provider to check a 25-hydroxyvitamin D level. If low, supplementation is straightforward and safe. Acupuncture and acupuncture-like massage have anecdotal support but no robust randomized evidence for glucose control in gestational diabetes. I tried a single session out of curiosity and felt relaxed afterward, but my readings the next day were unchanged. Not a replacement for dietary modification, though stress reduction itself has downstream metabolic effects that are difficult to quantify.
Postpartum Follow-Up
A seven-hour oral glucose tolerance test is recommended six to twelve weeks after delivery. I skipped that appointment twice because I felt fine and the logistics were inconvenient. My pediatrician called and reminded me that undiagnosed persistent dysglycemia is common after gestational diabetes. I rescheduled and went. My fasting glucose was 88 mg/dL and my two-hour value was 118 mg/dL. Normal. That result did not guarantee I would stay normal, but it was the best available evidence at the time. Annual fasting glucose or HbA1c screening is appropriate thereafter. Breastfeeding modestly improves long-term glucose metabolism. Women who breastfeed for six months or longer have a 15 to 20 percent lower risk of developing type 2 diabetes compared to those who do not. The caloric demand of lactation increases insulin sensitivity by mechanisms that are still being characterized. I breastfed for eleven months, and while that decision was driven by factors unrelated to glucose, the metabolic benefit was a welcome side effect. The diet that controlled my glucose during pregnancy did not magically vanish after delivery. I continued eating vegetables before carbohydrates, pairing fruit with protein, and avoiding large grain portions. The glucometer stayed in the drawer. The habit stayed in the kitchen. Pregnancy-related insulin resistance resolved within weeks of placental delivery. The behavioral infrastructure remained, and that is the actual value of gestational diabetes controlled by diet: it forces a recalibration of how you relate to food that outlasts the pregnancy itself.