The Stain That Actually Matters in Your Lab
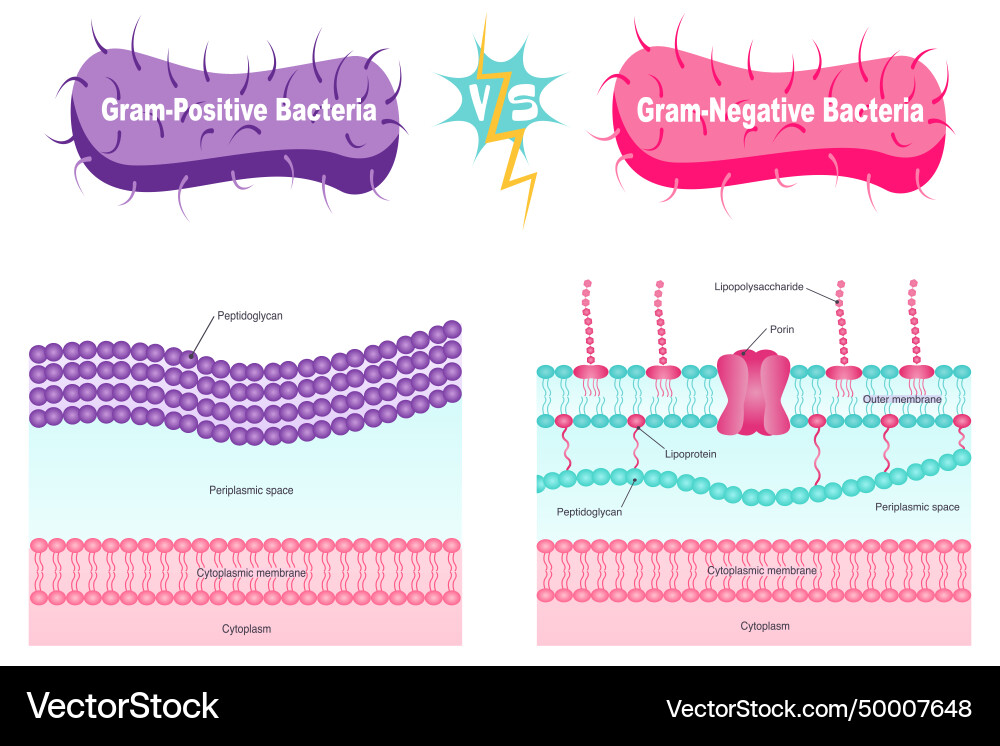
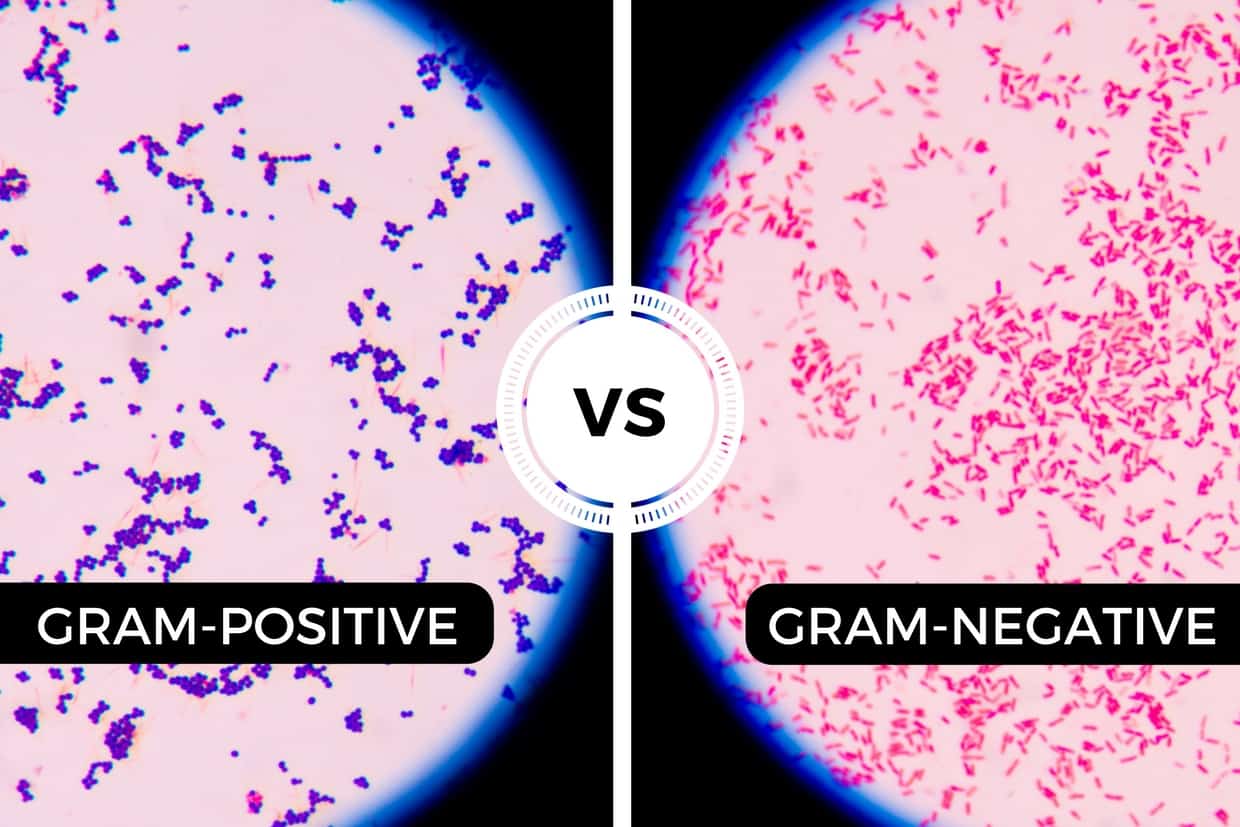
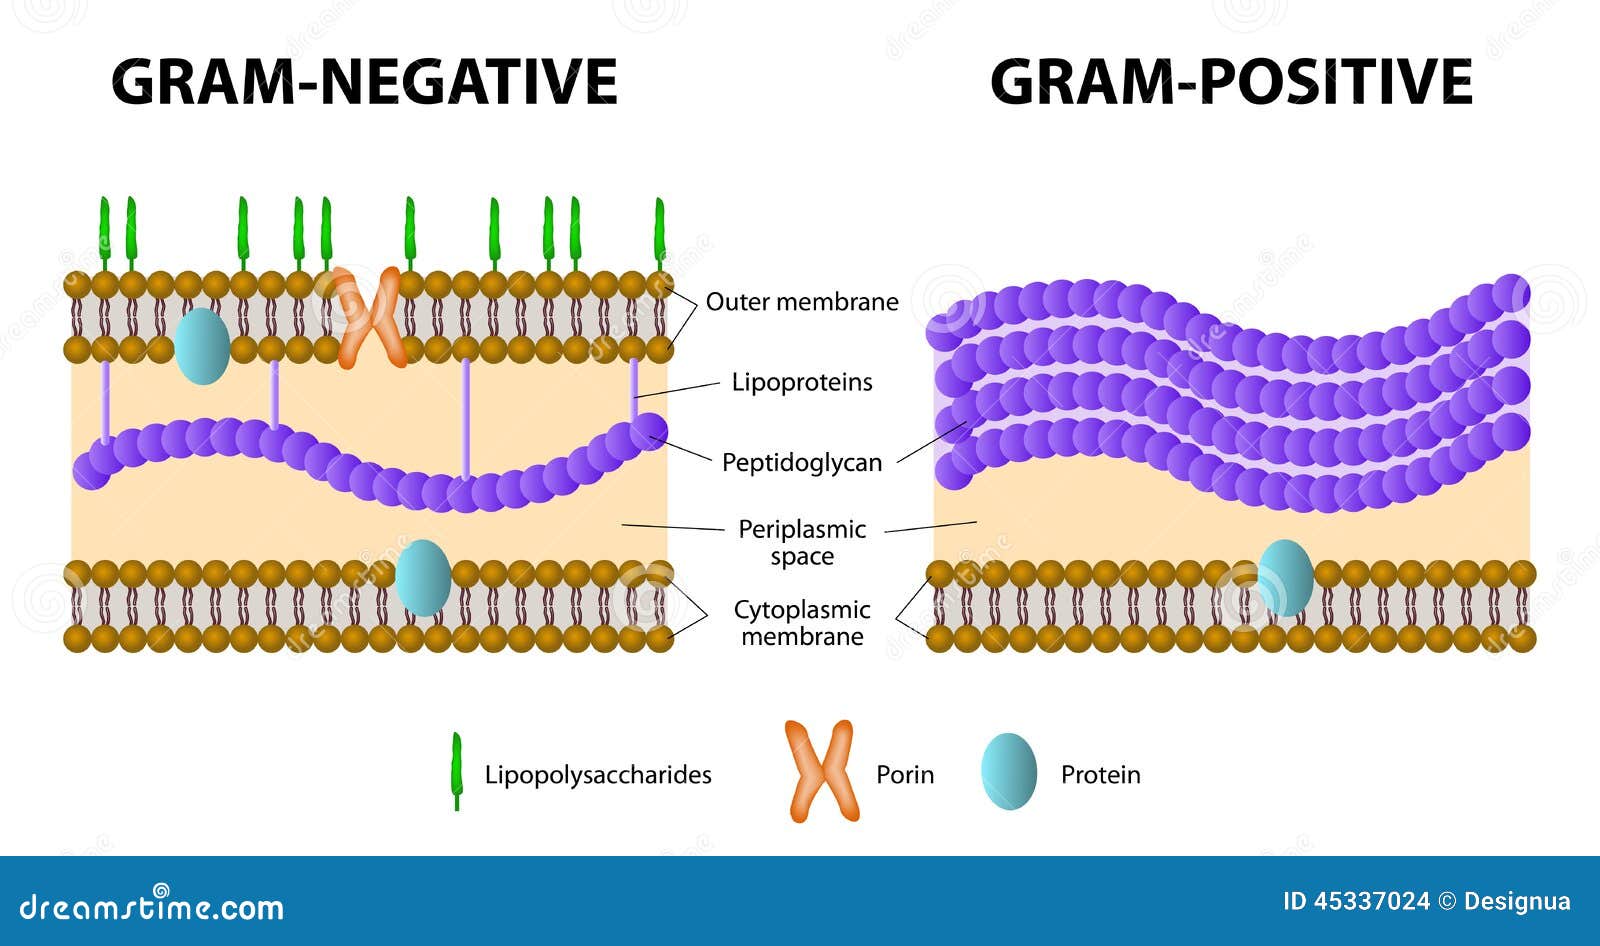
Gram staining is still the single most used microbiological technique after all these years, and for a reason that has nothing to do with tradition. The cell wall differences between the two major bacterial groups are real, structural, and they dictate how every downstream decision plays out — from antibiotic selection to contamination protocols on your bench. Here is how it works when you actually do it, not the simplified version from a textbook. You flood a heat-fixed smear with crystal violet for one minute. Drain it. Iodine for another minute — that is the mordant, and it forms a large crystal violet-iodine complex inside the cells. Then you decolorize with 95% ethanol or acetone-alcohol, and this is where everything hinges. You tilt the slide and let the solvent run across the smear for about 10 to 15 seconds. Not longer. Not shorter. If you leave it too long, even gram positives will lose the stain. If you cut it off too early, gram negatives won't decolorize properly and you get a false positive reading across the board. After decolorization, you counterstain with safranin for 45 seconds, rinse with tap water, blot dry with lens paper, and look at it under oil immersion. Gram positives retain the purple crystal violet-iodine complex because their thick peptidoglycan layer — roughly 20 to 80 nanometers, sometimes more — traps it. Gram negatives have a much thinner peptidoglycan layer, about 2 to 7 nanometers, plus an outer membrane rich in lipopolysaccharide. The alcohol dissolves that outer membrane and washes the complex right out of the thin peptidoglycan, so they take up the pink safranin instead.
I learned this the hard way during a routine quality control run a few years ago. I was processing sputum samples for a respiratory pathogen panel, and my gram stains kept showing mixed results — some gram negatives were holding onto purple while clearly being gram negative by culture. What I discovered was that my decolorization step was inconsistent because I was working with old ethanol that had absorbed moisture from the air. Open containers of 95% ethanol pull water fast in a non-hermetically sealed lab environment. I switched to freshly opened bottles and started capping them immediately after each use, and the inconsistency dropped to near zero. Another factor I did not initially consider was the age of the culture. Overgrown gram-negative colonies on nutrient agar develop altered membrane permeability and can retain crystal violet artificially. That is why I now use 18 to 24-hour cultures exclusively and never pick from plates older than 36 hours. The difference in staining reliability is substantial. Gram positive bacteria — things like Staphylococcus aureus, Streptococcus pneumoniae, Bacillus subtilis, and Listeria monocytogenes — show up as purple rods or clusters depending on the species. Gram negatives like E. coli, Pseudomonas aeruginosa, Salmonella, and Haemophilus influenzae appear pink or red. But the colors alone are not where the real utility sits. The structural distinction explains why vancomycin works against gram positives but not gram negatives — the drug simply cannot cross that outer membrane. It also explains why endotoxin, specifically lipid A from the lipopolysaccharide in gram-negative cell walls, is responsible for septic shock in infections by organisms like Neisseria meningitidis. Gram positives do not carry endotoxin. They produce exotoxins instead, which are secreted proteins with entirely different mechanisms of damage. There is a common pitfall that catches people frequently. When you are examining a clinical sample — blood, wound swab, urine sediment — you are not always looking at pure culture. Mixed flora is the norm rather than the exception outside of controlled isolation work. In those cases, distinguishing true pathogens from contaminants relies entirely on your ability to read the gram stain correctly and correlate it with colony morphology. I once spent two days troubleshooting what I thought was a gram-positive diplococci contamination, only to realize the organism was Veillonella, a gram-negative coccus that often gets misread because its small size and tendency to sit between larger cells makes it easy to dismiss. It did not change my treatment, but it changed how I approach initial smears — I scan the entire slide systematically instead of fixing on one field and calling it.
Another nuance worth noting is that some organisms sit in a gray area. Mycobacterium species have an entirely different cell wall structure built around mycolic acids, which is why the acid-fast stain exists as a separate category. Legionella pneumophila and Neisseria gonorrhoeae are gram-negative but stain very poorly with standard protocol, so you often need to use a modified stain or rely on alternative diagnostics. Enterococcus species can appear gram-variable even when they are technically gram-positive, especially in older cultures or when the cell wall is being actively remodeled during growth. If you are relying solely on gram staining without confirmatory culture, these edge cases will cost you. The practical timeline for a standard gram stain from smear to result is roughly 15 to 20 minutes if you are working methodically. Rapid inoculation loops, pre-labeled slides, and a dedicated staining station with reagents already uncapped can shave that down further. The bottleneck is almost always the decolorization step — it requires judgment rather than automation, and every technician interprets it slightly differently. Standardizing your technique across a lab team usually involves creating a reference slide set with known organisms and having everyone compare their results against it weekly. This is how you catch drift before it affects patient samples. If you need to identify organisms beyond the gram stain level, you move into biochemical testing or molecular methods. API strips, VITEK cards, MALDI-TOF mass spectrometry, and PCR panels each have their place, but none of them replace the initial gram stain as a triage tool. It tells you whether to start broad-spectrum coverage targeting gram positives, gram negatives, or both while you wait for culture results. In a sepsis workup, that initial 20-minute decision window is often the difference between appropriate empiric therapy and a delay that matters clinically.
Get the Full Details