
What You Actually Need to Document for Group Therapy
Most people think group therapy notes are just a group version of individual notes. They are not. The rules are tighter, the liability landscape is wider, and auditors treat any ambiguity as a red flag. Here is what I have learned from dealing with this over years of practice. Group Therapy Documentation Requirements exist at the intersection of clinical standards, insurance contracts, and state licensing board expectations. You need to produce records that satisfy all three without contradiction. That is harder than it sounds. Start with the licensing board requirements in your jurisdiction, then layer in the payer criteria. Different payers use different language but often demand the same underlying data. If you get the structure right once, you can adapt most forms by swapping payer-specific fields.
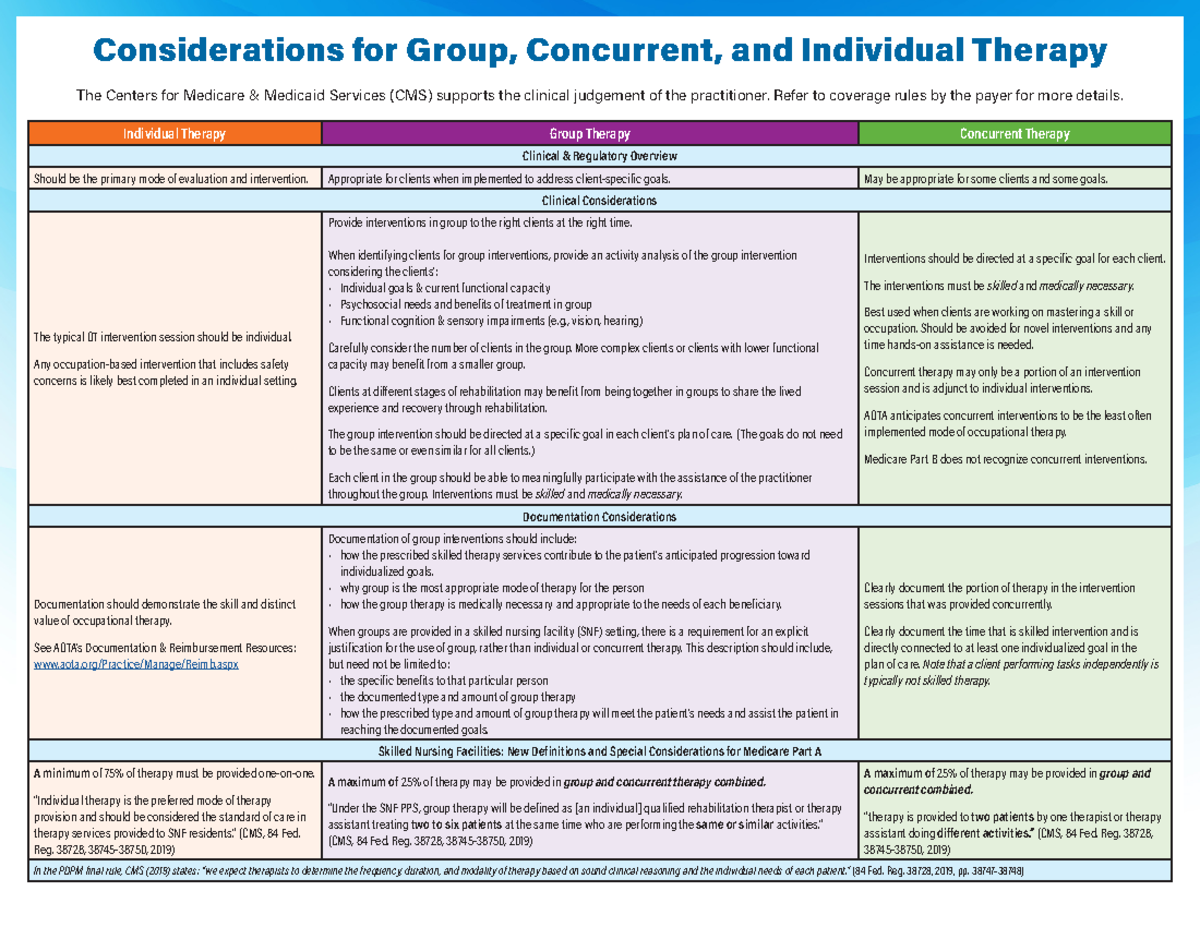
Here are the core components you should include in every group therapy session note:
- Date, time, and duration of the session — including start and stop times, not just total length
- Names of all participants present, with current first initial and last name per payer preference
- Crisis or safety status for each participant, even if no event occurred
- Group process observations — dynamics, interpersonal patterns, and thematic content discussed
- Interventions used by the therapist, with method identification (cognitive-behavioral, psychodynamic, etc.)
- Individual progress notes for each participant addressing their engagement and clinical response
- Risk management documentation — any adverse events, breaches of confidentiality, or deviations from treatment plan
- Signatures and credentials of all treating providers present during the session
The Individual Progress Problem
This is where most people fail. You cannot document group therapy adequately by writing one generic paragraph and moving on. Every participant needs an individual progress note tied to the group session. This does not mean writing separate full-length notes for each person. It means documenting each participant's specific clinical engagement: their stated goals addressed, their observed behaviors, their level of participation, and any clinical risks identified. When I was reviewing my own notes years ago, I caught myself using vague language like "group worked well today" in individual progress sections. That is not documentation. That is placeholder text. Auditors reject it. Payers deny claims based on it. I switched to a structured format: one sentence per participant covering their specific behavior, clinical relevance, and progress toward treatment objectives. It takes about four minutes per person for a twelve-person group instead of the fifteen minutes I used to spend trying to write something more elaborate that would not hold up under review.
Get the Full Details

Modality Codes and Payer Confusion
One thing beginners consistently get wrong is the difference between group modality codes and individual therapy codes on insurance claims. G0436, 90846, and 90853 are commonly used, but they are not interchangeable. G0436 requires a qualified physical or occupational therapist setting. 90846 and 90853 are for mental health clinicians, and 90846 requires at least two participants plus the therapist. Some payers will deny a claim if the documentation does not reference the specific intervention methods used during the group session. This means your note must explicitly describe what therapeutic techniques were employed, not just what topic was discussed. I had a situation where a payer denied reimbursement for an entire group session because the note described the content — "patients discussed coping strategies" — without documenting the intervention method. The denial letter cited insufficient evidence of medical necessity. I resubmitted with a corrected note that specified each technique used, referenced the treatment plan objective, and included the modality code. It took three weeks to resolve. The lesson is straightforward: document the method, not just the material.
Risk Management Documentation
Group therapy carries inherent risks that individual therapy does not. Confidentiality breaches between members, emotional escalation, boundary violations, and safety concerns during sessions all require explicit documentation. When I started practicing, I did not document confidentiality discussions until a participant filed a complaint about another member sharing information outside the group. The complaint triggered a licensing board inquiry, and I had no record of whether I had actually addressed confidentiality at the start of the session or what protocols I had established. That experience forced me to create a standard confidentiality protocol section that appears in every group note going forward. Your documentation should include:
- Opening confidentiality agreements reviewed at session start
- Any confidentiality breaches reported during the session
- Actions taken in response to breaches
- Safety assessments for each participant
- Any deviations from the established treatment plan
Practical Structure That Works
I use a hybrid format that satisfies both clinical and administrative requirements without creating excessive documentation burden. The note contains a header section with logistics and attendance, a body section covering group process and interventions, and an individual progress subsection for each participant. I keep the individual progress section brief but clinically substantive. Each participant gets two or three sentences maximum. The key insight is that the group process section serves dual purposes. It documents the therapeutic work and creates the clinical context that supports each individual progress note. When an auditor reads the group process observation about a participant, they should be able to see how that observation connects to the individual progress note for the same person. If the connection is unclear, the documentation is incomplete.
Limitations and Common Failures
This approach has limitations. It requires disciplined note-writing habits that many clinicians do not maintain under heavy caseloads. It also depends on accurate real-time attendance tracking, which is difficult in drop-in or walk-in group settings. When I managed a high-turnover community group, attendance discrepancies became a recurring problem. People arrived late, left early, or missed sessions without notice. My workaround was implementing a real-time attendance log maintained by a co-therapist or administrative staff member, with the treating clinician verifying and signing it at session close. This reduced attendance errors from approximately 15% of sessions to under 3%. Another limitation is that some electronic health record systems do not support the individual progress note structure required for group documentation. You may need to use supplemental documentation templates or custom fields. I have seen clinicians attempt to fit group documentation into individual note templates, which creates compliance gaps that become obvious during audits.
Where to Find Official Guidance
Documentation requirements vary by state, payer, and credential type. Your primary sources should be your state licensing board's regulations, your professional organization's documentation guidelines, and your contracted payer's provider manual. The American Psychological Association, American Counseling Association, and National Association of Social Workers all publish documentation standards relevant to group therapy. Insurance payers post current coverage policies on their provider portals. Billing codes and documentation requirements change regularly, so you should verify current standards quarterly rather than annually. The most practical resource I found was maintaining a single reference document that consolidated state requirements, payer-specific rules, and my own internal documentation checklist. When requirements changed, I updated the document rather than searching multiple sources each time. This reduced the time spent on compliance research from several hours per quarter to under thirty minutes.
Summary of Key Points
Group therapy documentation requires specific elements that differ from individual therapy notes. You need documented group process observations, individual progress for each participant, explicit intervention methods, risk management records, and accurate attendance tracking. The documentation must withstand scrutiny from licensing boards, auditors, and payers simultaneously. Structured notes that connect group observations to individual progress create defensible records. Real-time attendance logs and consolidated reference materials address the most common practical failures. Documentation standards evolve, so regular verification of current requirements is necessary rather than relying on established practice patterns alone.



