.png)
Building a Group Therapy Notes Template That Actually Survives Real Sessions
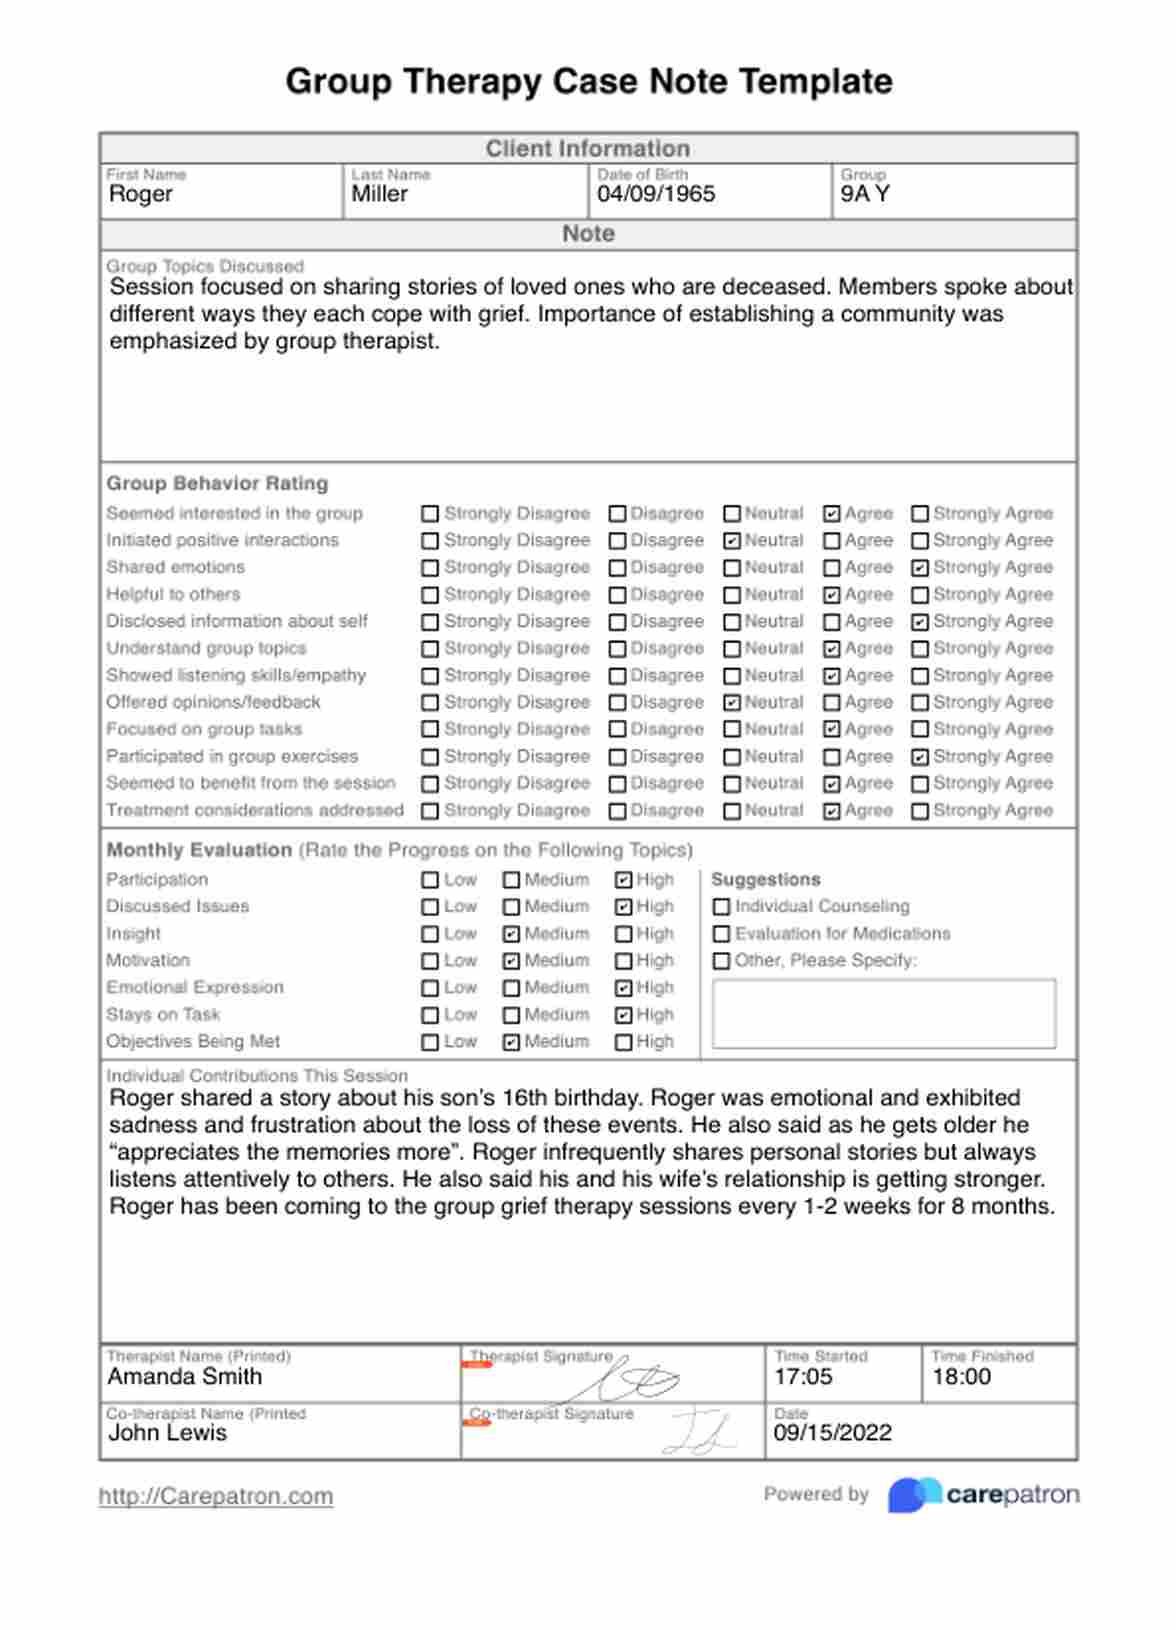
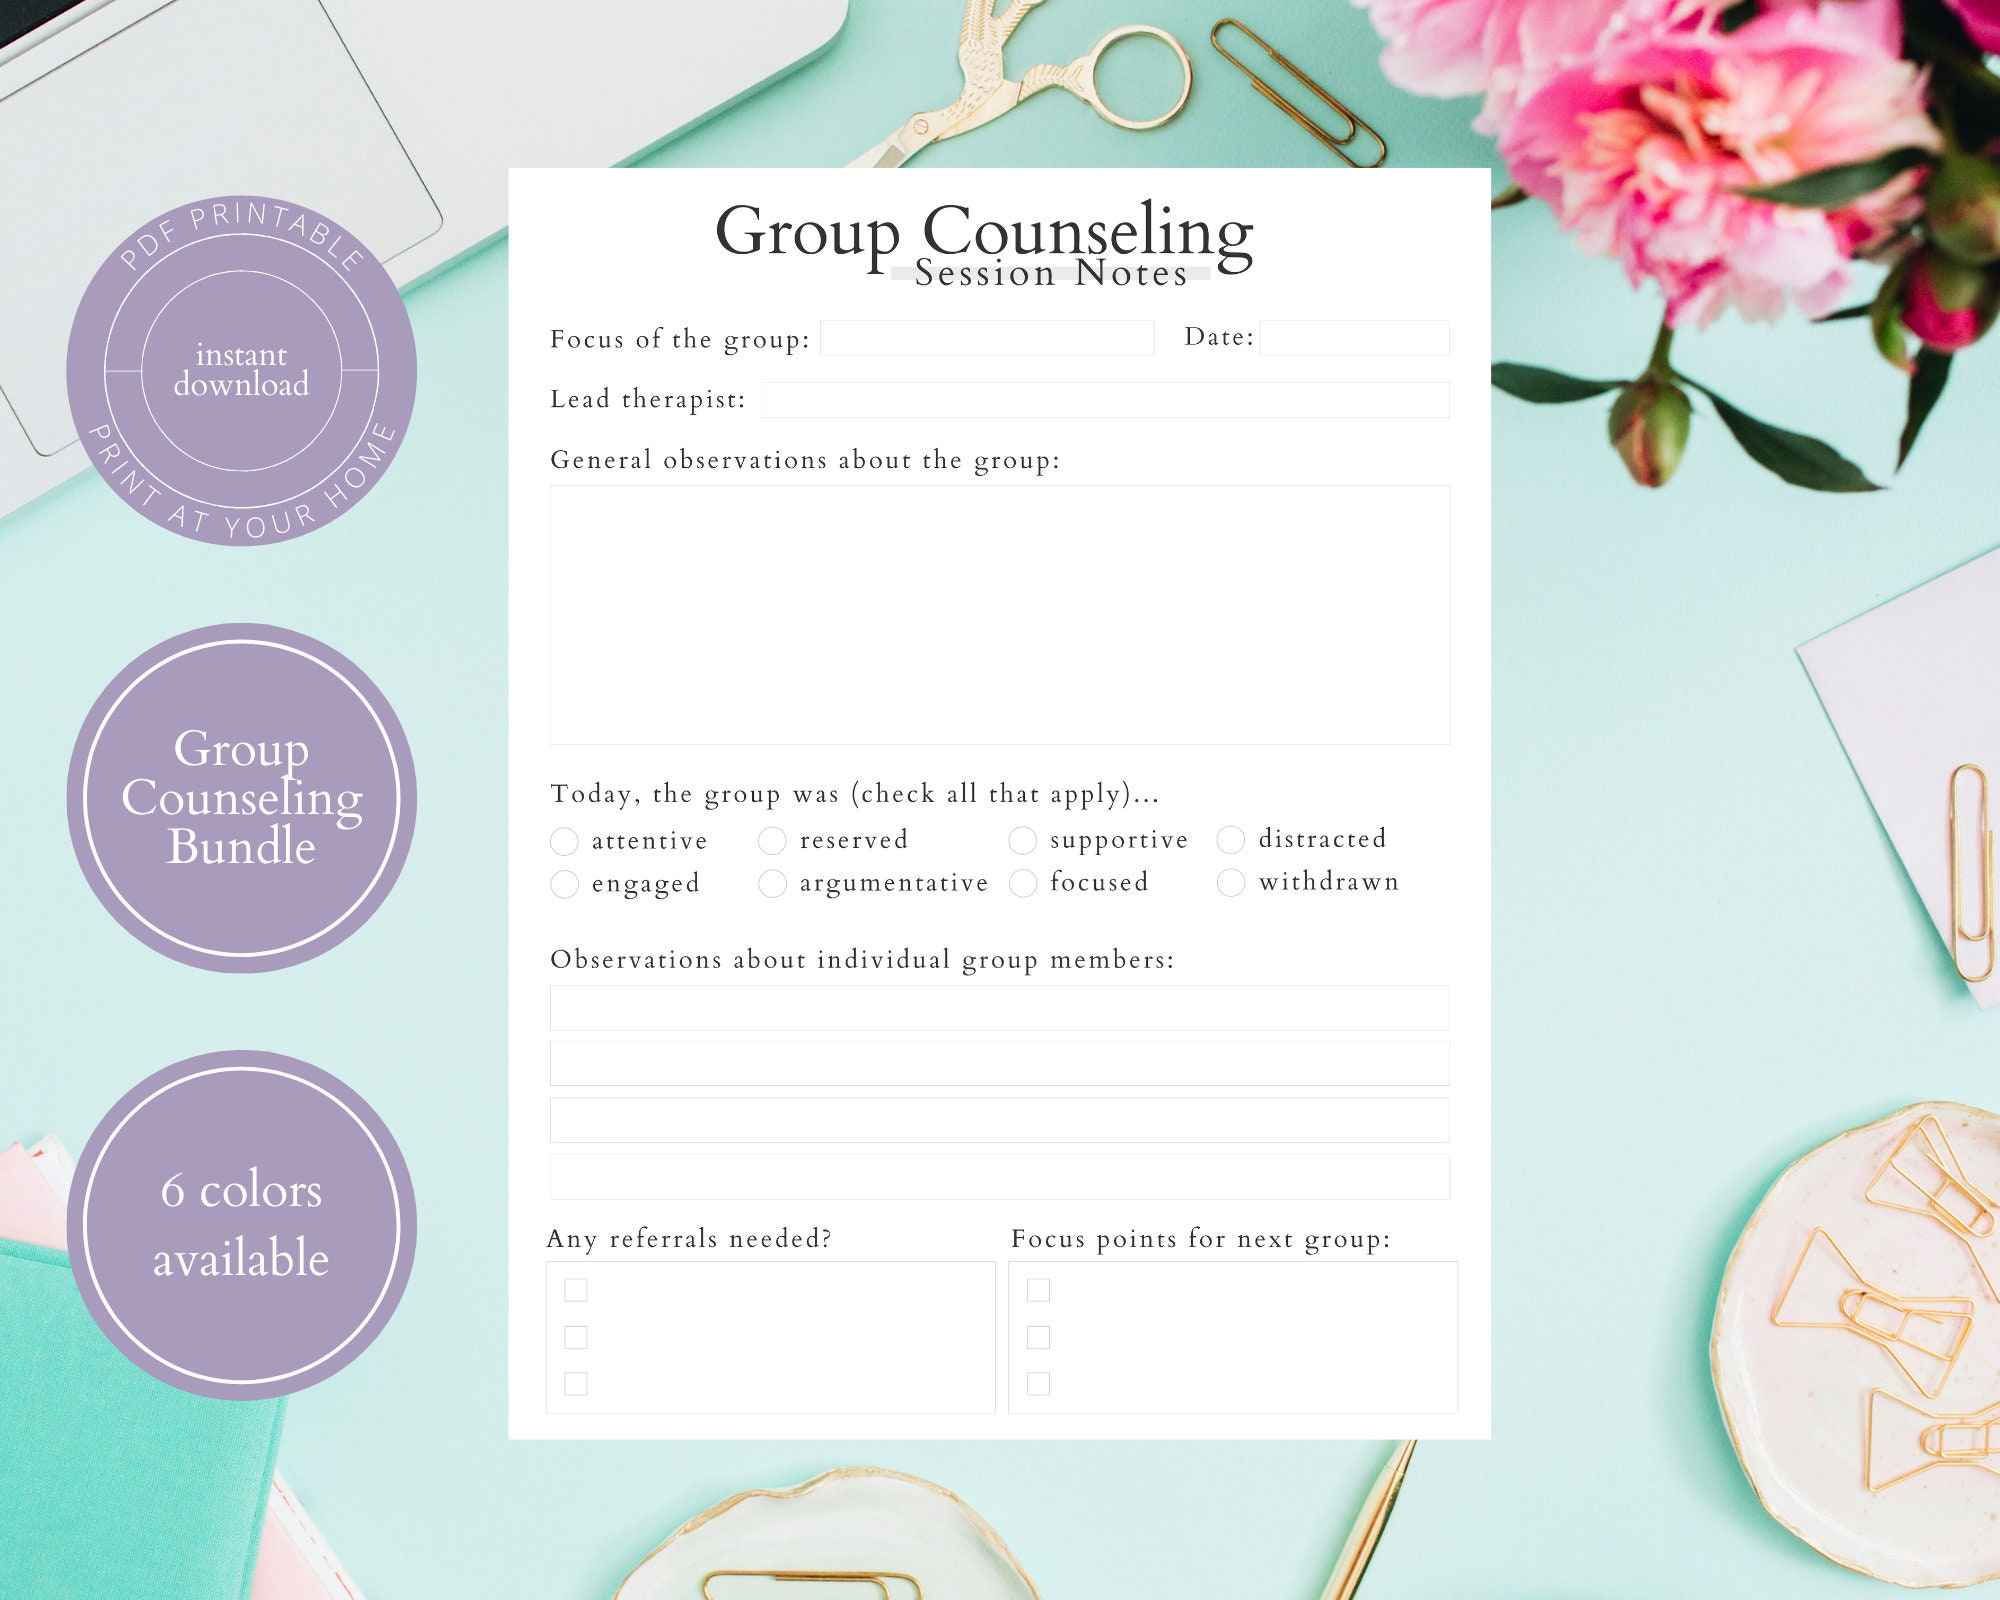
Most people approach group therapy documentation the wrong way. They start by finding a generic clinical note template and tacking "group" onto it. That produces something clunky that misses the whole point of what actually happens in a group room, so the note becomes a compliance exercise rather than a useful record. Here is the structure I settled on after trying about six different approaches over several years. It covers the essentials without ballooning into something you will never fill out.Group Therapy Notes Template
Session Header Date, start/end time, setting (in-person/telehealth), facilitator name(s), co-facilitator if present. Room or platform identifier. This sounds trivial but it matters when you have a third-party auditor pulling records six months later. Presenting Group
Group name or focus, stage designation (forming/storming/norming/performing/adjourning or your own framework), total members present, attendance changes since last session, any new members joining or members who left mid-stream. Roland Content Log This is the section people skip and then regret. List the main themes that emerged during the session, not as a verbatim transcript but as a running log of what was addressed, in rough chronological order. Two to five bullet points is usually enough. If someone monopolized the room for thirty minutes, note it here.
Individual Participation Summary One paragraph per member, covering engagement level, response to prompts, notable disclosures, and any risk indicators. Keep it tight. I stopped writing full narratives for each person and switched to a structured format: participation rating (engaged/minimal/absent), any clinically significant material, and any safety concerns flagged for that individual. Interventions Used
Get the Full Details
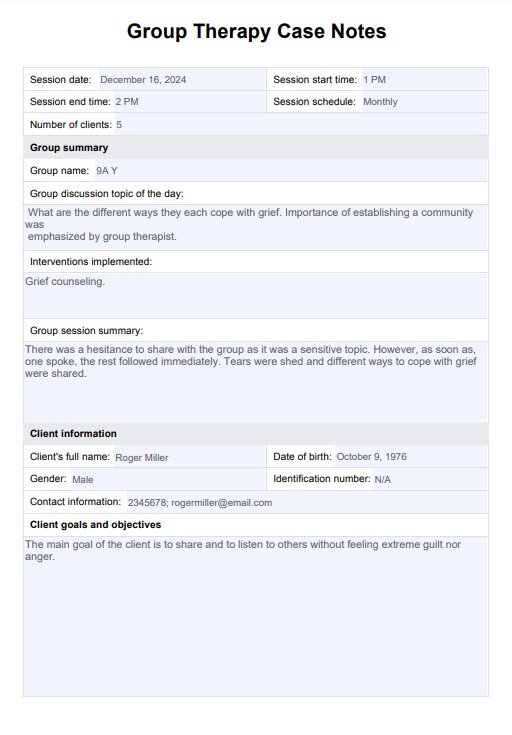
List the specific techniques applied. Role-play, psychodrama excerpt, psychoeducation segment, processing of a group conflict, behavioral rehearsal, homework review. This section connects directly to billing codes and treatment plan alignment. Include the primary intervention and its clinical purpose. Group Process Observations This is the part that actually separates a group note from twelve individual notes stapled together. Note dynamics: alliances, triangulation, scapegoating patterns, cohesion shifts, resistance themes. If the group bypassed a conflict to stay polite, write that down. Process is the therapeutic engine in group work and it is also the thing most likely to vanish from the record if you are not deliberate about capturing it.
Risk and Safety Assessment Any suicidal ideation, homicidal ideation, disclosure of abuse, substance use relapse, or decompensation observed or reported during the session. This is non-negotiable documentation regardless of how routine the session felt. Include what you did in response, not just the presence or absence of risk. Treatment Plan Correlation
Which treatment plan objectives were addressed this session? Cross-reference the goal number and brief description. If nothing from the treatment plan came up, say so and explain what replaced it. Auditors look for this alignment specifically. Homework and Follow-Up Assignments given, members who completed them, assignments deferred, planned focus for next session. If a member was promised a follow-up check between sessions, document the promise and the follow-through plan.

Clinician Signature and Credentials Standard sign-off. Date and time of note completion.
The practical reason this structure works comes down to time management. A session runs fifty to ninety minutes. You have roughly ten to fifteen minutes afterward to complete the note before the next group arrives or before you lose the thread. Any template that requires paragraphs per person or a full process narrative will force you to either rush through later that night or cut corners. The structure above typically takes about twelve minutes to complete for a standard session, give or take depending on complexity. I ran into a specific problem that forced me to rework this template entirely. I was running a trauma-informed support group where two members had a history of prior interpersonal conflict outside the group. During one session, they avoided direct interaction almost entirely, redirecting every conversation through a third member. The note template I was using had no field for tracking indirect interaction patterns or relational triangulation between specific participants. The resulting note read like a list of topics discussed, which was clinically useless for anyone reviewing the record later. I added a dedicated sub-section called "Relational Dynamics Between Specific Members" with a free-text line. It only fills out when relevant, which keeps the baseline template lean, but it captured the exact dynamic I needed to document and track across sessions. That section now appears in roughly one out of every five sessions I run, but when it does, it is the most useful part of the entire note. There is a common mistake beginners make with group notes that I want to flag. People conflate content summary with process observation. Writing "the group discussed anxiety about upcoming exams" is content. Writing "the group validated a member's academic stress and the facilitator redirected the focus toward coping strategies rather than problem-solving" is process. Both can appear in the same note, but they serve different purposes. Content summaries help with continuity. Process notes demonstrate clinical reasoning and justify the group modality itself. If you are only documenting content, you are not really documenting group therapy. Another counter-intuitive point: leaving members out of the individual participation summary when they were quiet can actually create a liability issue. A blank space reads like you did not notice them or did not document them, not as an intentional clinical choice. I now default to a one-line notation for every present member, even if it simply states "present but minimally engaged; no clinical concerns observed." It adds about thirty seconds per person and eliminates ambiguity. Limitations worth being honest about. This template assumes you have a reasonable amount of time between sessions to document. If you are running back-to-back groups with a two-minute turnover, it does not work well. In that scenario, a streamlined version with only the essentials—presenting group, interventions, risk assessment, and signature—is more realistic, though it sacrifices process depth. There is also a ceiling to how much group process you can capture in ten minutes without becoming a stenographer. If the group is highly complex with multiple simultaneous conflicts and significant clinical material, the note will either be rushed or incomplete. For those sessions, I recommend filing a brief contemporaneous summary immediately after and expanding it within twenty-four hours while the details are still fresh. No template fixes the problem of insufficient documentation time. Billing alignment deserves its own mention. The Group Therapy Notes Template should map directly to CPT code 90853 for group psychotherapy, or the appropriate telehealth variant with modifiers as applicable. Some payers require specific documentation elements for group therapy claims, including the number of participants, the modalities used, and evidence of group process intervention. If your notes do not reference process explicitly, you may get a denial for lack of medical necessity for the group modality specifically. This has happened to me with two different payers in separate instances. Making sure the "Group Process Observations" and "Interventions Used" sections are consistently populated is the simplest way to avoid that. Telehealth adds a small complication. Eye contact cues, side conversations, and nonverbal group dynamics translate differently over video. I now include a brief notation about the telehealth format and any limitations it imposed on observation, especially if a member appeared disengaged and it could not be verified whether they were truly absent from the interaction or simply camera-off. It is a minor addition but it has saved me from mischaracterizing behavior that was an artifact of the medium rather than a clinical signal. If you are building this from scratch rather than adapting an existing template, start with the structure above and test it on three consecutive sessions. You will quickly identify which sections you consistently skip and which ones you actually find useful. The sections that survive that test are the ones worth keeping. The rest can be trimmed without losing clinical or legal defensibility.