Most people think medical billing starts with submitting a claim. It doesn't. It starts with charge capture, and that's where the entire process either stays intact or falls apart within the first forty-five seconds of a patient encounter. I've sat in on audits where a single missed modifier on a diabetes code cascade cost a practice twelve thousand dollars in delayed reimbursements over six months. The fix wasn't complicated. They just needed a better front-desk checklist and a second set of eyes on the superbill before it ever left the room.
Getting Started With a Guide For Medical Billing
A proper guide for medical billing should walk you through the entire pipeline, from registration to remittance. What you'll find online usually skips the boring middle parts—the ones that actually matter. Let me fill that gap.
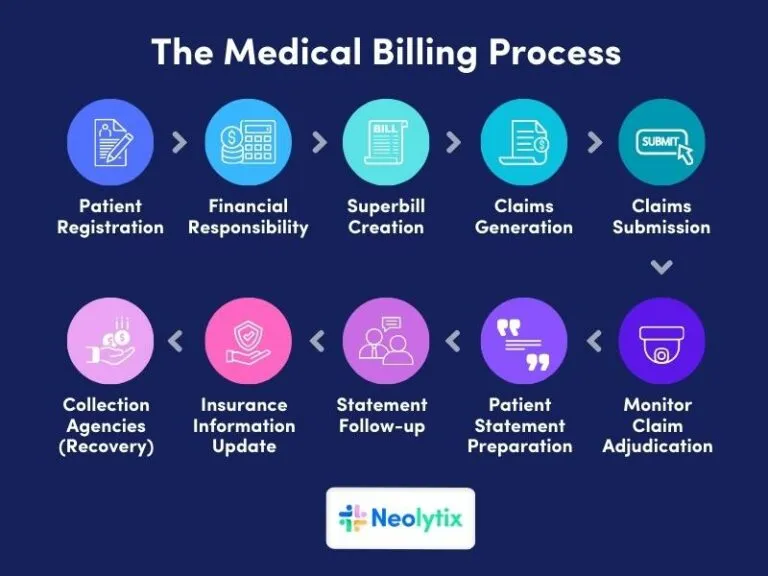
The pipeline runs like this: patient registration, insurance verification, charge entry, coding, claim submission, denial management, payment posting, and accounts receivable follow-up. Each step hands off to the next, and each handoff is a place where errors stack up. The trick isn't perfection at any single step. It's making sure the handoffs don't drop anything.
Here's what that looks like in practice. You register the patient and pull their insurance information in real time using a verification tool, not a printed card they handed you three years ago. A lot of people skip the real-time check because it takes twenty seconds. Those twenty seconds will save you three hours of denial chasing later. I learned this the hard way when a clinic I consulted for was consistently denied claims from a specific payer because the policy holders had switched plans mid-year and nobody updated the front desk. We implemented a daily automated eligibility check and the denial rate from that payer dropped from eleven percent to under two percent in the first billing cycle.
Charge entry happens after the visit. The provider documents the encounter, and someone—often the same person doing scheduling—translates that into CPT and ICD-10 codes. This is where most small practices bleed money. They use default code bundles that don't match what actually happened. If a patient comes in for a routine follow-up on hypertension and the coder just slaps on an E11.9 with an M99.09 because the chart mentioned back pain, you're leaving legitimate reimbursement on the table or worse, you're building an audit trail that looks reckless.
I handled a case last year where a provider was getting paged by a compliance officer because his chronic care management codes didn't align with his documented time entries. The CCM code required sixty minutes of non-face-to-face clinical staff time per month. His notes showed fifteen. He wasn't billing fraudulently, he was just sloppy with his documentation. The fix was a template update that forced the coder to cross-reference the time log before finalizing the claim. Took him an afternoon. Saved him from what could have been a serious issue.
Coding itself has gotten more complex in recent years. The shift to ICD-10 was just the beginning. Now you're dealing with MACRA, MIPS, specific payer policies that vary by state, and modifier stacking that can make your head spin if you're not careful. Modifiers like 25, 59, and XE/XS are the most commonly abused in my experience. A modifier 25 appended to an evaluation and management visit on the same day as a minor procedure should only happen when the E/M is genuinely separate and significant. If you're appending it to every visit just because, payers will notice. They have software for that now.
Claim Submission and What Actually Happens After
Once the claim is built, it goes out electronically through a clearinghouse. The clearinghouse does a basic scrub—checking for missing fields, invalid code combinations, format errors. If it passes, it routes to the payer. If it fails, you get an error message and have to fix it before resubmitting.
This is where the rubber meets the road. A clean claim rate above ninety-five percent is what you're aiming for. Anything below that and you're working too hard for too little money. Clean claim rate means the payer accepted it on the first try, no manual intervention needed. Most practices I talk to are sitting around eighty-two to eighty-eight percent. The difference between eighty-eight and ninety-six is usually just faster denial response and better front-end work.
When a denial comes in—and it will, even with perfect coding—you don't just resubmit it. You analyze the denial reason code. Common ones: CO-16 means missing information, CO-97 means not medically necessary, CO-50 means the service is a subset of another service already billed. Each one requires a different approach. A CO-16 denial might need a corrected form. A CO-97 needs a peer-to-peer review or additional documentation. A CO-50 means you bundled incorrectly and need to unbundled properly.
I keep a spreadsheet of denial reasons by payer. After six months of data, patterns emerge. One payer was denying ninety percent of our diabetes panel claims because they required a specific diagnostic code sequence. Once I figured out the pattern, I adjusted our encoder settings and those denials basically disappeared. That kind of payer-specific intelligence is what separates people who grind through billing from people who actually manage it.
Payment Posting and AR Follow-Up
Payment posting is the process of matching what the payer sent to what you expected to receive. Modern practice management software auto-posts a lot of this, but automatic posting is wrong more often than people think. I've seen entire months of postings skewed because the software misapplied a contractual adjustment or split a single payment across three claims incorrectly. Do a manual spot-check every week. It takes about twenty minutes and will catch errors before they compound.
Accounts receivable is your true north metric. If your AR days are above forty-five, you have a problem. Under thirty days is competitive. The formula is simple: total net charges divided by average daily billing. But the number alone doesn't tell you much. You need to break it down by aging bucket. Claims over ninety days old recover at a fraction of their value. At one hundred twenty days, you're lucky to collect thirty percent. At that point, the cost of chasing often exceeds the reimbursement itself.
I had a clinic client who was sitting at sixty-eight AR days. They were so behind on follow-up that their collections team was essentially playing whack-a-mole with new denials while old ones festered. We reorganized their workflow: daily denial review, immediate resubmission within twenty-four hours, and a strict sixty-day write-off policy for unrecoverable balances. Within ninety days, AR days dropped to thirty-four. Revenue increased by eighteen percent, not because they billed more, but because they collected what they were already owed.
When This Approach Breaks Down
Medical billing is not a set-and-forget system. It requires ongoing attention, and there are scenarios where even the best processes stall out. Small practices with fewer than five providers often can't justify a dedicated biller. They outsource. That's fine if they pick the right vendor, but a lot of them pick based on price alone. The cheapest billing company you'll find is the one that's processing your claims with the least amount of oversight. You get volume discounts on their end by cutting corners on yours.
Software itself has limitations. Some practice management systems handle certain specialties poorly. If you're a behavioral health provider using a system designed for general practice, you'll run into trouble with DSM-5 code sets and mental health parity billing requirements. If you're a physical therapist, you need therapy modifier tracking and visit count management built in, not bolted on. Buying software without testing it against your actual claim types is a mistake I see repeatedly.
Payer contracts are another area where things fall apart quietly. If your contract says eighty percent of allowed charges and the payer is paying seventy-five, you're losing money on every single claim and you might not notice for months. Annual contract audits catch this, but most practices never do one.
What Actually Moves the Needle
If you want a practical starting point, focus on three things first. Clean claim rate. Days in AR. Denial rate by reason code. Track these monthly. If clean claim rate is below ninety percent, fix your front-end registration and coding processes before you touch anything else. If AR days are above forty-five, fix your follow-up workflow. If denial rate is high, start categorizing denials and address the top three reasons.
There's no shortcut around doing the work. The systems and software help, but they're tools, not solutions. The people running them make the difference. I've seen impressive software fail because the staff treating it like a black box, and I've seen basic spreadsheets work well because someone was paying attention to the numbers every single day.
Gallery Guide For Medical Billing
What Is Medical Billing? The Complete 2026 Guide for Doctors
Guide to Medical Billing for Small Practices
Medical Billing Process: A Step-by-Step Guide
A Step-by-Step Hospital Medical Billing Guide | PDF
A Step-by-Step Hospital Medical Billing Guide | PDF