What H Pylori Quadruple Therapy Actually Looks Like In Practice
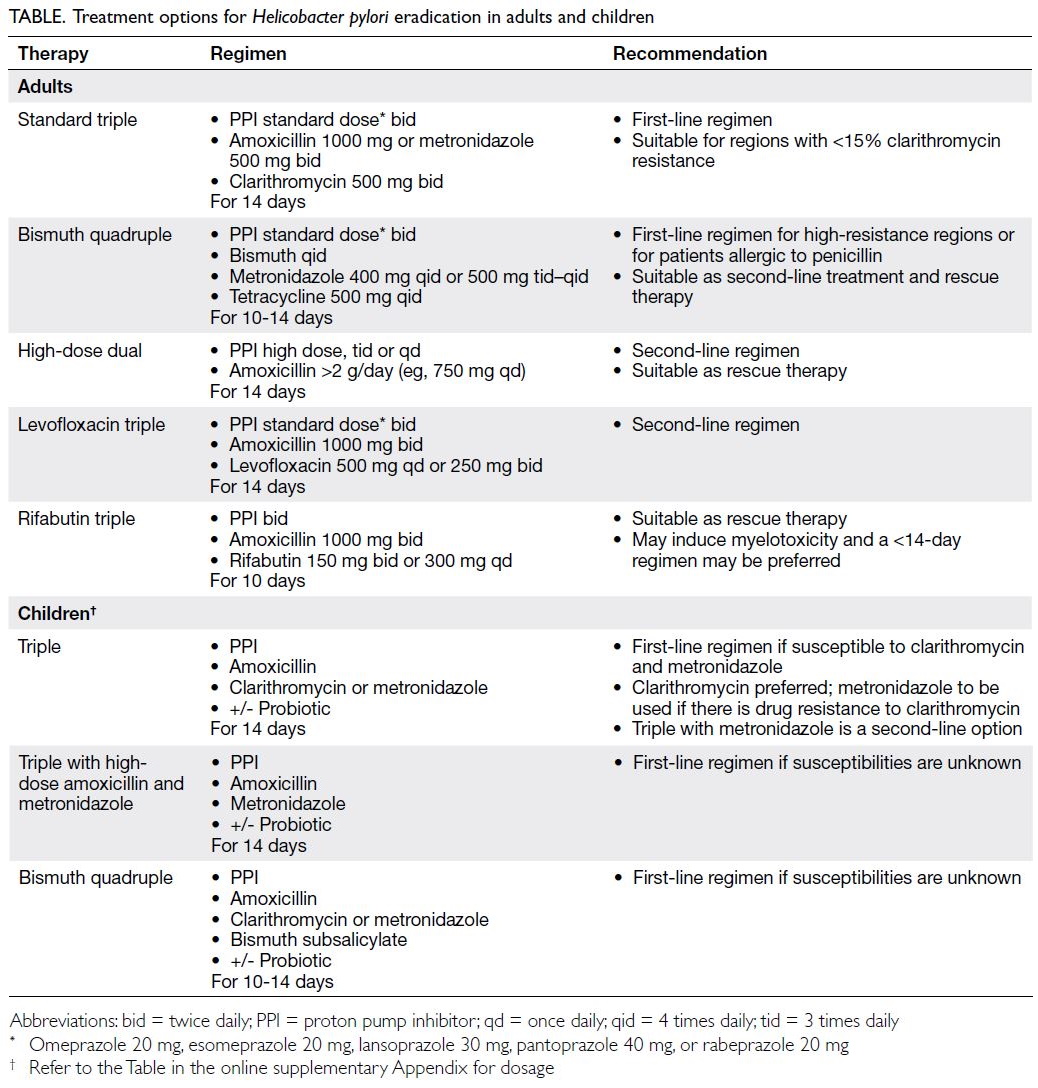
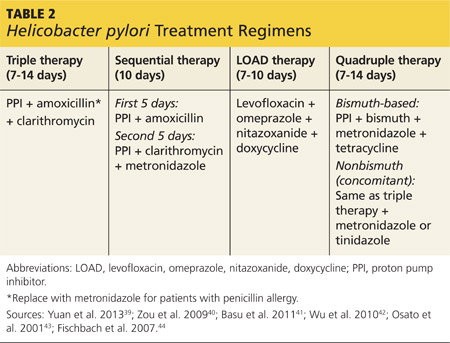
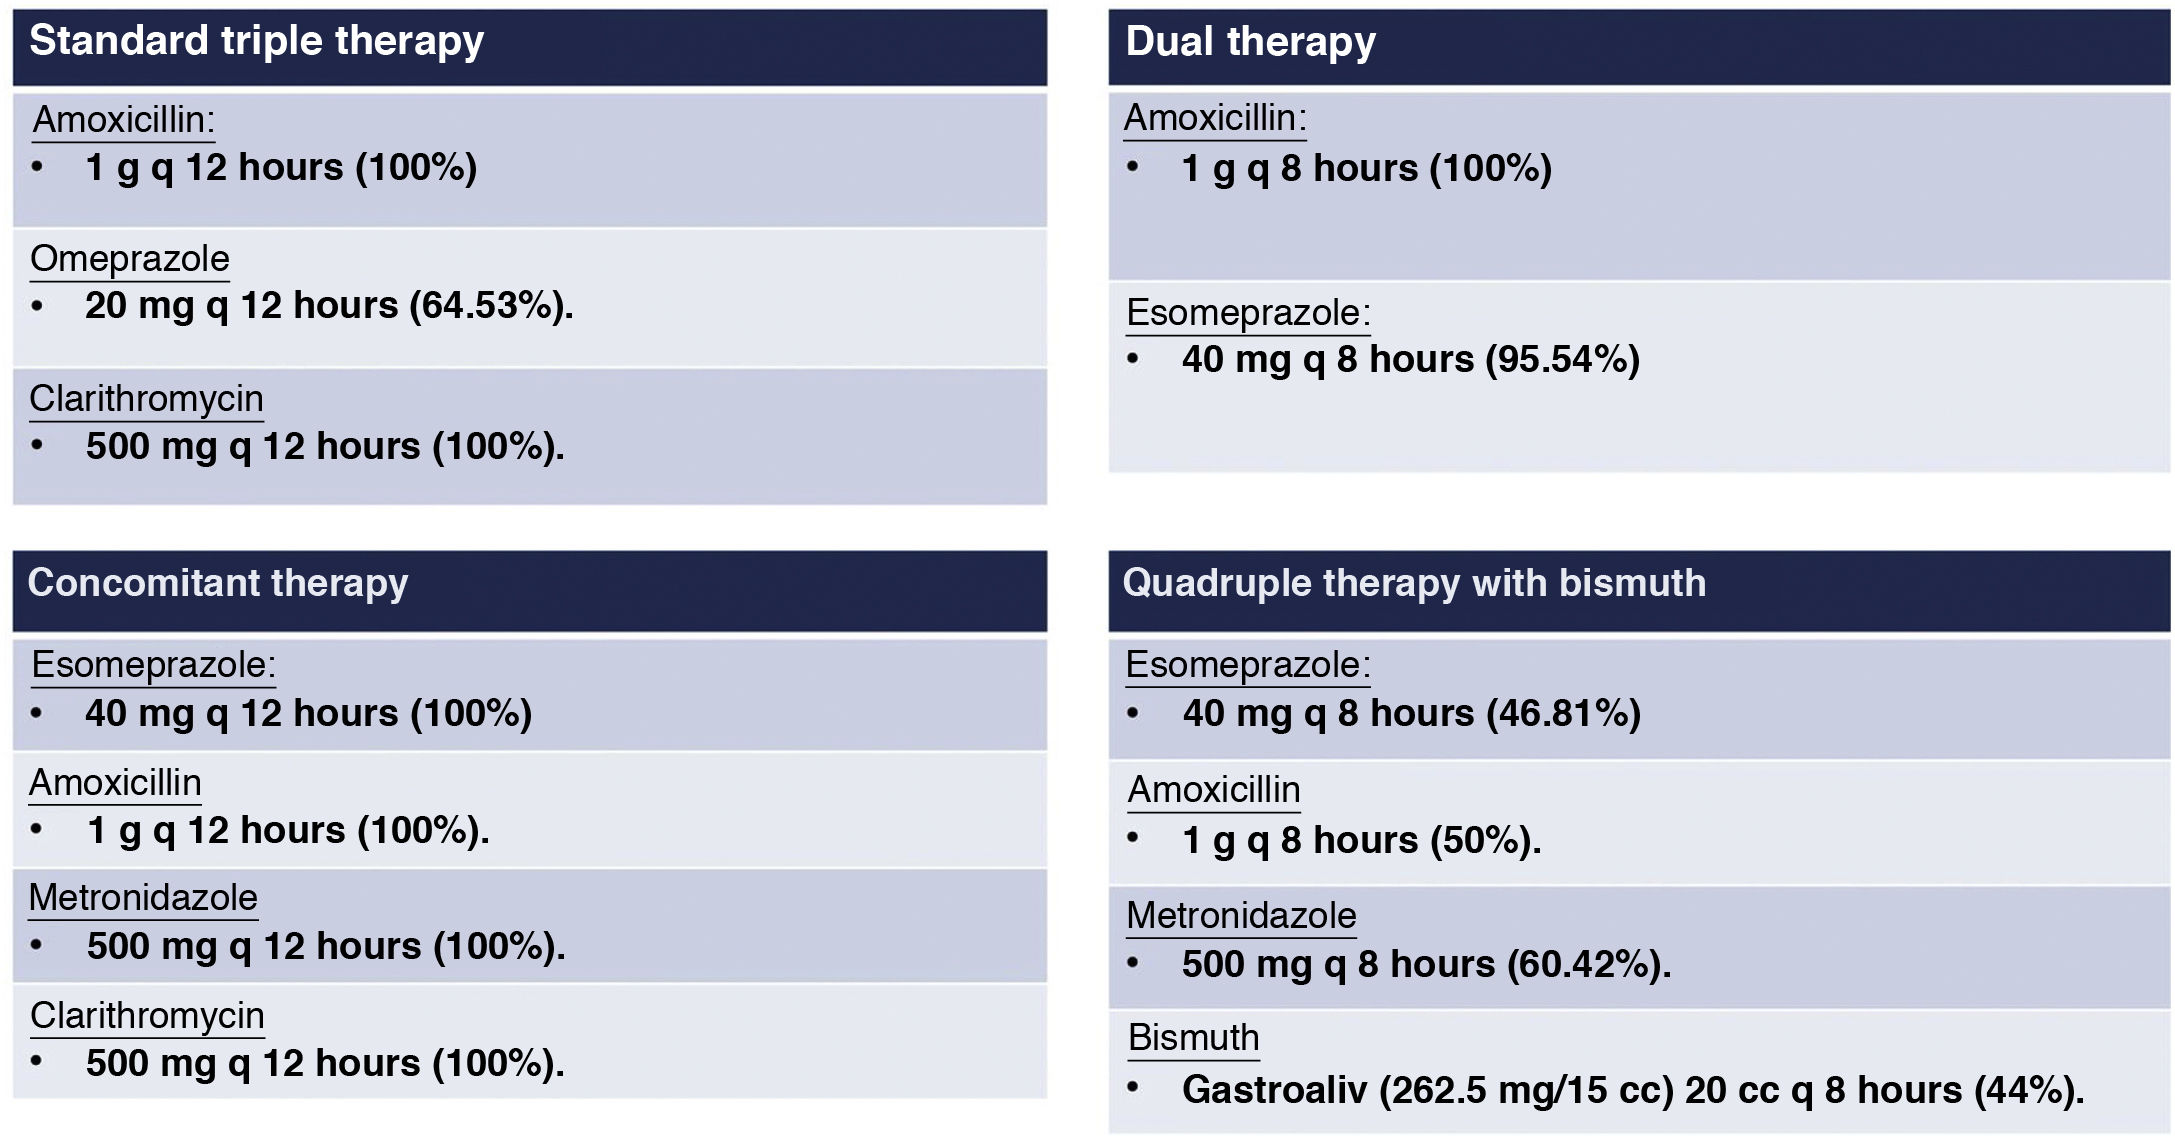
The standard bismuth quadruple therapy for H pylori is a 10 to 14 day regimen that most gastroenterologists prescribe when first-line clarithromycin-based therapy has failed or when local resistance rates are high. The four drugs are bismuth subsalicylate or bismuth subcitrate, metronidazole, tetracycline, and a proton pump inhibitor. In the United States, the most common prescription format is bismuth subsalicylate 525 mg four times daily, metronidazole 250 to 500 mg four times daily, tetracycline 500 mg four times daily, and a PPI such as omeprazole 20 mg twice daily or esomeprazole 40 mg once daily. The exact PPI dosing depends on the agent and whether you are using the brand or generic version. Bismuth subsalicylate: 525 mg orally four times a day, taken with meals and at bedtime. This gives roughly 2.1 grams per day. If you are using colloidal bismuth subcitrate instead, the dose is typically 120 mg four times daily. The two are not milligram-equivalent. Substituting one for the other without adjusting the dose is a common error. Metronidazole: 250 mg to 500 mg four times daily. The 500 mg four times daily dose is more widely used in clinical trials and tends to produce higher eradication rates, especially when resistance is suspected. I have seen patients on the lower dose fail to clear the infection and require retreatment. The trade-off is more side effects. Metallic taste, nausea, and disulfiram-like reactions with alcohol are standard complaints.
Tetracycline: 500 mg four times daily. This is a total daily dose of 2 grams. Tetracycline is the preferred tetracycline-class drug here. Doxycycline is not a reliable substitute in this regimen. The evidence for doxycycline as a replacement is weak and eradication rates drop noticeably. Take it on an empty stomach if possible, but if gastrite makes that intolerable, food is acceptable. Just avoid dairy within two hours of the dose because calcium binds the drug and cuts absorption significantly. Proton pump inhibitor: Standard dose twice daily is typical. Omeprazole 20 mg twice daily, esomeprazole 40 mg twice daily, or pantoprazole 40 mg twice daily. The acid suppression is not just symptom control. It raises gastric pH to a level where both bismuth and the antibiotics work better. Bismuth has direct anti-H pylori activity at neutral pH but loses much of its effectiveness in highly acidic conditions. That is why the PPI is non-negotiable in this regimen. The full course runs 10 to 14 days. Fourteen days consistently outperforms 10 days in randomized trials. If your patient can tolerate the pill burden, prescribe the longer course. The compliance drop-off between day 10 and day 14 is real but small compared to the efficacy gain.
Why Compliance Is the Real Bottleneck
Four drugs, four times a day, for two weeks. That is sixteen doses per day. Most patients cannot sustain that schedule. I had a patient who stopped taking the tetracycline after day six because the esophagitis from doing it lying down became unbearable. She did not tell her gastroenterologist. She just stopped. The treatment failed. The urea breath test eight weeks later was still positive. We switched her to a different regimen and it worked, but that is a whole extra cycle of testing and treatment that nobody wants. The workaround I use now is straightforward. I ask patients to take the tetracycline with a full glass of water and stay upright for at least 30 minutes after each dose. I also split the bismuth and metronidazole doses around meals and keep the PPI twice daily regardless of food timing. That simple restructuring cuts the number of pills taken simultaneously and makes the schedule easier to remember. Pill organizers help, but most patients throw those away by day four because the schedule is too complex for a standard seven-day box.
Get the Full Details
When This Regimen Fails And What To Do Next
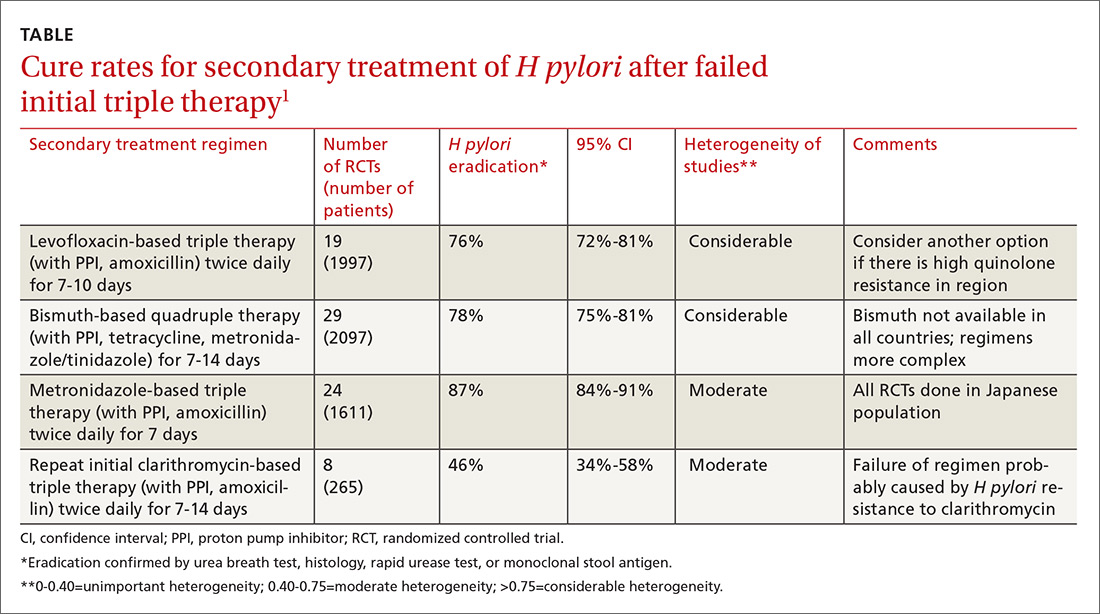
Bismuth quadruple therapy achieves eradication rates between 85 and 95 percent in most recent studies. That sounds good until you remember that the 5 to 15 percent who fail have already exhausted first-line options. Retreatments carry diminishing returns. If the first quadruple course fails, culture and susceptibility testing before the next regimen is the right move. Empirical retreatment without testing in a patient who has already failed two courses wastes time and drives resistance further. I have seen endoscopists skip testing and just prescribe levofloxacin-based triple therapy as salvage. In areas where fluoroquinolone resistance exceeds 15 percent, that approach fails too often. The data are clear. Levofloxacin resistance in H pylori is climbing rapidly across North America and Europe. If you must use a fluoroquinolone, check local resistance patterns first. Many academic centers now publish their regional susceptibility data annually. Use that number. If it is above 15 to 20 percent, do not use levofloxacin empirically.
Drug Interactions Worth Knowing Before You Prescribe
Metronidazole inhibits CYP2C9. This means warfarin levels can rise significantly during the course. I had a patient whose INR jumped from 2.1 to 4.8 while on quadruple therapy because we did not adjust the warfarin dose preemptively. Check baseline INR if the patient is on any vitamin K antagonist. Monitor twice weekly during treatment if possible. The interaction reverses within three to five days after stopping metronidazole, so the monitoring window is short but critical. Tetracycline and isotretinoin should never be combined. Intracranial hypertension is a documented risk. This is rare but severe. If a patient is on oral isotretinoin for acne, quadruple therapy is not an option without coordination between dermatology and gastroenterology. Bismuth subsalicylate contains salicylate. High doses can contribute to salicylate toxicity in patients who are already taking aspirin or NSAIDs regularly. The risk is low at standard quadruple doses but worth noting for elderly patients or those with renal impairment.
Special Populations Require Dose Adjustments
Renal impairment changes the metronidazole clearance curve. In severe renal failure, the half-life extends enough that dosing intervals may need to stretch. Tetracycline is contraindicated in pregnancy and in children under eight years old due to tooth discoloration and bone growth effects. That limitation is why pediatric H pylori treatment often diverges completely from adult protocols. For pregnant patients, the risk-benefit analysis is tough. Bismuth subsalicylate is category C and generally avoided in the third trimester. Colloidal bismuth subcitrate is not widely available in the US, which complicates things further. There is no clean alternative quadruple regimen for pregnant patients. The typical approach is to defer treatment until after delivery unless there is a compelling indication such as bleeding ulcer disease. Test of cure is mandatory. Urea breath test or stool antigen test at least four weeks after finishing antibiotics and two weeks off PPIs. Serology is useless for post-treatment confirmation because antibodies persist for months or years after eradication. I see this mistake repeatedly in follow-up clinics. A positive antibody test six months later is interpreted as treatment failure when the patient is actually cured. The serology result does not distinguish active infection from past exposure. If the test of cure is negative, you are done. No further follow-up is needed unless symptoms persist, in which case consider an alternative diagnosis. If the test is positive, you have failed one quadruple course. The next step should involve susceptibility-guided therapy whenever feasible. The options are limited at that point, which is why getting the first course right matters so much. Dosing accuracy, duration, and compliance are the three variables you can control before the patient even leaves the office.

Cost And Access Considerations
The good news is that every drug in this regimen is available as a generic. Bismuth subsalicylate is over-the-counter in most pharmacies, though many prescribers write a prescription anyway to ensure the patient understands the dosing schedule. Tetracycline and metronidazole are both very inexpensive generics. The PPI cost varies by agent and insurance formulary. Pantoprazole and omeprazole are usually the cheapest options. Esomeprazole costs more but some patients respond better to it due to CYP2C19 metabolism differences. If a patient is a rapid metabolizer, standard omeprazole doses may not suppress acid adequately and the regimen will underperform without any change to the antibiotic dosing. The total out-of-pocket cost for a 14-day course in the US is typically under $50 with a standard insurance plan. Without insurance, it is still very affordable. The real cost is the side effect burden and the time lost to compliance failures. Nobody factors that into the initial conversation with the patient.
Summary Of What Actually Works
Prescribe 14 days, not 10. Use metronidazole 500 mg four times daily unless the patient has a history of significant neurotoxicity. Keep the PPI twice daily. Advise patients to stay upright after tetracycline doses. Check INR if the patient is on warfarin. Test for cure with breath test or stool antigen, not serology. Do not reuse the same regimen if it fails. The margin for error is narrow but the regimen remains one of the most effective options available when given correctly.