How Head-to-Toe Assessments Actually Work in Practice
A head-to-toe assessment documentation sample is what you turn in when you need to show that you systematically evaluated a patient from neurological status down to peripheral circulation. Most people learn the process in school, but the gap between classroom simulation and real clinical work is enormous. The documentation itself needs to reflect that reality or it falls apart under review. I worked in med-surg for years before moving into case management, and honestly the biggest thing I see wrong with head-to-toe assessment documentation samples is that people treat them like checklists. They are not checklists. A checklist implies you can go down the list and circle normal for every category. That works fine for a healthy patient on day two of recovery, but it falls apart fast when you encounter something complicated.
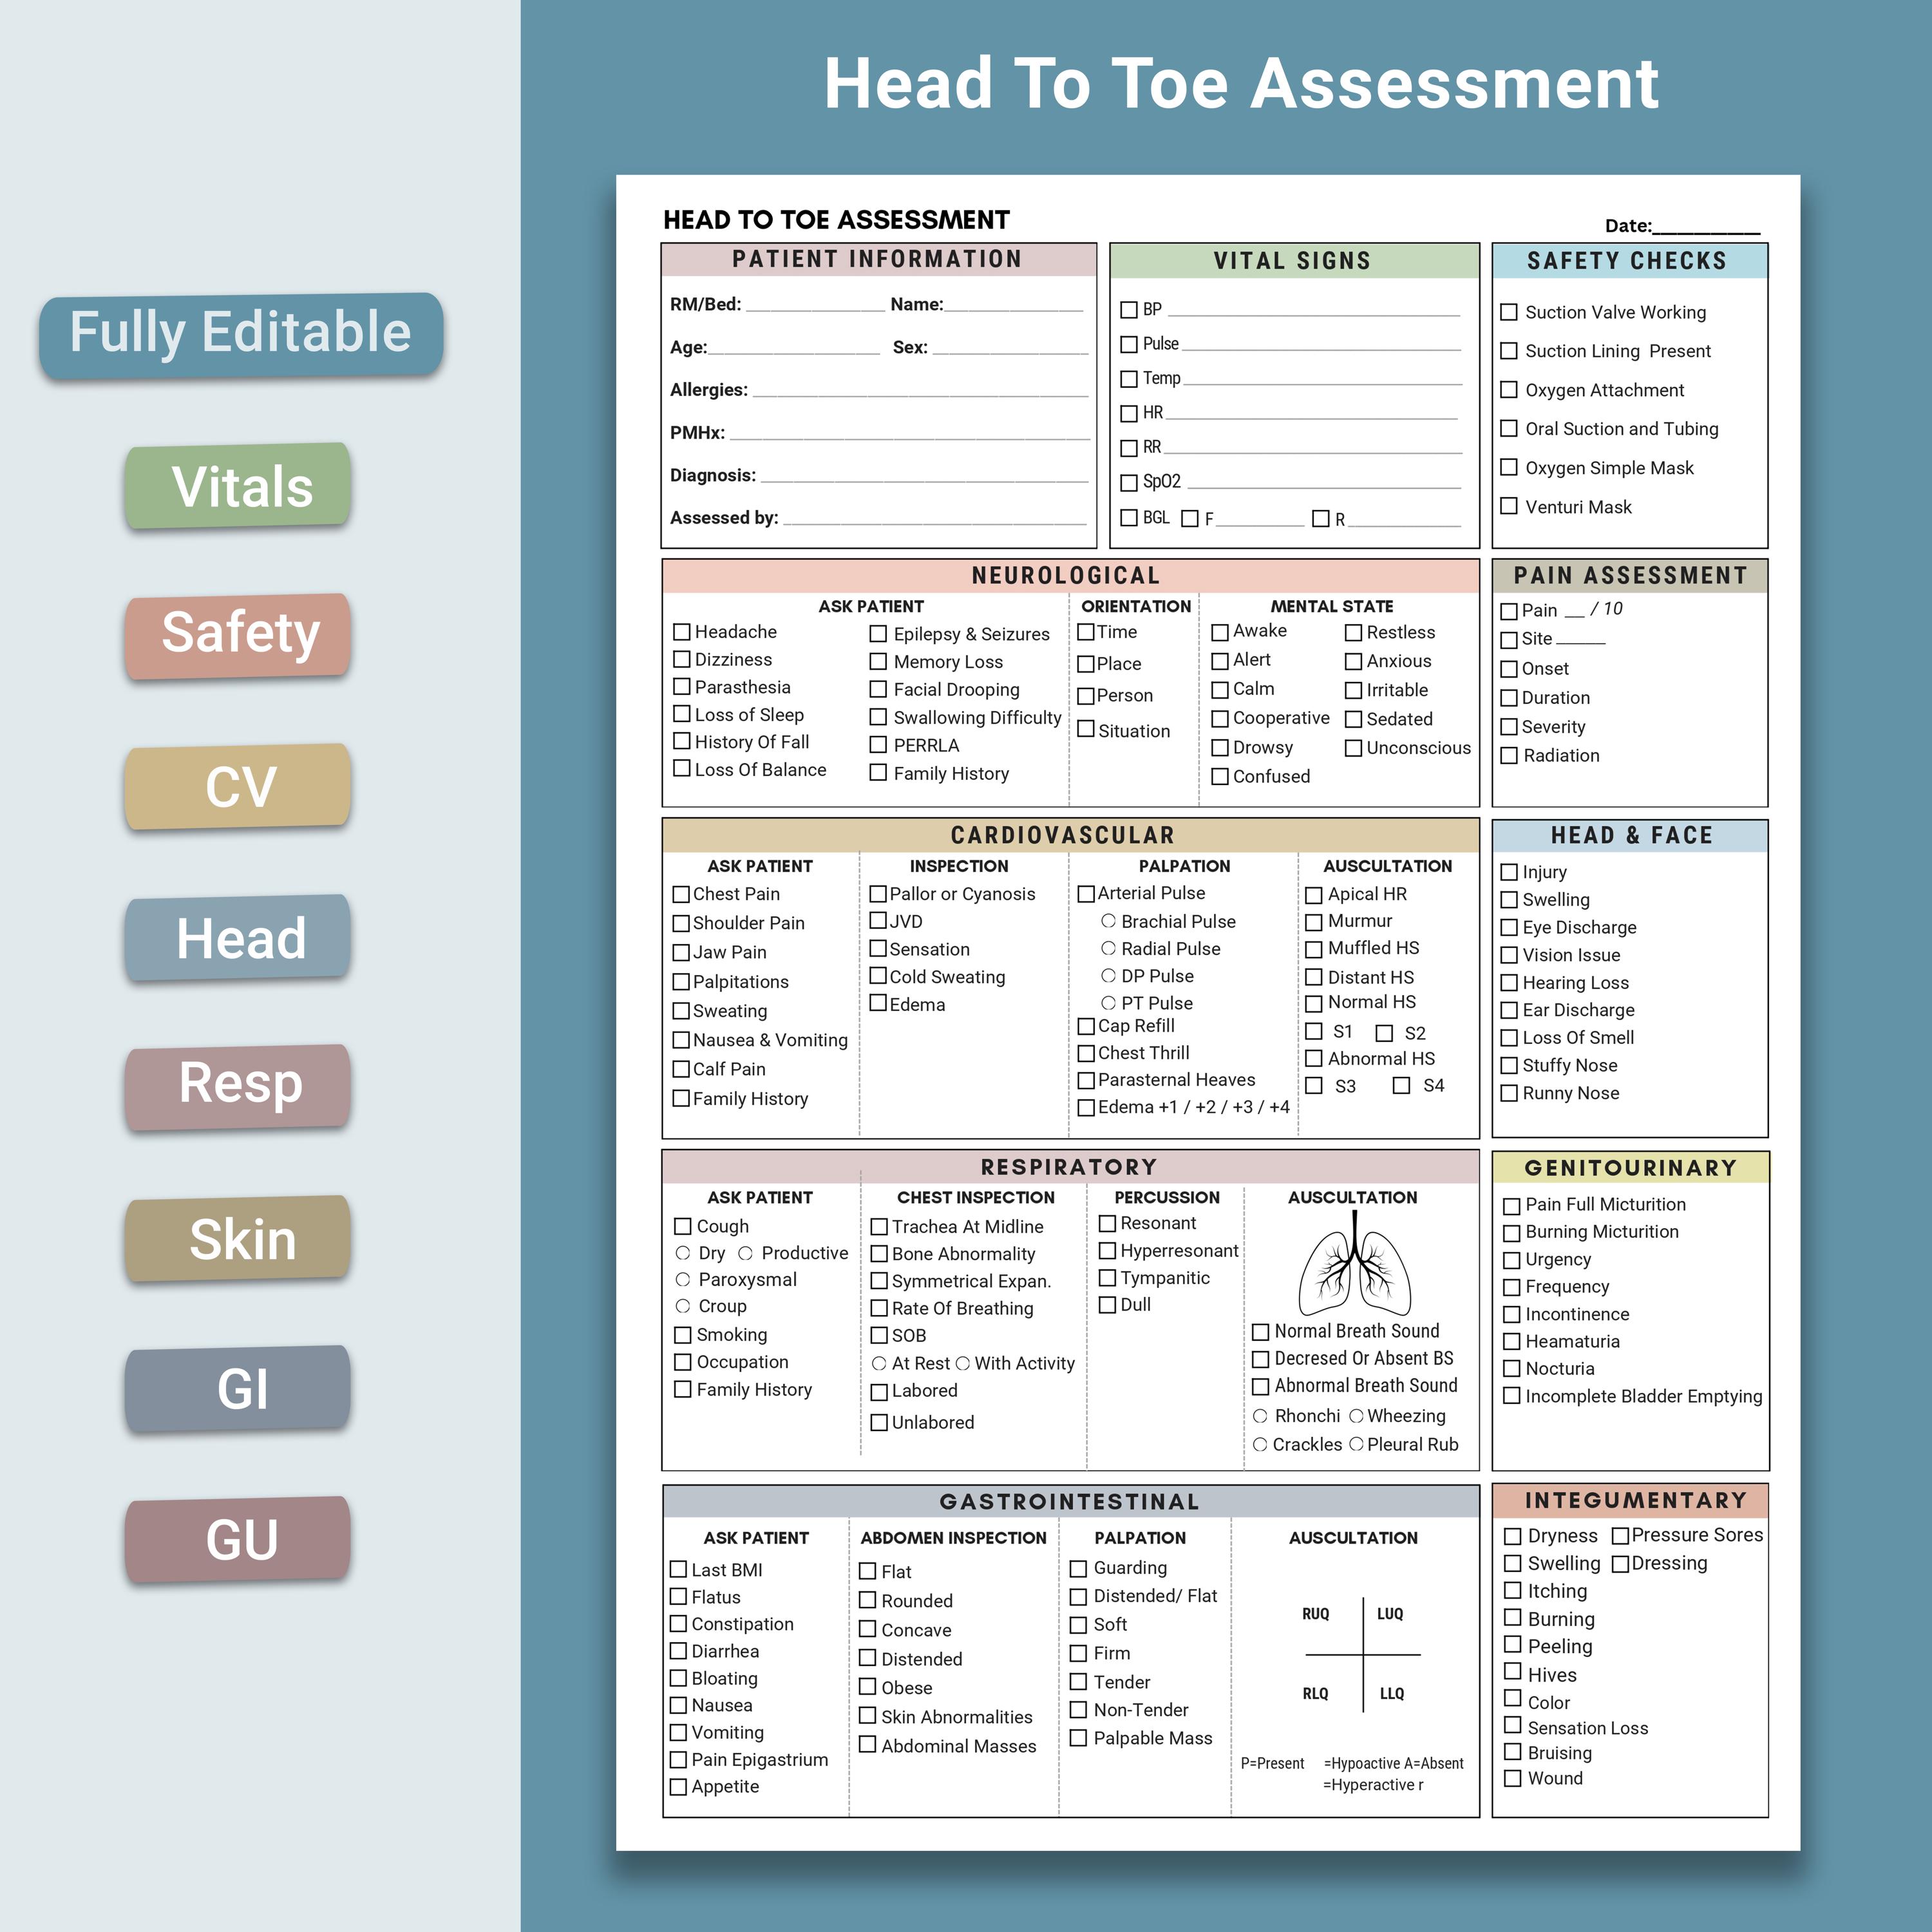
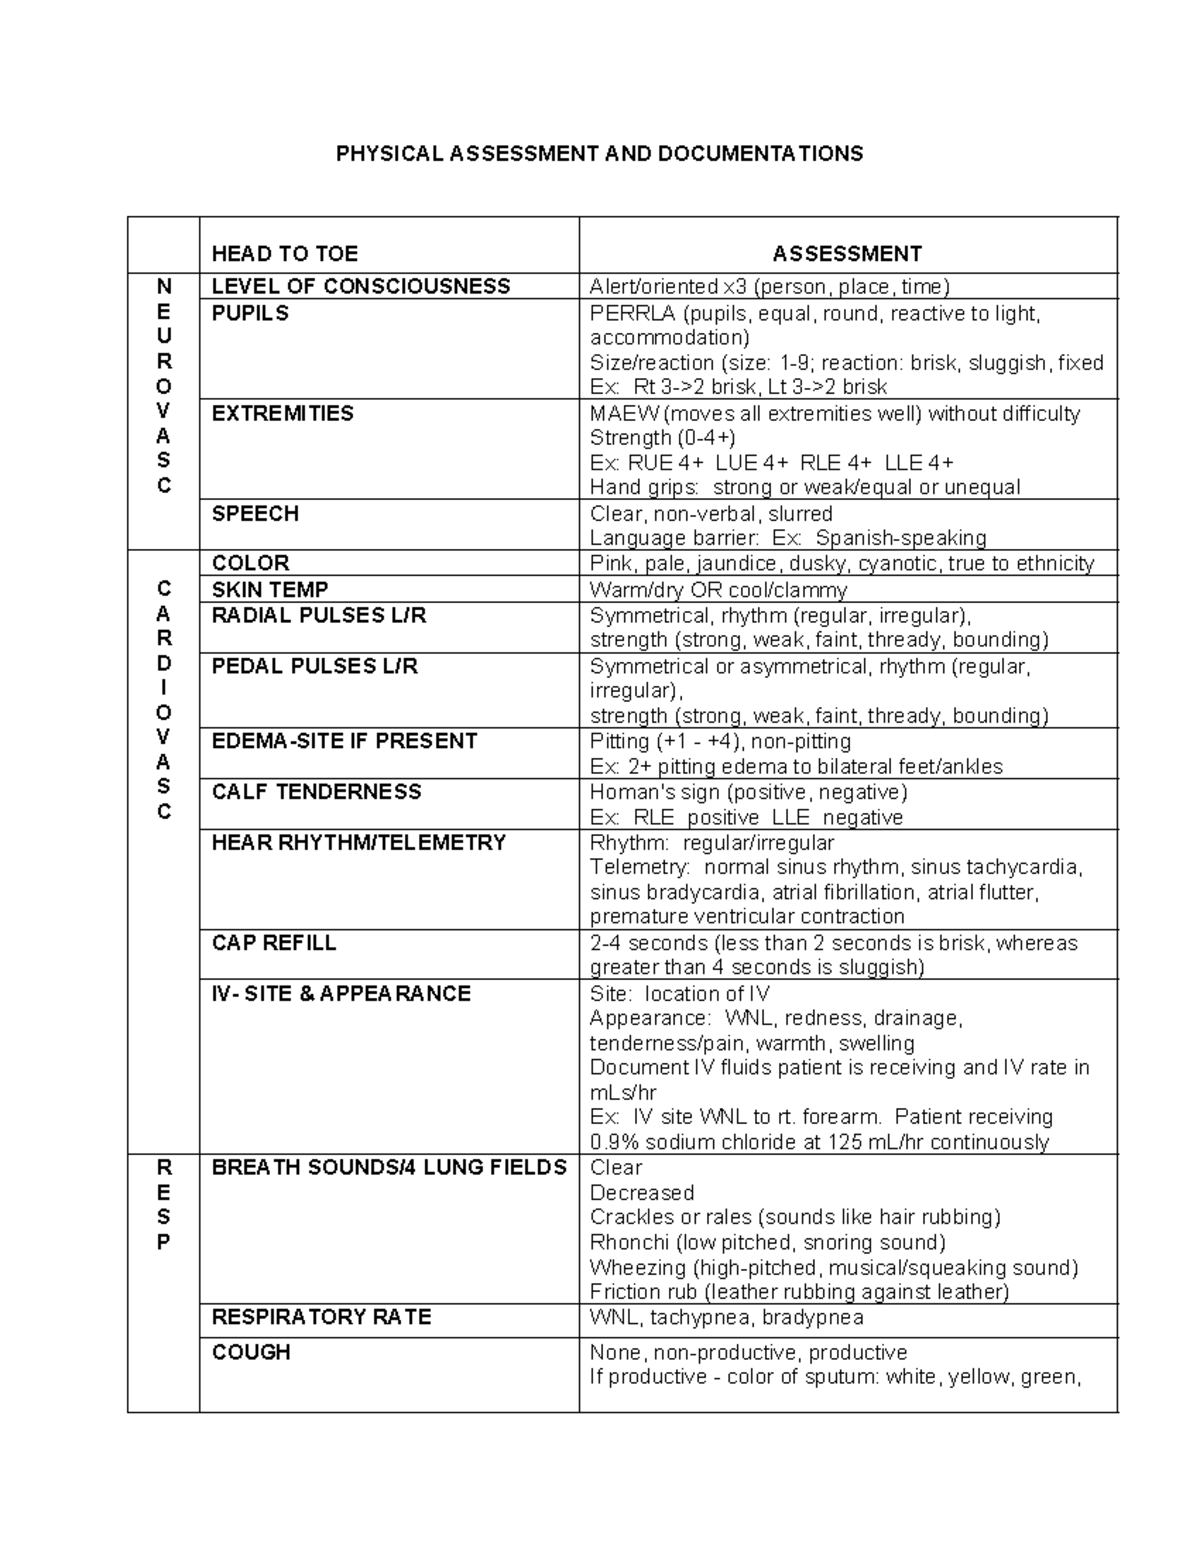
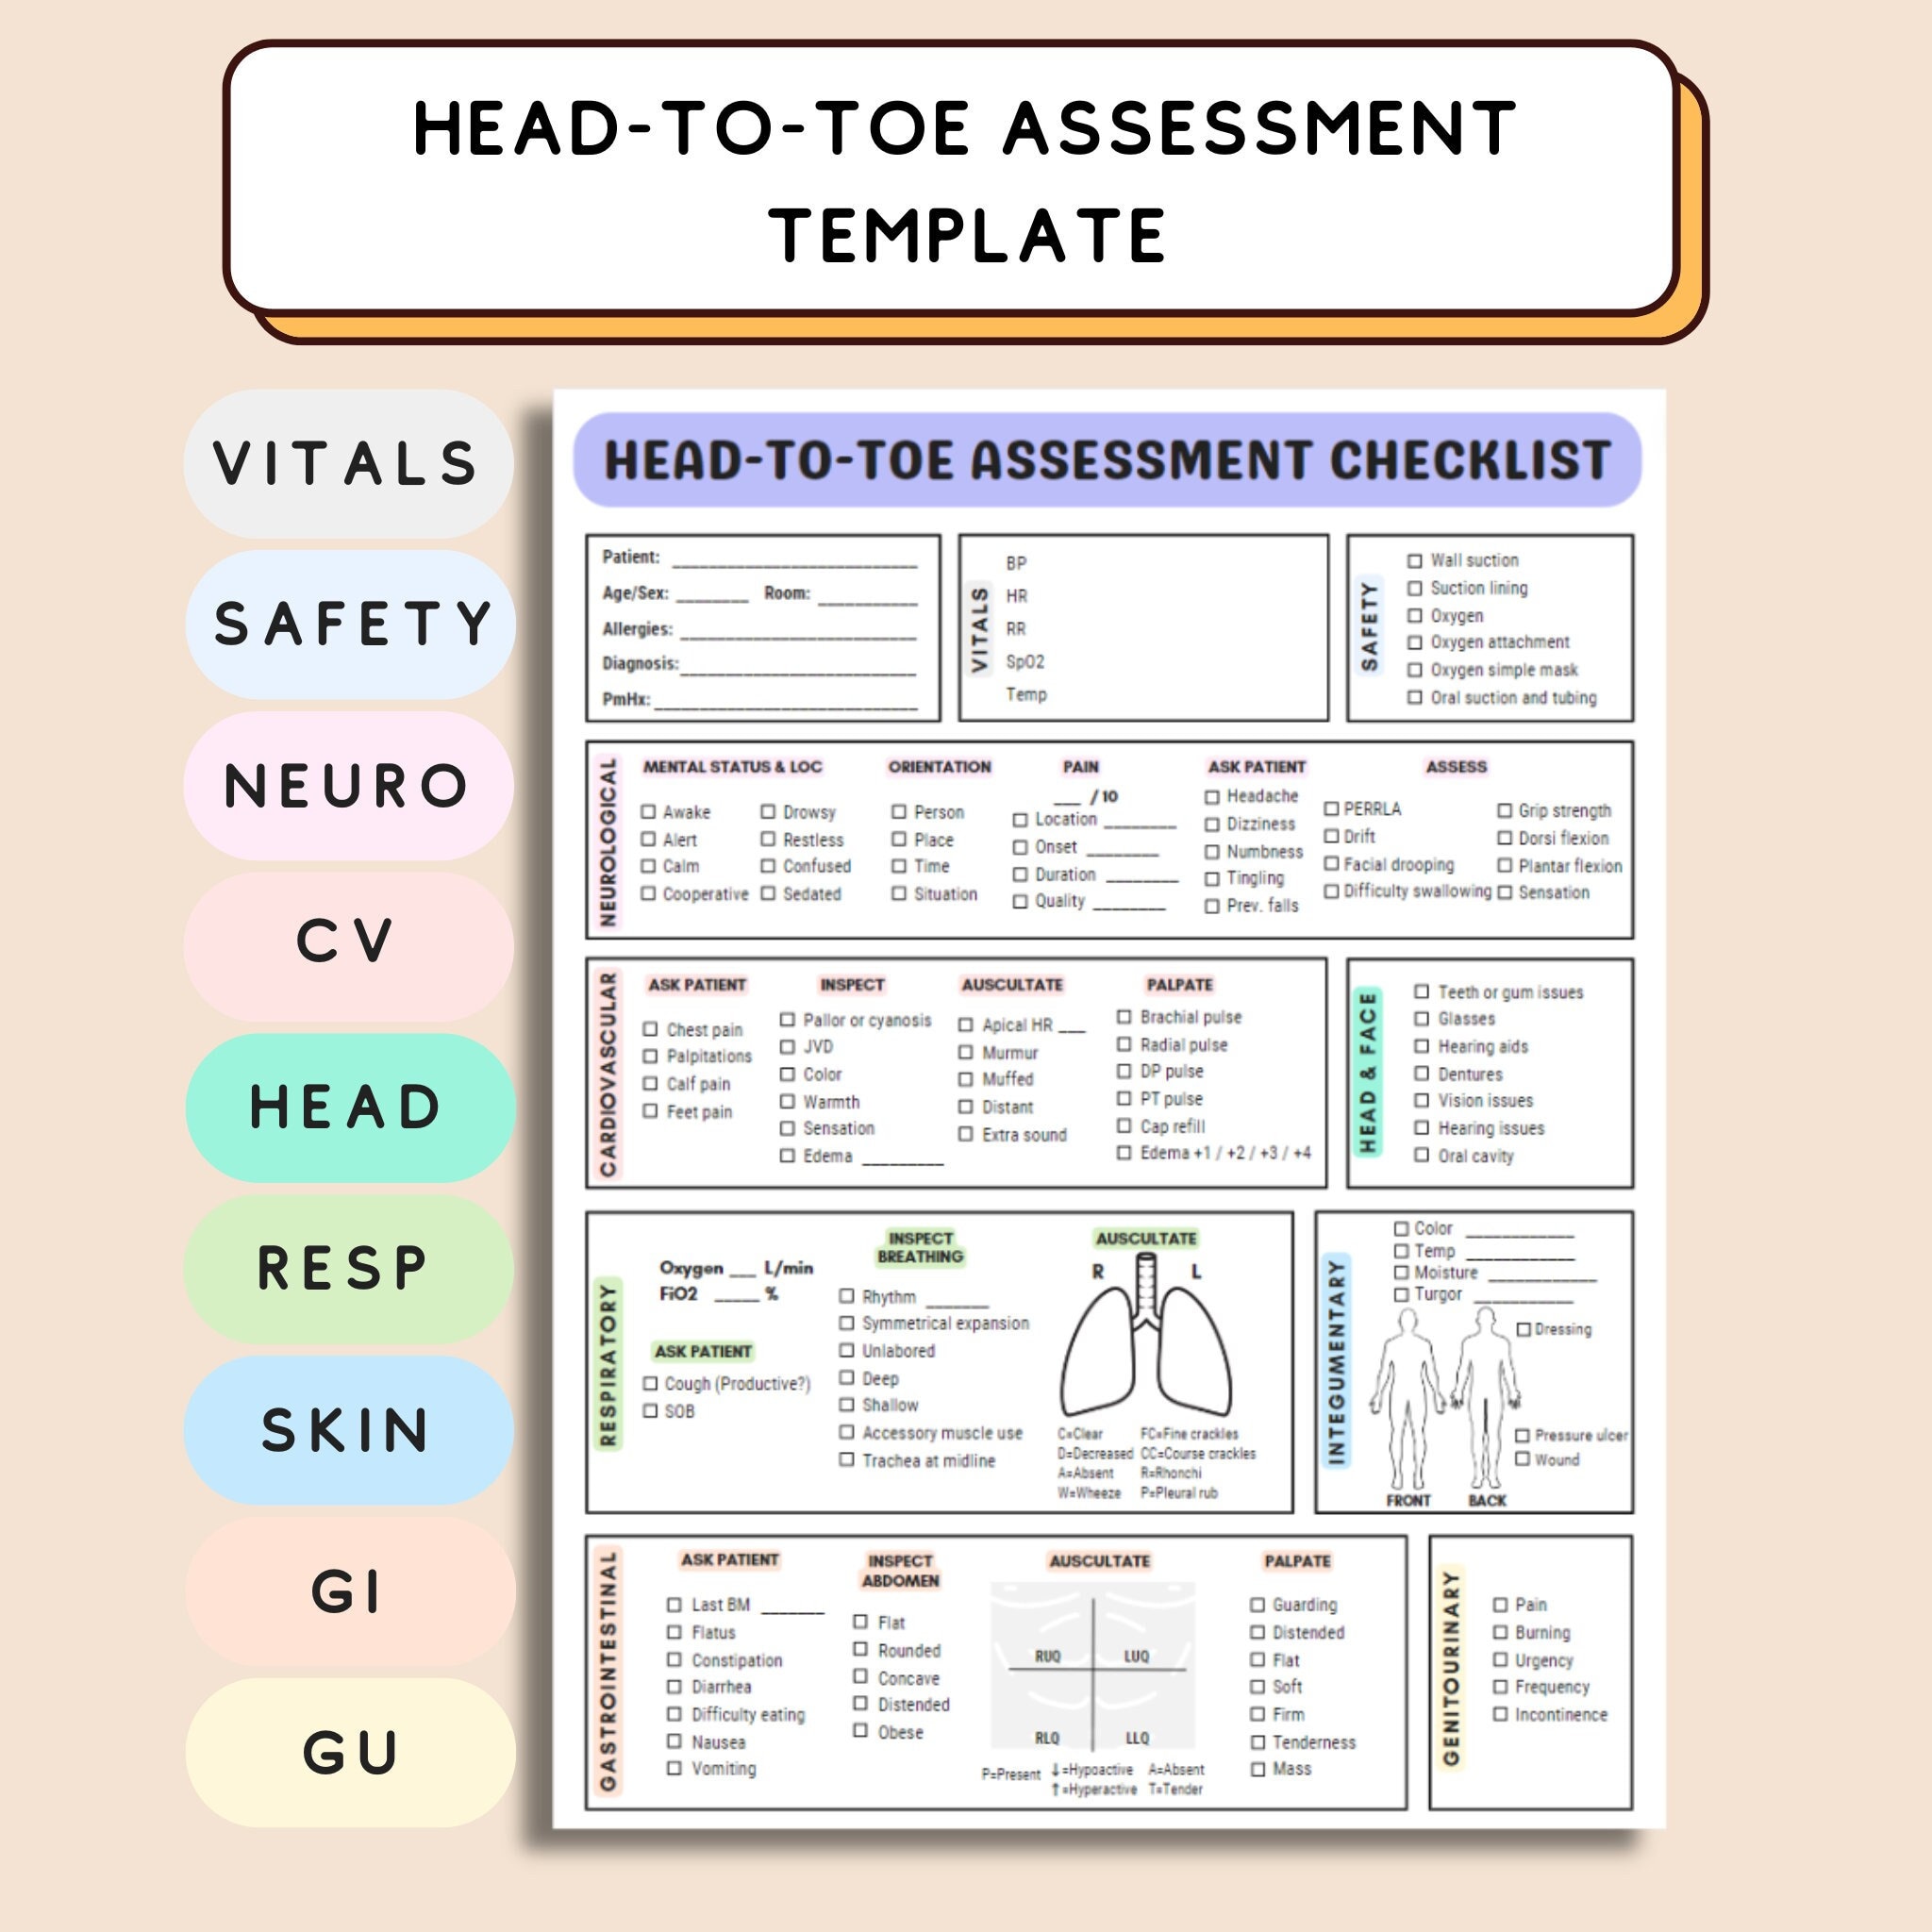
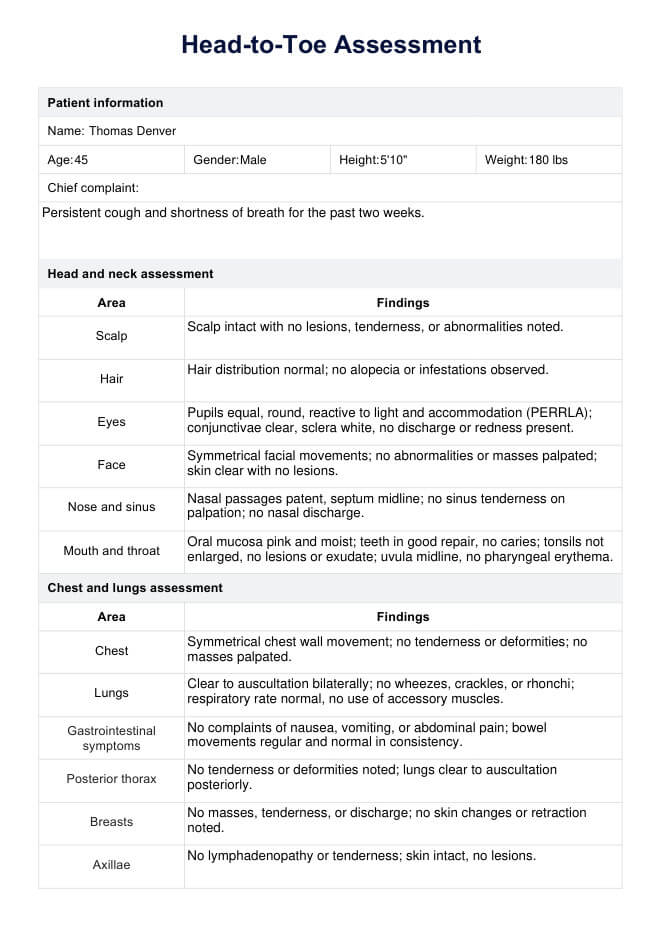
Head To Toe Assessment Documentation Sample
Let me walk through how this actually works. You start with the highest priority systems and move downward. Mental status and airway come first because those are the things that kill patients quickly. Then you move through respiratory, cardiovascular, abdominal, neurological, musculoskeletal, skin integrity, and finally peripheral vascular status. The sequence matters less than making sure nothing gets skipped. What matters more is that your documentation tells a story, not just a list of findings. I had a patient last year who came in post-op from a hip replacement. On paper, everything looked straightforward. The documentation sample I was working from from my organization was basically a standard template with checkboxes. The patient had diabetes, so skin assessment is obviously critical, but here is where it gets tricky. The heel on the surgical side was slightly swollen and warmer than the contralateral side, but the skin color looked fine. If I had just written "skin intact, no breaks noted," that would have been a complete failure of the assessment. Instead, I documented asymmetrical warmth and mild edema, upgraded the pressure injury risk score, and flagged it for vascular consult. Three days later that heel started breaking down. The early documentation caught it before it became a stage II ulcer. Had I checked the box and moved on, it would have been a preventable injury and a documentation failure. That is the kind of thing that separates a real assessment from a form you fill out. A proper head-to-toe assessment documentation sample needs to capture deviations from baseline, not just confirm normal findings. When everything is normal, you still document it, but you do it efficiently. "Lungs clear bilaterally, no wheezes or crackles" is acceptable. "Skin intact, no erythema or breakdown noted" works too. But you cannot let efficiency become laziness. There is a difference, and your chart will tell the difference faster than you might think.
Here is a practical structure I use. For each system, I record four elements: inspection, palpation, percussion or auscultation depending on the system, and functional assessment. So for cardiovascular, that means I look at the precordium, palpate the apical pulse, auscultate S1 and S2 plus any murmurs, and then check radial and dorsalis pedis pulses. For neurological, I assess orientation and cognition, cranial nerves, motor strength in all four extremities, sensory response, and reflexes. The structure keeps me honest because it forces me to actually perform each step rather than relying on whatever I happen to notice incidentally. One thing beginners consistently miss is the importance of documenting the patient's baseline. A head-to-toe assessment documentation sample is only meaningful when it can be compared to prior assessments. If the patient has known peripheral neuropathy, stating "decreased sensation in bilateral lower extremities" without noting that this is chronic and unchanged is misleading. It reads like a new finding. Add the qualifier. "Decreased sensation to light touch in bilateral lower extremities, consistent with known diabetic neuropathy, unchanged from prior." That one addition changes how the entire assessment is interpreted by whoever reads it next. Another counter-intuitive point: abnormal findings should not be buried at the bottom of your neuro assessment. If a patient has an irregular heart rhythm, that belongs in the cardiovascular section, not tacked onto the end as an afterthought. The documentation should mirror the order of your assessment. When review nurses and auditors scan the chart, they follow your structure. If you jump around, they miss things. I have seen patients readmitted within 48 hours because a subtle change in bowel sounds or a new abdominal tenderness was documented in the wrong section and got overlooked during shift handoff.
Get the Full Details

There are downsides to standardized documentation templates, and I want to be blunt about them. They encourage a box-checking mentality. They do not capture nuance well. When you are rushed and have ten patients to assess, it is tempting to copy the previous shift's documentation with minor modifications. That is dangerous, and it happens more often than anyone wants to admit. I have done it myself. The worst outcome I faced was a patient whose declining respiratory status was documented as "stable" because I carried forward the prior entry without re-assessing properly. It was caught before anything serious happened, but it took three hours of chart review and an incident report to sort out. That is not something you want to experience. If you are building your own head-to-toe assessment documentation sample, start with a template but leave room for narrative. Most electronic health record systems allow both structured data entry and free-text fields. Use the structure for speed and the narrative for context. A two-line summary at the end of each system section costs maybe thirty seconds and dramatically improves clarity. Something like "Cardiovascular: regular rate and rhythm, no murmurs appreciated. Peripheral pulses 2+ bilaterally, no edema. Patient reports occasional palpitations with exertion, communicated to attending." That is eight seconds to write and a hundred times more useful than just checking boxes. For a downloadable reference, most hospital websites and nursing education programs offer their own versions. The one I rely on is from my current organization's clinical documentation team, and it aligns with Joint Commission expectations. It covers all major systems, includes space for pain assessment, functional status, and safety considerations like fall risk. It is not perfect, but it is practical. I would look for a version from your own institution first since it will match your EHR workflow and your unit's specific requirements. A generic sample online is fine for learning the structure, but it will not reflect your documentation standards or legal requirements.
The bottom line is that a head-to-toe assessment documentation sample is a tool, not a product. It only works when you actually do the assessment it represents. The documentation follows the work, not the other way around. If you skip parts of the exam, no amount of careful documentation will cover that up. Auditors know this. Charge nurses know this. The patients know this when their condition changes and nobody noticed. Spend the time to do the assessment properly, then document it in a way that reflects what you actually found.