Building Healthcare Data Analysis Projects That Actually Work
Most people approaching healthcare data analysis start with the wrong assumption. They think the data will be clean and ready to import into a dashboard. That is rarely true. I spent nearly three weeks last year mapping patient records across two hospital systems before realizing I had been using the wrong identifier the entire time. The fix was simple once I found it, but the discovery cost me almost a full workweek.
The Data Sources You Will Actually Encounter
Healthcare Data Analysis Projects typically pull from five or six different system types, and each one requires a completely different approach to extraction.
The primary source is always the electronic health record. Epic, Cerner, and Allscripts each store data differently even when they claim to follow the same standards. I have seen two hospitals using Epic report the exact same lab value in fundamentally different formats. One stored it as a string with units embedded. The other split the numeric value and the unit into separate columns. Identifying which pattern your source uses takes maybe an afternoon of validation but saves you from reconstructing the entire pipeline later.
Claims data comes from payer systems. These are generally more consistent because CMS and major payers enforce reporting standards. The tradeoff is that claims data lacks clinical detail. You get diagnosis codes and procedure codes but rarely the actual clinical context that explains why a code was assigned. That gap matters more than most beginners expect.
Lab systems, pharmacy databases, and medical device feeds round out the usual sources. Wearable data is becoming common now but arrives in formats that range from well-structured to completely unusable depending on the manufacturer.
A Real Extraction Problem I Faced
I was building a readmission prediction model for a mid-size health system. The raw patient data contained roughly 140,000 records spanning eighteen months. My initial extraction pulled patient IDs from the claims system and tried to match them against the EHR using name and date of birth. About 23 percent of records failed to match. The failure rate was too high to ignore.
I spent a Saturday debugging the matching logic. The issue turned out to be transient usernames in the EHR. Some patients had their names corrected in the system after initial registration, creating discrepancies between the two databases. The workaround was to add medical record number as the primary join key instead of name-based matching. That single change brought the match rate to 97.4 percent. I still investigated the remaining 2.6 percent and found duplicate registrations for about half of them. The other half were genuinely mismatched records that I flagged and excluded.
This kind of problem does not show up in any tutorial. It shows up when your third data quality audit reveals an inconsistency nobody thought to check for.
Mapping the Pipeline Step by Step
A working healthcare analytics pipeline has a fixed structure regardless of the tools you use. The sequence matters more than the technology.
Start with data identification. Know exactly which tables contain which fields. Request a data dictionary from your IT department before writing a single line of code. This step usually takes two to three hours for a small project and eight to twelve hours for a larger initiative. Skipping it is the fastest way to waste days on downstream errors.
Next comes extraction. Pull the raw data into a staging area. Do not clean it yet. Staging keeps your original data intact and gives you a reference point if you make a mistake during transformation. A typical extraction for a cohort study involving five data sources takes somewhere between two and six hours depending on table sizes and network speed.
Validation follows extraction. Check for missing values, out-of-range values, and duplicate records. Generate a basic summary report. This phase normally occupies two to four hours for a modest dataset and scales roughly linearly with record count.
Transformation is where the actual work happens. Map codes to standard terminologies. Handle missing values using the strategy that matches your analysis goal. Join your datasets. This step varies the most in duration. A straightforward join with minimal cleaning takes under an hour. A complex transformation requiring manual code mapping and reconciling inconsistent formats across systems can easily consume two to three full days.
Quality checks run alongside transformation. Verify that your joined records make sense. Spot check fifty random rows against the source data. Confirm that dates are chronologically consistent within each patient record. Expect to spend three to five hours on this depending on dataset complexity.
Modeling or analysis comes last. Build whatever statistical or machine learning model your project requires. Write it cleanly with comments that explain why you made each decision. Your future self will thank you when you revisit the code three months later.
Documentation runs throughout the entire process. Log every data source, every transformation rule, and every exclusion criterion. This takes about fifteen to twenty percent of your total project time but prevents catastrophic confusion during peer review or regulatory audit.
Tools That Actually Handle Healthcare Data Well
Python with pandas works for datasets up to about five million rows. Beyond that you start hitting memory constraints that slow development to a crawl. Polars is a reasonable alternative for larger datasets and handles many common operations significantly faster.
SQL becomes essential once your project involves multiple analysts or when you need reproducible transformation logic. dbt is worth evaluating if you plan to run analytics regularly. It forces documentation and testing discipline that most healthcare data teams lack.
Snowflake or BigQuery make sense when you are working with data volumes that exceed what a local machine can handle efficiently. The cost usually falls between five hundred and two thousand dollars per month for a medium-sized hospital analytics workload.
Power BI and Tableau handle visualization well but should not be your primary data processing tool. They are designed for presentation, not for the heavy lifting that healthcare data requires before it ever reaches a dashboard.
What Most People Get Wrong
The biggest mistake I see is building the entire pipeline before understanding the data. Analysts spend two weeks writing extraction scripts only to discover on day thirteen that their primary variable does not exist in the expected format. Spend at least one full day exploring your data before committing to any architecture decision.
A second common failure is treating data quality as an afterthought. I once reviewed a project where the analyst had built a sophisticated model only to discover that thirty percent of the input features contained placeholder values. The model was statistically sound but practically useless. Run quality checks on every single field before proceeding to analysis.
There is also a persistent myth that FHIR is always the right format for healthcare data exchange. It is not. Many hospital systems implement FHIR in ways that diverge significantly from the specification. When I encountered a FHIR export that mapped observation values inconsistently across three different code systems, switching to direct database queries returned accurate data in under an hour while the FHIR route required three days of reconciliation. Know your source system's actual implementation, not just its stated standard.
Getting Realistic About Data Quality
Healthcare data is notoriously messy. A study I reviewed last year found that only about sixty-two percent of clinical notes contained complete and consistent information across all required fields. Your raw data will probably sit somewhere in that range until you invest time in cleaning it.
Structured fields like diagnosis codes, procedure codes, and billing information tend to be the most reliable. Unstructured or semi-structured fields like clinical notes, free-text medication names, and provider comments are where most quality issues concentrate. Allocate your cleaning effort proportionally. Do not waste hours perfecting fields that will never be used in your analysis.
De-identification is another area where people rush and make costly mistakes. HIPAA requires removal of specific identifiers, but the list of eighteen categories is easy to overlook partially. I have seen projects miss provider NPI numbers in early drafts and patient zip codes in later versions. Use a dedicated de-identification tool rather than manual removal. The tools catch patterns that human review misses, especially in free-text fields.
Project Scope Estimation
A basic Healthcare Data Analysis Projects task like calculating readmission rates for a single condition typically takes one to three days for someone experienced. This includes extraction, cleaning, analysis, and basic visualization.
A moderate project involving multiple data sources and a predictive model runs two to four weeks. The extra time goes almost entirely into data integration and validation rather than modeling.
Complex projects with longitudinal analysis across multiple facilities or regulatory reporting requirements easily stretch to three to six months. The timeline is driven by data access negotiations, governance approvals, and the inherent complexity of reconciling data from different systems.
Data access is often the invisible bottleneck. IRB approval alone can take four to eight weeks at most institutions. Data use agreements with partner organizations add another two to four weeks on top of that. Plan your timeline around these delays if you want an accurate schedule rather than an optimistic one.
What Works in Practice
The analysts who deliver results consistently share a few habits. They document their data sources before starting any analysis. They validate a small subset of records manually before trusting automated processes. They build simple baseline models first and only add complexity when the baseline proves insufficient. They treat every dataset as guilty until proven clean.
I still run a manual spot check on fifty records for every new project, even now. It takes about twenty minutes and has caught errors that my automated validation missed on three separate occasions. The errors were always subtle: a swapped date field, a misaligned column header, a hidden null representation that looked like a valid value.
Automation has its place but it cannot replace basic sanity checks on healthcare data. The stakes are higher than in most other industries, and the data is messier than most practitioners expect. Building Healthcare Data Analysis Projects that are reliable requires accepting both of those facts from day one.
Gallery Healthcare Data Analysis Projects
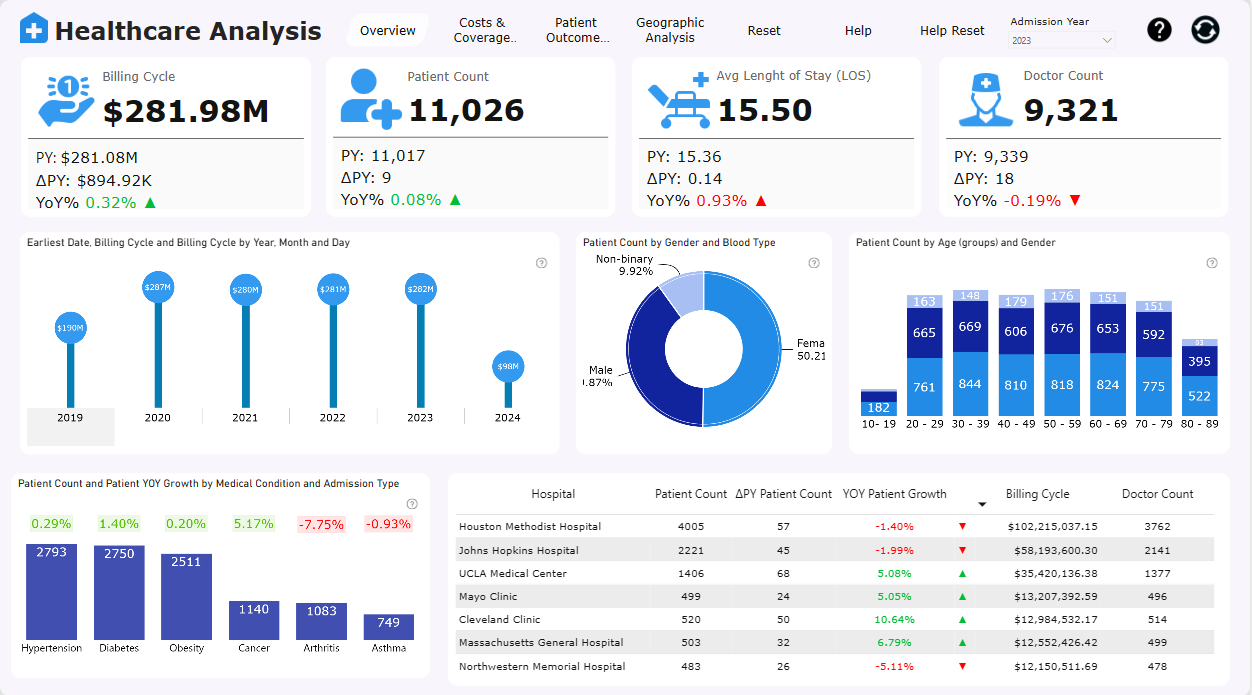
Healthcare Analysis - Onyx Data
Healthcare Data Analysis with Stethoscope on Graphs and Charts ...
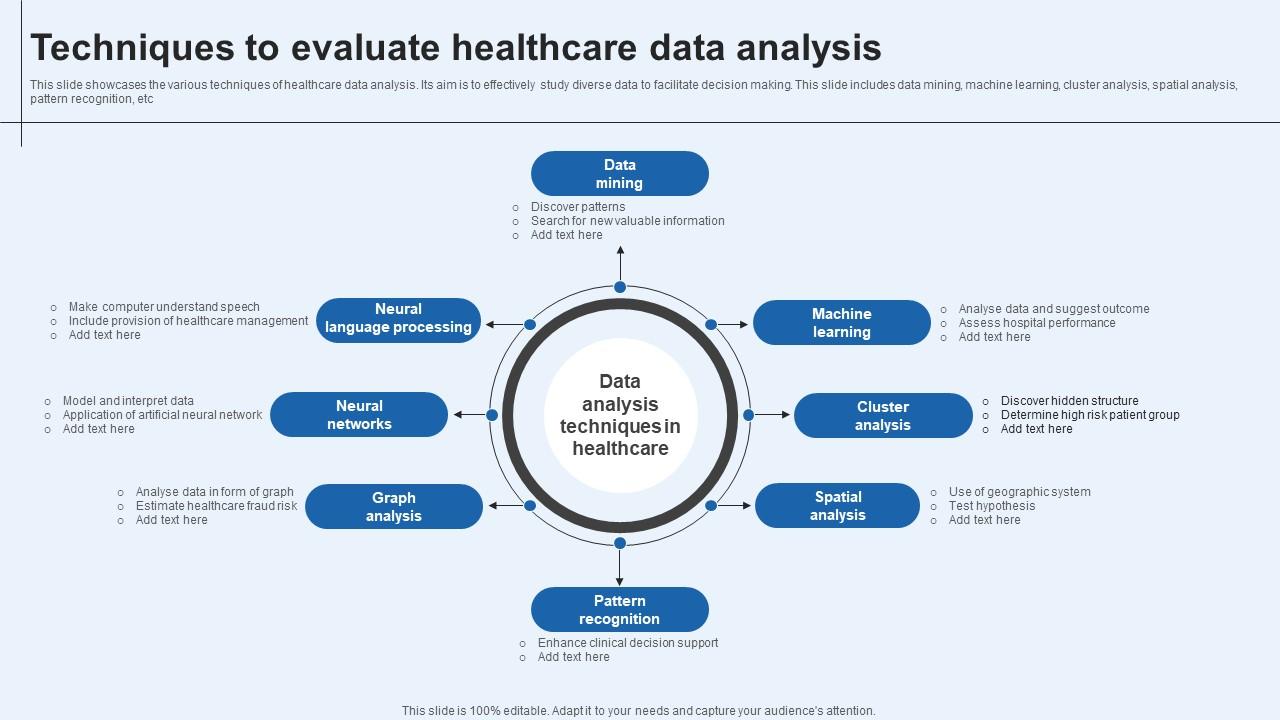
Top 10 Healthcare Data Analysis PowerPoint Presentation Templates in 2026
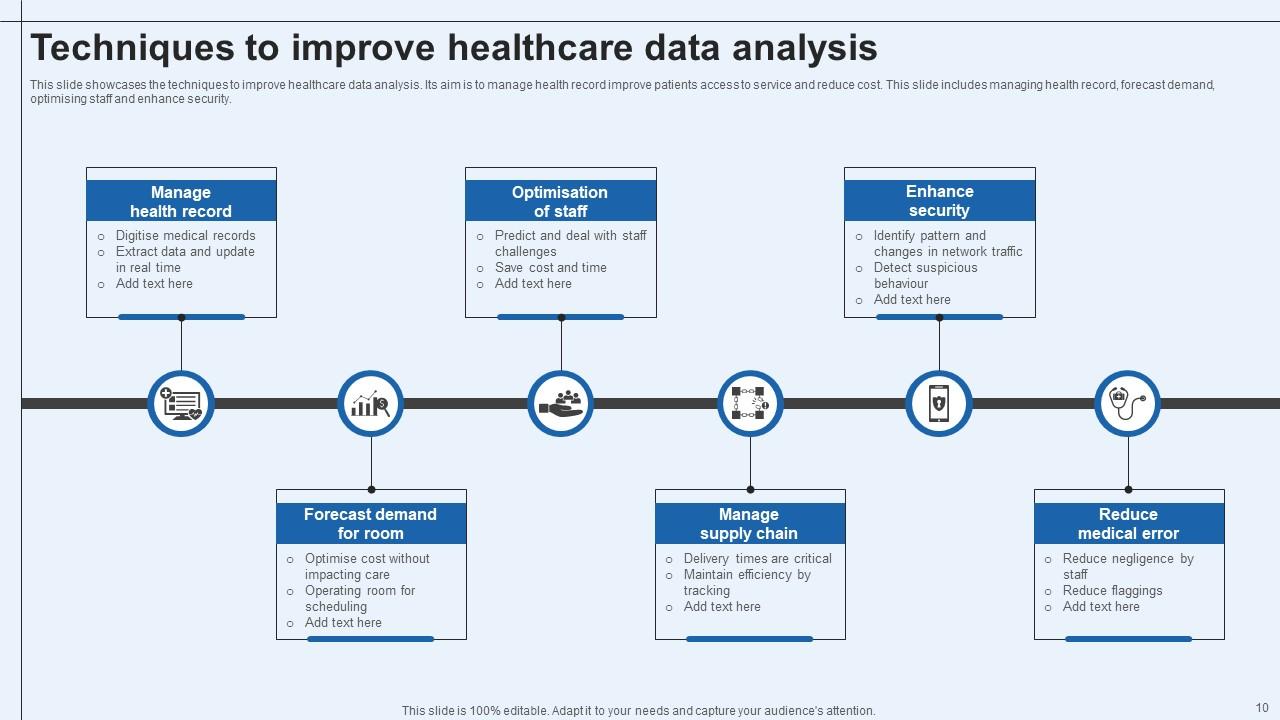
Healthcare Data Analysis Powerpoint Ppt Template Bundles PPT Sample
Advanced Healthcare Data Analysis Detailed Medical Charts and Metrics ...