Why the Sitting Position in Surgery Gets Messed Up (And How to Actually Document It Right)
The medical term for sitting position is straightforward—sitting position, seated position, or occasionally Becker position depending on the specialty—but the way people actually write it in operative reports is where everything falls apart. I have spent more hours than I care to admit correcting sloppy position documentation from residents and surgical techs who treat it like an afterthought. It shouldn't be. Here is what the sitting position actually is, how it functions in practice, and the specific problems you will run into when using it. I am going to start with the technical reality because most guides front-load definitions and leave out the parts that matter when you are actually positioning a patient.
Sitting Position Medical Term: What It Actually Means
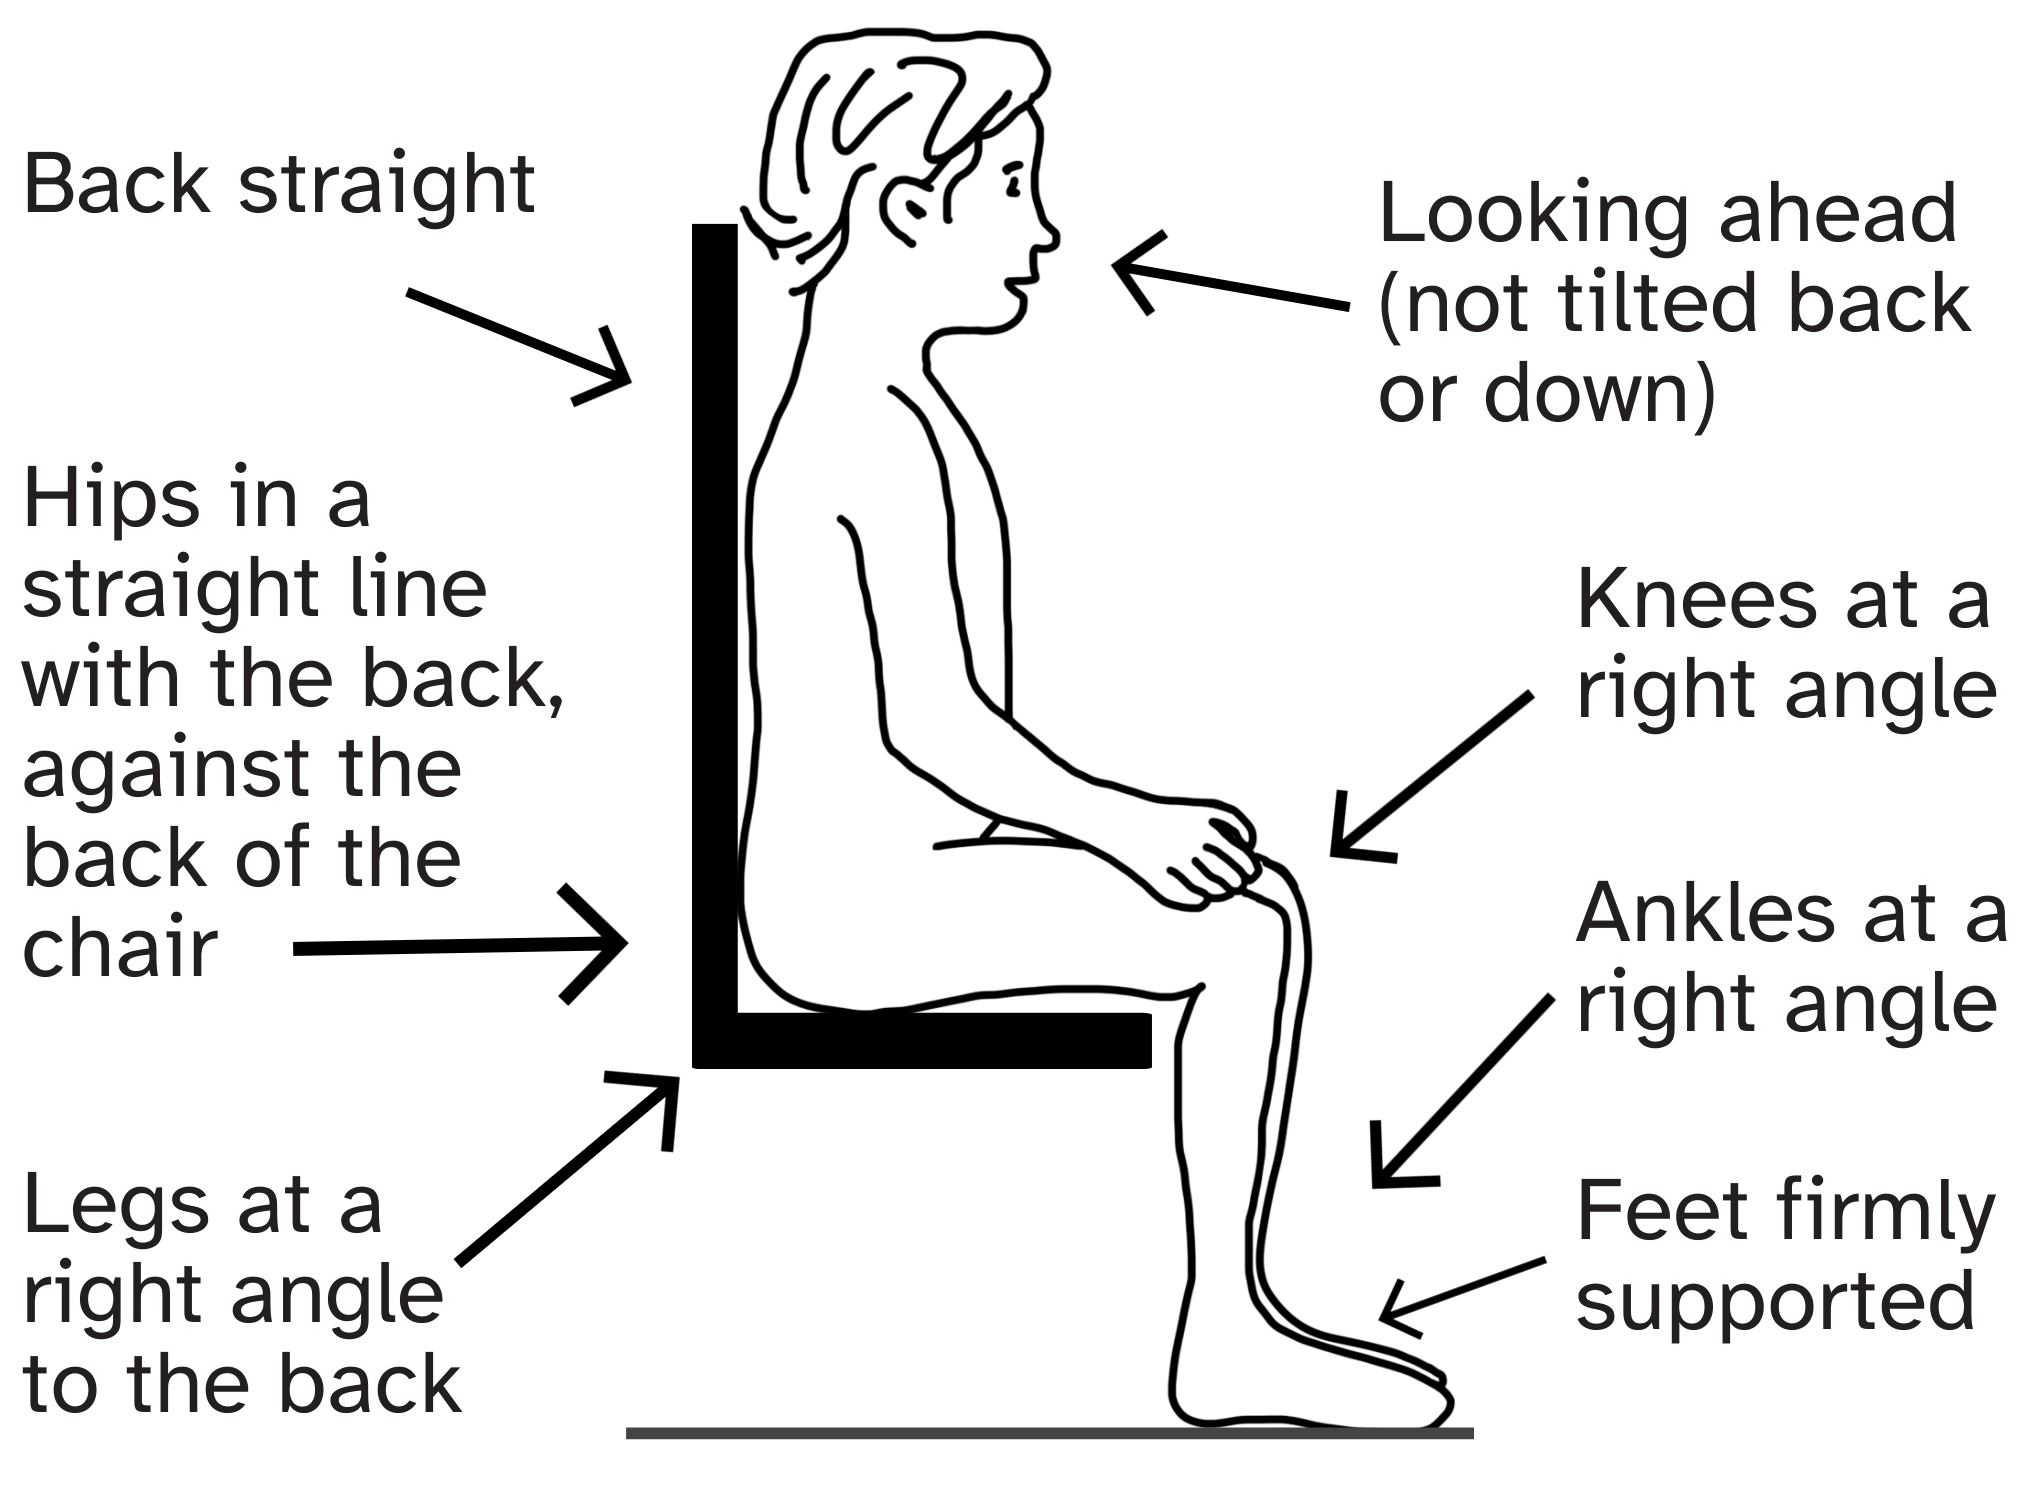
The sitting position places the patient upright with the trunk vertical and the thighs horizontal, essentially resembling a chair. The head is maintained in neutral or slight flexion depending on the surgical target. In neurosurgery, this is most commonly used for posterior fossa procedures where gravity assists with venous drainage and cerebellar relaxation. In orthopedics, it appears occasionally for certain shoulder arthroscopies, though the lateral decubitus has largely replaced it there. The key anatomical detail that beginners miss: the sitting position is not simply "sitting up in bed." It is a rigidly maintained configuration. The hip angle is approximately 80 to 90 degrees. The knees are flexed at roughly 90 degrees with the lower legs supported. The spine remains neutral—no slouching, no list to either side. Any deviation changes the surgical field geometry and can alter hemodynamics significantly.
How It Works in Practice (The Parts No Textbook Emphasizes)
When you place a patient in the sitting position, you are creating a hydrostatic column that extends from the brain down to the feet. This matters enormously for blood pressure management. The arterial line transducer must be leveled at the level of the circle of Willis, not the right atrium, or your intraoperative blood pressure readings are meaningless. I learned this the hard way during a posterior fossa craniotomy when the anesthesia team forgot to relevel the transducer after we repositioned the head. We were reading systolic pressures in the 160s when the patient was actually normotensive. We caught it before it became a problem, but it took twenty minutes of recalibration and reconfirmation. The second practical detail involves fixation. The head is secured in a three-pin skull clamp or a padded headrest system. Pin sites must be placed according to the Klingler or safe triangle method depending on surgeon preference. The danger zone is the supratrochlear and supraorbital nerves anteriorly and the superficial temporal artery laterally. A pin placed too anteriorly can cause temporary or permanent facial numbness. I have seen it happen twice in my career. Neither case was malpractice, but both were entirely preventable. Venous air embolism is the complication everyone talks about, and for good reason. The pressure gradient between the operative field and the right atrium can be substantial when the head is above heart level. Preoperative transesophageal echocardiography or bubble study setup is standard in most high-volume centers. Precordial Doppler is the cheapest and most sensitive early detection method available. You place it over the right heart border before induction and leave it there. A mill wheel murmur is a late sign. Early detection shows up as a sudden drop in end-tidal CO2, often before any hemodynamic change. That drop can be as small as 5 to 10 mmHg, and it is your first warning.
Get the Full Details

Common Pitfalls and Where the Position Fails Completely
The sitting position is not universally applicable, and it is important to state that plainly. It is contraindicated in patients with a known patent foramen ovale because the risk of paradoxical air embolism becomes unacceptably high. I had a case where we proceeded with a cervical laminoplasty in the sitting position despite a borderline PFO on preoperative echo, and we aborted the case after the TEE showed significant right-to-left shunting. The surgery was rescheduled in the prone position two weeks later. It added cost and delay, but it prevented a potential stroke. Another failure mode is prolonged duration. The sitting position places significant shear stress on the sacral skin and ischial tuberosities. For cases exceeding three hours, pressure injury risk climbs steeply. We use silicone foam dressings on the sacrum and greater trochanters as a standard preventive measure, and we verify contact points immediately after positioning but before the surgical drape is applied. Documentation of skin inspection findings in the operative record is something I check religiously. The most counter-intuitive point about the sitting position that few people understand: it can actually worsen cerebral perfusion in certain scenarios. The classic teaching emphasizes that venous drainage improves, which is true, but arterial inflow is equally dependent on the hydrostatic gradient. If the patient is hypovolemic, the arterial pressure at the brain level drops disproportionately. We maintain a slightly higher central venous pressure target—around 8 to 10 cm H2O—during sitting position cases specifically to maintain adequate cerebral perfusion pressure. This is not standard across all cases, and it requires careful fluid management, but it is a detail that separates adequate outcomes from poor ones.
Documentation Standards for the Sitting Position
When documenting this position, the operative report should specify: the exact position name, whether pins or a padding system was used, transducer leveling method, ETE or Doppler monitoring setup, skin protection measures applied, and any intraoperative position-related complications. Vague phrases like "patient positioned appropriately" are not sufficient and create liability exposure. I make a point of writing these details explicitly because I have reviewed charts where ambiguous positioning documentation was the only record available during a postoperative complication workup. The sitting position remains a valuable surgical tool, particularly in posterior fossa neurosurgery. It demands precise positioning, vigilant monitoring, and thorough documentation. Get any of those three wrong and the consequences can be severe. Get them right and the surgical field and hemodynamic profile are excellent. There is no middle ground with this position—it rewards attention to detail and punishes shortcuts.