Understanding Where the Heart Actually Sits
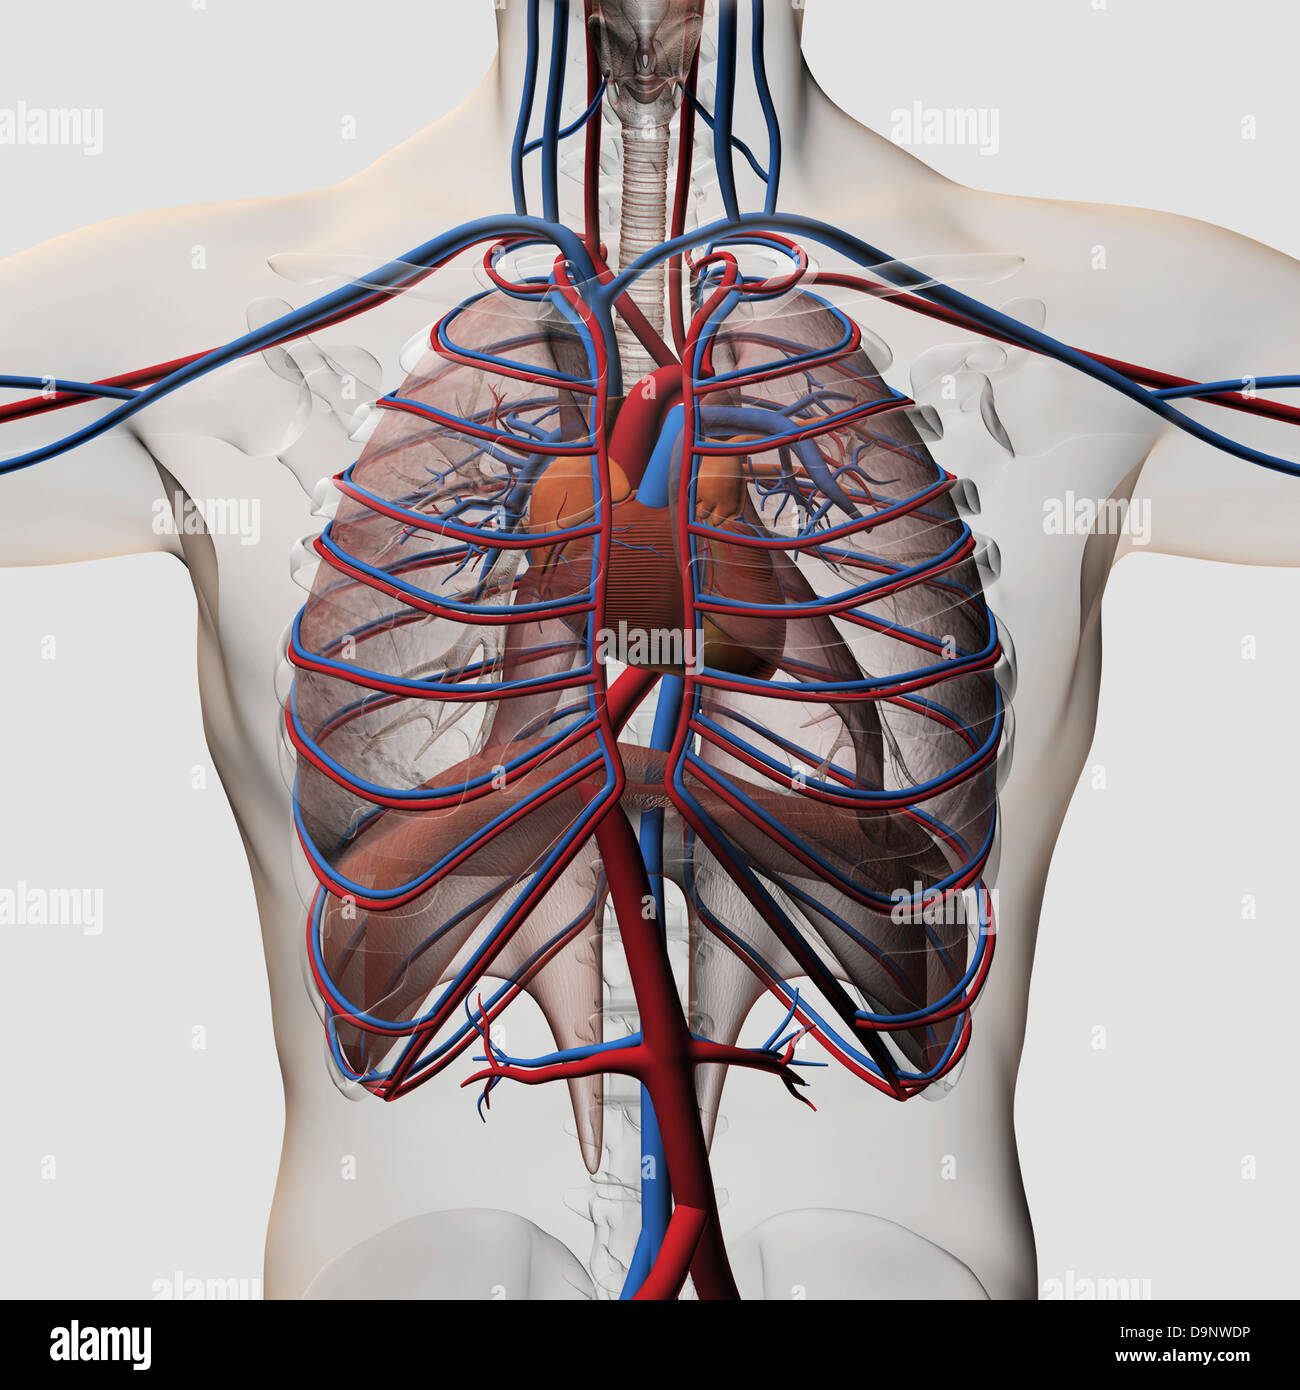
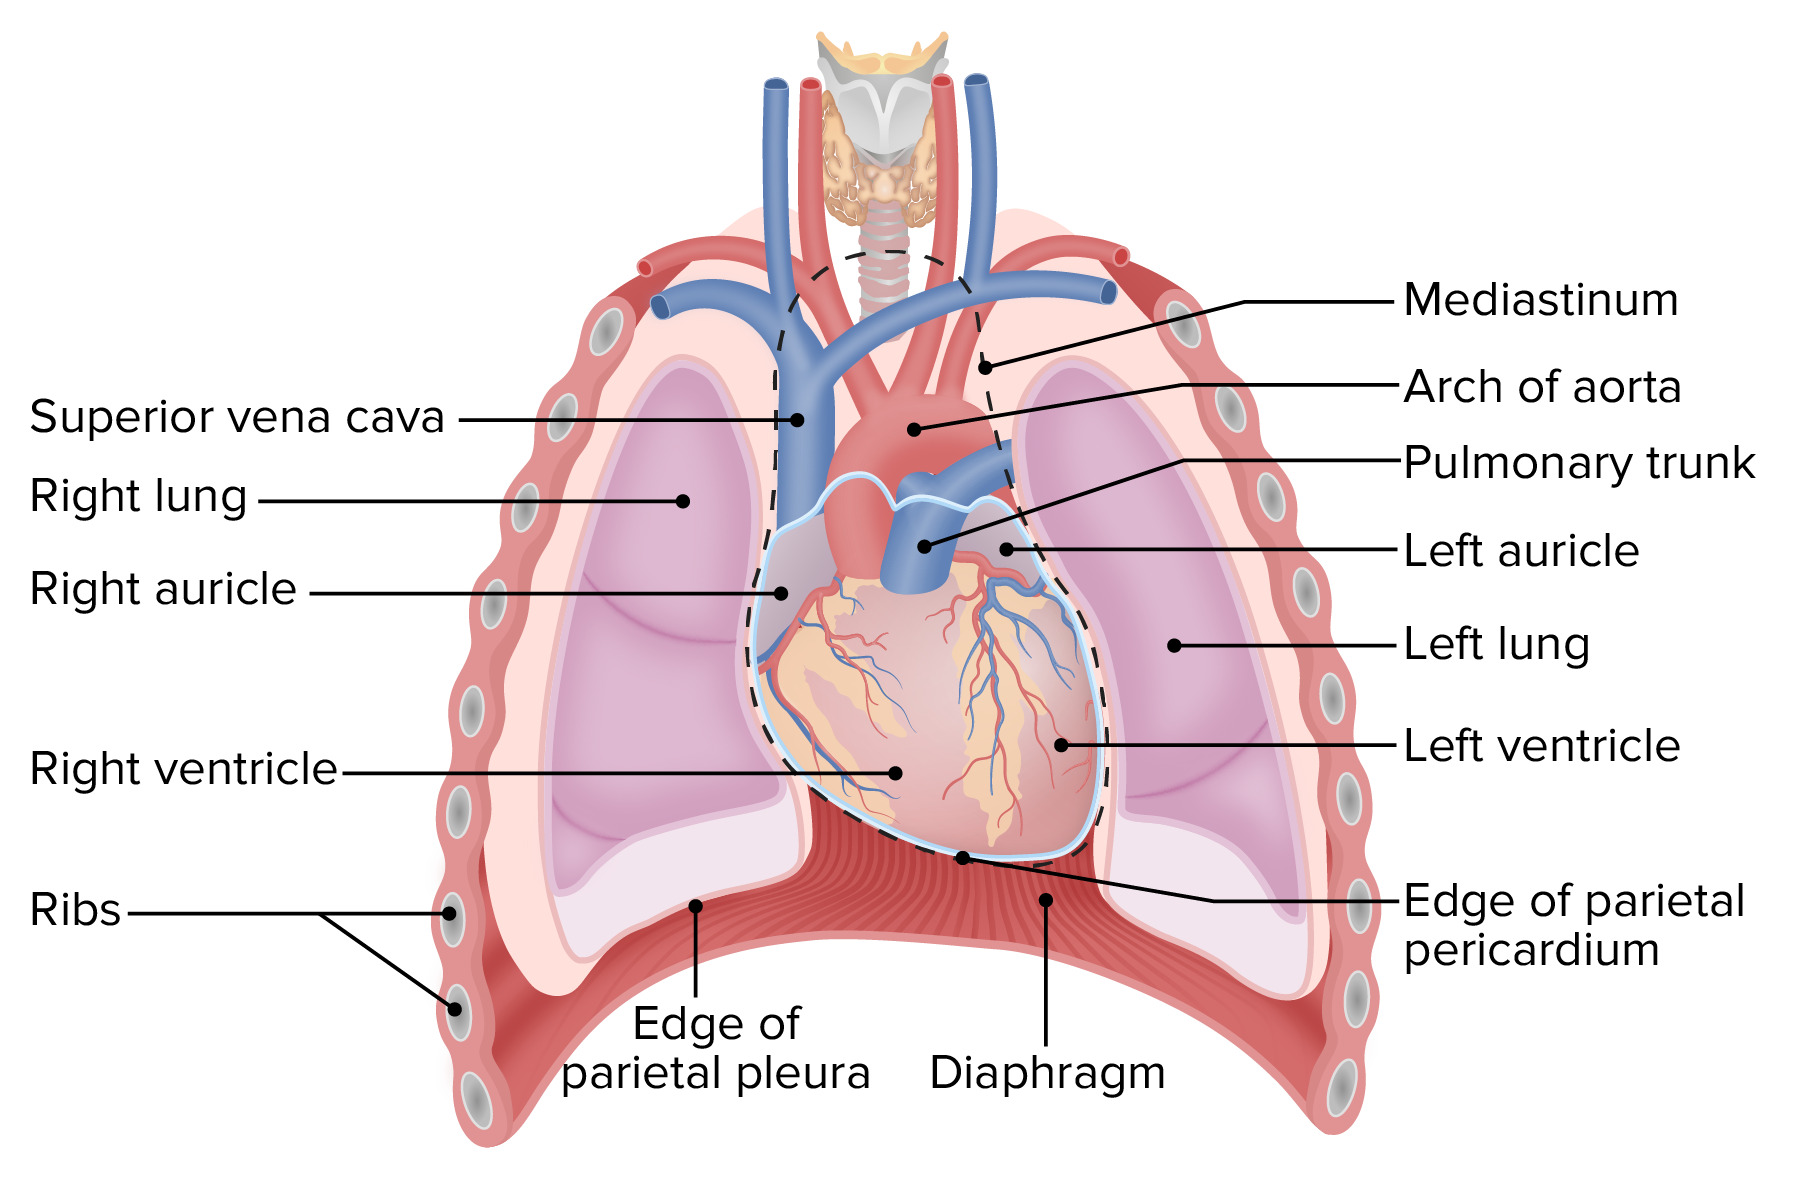
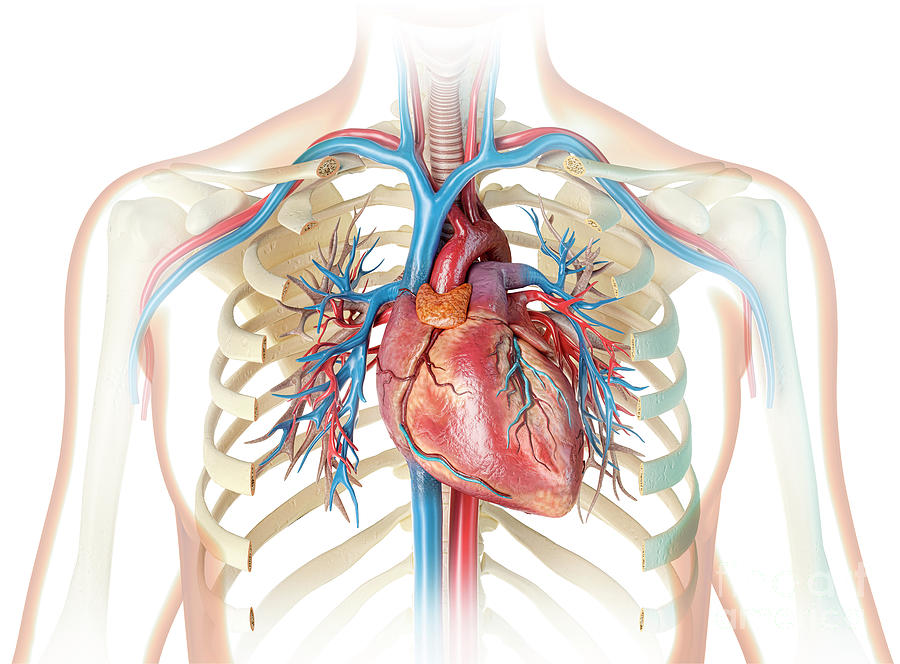
The heart is not located in the middle of your chest where most people point when they press a hand to their sternum. It sits slightly off-center, leaning toward the left side of the thoracic cavity. The apex — the bottom tip of the heart — points downward and outward toward the left midclavicular line, roughly at the level of the fifth intercostal space. The base sits higher up, resting on the diaphragm near the second rib. This positioning matters if you are studying anatomy, performing palpations, or interpreting imaging results. A common mistake beginners make is assuming the heart is centrally placed and not accounting for the leftward rotation when reading an X-ray or ECG. The organ occupies the middle mediastinum, which is the central compartment of the thoracic cavity. It lies between the lungs and sits posterior to the body of the sternum. About two-thirds of the heart mass extends to the left of the midline and one-third to the right. The pericardial sac anchors it in place, but there is still a small amount of mobility — enough that trauma or surgical intervention can shift its position noticeably. I spent time working with chest trauma cases early in my career and one particular edge case stands out. A patient came in with a left-sided pneumothorax, collapsed lung on that side. Because the pressure differential inside the chest changed, the heart shifted toward the right — a condition called mediastinal shift. If you relied on standard anatomical diagrams without understanding this dynamic, you would misinterpret the physical exam findings entirely. The workaround I used was straightforward: correlate bedside ultrasound with the physical assessment before drawing any conclusions. Palpation alone can tell you the apex beat location, but in a trauma setting you need imaging confirmation before proceeding with any intervention.
Why This Positioning Exists
The leftward tilt of the heart is not arbitrary. It relates to the development of the cardiovascular system during embryogenesis. The primitive heart tube loops to the left during the fourth week of gestation, establishing the orientation that persists throughout life. Functionally, the asymmetric placement allows the left ventricle — the chamber responsible for systemic circulation at higher pressures — to have more room and a more favorable geometry for contraction. The right ventricle sits more anteriorly, which is why it is closer to the chest wall and easier to access clinically. Another detail most people miss is the relationship between the heart and the esophagus. The esophagus passes directly behind the left atrium. This anatomical proximity is clinically relevant because esophagectomy or severe esophageal disease can impinge on the left atrium and alter cardiac function. Similarly, a dilated esophagus from achalasia can be visible on a chest X-ray and mistaken for a mediastinal mass if the radiologist does not account for the cardiac silhouette's normal borders.
Practical Applications
Knowing the precise location of the heart in the chest is essential for several procedures. When performing a pericardiocentesis to drain fluid around the heart, the standard subxiphoid approach targets the space just lateral to the xiphoid process, angling toward the left shoulder. Getting this wrong risks lacerating the liver or puncturing the lung. The parasternal approach is an alternative but carries a different set of risks including coronary artery injury. ECG lead placement also depends on understanding heart position. Lead V1 goes in the fourth intercostal space at the right sternal border, V2 at the same level on the left, V4 at the fifth intercostal space along the midclavicular line — which corresponds to the apex beat location in most adults. Misplacing V4 even one intercostal space too high or too medial can distort the QRS complex and lead to misdiagnosis of ventricular hypertrophy or infarction patterns.
Get the Full Details

Common Misconceptions
The idea that the heart is on the left side is only half true. Anatomically, the heart spans both sides of the midline. The right atrium forms most of the right border of the cardiac silhouette on a frontal chest X-ray. Only the apex and part of the left ventricle extend into the left hemithorax. This distinction matters when you are evaluating cardiomegaly or looking for pathologies like aortic dissection that may present with an abnormal mediastinal contour. Another misconception involves the so-called "point of maximal impulse." Many assume this is where the heart is anatomically centered. In reality, it marks the location where the apex of the left ventricle contacts the chest wall during systole. In a large person or someone with hyperinflation from COPD, this impulse may be difficult to palpate at all, even though the heart is in a perfectly normal position. Conversely, in thin individuals with a barrel chest, the PMI can shift slightly and appear more lateral than standard texts describe.
What Can Change Heart Position
Several conditions alter the normal placement of the heart within the chest. Dextrocardia is a congenital condition where the heart is mirrored to the right side, occurring in approximately one in ten thousand births. When accompanied by situs inversus, where all visceral organs are reversed, the patient is usually asymptomatic but requires careful consideration during any surgical or procedural planning. Missing this on a preoperative X-ray could lead to catastrophic errors. Pulmonary conditions also affect position. A large pleural effusion on one side pushes the heart away, while lung collapse or fibrosis on one side pulls it toward the affected side. I once reviewed a case where a chronic pulmonary fibrosis patient had such significant volume loss on the right that the heart was rotated nearly into the right hemithorax. Standard echo probe placement would have been ineffective without adjusting for the anomalous position. Heart Placement In Chest is not a static concept locked to textbook diagrams. The heart moves, shifts, and adapts based on pathology, body habitus, and individual variation. Understanding the standard position gives you a baseline, but clinical competence comes from recognizing when things are different and knowing how to adjust your approach accordingly. Whether you are studying for boards, learning procedural skills, or working in a clinical setting, take the time to correlate anatomical knowledge with imaging and physical examination. The diagrams are useful but incomplete without that practical context.