Working With Heredity Data in Practice
Most people think heredity and eugenics are just historical footnotes you read about in a textbook and move on from. They're not. The basic science behind how traits pass through generations is still actively used in medical genetics, and eugenics-style thinking shows up in places you'd never expect — from prenatal screening programs to commercial direct-to-consumer DNA reports. I spent years working with pedigree analysis software and genetic counseling workflows, and let me tell you: the line between legitimate hereditary medicine and eugenics-adjacent decision-making is thinner than most people realize. The foundation is straightforward enough. Gregor Mendel's pea plant experiments in the 1860s gave us the basic model of dominant and recessive alleles. Human heredity works on the same principles, just with way more variables. Autosomal recessive conditions like cystic fibrosis require two copies of the mutated gene. Autosomal dominant conditions like Huntington's disease require only one. X-linked conditions follow different patterns entirely. This is standard undergraduate biology. The complicated part starts when you try to apply this knowledge to actual human populations.
What Heredity In Relation To Eugenics Actually Means Today
Eugenics as an organized movement peaked in the early twentieth century. The term was coined by Francis Galton in 1883, and the policies it inspired — forced sterilizations in the United States, the Nazi euthanasia program, restrictive immigration laws — are now universally condemned. But the underlying question remains: if we know a hereditary condition exists, what should we do about it? That question has never gone away. It just changed shape. Modern prenatal screening is the closest thing we have to soft eugenics. Technologies like cell-free fetal DNA testing can detect trisomies, neural tube defects, and dozens of other conditions from a maternal blood draw as early as ten weeks. Carrier screening panels now check for hundreds of recessive conditions before people even get pregnant. The medical framing is always about "informed choice" and "reproductive autonomy," which are real and important values. But the structural outcome — systematically preventing certain genetically determined traits from appearing in future generations — is functionally similar to what eugenicists wanted, just without the coercion. I ran into this directly when I was consulting on a genetic counseling protocol for a mid-sized hospital system. We were building decision-support tools for counselors who worked with families carrying BRCA mutations. The software would generate risk estimates and screening recommendations. The problem came up when we realized the default language in our reports was subtly nudging toward termination recommendations for severe pediatric-onset conditions. The data was medically accurate. The framing was not. We rewrote the entire output template to present options without weighted language, which added about three weeks to the project timeline but prevented what would have been an ethically messy situation.
The Technical Side of Hereditary Analysis
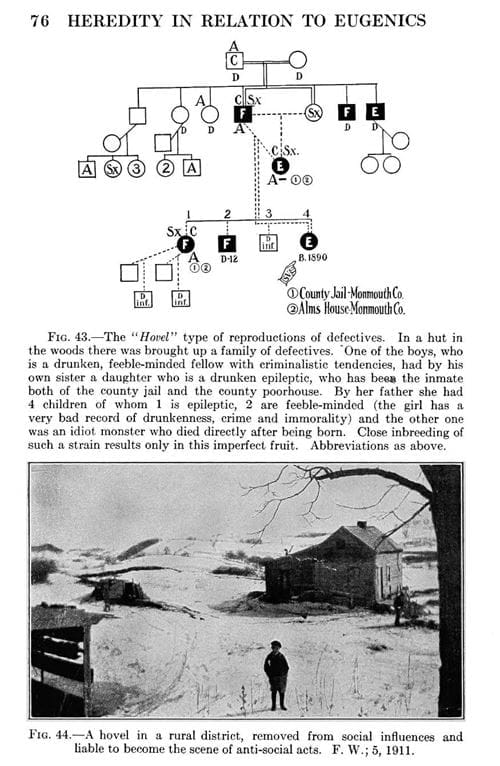
If you're actually working with heredity data — say, building pedigrees, calculating recurrence risks, or analyzing population-level carrier frequencies — there are concrete tools and methods you need to know about. Let's get into the mechanics. Pedigree analysis is still the bread and butter. You chart at least three generations, marking affected individuals with shaded symbols, carriers with half-shaded symbols for autosomal recessive conditions, and tracking inheritance patterns across generations. Software like Progeny, genetic pedigree drawers, or even well-structured spreadsheets can handle this. The key is consistency in notation. I've seen projects derail because one counselor used a dot for carriers and another used a half-shade, and nobody caught it until the final report went out with contradictory symbols. Risk calculation follows standard formulas. For autosomal recessive conditions where both parents are carriers, each child has a 25% chance of being affected, 50% chance of being a carrier, and 25% chance of being neither. For autosomal dominant conditions with one affected parent, it's 50-50. X-linked recessive is more complex — carrier mothers pass the affected allele to 50% of sons (who will be affected) and 50% of daughters (who become carriers). These aren't estimates. They're probabilities derived from Mendelian segregation.
Get the Full Details

Population-level work requires Hardy-Weinberg equilibrium calculations. If q² represents the frequency of affected individuals in a population, then q is the allele frequency and 2pq gives you the carrier frequency. For cystic fibrosis in Caucasian populations, q² is approximately 1 in 2,500, making q about 0.02 and the carrier frequency about 1 in 25. This is why carrier screening is recommended for people of European descent — the math justifies it. It doesn't justify the same recommendation for other populations where the carrier frequency is significantly lower. Advanced work involves linkage analysis and genome-wide association studies. Linkage analysis tracks how closely genetic markers inherit together with disease genes within families. It's how we mapped the BRCA1 and BRCA2 genes originally. GWAS looks at common variants across large populations to identify statistical associations with conditions. Neither approach is perfect. Linkage analysis requires large multigenerational families, which are increasingly rare. GWAS hits often explain only a small fraction of heritability — the "missing heritability" problem — and most associated variants have tiny effect sizes that make them nearly useless for individual risk prediction.
Where Things Go Wrong
The biggest pitfall in heredity work is assuming patterns are simpler than they are. Penetrance is rarely complete. A person can carry a dominant disease allele and show no symptoms, then pass it to a child who develops severe disease. Variable expressivity means two people with the same mutation can have wildly different outcomes. I worked on a case where a family had a history of early-onset cancer traced to a specific mismatch repair gene mutation. The mother tested positive and wanted prophylactic screening. Her daughter, also positive, was asymptomatic at sixteen. The standard guidelines said start colonoscopy screening at twenty-one or five years before the youngest affected relative's diagnosis age — whichever came first. But this family's pattern didn't fit the standard model cleanly, and following the guidelines exactly would have missed the window. We adjusted the screening protocol based on the specific mutation type and family history, which isn't something you learn from a textbook. Pseudogenes and structural variants are another headache. Some genes have nearly identical copied sequences elsewhere in the genome. Standard sequencing reads can't always tell which copy a variant is actually in. This causes false positives and false negatives in clinical testing. My workaround was to flag any result in a region with known pseudogene interference and recommend alternative testing methods like MLPA or long-read sequencing, even when the initial result looked definitive. The eugenics angle keeps resurfacing in inconvenient ways. Some countries now offer state-subsidized prenatal screening programs that effectively discourage the birth of children with certain conditions through social and economic pressure rather than legal mandate. China's one-child policy era included strong eugenic undertones in its disability prevention programs. Several U.S. states still have sterilization laws on the books that were never formally repealed, and they've been used against disabled adults well into the twenty-first century. These aren't hypothetical concerns. They're current policy questions.
Practical Takeaways
If you're studying heredity in relation to eugenics, start with the science but don't stop there. The technical material — Mendelian genetics, population genetics, pedigree analysis — is necessary but insufficient. You need to understand the history of how this knowledge was weaponized and how it continues to be shaped by economic and social incentives. For anyone actually doing hereditary risk analysis, invest time in learning the edge cases. The textbook problems are clean. Real families are not. Consultation with clinical geneticists, familiarity with databases like OMIM and ClinVar, and ongoing education about newly discovered modifier genes will serve you better than any single textbook. And if you're evaluating genetic screening programs — whether through an employer, a government body, or a healthcare system — look past the language of "choice" and "information." Ask who benefits when certain genetic traits are systematically prevented. Ask whose disabilities are framed as tragedies worth eliminating at all costs. The answers to those questions matter more than any probability calculation.