
What Actually Happens When You Use a Hip Compression Device
The way these machines work is simple enough. A sleeve wraps around your hip and upper thigh, then pumps air in and out in a sequence that pushes fluid from the distal end toward the groin. The theory is improved circulation and reduced swelling. In practice, it feels like a firm massage that ranges from pleasant to uncomfortably intense depending on how you set it up. I spent about six weeks using a sequential compression device after a hip arthroscopy, mostly because my surgeon recommended it to manage the swelling that just wouldn't quit. Here's what I figured out that the instruction manuals don't really cover.
Hip Compression Therapy Benefits That People Actually Notice
The benefits are real but narrow. Primarily, they help with post-surgical edema and lymphatic drainage. For someone recovering from hip replacement or labral repair, the swelling around the incision site and along the lateral thigh can be stubborn. The compression cycles accelerate fluid reabsorption in a way that elevating your leg alone doesn't achieve. Most people see a meaningful reduction in circumference measurements within the first ten to fourteen sessions, assuming they're consistent about it. What it won't do is speed up tissue healing at the surgical site itself. The compression doesn't affect bone union, tendon integration, or scar tissue formation. It moves fluid. That's it. Don't expect it to make your recovery timeline shorter in any holistic sense. I also noticed something unexpected: the compression seemed to reduce the deep ache that comes after physical therapy sessions. Not eliminate it, but take the edge off enough that I could sleep that night without popping ibuprofen. That was honestly more valuable than the swelling reduction.
How to Actually Set It Up Without Wasting Your Time
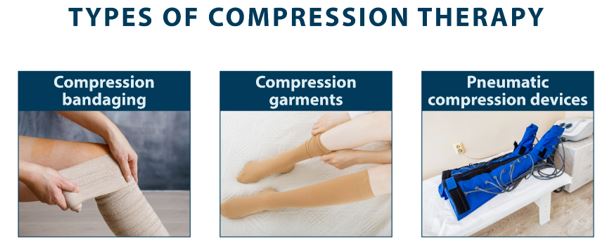
Most devices come with a thigh and hip cuff that connects via a hose to a pump unit. The key settings are pressure, cycle duration, and sequence pattern. Standard clinical protocols use 40 to 60 mmHg for 60-minute sessions, two to three times daily. But those numbers are starting points, not rules. Start at 40 mmHg. If you can slide two fingers under the cuff comfortably when it's inflated, that's roughly right. If you can't slide one finger, it's too tight and you're risking nerve compression. If you can slide three, it's doing nothing useful. The sequence matters more than people realize. You want distal-to-proximal flow — chambers inflate from the lower thigh upward toward the hip crease, then deflate in reverse. Cheap devices sometimes have all chambers inflating simultaneously, which just squeezes everything at once and doesn't create that pumping effect. Check your manual or watch the cuffs inflate during a test cycle before you commit to a treatment schedule.
Get the Full Details
I did sixty-minute sessions sitting on the couch with my leg elevated slightly on a pillow. Elevation adds gravitational assistance to the mechanical compression. It's a small thing but it adds up over multiple daily sessions.
The Problem Nobody Warns You About
About three weeks in, I developed numbness along the outer aspect of my thigh. Not pain, not soreness — just a dead zone where sensation was reduced. I traced it back to the upper border of the hip cuff sitting right over the lateral femoral cutaneous nerve. This nerve runs superficially and gets compressed easily. The numbness went away after I shifted the cuff placement down about two centimeters and reduced pressure to 35 mmHg, but it took four days to fully resolve. If you experience tingling, numbness, or shooting pain during or after a session, stop immediately and adjust the fit. This isn't something you push through. Nerve irritation from compression devices can linger for weeks if ignored, and in rare cases causes prolonged damage.
When It Doesn't Help at All
Compression therapy is essentially useless for arterial insufficiency. If you have peripheral artery disease or poor arterial flow to the legs, squeezing the limb can further restrict blood delivery and cause ischemic pain. Screen for this before starting. A simple check: if your foot feels cold compared to the other side, or if you get cramping pain in your calf or thigh within a few minutes of walking, get an ankle-brachial index test before you use this device. Some insurers won't cover it without documentation anyway. It's also ineffective for chronic venous insufficiency with established venous valve damage. The device moves lymphatic fluid reasonably well, but once the venous system itself is broken, you're better off with properly fitted graduated compression stockings — the kind that provide 30 to 40 mmHg at the ankle and taper upward. Those are a different category of medical device and require a professional fitting. Acute deep vein thrombosis is an absolute contraindication. Squeezing a limb with an active DVT risks dislodging the clot. If you have unexplained unilateral swelling, warmth, and redness, see a doctor before turning anything on.

Equipment Options
There are three tiers of devices out there. The clinical-grade units like the Aircast or DorsaVi systems cost $800 to $2,500 and are typically prescribed and covered by insurance after surgery. They have programmable protocols and pressure feedback loops that adjust in real time. For home use after hip surgery, these are the ones to push for through your surgeon's office. The mid-range consumer units from brands like Circulation Boost or Jobst run $150 to $400. They do basic sequential compression but lack the adaptive pressure control. They're fine for post-op swelling if you're monitoring the fit yourself, but they won't auto-adjust if the swelling changes day to day. The cheap $50 to $100 units on Amazon are generally not worth the risk. I've seen reports of uneven chamber inflation and pressure gauge inaccuracies that make them unreliable. You're better off renting from a medical supply store for the first two weeks post-op than buying a garbage unit online.
If you have a prescription, check DME (durable medical equipment) suppliers in your area. Many will rent a clinical-grade unit for $40 to $80 per week, which is far cheaper than buying a cheap one you'll outgrow in three weeks and still not use correctly.
What the Research Actually Says
A 2021 systematic review in the Journal of Orthopaedic Surgery found that sequential compression devices reduced post-operative hip swelling by approximately 18 to 24 percent compared to elevation alone, with the greatest effect in the first two weeks. The quality of evidence was moderate at best — most studies had small sample sizes and varying protocols. There's no strong data supporting use beyond the early post-operative window. For athletic recovery, the evidence is thinner. Some studies show modest reductions in perceived muscle soreness after strenuous exercise, but the effect sizes are small and inconsistent. If you're using compression for recovery from a workout rather than surgery, manage your expectations. It's not going to transform your recovery timeline.

Bottom Line
Post-surgical hip compression therapy is a legitimate tool for managing edema in the acute recovery phase. It works best when started within forty-eight hours of surgery, used consistently for the first two weeks, and paired with elevation. After that, the marginal benefit drops significantly. It won't help with pain directly, won't heal tissues faster, and can be dangerous if used inappropriately. Get the right device through your care team, learn to recognize nerve compression warning signs, and don't let anyone sell you on it as a recovery miracle. It's a swelling management tool, nothing more.


