What Actually Happens When You Treat a Hip Labrum Tear
The hip labrum is a ring of cartilage that seals the ball-and-socket joint. When it tears, you get mechanical symptoms: catching, clicking, sharp pain with deep flexion or rotation. The typical patient comes in after months of trying to ice it away and realizing the pain keeps coming back whenever they twist to get out of a car or sit through a long meeting. This is where Hip Labrum Tear Physical Therapy becomes relevant, and it's also where most people waste a lot of time. I work with athletes and desk workers who have both the same structural problem but totally different functional demands. A sprinter tearing their labrum during a change of direction hits it one way. An accountant who developed symptoms from sitting at 90-degree hip angles all day for three years hits it differently. The rehab framework is similar, but the loading patterns are completely different. You need to know which category you're in before you start putting them through exercises. The first thing I check is whether the symptoms are coming from pure structural damage or from a combination of structural damage and poor motor control around the joint. A lot of people have labral tears that are partly incidental. You see labral pathology on MRIs in asymptomatic people at a rate that surprised everyone when the studies came out. About 40% of people without hip pain will show a labral tear on imaging. That changes how you approach treatment significantly.
Hip Labrum Tear Physical Therapy: The Actual Approach
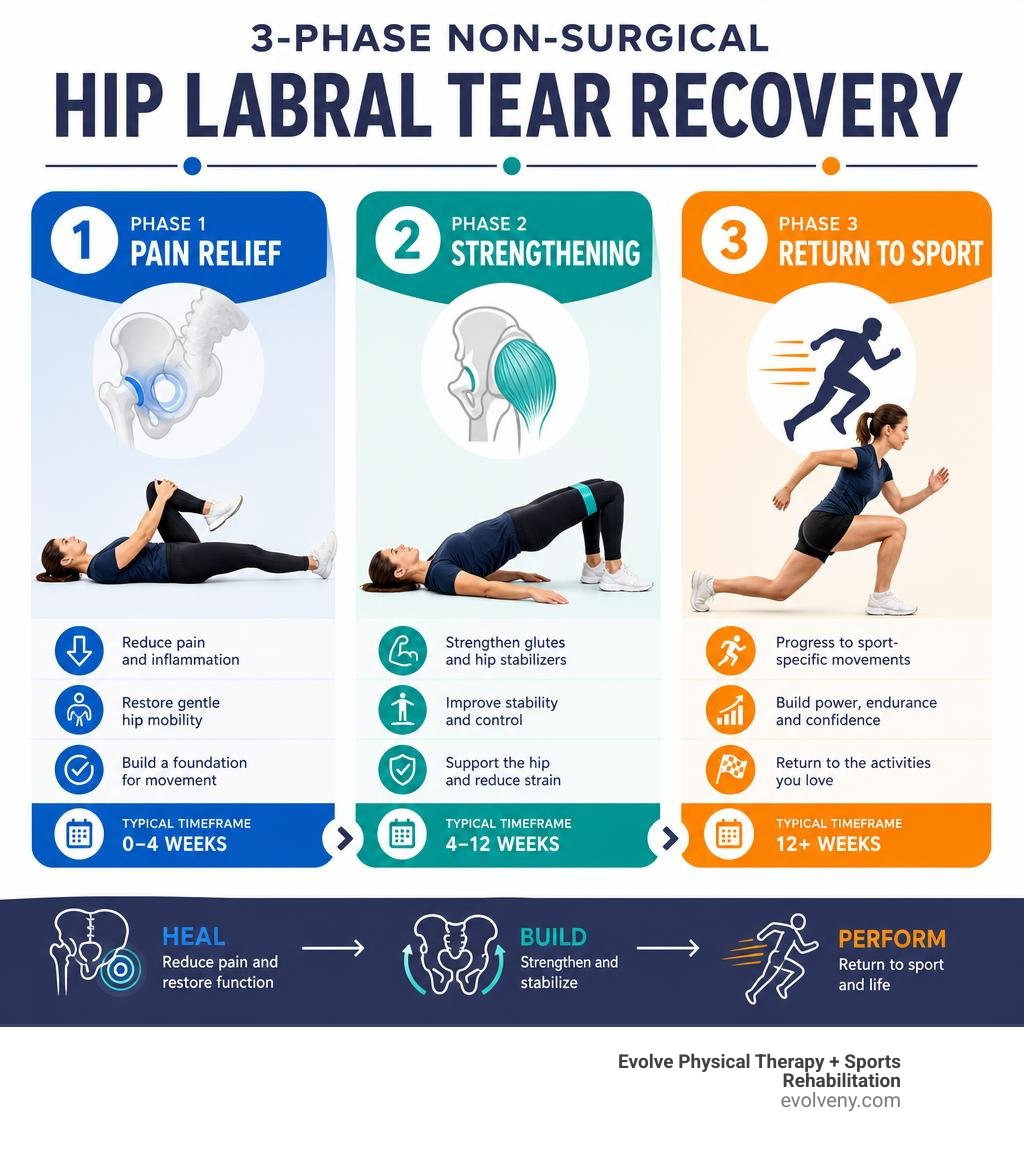
Acute phase management centers on symptom modulation through movement. Not rest, because complete rest makes the hip stiffer and the surrounding tissues weaker. You want controlled movement within a pain-free range. I typically avoid anything beyond 90 degrees of hip flexion and any combination of flexion plus internal rotation during the first two to four weeks. Those positions put the labrum under the most compressive and shear stress. The gluteus medius and maximus need to be activated early. Not strengthened heavily, just activated. The simplest way is a side-lying leg lift at about 30 degrees of abduction, held for five seconds, ten reps on each side. If that reproduces the sharp pain, you dial it back further. A lot of patients can do this without any symptoms and still have a tear. That's fine. The goal isn't to provoke the pain, it's to load the supporting structures without aggravating the torn tissue. Prior to starting any program, you should get a proper clinical assessment. An orthopedic specialist or a physical therapist who understands hip pathology should confirm the diagnosis and rule out other sources of groin pain like femoroacetabular impingement, athletic pubalgia, or lumbar referral patterns. Treating the wrong structure wastes time and lets the actual problem progress.
The Progression I Use
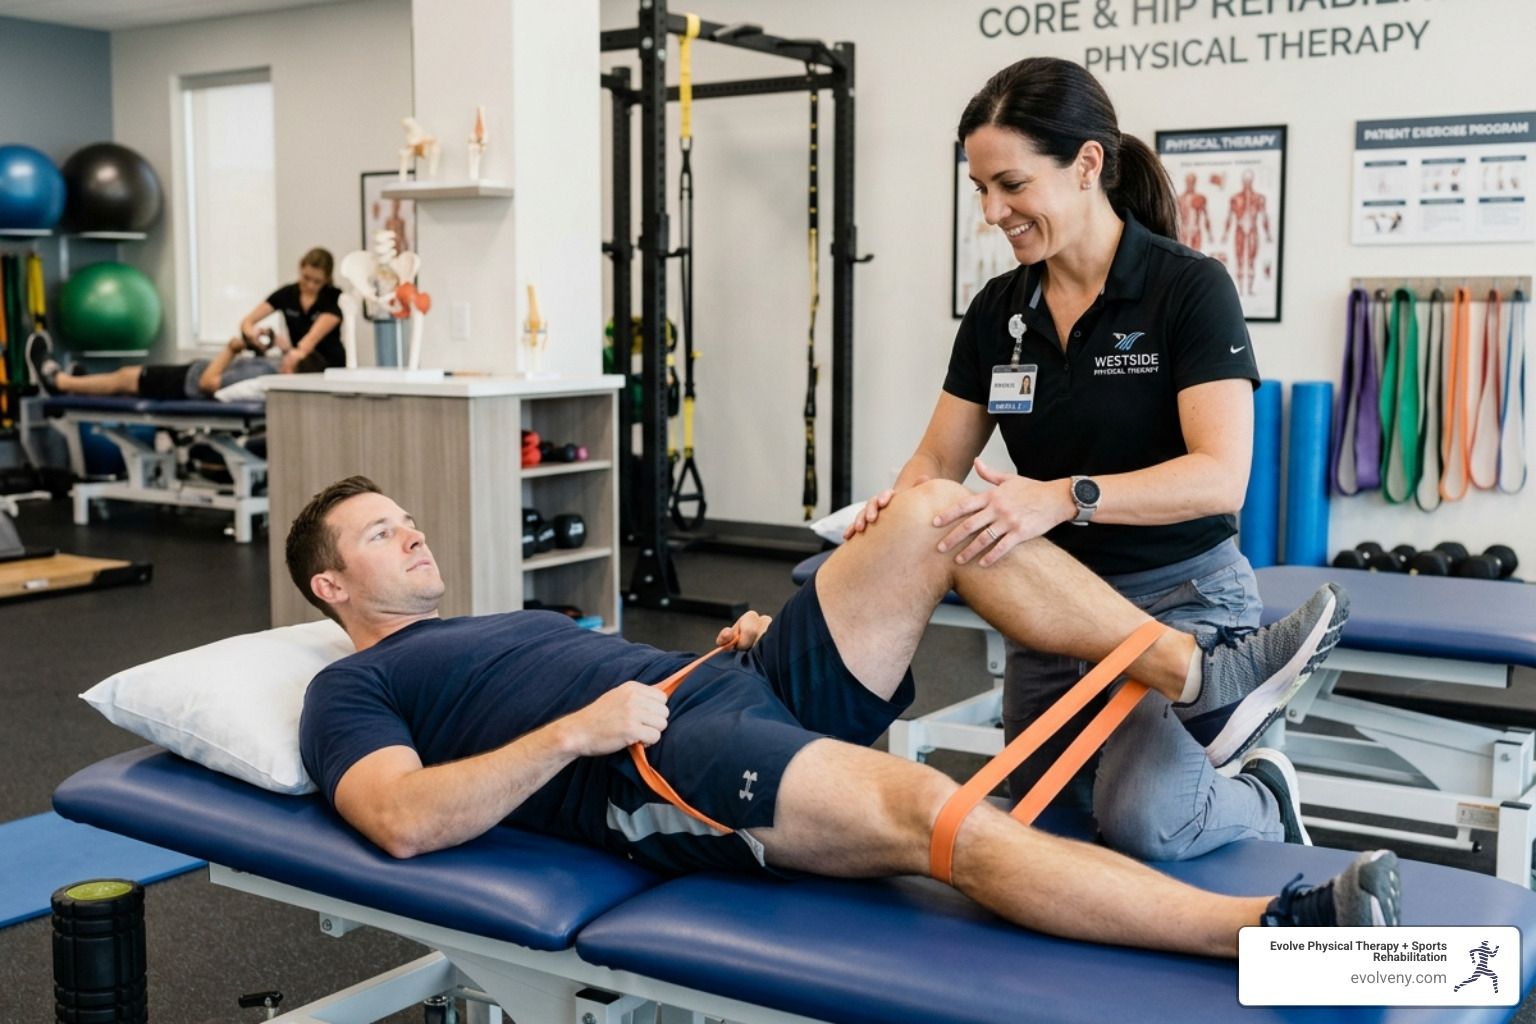
Weeks three through six shift toward loading the hip through a fuller range of motion. Bridges progress from double-leg to single-leg.clamshells with resistance bands get added. Mini-squats to 60 degrees come in before any deeper squatting is attempted. The key metric at this stage is that the patient can complete the exercises without a pain spike during the movement and without increased symptoms the following day. If symptoms escalate overnight, you backed off too slowly. By week six, most patients tolerate single-leg Romanian deadlifts with minimal weight. These build eccentric control through the posterior chain, which directly offloads the anterior joint structures where most labral tears occur. The single-leg RDL is one of those exercises that looks simple but requires genuine coordination. People who rush into it without first mastering bilateral hinge patterns usually compensate with their lumbar spine instead of their hips, which defeats the purpose entirely. Proprioception work matters more than people expect. Balance training on a firm surface progresses to a soft surface. Single-leg stands with eyes closed challenge the joint position sense that gets disrupted after a labral injury. This isn't fluffy stuff. Studies show that proprioceptive training alongside strength training produces better outcomes than strength training alone for labral pathology.
Get the Full Details
The Problem I Keep Running Into
Here's the edge case that always trips people up: a patient who has a posterior-superior labral tear and responds very differently to adductor strengthening than someone with an anterior tear. I had a patient last year who was doing standard rehab — lots of glute focus, minimal adductor work — and kept getting anterior groin pain after sessions. We were assuming it was residual inflammation. It wasn't. The tear was posterior, and her adductors were underloading because we'd been avoiding them. Once I loaded the adductors through isometric holds in a neutral hip position and progressed to resisted adduction, the anterior pain dropped by half within two weeks. Adding a straight-leg adductor squeeze against a pillow for 30-second holds, four sets, three times daily did more for her than any glute exercise we'd been prescribing. This is why the treatment plan needs to be individualized based on tear location and the patient's specific movement patterns. Generic protocols exist, but they don't account for this kind of variation, and that's where people stall for months without knowing why.
What This Doesn't Fix
Physical therapy won't heal a full-thickness labral tear. The labrum has poor blood supply, especially in the central two-thirds. What PT does is improve the environment around the tear so the joint functions better despite the damage. It builds strength, restores range of motion, corrects movement compensations, and reduces mechanical irritation. For many people, that's enough to return to normal activity without surgery. But there's a clear cutoff. If a patient has persistent mechanical locking, gives way, or has pain that doesn't improve after eight to twelve weeks of structured rehabilitation, surgical consultation is warranted. Arthroscopic labral repair or debridement becomes the conversation at that point. I've seen patients who kept pushing through six months of rehab hoping it would resolve when it never was going to, and by then the surrounding joint structures had adapted in unhelpful ways that made post-surgical rehab harder. Another limitation: if the patient has concurrent hip dysplasia or significant cam impingement, the labral tear is a symptom of a deeper structural problem. Isolating the tear and rehabbing it in a vacuum will only get you so far. The underlying geometry issue will keep reloading the repaired or healing tissue. Patients with dysplasia especially need to understand this upfront, because their rehab trajectory is longer and the threshold for surgical intervention is lower.
A Few Details People Miss
The direction of your symptoms tells you something about the tear. Anterior groin pain with flexion and internal rotation usually points to an anterior or anterosuperior tear. Posterior hip or buttock pain that worsens with extension and external rotation often indicates a posterior labral lesion. Knowing this helps you target which movements to emphasize and which to avoid during each phase. Pain during the night is another signal worth noting. If the patient is waking up multiple times per night with hip pain, the inflammatory load is high enough that the current activity level is too aggressive. Cutting the volume in half for a week while maintaining the same exercises usually brings nighttime symptoms under control. Not adding ice, not changing the exercise selection, just reducing the dose. Return to sport timelines vary wildly. A runner might be back to light jogging around week eight if progression has been clean. A soccer player needing cutting and pivoting might not be ready until week sixteen to twenty. The tissue hasn't necessarily healed more by then, but the surrounding musculature has adapted enough to protect the joint under higher demands. Rushing this timeline is the most common reason patients regress.

Most patients who commit to a consistent program see meaningful improvement within six to eight weeks. The ones who don't improve are usually the ones skipping sessions, returning to aggravating activities too early, or dealing with a structural problem that PT alone can't address. Neither outcome is a failure of the approach. They're just realities of how this injury behaves.