
Getting Through Hip Spacer Precautions Physical Therapy Without Losing Your Mind
You finish your hip spacer surgery and the surgeon hands you a one-page sheet of instructions that basically says "don't do anything for six weeks." That sheet is not comprehensive. It's a legal document, not a rehab plan. The actual work starts when you're home and someone tells you to begin "Hip Spacer Precautions Physical Therapy" but gives you zero detail on what that actually entails day to day. A hip spacer is a temporary antibiotic-impregnated cement ball placed in your hip joint while you recover from an infection or await revision surgery. It's not a replacement implant. It sits there holding your joint open so the surgeon can come back later and put in a real prosthesis. The spacer limits your range of motion dramatically. Your leg is essentially locked into whatever position was set during surgery, and the surrounding soft tissues are inflamed, weak, and confused. The physical therapy around this is entirely different from standard post-op hip protocols. You're not strengthening a new joint. You're preventing the things that go wrong when a joint has been immobilized with a foreign body inside it.
I spent three years working with post-arthrodesis and revision patients before I started seeing spacers regularly. The first time I worked with a spacer patient, I followed the standard pre-op strengthening protocol and nearly lost my mind. The patient could barely sit through a 10-minute session because the spacer shifted uncomfortably every time the hip rotated past a certain angle. That was my first lesson: you don't push the spacer joint. You work everything around it and let the joint sit still.
The Day-to-Day Reality
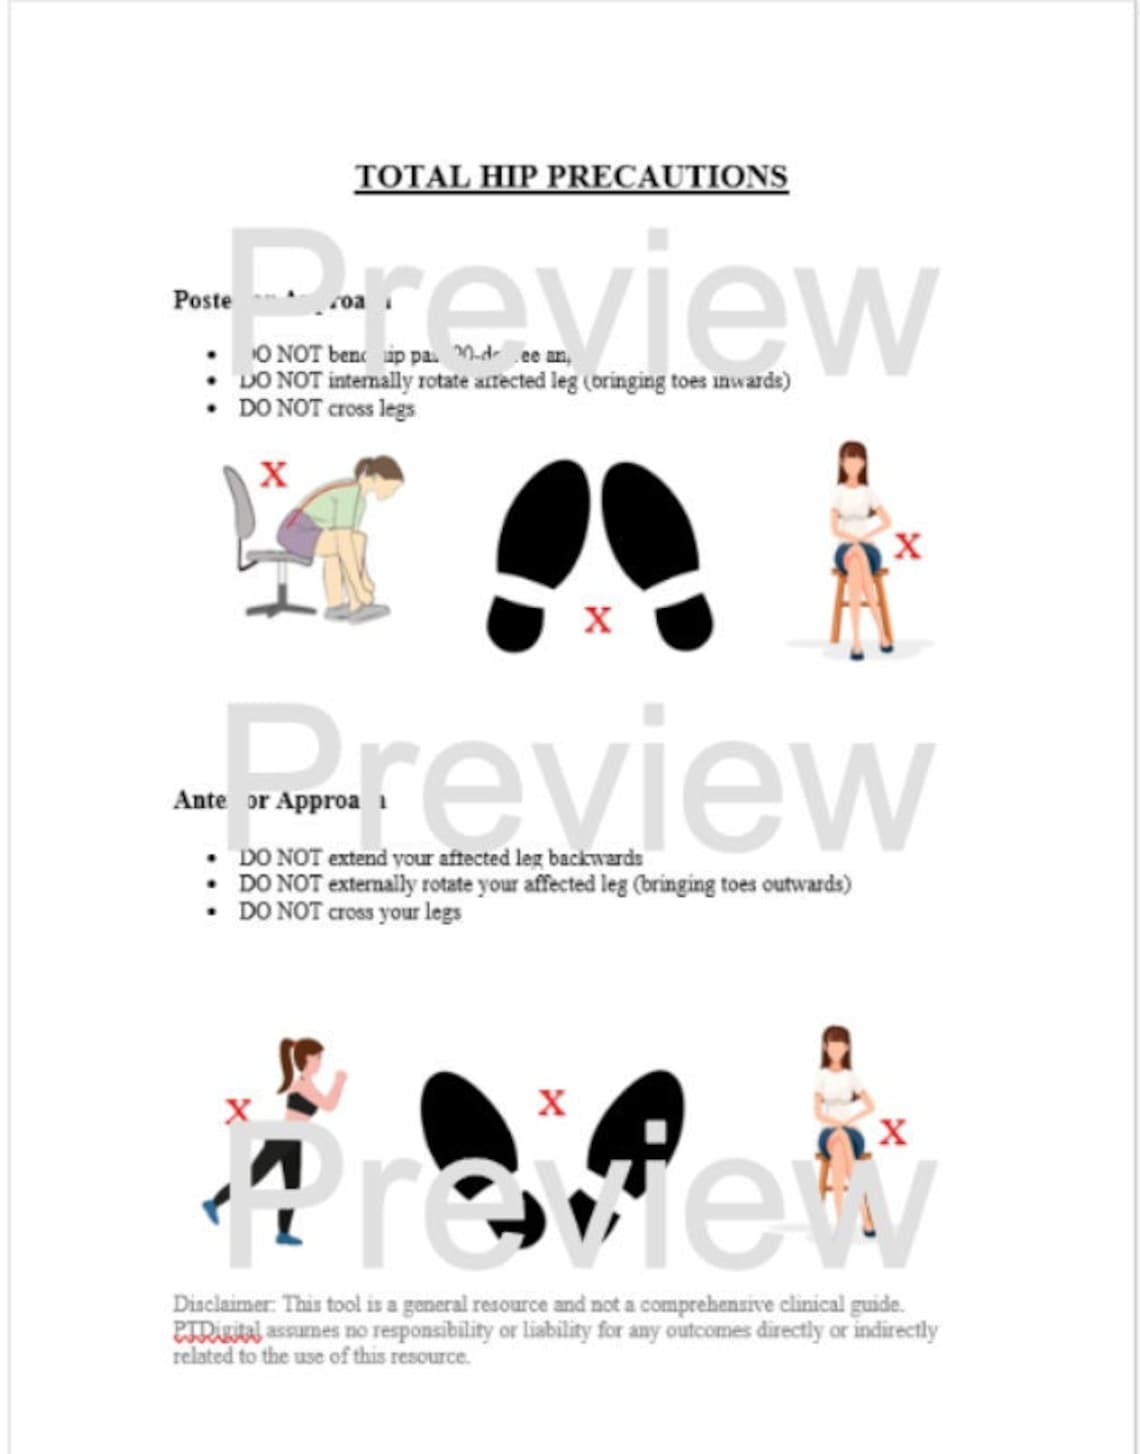
Most of what happens in the weeks leading up to spacer removal is about maintaining what you have rather than building something new. The spacer itself doesn't move much by design. The cement block is shaped to lock into the medullary canal. What moves is everything else — the surrounding muscles, the skin, the soft tissue envelope, and the opposite leg which is now doing double duty for walking. Early phase precautions are about protecting the surgical site: No flexion past the limit the surgeon set. This varies by spacer type and surgical approach, but I've seen limits range from 60 degrees of flexion for posterior approach spacers up to 90 degrees for anterior approach spacers. Ask your surgeon. Don't guess. The spacer can dislodge if you exceed the safe arc, and that's a complication most patients don't want to deal with eight weeks into their treatment.
Get the Full Details

No internal rotation beyond neutral for posterior approach spacers. No external rotation beyond what feels comfortable. The spacer has a preferred orientation. Work with it, not against it. Weight bearing status is another variable: Some surgeons allow weight bearing as tolerated with a walker. Others restrict to touch-down weight bearing. This depends heavily on whether the spacer was placed with the intention of maintaining limb length and whether the periprosthetic bone quality is decent. I had a case where the spacer was press-fit loosely because the patient had significant bone loss from the prior infection. That patient was non-weight bearing on that side for the entire six weeks. Another patient had a well-seated spacer with good bone stock and walked with partial weight bearing from day two. The difference in outcome between those two patients was not small.
What Actually Gets Done in Therapy
The exercises that matter during this phase are deceptively simple. Most of them don't involve the hip joint directly. Ankle pumps and circles. These prevent DVT. This is not optional. A hip spacer patient who isn't doing ankle pumps is a patient who has a higher risk of pulmonary embolism. I make every spacer patient do these during every session, usually while they're lying supine with their legs elevated slightly. Three sets of 20, twice a day minimum. If they can't do that at home, they need to be reminded weekly. Quadriceps sets and gluteal sets. Isometric contractions without moving the joint. The spacer doesn't want to move. The quads and glutes do not want to atrophy completely. This is where isometrics earn their keep. Hold for five seconds, relax for five, ten repetitions. Two to three times daily.
Hamstring sets. Often forgotten. Sit at the edge of the bed with the operated leg extended and gently press the heel down to create a hamstring contraction. The hip stays neutral. No flexion. Just the contraction. Knee range of motion on the operated side. This is where people get tripped up. The hip is restricted. The knee is not. A stiff knee after hip surgery is incredibly common and it affects gait more than you'd think. I use a standard passive knee flexion protocol — heel slides on a flat surface — as long as the hip doesn't flex beyond the prescribed limit. Some patients need a pillow under the knee to keep hip flexion minimal during this exercise. Upper body strengthening. You're going to be using a walker or crutches for weeks. Your arms need to handle that load. I typically add wall push-ups and seated rows with a resistance band early on. Not intense, but enough to prevent upper extremity fatigue from setting in.
The Problem Nobody Warns You About
I scarify over this occasionally in consultations because it genuinely catches people off guard. The contralateral leg — the one you're not operating on — takes a massive amount of abuse during spacer recovery. Walking with a walker and a non-weight-bearing or partially weight-bearing status on one side means the other leg is bearing 70 to 90 percent of your body weight for extended periods. I've seen patients develop groin strain on the unoperated side, IT band syndrome, and even sacroiliac joint irritation from the altered pelvic alignment. In one specific case, a patient came to me seven weeks post-spacer placement complaining of sharp pain in the right groin. She had a left hip spacer. Her right leg had been compensating for six weeks straight. No unusual activity. No falls. Just the mechanical load of walking with a walker and avoiding the left side entirely. I did a quick screening — straight leg raise was negative, no neurological signs, but there was significant tenderness at the right inguinal ligament insertion. The diagnosis was a medial hamstring proximal tendinopathy from chronic compensation. We modified her walker technique, added more rest intervals, and focused on isometric loading of the right hamstring without stretching it. It resolved in three weeks. The key insight here is that the unaffected side often becomes the limiting factor in spacer recovery, not the surgical side.
Progression and Transition Out of the Spacer Phase
When the spacer comes out — usually after infection clearance is confirmed with labs and possibly a aspiration — the physical therapy plan shifts almost overnight. You go from protecting a joint that shouldn't move to rehabilitating a joint that just got a brand new prosthesis inserted. This transition is where most patients get confused because the protocols are fundamentally different. The spacer phase is about preservation. The post-explant phase is about restoration. The good news is that the work you did during spacer precautions physical therapy — maintaining quad and glute strength, preserving knee ROM, keeping the opposite leg functional — gives you a meaningful head start once the new implant is in. Patients who came out of spacer therapy with decent quad control and an intact knee flexion arc typically adapt to their new hip replacement faster than those who spent six weeks mostly immobile. The difference isn't dramatic but it's measurable. In my experience, it can shave roughly two to three weeks off the overall rehabilitation timeline compared to patients who did minimal activity during the spacer period.
What Doesn't Work and When to Stop
Pushing through sharp pain at the surgical site is not a valid strategy. Discomfort from muscle atrophy and stiffness is expected. Sharp, localized pain near the incision or deep in the joint is not. If that happens, stop the activity and contact the surgeon. Spacer displacement is rare but it does happen, and continuing to exercise through joint pain is how you make it worse. Using a heating pad directly over the surgical site during the early weeks is not recommended. The skin and soft tissues are healing. Heat increases blood flow to an area that needs stability, not inflammation. Ice is fine for swelling management. Heat should be avoided until the incision is fully closed and the surgeon clears it. Attempting to stretch the hip into greater range of motion than prescribed is the single most common mistake I see. Patients believe that more mobility equals better recovery. During spacer therapy, that belief is wrong. The spacer is intentionally restricting movement. Fighting that restriction doesn't improve flexibility. It risks displacing the spacer or irritating the surrounding tissues to the point where the surgical site takes longer to heal.

Water immersion before the incision is fully healed and cleared by the surgeon is another risk. I've seen infections traced back to patients who sat in a warm bath two weeks after surgery because the therapist hadn't clarified the wound status. If the incision isn't fully epithelialized and the surgeon hasn't given explicit approval, no baths, no swimming, no hot tubs. Showers are usually fine with a waterproof dressing, but verify with the surgical team.
Practical Notes That Actually Help
Use a raised toilet seat. A standard toilet puts the hip into flexion that may exceed your precautions, especially if you're also doing any internal rotation during the sit-to-stand movement. A raised seat keeps the hip angle more open and reduces the demand on your quads during transfers. A reacher grabber tool is worth the twenty dollars. Bending to pick things up is a flexion violation waiting to happen. Having a tool that lets you retrieve objects without leaning forward saves you from making a mistake when you're tired or distracted. Ice after sessions is standard but should be limited to fifteen minutes at a time. Longer application doesn't reduce swelling more effectively and can cause reactive vasodilation, which is the opposite of what you want.
Document your pain levels and any changes in sensation. Numbness around the incision is common and usually resolves over months. But new numbness in the foot or toes, or any change in color or temperature of the operated limb, warrants immediate attention. These are not normal spacer recovery symptoms. The spacer itself can sometimes be felt as a hard lump through the skin, particularly in thinner patients. This is normal. It doesn't mean anything is wrong. It's just a block of cement in your hip joint. It will be there until the surgeon removes it.


