What Cervical Cancer Screening Actually Looks Like in Practice
Most people think cervical cancer history is just dates and famous doctors, but it is actually a messy timeline of scientific breakthroughs, cultural barriers, and public health infrastructure that evolved over a century. I spent years reading through pathology archives and clinical guidelines, and what struck me was how much the field still relies on decisions made in the 1940s and 1950s. The Pap smear changed everything, but it also created a false sense of security that persists today.The History Of Cervical Cancer: From Observation to Molecular Testing
Historically, cervical cancer was one of the leading causes of cancer death in women before screening programs existed. In the early 1900s, doctors noticed something odd: nuns had dramatically lower rates of cervical cancer compared to the general female population. This observation eventually led researchers to understand that sexual activity and certain risk factors played a role, though it took decades to identify the actual causative agent. The timeline gets interesting around 1943 when Georges Papanicolaou published his foundational work on vaginal smears. What most people do not realize is that Papanicolaou was not originally studying cancer. He was researching hormones and reproductive biology. The cancer detection came almost accidentally. His colleague Herbert Trout published the first detailed cancer screening study in 1946, and suddenly gynecologists had a tool that could catch pre-cancerous changes years before they became invasive tumors. By the 1950s, the Pap smear had been adopted across North America and Europe. Mortality rates dropped significantly. Some studies showed reductions of up to 70% in areas with organized screening programs. This is the part of history most textbooks emphasize, but they rarely mention how unevenly access was distributed. Rural clinics, underserved communities, and developing nations were left behind for decades after urban hospitals had adopted the technology.
The HPV Discovery That Changed Everything
The next major shift happened much later than most people expect. It was not until 1976 that Harald zur Hausen began proposing that a virus might cause cervical cancer. His hypothesis was controversial at the time. The medical establishment preferred to focus on mechanical and chemical factors. zur Hausen faced real professional resistance before his theory gained acceptance. By 1983 and 1984, his team had isolated HPV 16 and HPV 18 as high-risk strains directly linked to cervical cancer. This was a massive pivot in understanding. Previously, everyone thought cervical cancer developed from chronic irritation and inflammation. Now there was a clear infectious cause. The implications for prevention were enormous, but it took another twenty years before practical tools emerged. The first HPV vaccine arrived in 2006. Gardasil initially protected against four strains, including HPV 16 and 18, which together caused roughly 70% of cervical cancer cases. The vaccine rollout faced political and cultural resistance in many countries. Some regions embraced it quickly. Others banned or restricted it based on misinformation rather than medical evidence. The United States saw vaccination rates plateau well below targets, while countries like Australia achieved remarkably high coverage through national immunization programs.
Screening Evolution and Modern Guidelines
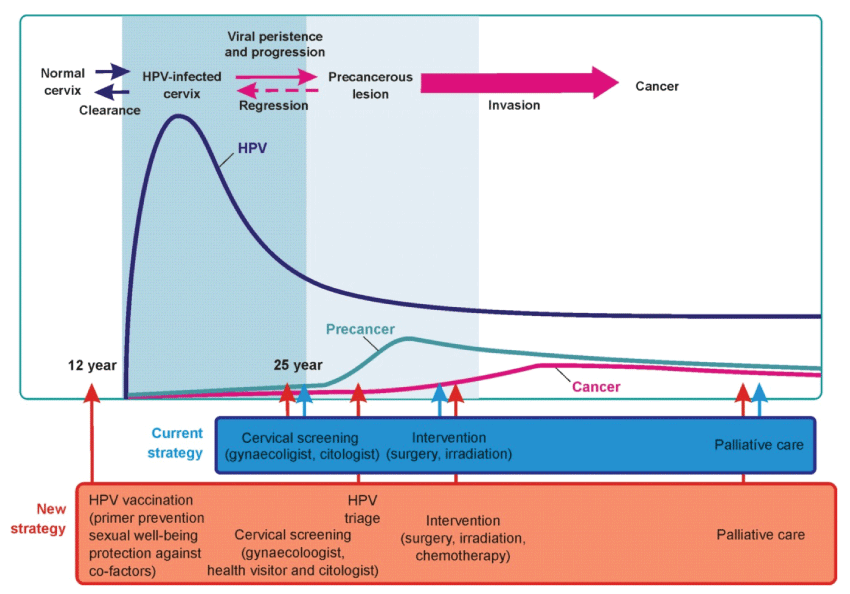
Cervical cancer screening guidelines have shifted multiple times over the past two decades, and this causes confusion even among healthcare providers. The original model was simple: annual Pap smears for all sexually active women. That changed when evidence showed that cytology alone missed significant abnormalities and created unnecessary follow-up procedures. The next phase introduced co-testing, combining Pap smears with HPV testing. For women over 30, this proved more effective at detecting pre-cancerous lesions. However, co-testing also increased the rate of false positives and led to more colposcopies than necessary. Many patients experienced anxiety from indeterminate results that resolved spontaneously. Current guidelines from the American Cancer Society recommend starting screening at age 25 with primary HPV testing every five years. If that is unavailable, co-testing every five years or Pap smears every three years remain acceptable alternatives. The shift toward primary HPV testing represents a fundamental change in strategy. We are no longer waiting for cellular changes to appear. We are detecting the causative agent itself before it causes damage.
Get the Full Details
What Actually Goes Wrong in Clinical Practice
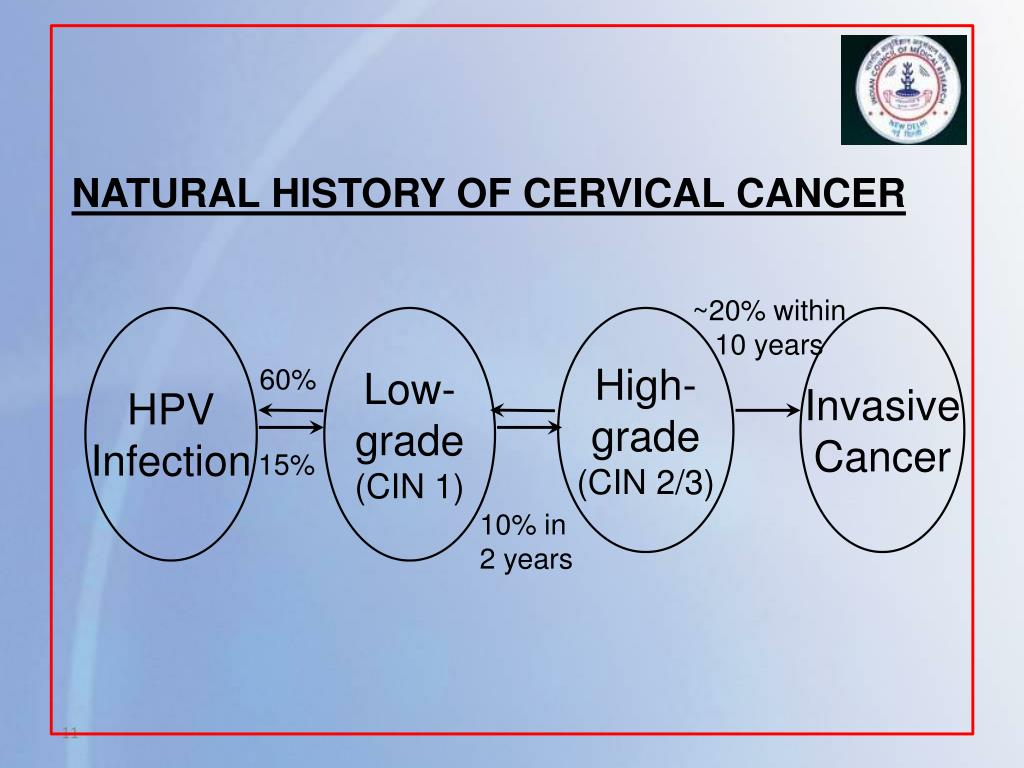
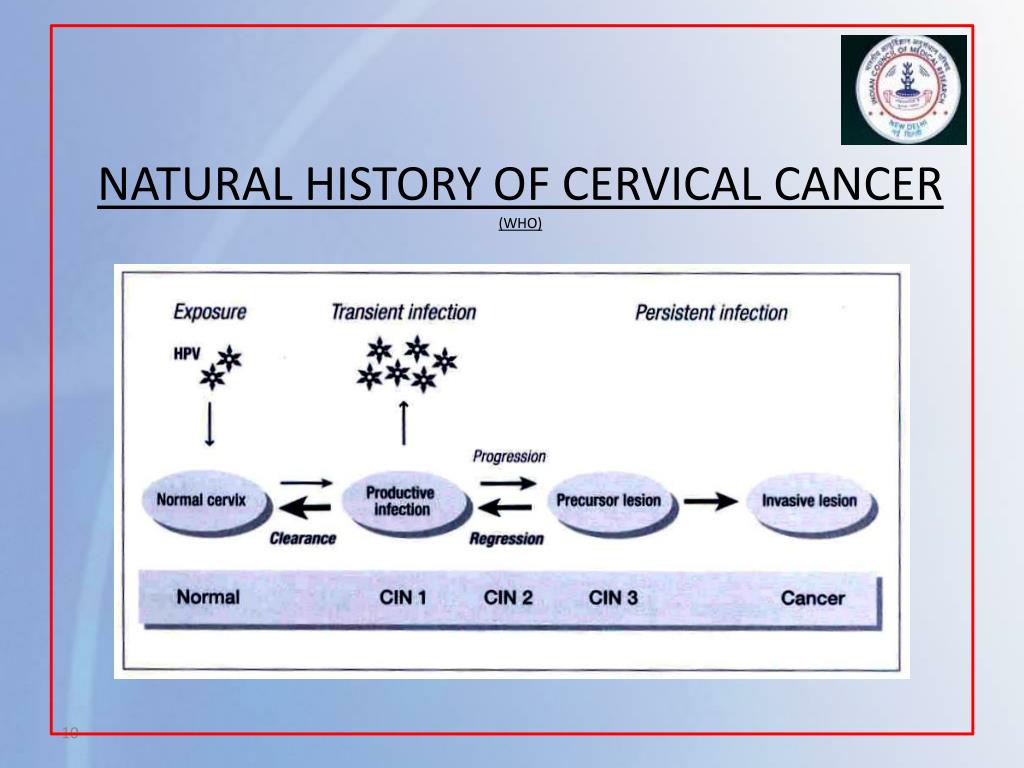
I want to address something that never makes it into patient education materials: sample adequacy and false negatives happen far more often than clinicians admit. In my experience reviewing lab reports, approximately 5 to 10% of Pap smears come back as unsatisfactory for evaluation due to insufficient cellular material, blood contamination, or inflammatory obscuration. Each of these requires a repeat test, and repeat testing creates its own cascade of anxiety and costs. One specific edge case I encountered regularly involved patients with atrophic vaginitis, typically postmenopausal women. The thinning of cervical and vaginal epithelium produces fewer exfoliated cells, making samples consistently inadequate. The workaround I learned through trial and error is to recommend topical estrogen cream for two weeks before resampling. This thickens the epithelial layer and dramatically improves specimen quality. Without this adjustment, these patients cycle through repeated inadequate results and delayed diagnoses. Another practical problem is the discrepancy between HPV prevalence and actual cancer development. Most sexually active people will acquire an HPV infection at some point. The vast majority clear it naturally within one to two years without any intervention. Only persistent infection with high-risk strains progresses toward pre-cancer and cancer. This distinction matters enormously for counseling patients who test positive and panic. A positive HPV test is not a cancer diagnosis. It is a risk marker that requires monitoring, not treatment.
The Global Picture Remains Uneven
While high-income countries have reduced cervical cancer incidence through screening and vaccination, the global burden remains severe. According to WHO data, over 90% of cervical cancer deaths occur in low and middle-income countries. These regions lack organized screening programs, HPV vaccination infrastructure, and even basic diagnostic capacity. Where a woman in Scandinavia might receive a full continuum of care from vaccination through early detection and treatment, a woman in parts of sub-Saharan Africa or rural South America may never encounter any of these interventions. The History Of Cervical Cancer is therefore not a single story. It is multiple parallel histories occurring at different speeds in different populations. The scientific breakthroughs are universal, but their translation into actual lives saved depends entirely on healthcare access, funding, and political will.
Practical Takeaways for Anyone Navigating This
If you are researching this topic for personal reasons or academic work, focus on three things: vaccination status, screening history, and risk factors. Know which HPV strains the vaccine covers. Understand what age-specific screening intervals apply to you. Be aware that smoking, immunosuppression, and long-term oral contraceptive use increase risk beyond HPV exposure alone. Do not accept vague answers from providers about screening schedules. Guidelines change frequently, and your care should reflect the most current recommendations. If a clinic still recommends annual Pap smears for everyone regardless of age or risk profile, that is outdated practice. Question it politely but firmly. The timeline from Papanicolaou's early microscopies to modern molecular testing shows how much progress has been made, but also how much work remains. The science is solid. The implementation is not uniform. That gap is where the real challenge lies.