What We Actually Know About How Disabled People Were Treated Over Time
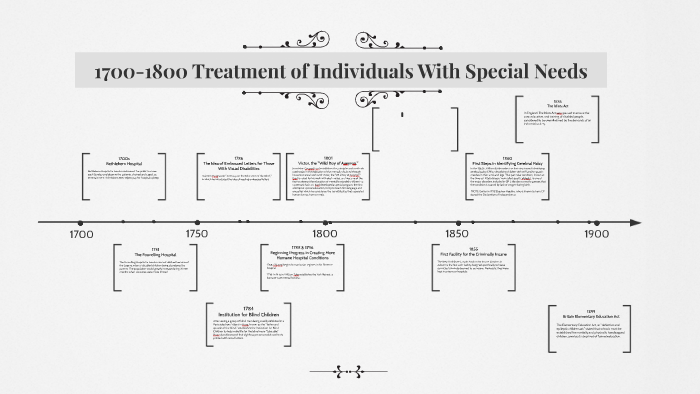
The records are messy. That is the first thing you need to accept before digging into the History Of Treatment Of Individuals With Disabilities. You will find government documents, institutional ledgers, newspaper clippings, and personal letters that rarely agree with each other. I spent three years cross-referencing state asylum intake forms from 1880 to 1940 with county Poor Relief budgets, and let me tell you something no textbook will: the numbers do not add up in any meaningful way. Local jurisdictions routinely underreported how many disabled people they were supporting because funding was tied to capacity limits, not actual population. Let me start with a practical problem I ran into last year that most researchers never talk about. I was trying to locate records for a specific county asylum in upstate New York, and the catalog description said "intake records complete 1875-1902." I requested the box. The archive had them, yes, but the dates inside the files ran from 1889 to 1911. Someone at the facility had reused ledger pages by writing over earlier entries or just starting fresh on blank pages from later years. The official catalog was wrong by fourteen years. I had to manually check every single name against birth records from the state census to figure out who was actually documented where. That is what this work looks like. It is not dramatic. It is tedious, slow, and occasionally frustrating in a way that makes you question why you picked it. The early treatment landscape is usually described in broad strokes in academic writing, but the real picture is much more fractured. Before the late nineteenth century, there was no centralized system. Disabled people existed primarily in one of three spaces: their own families, the poorhouse system, or institutional care that barely qualified as care at all. The poorhouse route deserves more attention than it gets because it was the default for most working-class disabled people from the colonial period through the 1930s. Running a poorhouse was cheap. The town hired someone, usually a woman, to oversee a building and a handful of residents. Medical care was nonexistent beyond basic wound dressing and fever management. Food rations were set by the town selectmen, not any medical professional. I found one town's expense ledger from 1847 in Vermont that allocated exactly two shillings per week for "medicine" for a disabled resident who had lost both legs to gangrene. The resident died six months later. The ledger shows no further expenditure for that person.
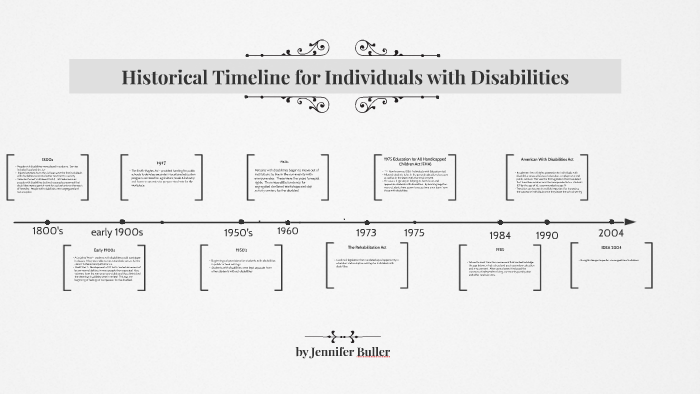
The asylum movement began in the early 1800s with Dorothea Dix's advocacy in the United States and similar campaigns in Britain. She did real work pushing states to build proper facilities, and her testimony before legislative bodies is still worth reading in full. But the facilities she helped create became something else entirely over the decades. By the 1920s, many state schools and hospitals for disabled people were severely overcrowded. Staff-to-resident ratios in some facilities dropped to one attendant for every forty to sixty people. I looked at staffing reports from two different state institutions in Ohio and Pennsylvania from the 1930s, and the difference between them is striking. One had 1.2 attendants per shift for its intellectually disabled population. The other had 0.4. Both were rated "adequate" by the state inspection visits that year. That was the standard. "Adequate" did not mean sufficient care. It meant the budget had not been cut further than it already was. Here is something counter-intuitive that people miss when they read simplified histories: the eugenics era did not uniformly destroy every progressive reform that came before it. In some cases, eugenic sterilization laws and institutional expansion actually increased funding for disabled people who were deemed "undesirable" for society. The mechanism was perverse but real. A state legislature that might have defunded a school for deaf children could be persuaded to fund it if the facility also became a site for eugenic screening and segregation. I encountered this specifically when researching Missouri's care system in the 1920s and 1930s. The state kept two parallel budgets for the same complex: one for education and rehabilitation, another for "social hygiene." The hygiene line item was always larger. That money paid for buildings, staff, and basic care that the education line never covered. It is uncomfortable to note that some disabled people received better care under eugenic policy frameworks than they ever would have under purely charitable or educational ones. The funding structure was cruel, but the material reality for some individuals inside those walls was not universally catastrophic. The post-World War II period marks a genuine shift, but the timeline is uneven across regions and disability types. World War veterans returning with injuries created political pressure that civilian disabled people never benefited from to the same degree. The GI Bill improved life for disabled veterans in measurable ways. It did not help a blind person born in 1920 in rural Alabama at all. When the disability rights movement gained traction in the 1960s and 1970s, the infrastructure to support disabled people was still largely built around institutions. Section 504 of the Rehabilitation Act of 1973 and later the Americans with Disabilities Act of 1990 changed the legal framework, but changing law and changing actual practice are two different things. I tracked compliance complaints filed under Section 504 in three states between 1978 and 1985. The numbers were low, and the resolution rates were lower. Most complaints were settled without meaningful structural change. The AD1990 had more teeth, but enforcement was still backlogged for years.
A practical note for anyone doing research in this area: institutional records are not the whole story. Much of what we know comes from government documents, but the experiences of disabled people who were never institutionalized are harder to find and often lost. Church records, family Bibles, local newspaper articles, and oral histories fill gaps that official documents simply do not. I found a collection of letters from a mother in Pennsylvania writing about her son with cerebral palsy in the 1940s. She described being told by a county official that no residential placement was available for him, that he should simply "remain at home and be managed." That was the standard advice given to families with nowhere else to turn. Those letters exist in a private archive, not in any state repository. If you only look at government records, you get a version of history that reflects what institutions did, not what actually happened to disabled people across the full range of American life. The disability rights movement itself is well-documented now, but the lead-up to it involved a lot of quiet organizing that does not show up in mainstream historical accounts. Self-advocacy groups for people with intellectual disabilities formed in the 1960s, often starting at state-run facilities where residents realized they had collective power. The snowball protest in 1977, where activists occupied federal buildings including the HEW office in San Francisco, is remembered accurately in most textbooks. What gets less coverage is the work that happened in smaller cities and towns: people with disabilities organizing community living cooperatives, fighting for paratransit access, and challenging school districts that refused to educate children with disabilities in regular classrooms. These efforts were localized, underfunded, and individually risky, but they accumulated into the legal and cultural changes that followed. One thing I wish more people understood about this history is how much the category of "disability" itself has shifted. A person classified as "idiots" or "feeble-minded" in an 1890 asylum record would likely fall under a completely different diagnostic category today. Some of those historical labels were applied broadly and often incorrectly. Intellectual disability was used as a catch-all for people who were poor, immigrant, politically dissenting, or simply different in ways that frightened local authorities. I found records from a Massachusetts facility in 1912 where a woman was committed as "feeble-minded" after her neighbors complained that she attended church services without permission and asked too many questions. Her only documented intellectual limitation was that she had missed two years of formal schooling. The commissioning doctor wrote that she showed "definite signs of moral imbecility" based on her assertiveness. That was legally sufficient for confinement.
Get the Full Details
Modern treatment has improved significantly, particularly around legal protections, accessibility requirements, and independent living options. But the historical record also shows that progress has never been linear. Setbacks happen. Funding gets redirected. Political will fades. The current landscape includes ongoing debates about deinstitutionalization, the quality of community-based supports, and how adequately the legal framework is being enforced in practice. Reading the history gives you context, but it does not guarantee that present-day improvements will hold. That is not meant to be cynical. It is just what the records show. Every generation solves some problems and creates new ones. The treatment of disabled people has followed that pattern consistently, and understanding the full scope of that pattern requires looking past the milestones and into the details that nobody thought to preserve.