Understanding the actual workflow of hospital-based clinical research
Most people think running a study inside a hospital is about good intentions and paperwork. It isn't. It's a maze of overlapping regulatory bodies, broken electronic health record integrations, and clinicians who genuinely do not have time for your data collection forms. The people who survive this environment learn to treat the bureaucracy as part of the protocol, not an obstacle to it.Getting Hospital Research Studies Approved Without Losing Your Mind
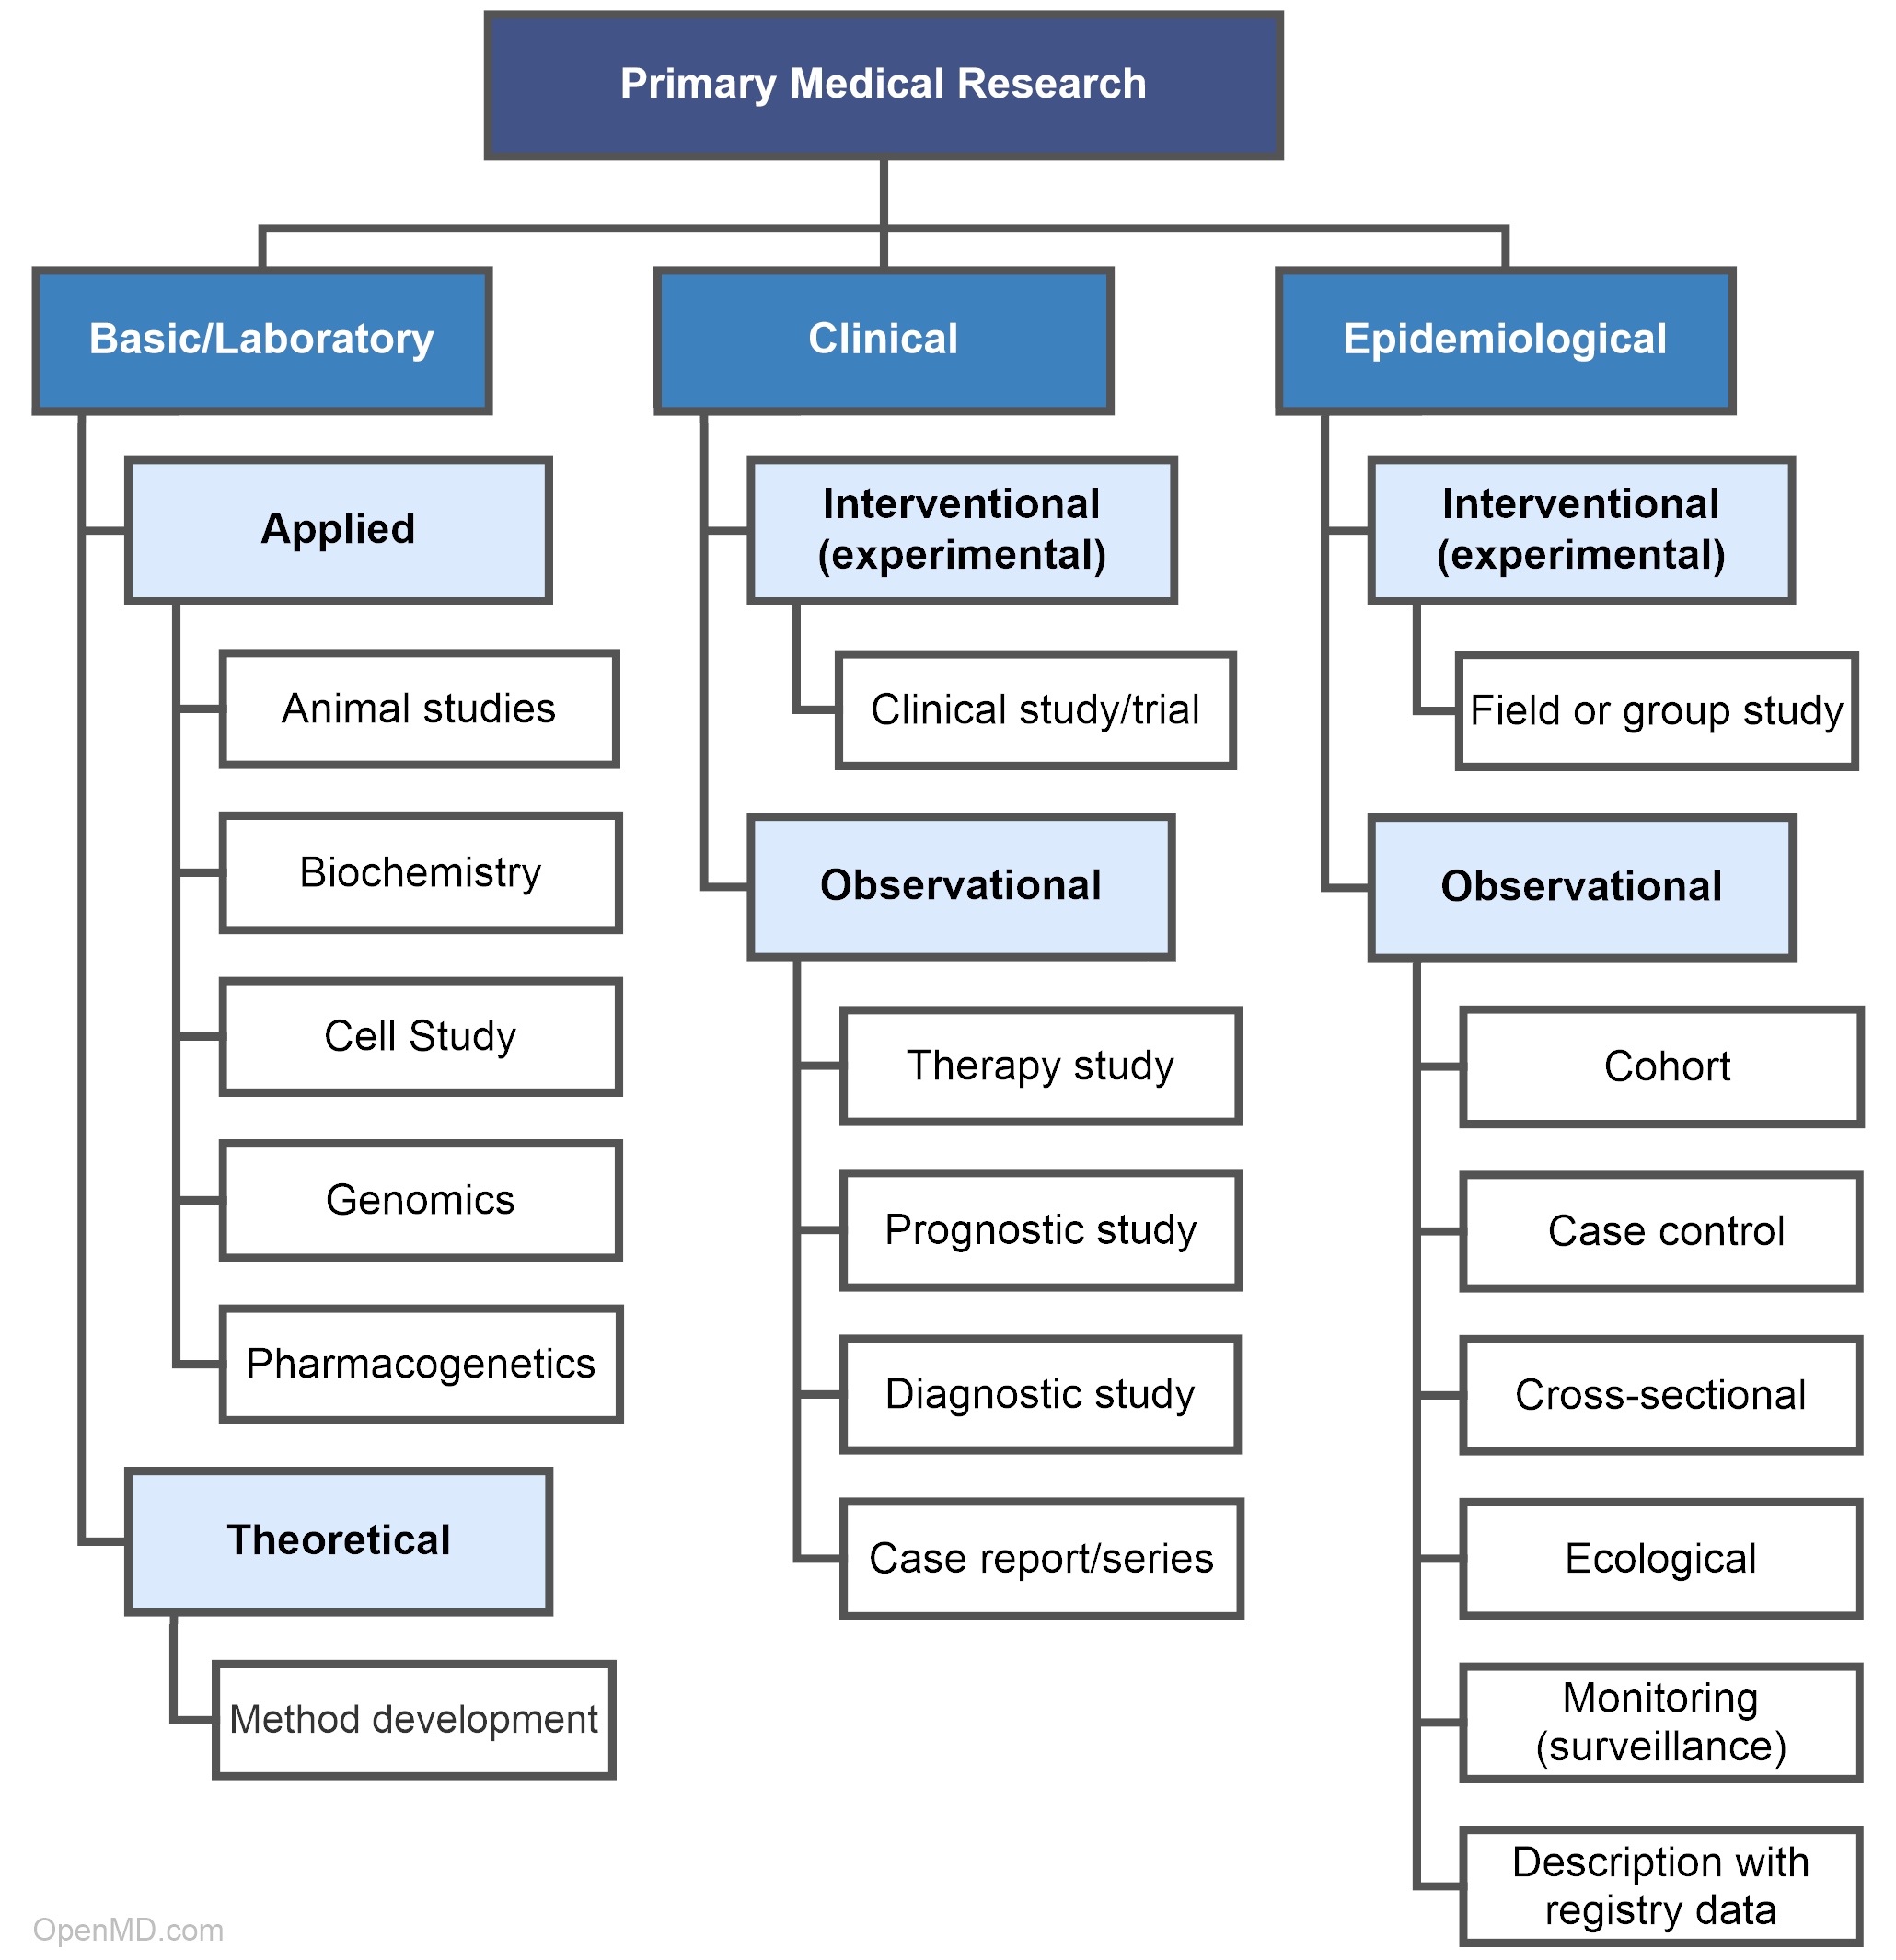
The first thing I learned the hard way is that Institutional Review Board timelines vary wildly depending on the study type. Full board review can take anywhere from four to twelve weeks. Expedited review is faster but has strict eligibility criteria — you need to know which category your study falls into before you even submit, because misclassification means resubmission and another three-to-six week delay. Risk level dictates everything downstream, including what consent documents look like and whether you need a data safety monitoring board. I once submitted a retrospective chart review study that was initially sent back for full board review. The protocol looked prospective on paper because of how the objectives were phrased. I rewrote the aims section to clearly state no new clinical decisions would be made based on study data and that all patient encounters were standard of care. Resubmitted as expedited, approved in two weeks. The wording matters more than the science at this stage.
The practical reality of patient recruitment in clinical settings
Recruitment in hospitals is where most studies quietly die. You can have a perfectly designed protocol and still fail to recruit because no one told the attending physicians they were supposed to screen their own patients for inclusion criteria. I've seen three-month recruitment targets blown because the research coordinator hadn't scheduled a single shift in the oncology unit during hours when attendings were actually seeing patients. The workaround that actually works: build a recruitment log directly into the EHR if your institution allows it. Set up a smart phrase or order set that triggers when a patient meets criteria. This cuts your identification time from manual chart review, which takes about twenty minutes per patient, down to roughly three minutes of reviewing flagged encounters. Not every hospital system supports this, but if yours does, use it. If not, at minimum coordinate with nursing leadership so they know which beds to flag. Consent is its own trap. The process usually takes forty-five to ninety minutes depending on complexity, and patients are rarely in the headspace for deep processing when you approach them. Having a licensed clinician co-present for complex consent discussions significantly improves comprehension rates and reduces later disputes about whether the patient understood the randomization process.
Data management and the hidden costs
Every hospital research study I've managed has had a data reconciliation phase that consumed roughly thirty percent of the total project timeline. Raw data from EHR exports doesn't match case report forms. It almost never matches. Coding differences, duplicate entries, timestamps that don't align across systems — you will spend a week just figuring out why patient-level vital signs differ between your data source and the electronic data capture system. I started requiring data validation scripts at the point of entry rather than at the end. It's not glamorous but it prevents the worst kind of delay: discovering six months into data collection that your primary endpoint variable was pulled from a field that gets overwritten during routine clinical workflows. That happened to me once. We lost the first eight enrolled patients' data for the primary analysis and had to extend recruitment by four months to compensate. Never again.
Get the Full Details

Regulatory compliance is not optional and it will bite you
HIPAA requires a specific waiver or authorization depending on whether your study is prospective or retrospective. De-identification standards under the Safe Harbor method remove eighteen specific identifiers, but many people miss that dates like discharge dates still count as identifiers if they could link back to an individual in a small hospital population. If you're doing any public reporting of results, this catches you. Food and Drug Administration regulations apply differently depending on whether your study involves an investigational new drug, a device, or just an observational design. Getting this wrong at submission means the IRB won't even review your protocol. I always verify the regulatory pathway before writing the Methods section instead of after, which saves the standard two-week revision cycle most people encounter.
When Hospital Research Studies don't work and what to do instead
Not every question needs a prospective randomized controlled trial inside a hospital. Many research questions are better served by pragmatic trial designs that integrate intervention into normal clinical workflows, or by using existing administrative claims data for observational analysis. A prospective trial adds roughly eighteen to twenty-four months to your timeline compared to a retrospective cohort study using the same question. The data quality tradeoff is real but often worth it for certain endpoints. If your study involves vulnerable populations — pediatric patients, individuals with diminished capacity, incarcerated persons — you add additional layers of oversight and consent requirements that can double your preparation time. Budget for that. There's no shortcut that keeps these protections meaningful while rushing through. The most common reason hospital-based research studies fail is not bad science. It's underestimating the operational friction between what the protocol says should happen and what actually happens in a busy clinical environment. The researchers who finish on time treat the hospital infrastructure as a variable in their design, not background noise.




