What Glandular Fever Actually Is
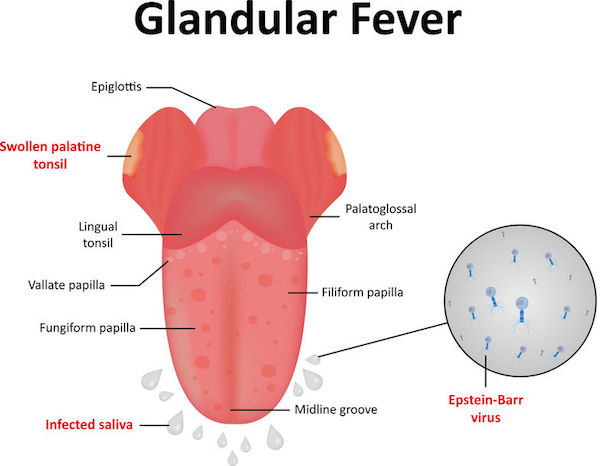
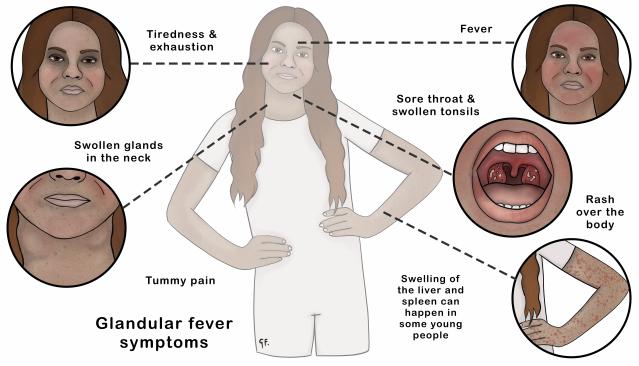
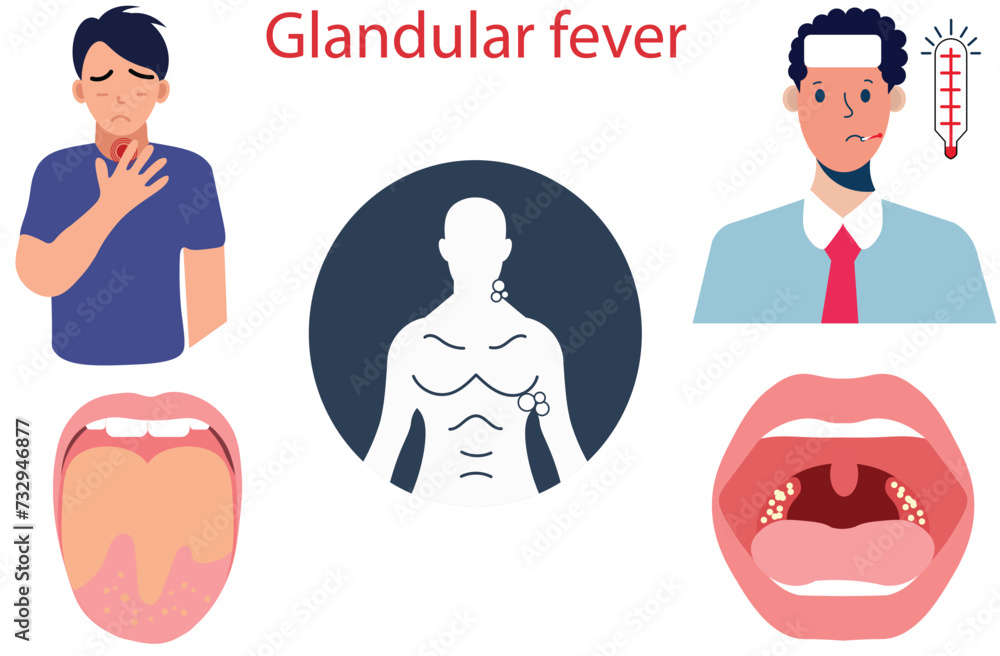
Glandular fever, medically known as infectious mononucleosis, is most commonly caused by the Epstein-Barr virus (EBV). It's a real thing that hits young adults particularly hard, and it's been around since it was first identified in the 1960s. The virus belongs to the herpes family, which means once you have it, it stays in your system for life. That's not meant to scare anyone, but it's a fact most people gloss over when they're googling their symptoms at 2am. What people don't always understand is that EBV is staggeringly common. By the time most of us reach adulthood, somewhere between 85 and 95 percent of us have been exposed to it. The reason it gets such a bad reputation is that when it does cause active illness in teenagers and young adults, it tends to be severe. Kids often pick it up with barely any symptoms. It's the awkward decade between about 15 and 25 where everything goes wrong.
How Do You Get Glandular Fever
The primary route of transmission is through saliva. This is why it's sometimes called the kissing disease, though that label undersells how broadly it spreads. Sharing drinks, using the same lip balm, sharing utensils, or even close contact in communal living situations like university dorms can all transmit the virus. The virus needs direct access to the mucous membranes or microscopic breaks in the skin around the mouth and throat. There are other routes too, though they're less common. Blood transfusions and organ transplants have historically been vectors, but screening has made this extremely rare in developed countries. More relevant to everyday life is the fact that the virus can persist in saliva for weeks after someone's symptoms have cleared. Someone might feel fine and still be shedding the virus. That's why outbreaks tend to cluster in settings where people live in close proximity and share food and drink casually. I spent a lot of time early on thinking the diagnosis was straightforward. It isn't. The classic triad is fever, pharyngitis, and lymphadenopathy, but not everyone presents with all three. I had a patient once who presented almost entirely with profound fatigue and mild spleen enlargement, no significant fever, no severe sore throat. We nearly missed it because the presentation was so atypical. The monospot test came back negative initially, which added to the confusion. We ended up confirming it with an EBV-specific antibody panel, which is the gold standard but something that doesn't get ordered as often as it should in primary care settings.
The incubation period and what happens next
After exposure, the incubation period runs roughly from four to six weeks. This long window is one of the reasons glandular fever spreads so silently through populations. By the time someone realizes they're unwell, they've likely been contagious for days or even weeks. The virus replicates in the oropharynx and then spreads to the B cells of the immune system, which is why you see such a dramatic immune response with the characteristic atypical lymphocytes that doctors look for on a blood smear. The illness typically lasts two to four weeks for the acute phase, but the fatigue component frequently lingers. I've seen patients describe exhaustion that persists for three or four months after the fever and swollen glands have resolved. This post-viral fatigue syndrome is real and well-documented, and it's one of the most frustrating aspects of managing glandular fever. There's no specific antiviral treatment for it, and corticosteroids only help in severe cases involving airway compromise or extreme splenomegaly.
Get the Full Details

Diagnosis and common pitfalls
The monospot test, also called the heterophile antibody test, is the quick screening tool most people encounter. It's fast, usually giving results within minutes, but it has limitations. Sensitivity in the first week of illness is only about 70 percent, meaning a negative result early on doesn't rule out glandular fever. If clinical suspicion remains high, you need to repeat the test in one to two weeks or go straight to the EBV antibody panel. The full panel looks at IgM and IgG antibodies against the viral capsid antigen (VCA) and the Epstein-Barr nuclear antigen (EBNA). These patterns tell you whether the infection is acute, recent, or past. A positive VCA IgM with negative VCA IgG and negative EBNA indicates acute infection. A positive VCA IgM and IgG with negative EBNA suggests recent infection, maybe three to six months back. Positive VCA IgM, IgG, and EBNA means past infection and recovery. This last pattern is actually the most common finding in adult populations, which is why serology alone can't distinguish between active disease and prior exposure without clinical correlation. One thing I wish more people understood is that glandular fever isn't the only condition that causes a positive monospot test. Cytomegalovirus (CMV) can produce a similar clinical picture and a false-positive heterophile test. Toxoplasmosis, acute HIV infection, and even some lymphomas can mimic the presentation. When someone comes in with prolonged fatigue and swollen lymph nodes, the differential is broad, and glandular fever is just one possibility among many.
What actually helps and what doesn't
There is no cure for glandular fever in the sense of a medication that kills the virus. The management is supportive, and that frustration is genuine. Rest, hydration, and symptomatic treatment with paracetamol or ibuprofen for fever and pain make up the bulk of what you can do. Some clinicians prescribe a short course of oral steroids for severe pharyngeal swelling that threatens the airway, but this is reserved for specific cases and isn't routine. Antibiotics have no role in treating the viral infection itself, and ampicillin or amoxicillin in particular should be avoided because they cause a non-allergic rash in roughly 80 to 100 percent of people with glandular fever. This is a well-known interaction that catches out both patients and practitioners. People sometimes get prescribed antibiotics for what looks like strep throat, develop the rash, and then get incorrectly labelled as penicillin-allergic for life. It's a cascading error that I've seen play out far too often. Return-to-activity guidance matters more than most people realize. The spleen can become enlarged in about 50 percent of cases, and ruptures, while uncommon, are a genuine risk. Contact sports and heavy lifting should be avoided for at least three to four weeks from symptom onset, and some guidelines recommend ultrasound confirmation of spleen size before clearing someone for strenuous activity. I've had patients push through too early and end up in emergency departments with splenic rupture. It's rare but it happens, and it's entirely preventable with clear communication about the restriction.
The longer-term picture
Most people recover fully from a single episode of glandular fever. The virus remains dormant in the body afterwards, and occasional reactivation can occur, usually without symptoms. There are associations between EBV and certain conditions later in life, including some lymphomas and nasopharyngeal carcinoma, but these are more relevant in specific geographic and immunological contexts. For the vast majority of otherwise healthy individuals, getting glandular fever is a miserable few weeks followed by gradual return to normal. The fatigue that follows is the part nobody warns you about. I remember a patient who was a graduate student, diagnosed in mid-semester, who pushed through despite being told to rest. She ended up with a relapse that kept her out of work for another two months. The medical literature supports what experienced clinicians observe: early mobilization in acute glandular fever is associated with prolonged recovery. The advice to rest isn't conservative medicine being cautious for no reason. The biology backs it up. If you're dealing with symptoms that match this description, getting a proper diagnostic workup is worth the effort rather than assuming it's just a prolonged bug. The conditions that mimic glandular fever range from manageable to serious, and the distinction matters.