The Physics Behind The Noise
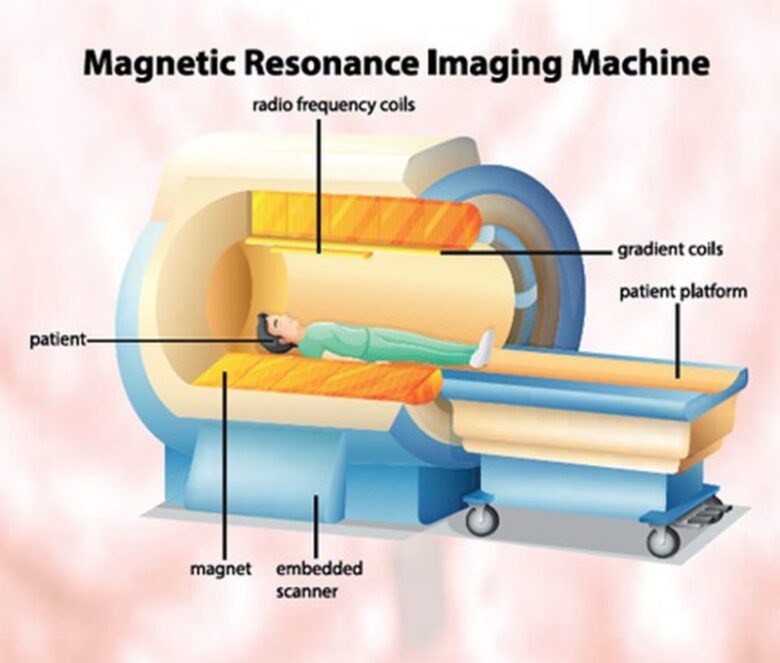
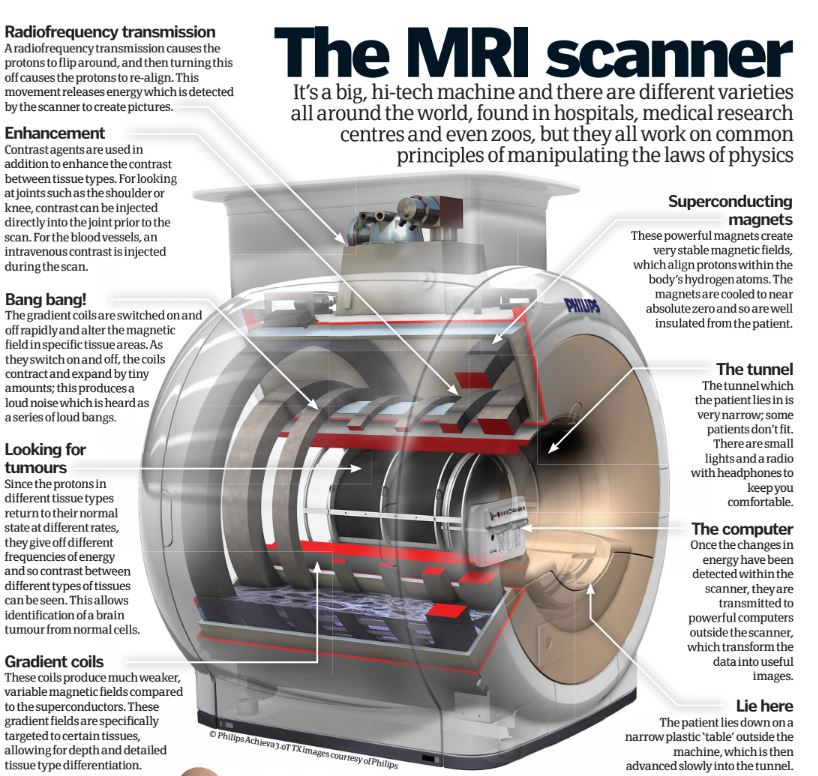
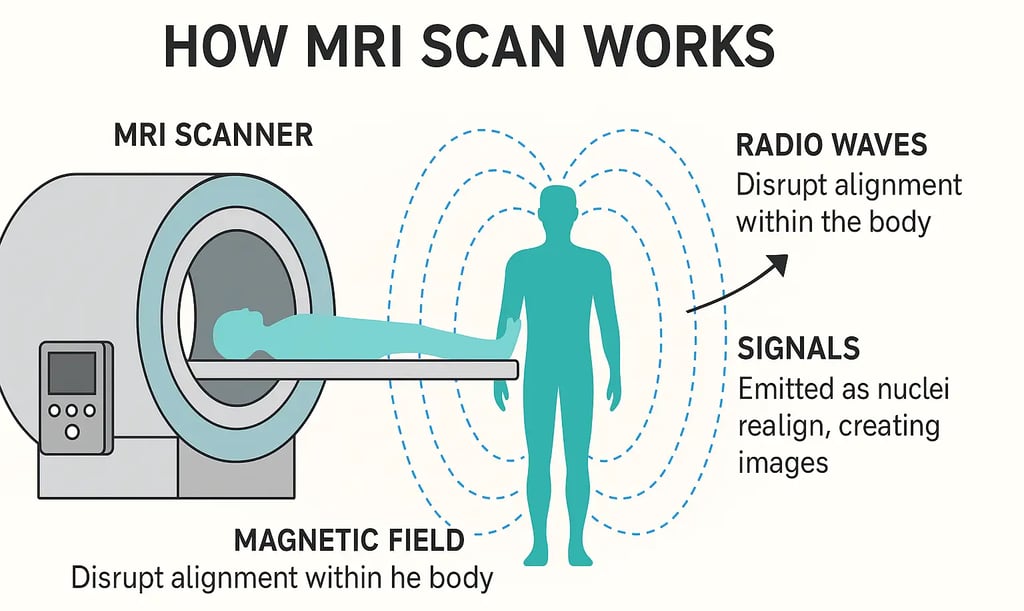
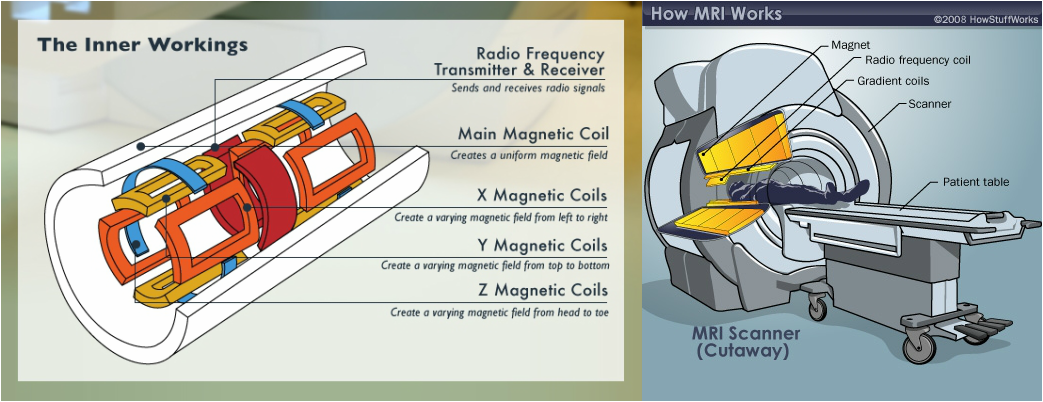
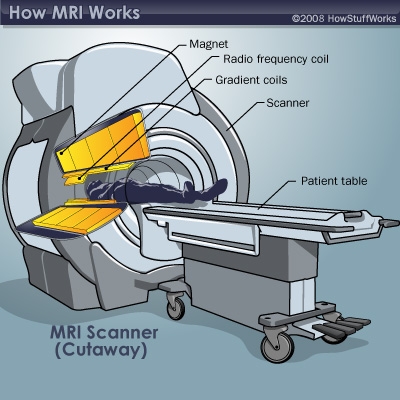
MRI stands for Magnetic Resonance Imaging. It uses a powerful magnet, radio waves, and computer processing to create detailed images of the inside of the body. No ionizing radiation involved. That alone makes it preferable to CT scans for many applications, though it is far from perfect. Here is the basic mechanism. Your body is mostly water, and water contains hydrogen atoms. Hydrogen nuclei act like tiny magnets with a property called spin. When you place a patient inside the MRI bore, a superconducting magnet—typically 1.5 to 3 Tesla for clinical systems, sometimes up to 7T for research—aligns those hydrogen protons. They line up either parallel or anti-parallel to the main magnetic field. The parallel state is slightly more populated, creating a net magnetization vector along the direction of the bore. Then a radiofrequency coil sends a pulse at the Larmor frequency. For a 1.5T system, that is roughly 63.86 MHz. The protons absorb this energy and flip their alignment. When the pulse stops, they relax back to their original state. Two relaxation processes happen simultaneously: T1 recovery, which is the longitudinal magnetization rebuilding along the main field, and T2 decay, which is the transverse magnetization fading as protons lose phase coherence with each other. Different tissues have different T1 and T2 values. That difference is what gives you contrast between gray matter, white matter, fluid, fat, and pathology.
How Does A Mri Work in Practice
The gradient coils are what actually let you form an image. Without them, you would just have a signal with no spatial information. The main magnet provides a uniform field. The gradient coils add small, controlled variations to that field so that the Larmor frequency becomes position-dependent. A slice selection gradient picks which anatomical slice you excite. A frequency encoding gradient determines where along one axis the signal comes from. A phase encoding gradient determines where along the perpendicular axis it comes from. You repeat the excitation and readout many times with different phase encoding steps. Each repetition fills one line of k-space, which is the raw Fourier-domain data. Once k-space is filled, a 2D or 3D inverse Fourier transform converts it into the image you see on the console. The whole sequence—TR, TE, flip angle, repetition count—is configurable, and changing those parameters changes the weighting: T1-weighted, T2-weighted, proton density-weighted, FLAIR, diffusion-weighted, and so on. I spent years troubleshooting MRI artifacts in a busy academic hospital, and the thing nobody warns you about is how sensitive these systems are to anything that disturbs the magnetic field homogeneity. Shims correct for imperfections, but they can only do so much. I had a case where a patient had a hip replacement with a cobalt-chromium alloy. The manufacturer claimed it was MRI-conditional at 1.5T. It was. The artifact from the implant still consumed most of the pelvis on standard sequences. What actually worked was switching to a MAVRIC SE (Multi-Acquisition Variable-Resonance Image Combination with Spectral Adiabatic Inversion Recovery) sequence. It takes longer—roughly 12 to 15 minutes instead of the usual 4—but it suppresses the metallic artifact significantly enough to see the joint space and surrounding soft tissue. Standard flow-compensated sequences were useless there. You learn pretty quickly that the textbook specs and real-world performance are not the same thing.
Another counter-intuitive point that beginners miss: higher field strength does not always mean better images. A 3T scanner gives you roughly double the signal-to-noise ratio of a 1.5T system, which is true. But it also doubles the susceptibility artifacts, shortens T2* relaxation times, increases specific absorption rate from RF deposition, and makes B0 inhomogeneity more noticeable. For brain imaging at 3T, you get finer detail. For patients with spinal hardware, orbit implants, or certain cardiac devices, 1.5T is often the better choice despite the lower SNR. The trade-off is not linear, and it depends entirely on what you are trying to visualize. Pulse sequence design is where the real engineering happens. Spin echo sequences use a 90-degree excitation pulse followed by a 180-degree refocusing pulse, which corrects for some B0 inhomogeneity. Gradient echo sequences skip the 180-degree pulse, which makes them faster but more susceptible to field inhomogeneities. That is why GRE is sensitive to blood products and calcification—it is useful for certain diagnoses but annoying for others. Fast spin echo, also called turbo spin echo, fires multiple 180-degree pulses after each excitation to fill multiple k-space lines per TR. This cuts scan time dramatically but can introduce blurring if the echo train is too long. Echo planar imaging, used for diffusion and functional MRI, acquires an entire image in 50 to 100 milliseconds. It is incredibly fast and incredibly prone to distortion near air-tissue interfaces like the sinuses and the base of the skull. Coils matter as much as the magnet. Modern scanners use phased array coils with multiple element pairs, each optimized for a specific anatomical region. A knee coil might have eight channels. A head coil might have 32. More channels mean parallel imaging can be applied, which undersamples k-space and reconstructs the full image using the known sensitivity profiles of each coil element. GRAPPA and SENSE are the two most common acceleration techniques. A typical parallel imaging factor of 2 cuts scan time roughly in half. A factor of 3 is possible but introduces more noise amplification, measured as a g-factor, which becomes problematic in the periphery of the field of view.
Get the Full Details
The cryogen system is another part people rarely think about. The superconducting magnet needs to stay at roughly 4 Kelvin, which means liquid helium. A 3T scanner holds somewhere around 1500 to 2000 liters of liquid helium. If the system quenches—which is when the superconducting state collapses and the helium boils off violently—the magnet is ruined and the facility is sealed until the gas clears. Quenches are rare but expensive. Most modern systems have cold heads and helium recycling to minimize boil-off, and some newer designs are dry-insert magnets that use far less helium. They still require liquid helium for initial cooldown, but the operational loss is dramatically lower. Safety is the elephant in the room. The static magnetic field is always on, even when the scanner is not acquiring data. That means any ferromagnetic object in the room becomes a projectile. I once saw a therapy chair—actually a standard hospital exam chair with a steel frame—get yanked across the suite and dent the wall when someone forgot it had been left near the boundary. The Fifth Tier safety zone isn't just bureaucratic paperwork. It is a physical reality. Pacemakers, cochlear implants, aneurysm clips, orthopedic hardware—all of it needs to be verified as MRI-conditional before a patient goes in. The manufacturer documentation matters. The date of implant matters. The specific model matters. There is no general rule you can apply by guessing. Contrast agents exist too. Gadolinium-based agents shorten T1 relaxation time, making vessels and inflamed tissue appear bright on T1-weighted images. Macrocylic agents are more stable than linear agents, which matters because free gadolinium is nephrotoxic and can deposit in the brain with repeated exposure, particularly in patients with severe renal impairment. Nephrogenic systemic fibrosis is rare but real. Screening for kidney function before administering contrast is standard practice, and it is not negotiable.
The image quality depends on patient cooperation as much as hardware. Motion ruins everything. A 30-second sequence becomes unreadable if the patient breathes, swallows, or fidgets. Respiratory gating and navigator echoes help for abdominal imaging, but they add time. Sedation is common for pediatric scans. I have seen scan times double when a restless adult requires coaching and breaks between repetitions. Compression wraps and padding reduce motion but introduce their own artifacts if they shift during the scan. Post-processing has become almost as important as acquisition. Quantitative MRI methods measure actual T1, T2, and diffusion coefficients instead of relying on relative contrast. Diffusion tensor imaging maps white matter tracts by measuring the directionality of water diffusion. Perfusion imaging tracks contrast bolus passage to estimate blood flow. These techniques add minutes to a scan but provide data that conventional sequences cannot. The trade-off is increased complexity and longer reconstruction times on the console. MRI will never replace ultrasound for point-of-care work or CT for trauma because of speed and cost. An emergency CT of the head takes three minutes. A comparable MRI protocol takes twenty to thirty minutes minimum, and motion artifacts make it unreliable in an agitated or unconscious patient. Ultrasound costs a fraction of the capital expense and has no safety restrictions around metal implants. MRI is the right tool when you need soft tissue contrast that nothing else can provide—brain tumors, ligament tears, disc herniations, multiple sclerosis plaques, musculoskeletal cartilage, pediatric neurology. It is overkill for a broken bone or a routine chest evaluation.
The technology keeps improving. Compressed sensing reduces the amount of k-space data needed by exploiting the sparsity of medical images. AI-based reconstruction algorithms are now being deployed on some systems to clean up undersampled data and reduce scan times further. Direct polarized xenon imaging and hyperpolarized carbon-13 metabolic imaging are experimental but show promise for functional assessment beyond anatomy. The fundamental physics has not changed since the first human scan in 1977, but the engineering around it has matured considerably.