How to Actually Document Impaired Gas Exchange Without Making It Meaningless
Most nursing students learn the definition but never grasp how to translate a set of clinical signs into a coherent, defensible nursing diagnosis. You will find plenty of textbook definitions online. They tell you impaired gas exchange is an imbalance between oxygenation and carbon dioxide elimination at the alveolar-capillary level. That tells you nothing about what to actually write on a patient's chart when their SpO2 is hovering around 89 percent and they are working to breathe. The real problem isn't knowing the definition. It's linking objective data to the diagnostic label in a way that survives review and actually guides intervention. I have seen nurses write "impaired gas exchange related to alveolar membrane changes" and then list nothing but a pulse ox reading as evidence. That documentation gets flagged immediately. Pulse ox alone does not substantiate a gas exchange diagnosis because it measures hemoglobin saturation, not alveolar diffusion or ventilation-perfusion mismatch. You need more than that.
Impaired Gas Exchange Nursing Diagnosis
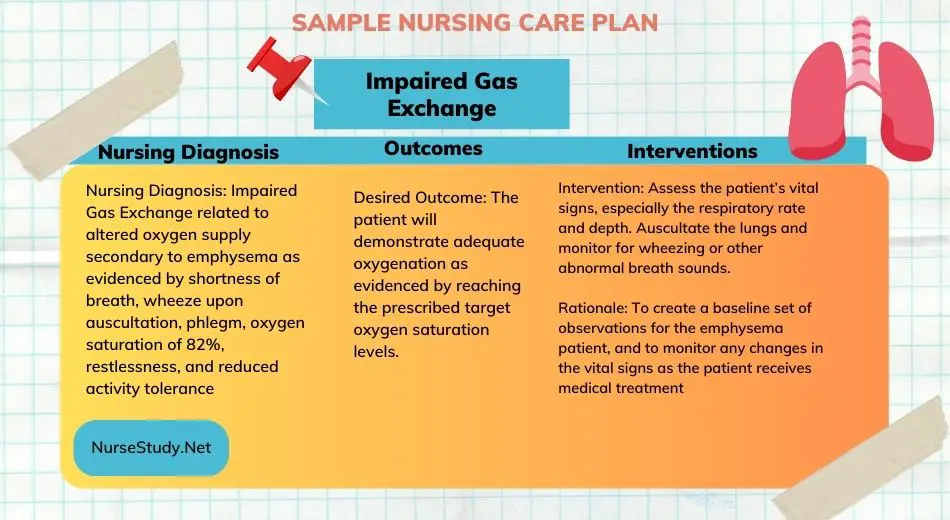
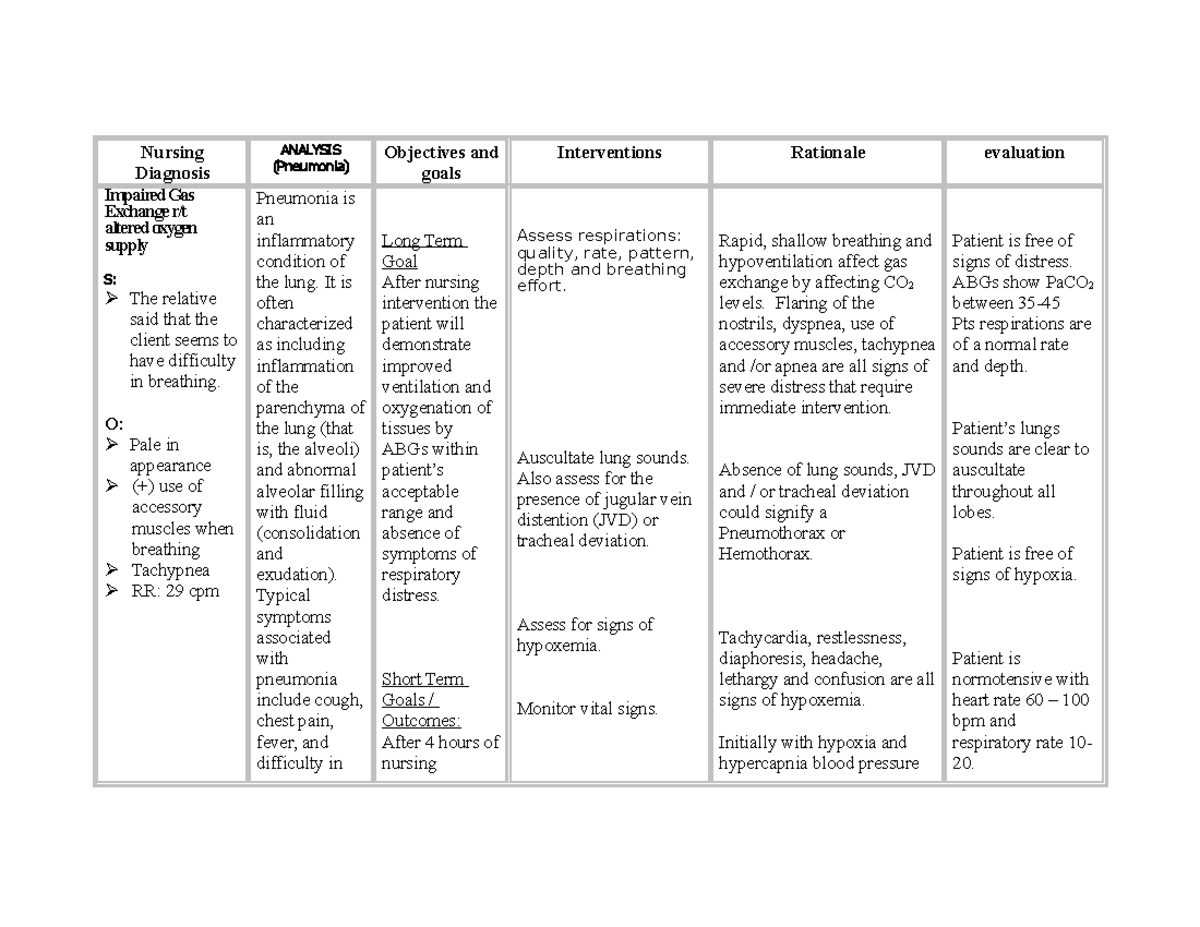
Here is how the diagnosis actually breaks down in practice. The defining characteristics fall into two buckets. First, you need evidence of abnormal gas values. ABG results showing PaO2 below 80 mmHg, PaCO2 above 45 mmHg, or decreased SaO2 are the gold standard. If your hospital does not pull routine ABGs on stable patients, arterial blood gases might be the only time you get hard numbers. That is fine. SpO2 trends, respiratory rate, work of breathing, and skin color all count as supporting evidence, but they are secondary. Lead with the ABG if you have it. Second, you need clinical signs that the body is struggling to compensate. Tachypnea, use of accessory muscles, nasal flaring, cyanosis, restlessness or altered mental status from hypoxia, and elevated respiratory rate above 20 or below 12 in adults. These signs do not prove impaired gas exchange on their own. A patient with anxiety can be tachypneic without any gas exchange problem. A patient with metabolic acidosis from DKA can have Kussmaul respirations that look like respiratory distress but are actually a compensatory mechanism for a metabolic issue. Context matters more than any single sign. The related factors are where most people stumble. Do not write "related to pneumonia" as your etiology. Pneumonia is a medical diagnosis, not a nursing etiology. What you are really documenting is the physiological mechanism your nursing interventions can address. Related to altered alveolar-capillary membrane caused by inflammatory exudate in the alveoli. Related to ventilation-perfusion imbalance. Related to retained secretions impairing alveolar ventilation. These are actionable. They tell another nurse or an audit reviewer exactly what you think is going wrong and what you plan to do about it.
Let me share a specific situation I ran into a few years back. I was caring for a post-operative patient who had a normal ABG on room air but had persistent tachycardia in the 110s, mild anxiety, and a respiratory rate of 18. Their oxygen saturation was 94 percent. A template-based approach would have pushed for a respiratory diagnosis because the vitals looked slightly off. But the ABG was normal. Instead of forcing a gas exchange diagnosis, I documented impaired gas exchange related to post-anesthetic residual effects on respiratory drive and early atelectasis, with the related factor being decreased lung expansion from pain-limited deep breathing. The evidence I cited was not the ABG. It was the shallow breathing pattern, the patient's inability to take a full breath despite coaching, the diminished breath sounds at the left base, and the mild tachycardia that did not resolve with pain medication alone. Within two hours of hourly incentive spirometry and assisted ambulation, their heart rate dropped to 82 and breath sounds improved. The diagnosis was correct, but the evidence was subtle. If I had relied on the ABG alone, I would have missed it entirely. This is the nuance that rarely gets taught. Impaired gas exchange can exist with normal oxygen saturation. A patient can have a significant V/Q mismatch early in their course, and the pulse oximeter will still read 95 percent because hemoglobin is saturated, even though the alveoli are not exchanging gas efficiently. The compensation happens until it does not. Your job is to catch the mismatch before the numbers crash. Look at the trend, not the snapshot. Look at work of breathing, not just the oxygen number. Another thing beginners consistently get wrong is the severity specification. NANDA-I recognizes this diagnosis as specified, unspecified, and risk for. You do not need a separate risk diagnosis if the patient already has the clinical signs. But you also should not declare impaired gas exchange in a patient who is genuinely stable with no supporting data just because they have a condition that could lead to it. That is lazy documentation and it dilutes the usefulness of your care plan. If there are no defining characteristics present yet, write risk for impaired gas exchange and link it to the specific risk factor. Risk for impaired gas exchange related to prolonged immobilization and decreased lung expansion following hip replacement surgery. That is accurate and it triggers the right preventive interventions.
Get the Full Details

When writing the actual care plan, keep the goal statements measurable. Oxygen saturation maintained above 92 percent is fine for most patients. For a COPD patient, 88 to 92 percent is the actual target range and pushing for above 92 percent could suppress their hypoxic drive. I learned that the hard way with a patient who had severe COPD and chronic CO2 retention. We had a standing order to keep SpO2 above 92. After starting supplemental oxygen at two liters, their saturation climbed to 95 and within three hours they became somnolent with a PaCO2 that spiked from their baseline of 55 to 78. The oxygen had done more harm than good. The lesson is simple. Goal settings must match the underlying pathology, not some universal standard. Interventions should flow directly from your related factor. If the problem is retained secretions, the interventions are positioning, humidification, suctioning, and hydration. If the problem is alveolar collapse from poor expansion, the interventions are incentive spirometry, early mobilization, and pain management that actually allows deep breathing. If the problem is ventilation-perfusion mismatch from pulmonary edema, the interventions include diuresis monitoring, fluid balance tracking, and oxygen delivery optimization. Write the interventions in language that shows the connection. Do not just list them as checkboxes. Documentation review is another area where people lose points. Auditors want to see coherence between the diagnosis, the related factor, the evidence, and the interventions. If your related factor says retained secretions but your interventions are all about positioning and oxygen therapy with no mention of airway clearance techniques, the audit trail breaks. Match every intervention to the etiology you stated. This takes an extra ten minutes but it prevents your entire care plan from getting returned for revision.
There is a limitation worth noting honestly. This diagnosis relies heavily on ABG data, and many hospitals have moved away from routine arterial blood gas draws due to cost and patient discomfort. Capillary blood gases and transcutaneous monitoring exist but they are less accurate and not universally available. When you lack ABG confirmation, your diagnosis becomes weaker and more dependent on clinical observation, which is inherently subjective. In those cases, consider whether the evidence supports a different primary diagnosis like ineffective airway clearance or hypercapnia that might be more straightforward to document without arterial blood gas backing. Not every breathing problem is impaired gas exchange, and mislabeling it will only create confusion down the line. If you want a quick reference while you write these up, the NANDA-I handbook lists the defining characteristics and related factors I described above. The most recent edition added more specificity around the V/Q mismatch criterion, which is useful because that is the most common pathophysiological mechanism in adult hospital populations. The handbook itself does not give you documentation templates, which is frustrating. Most of my unit uses a modified version of the NANDA taxonomy mapped to our EHR's standardized nursing language module, and the fields there push you toward the right structure automatically. If your hospital does not have that, a simple three-column format works. Column one for the diagnosis and related factor, column two for the defining characteristics with dates and values, column three for the interventions with planned outcomes. The bottom line is that impaired gas exchange is not a difficult diagnosis conceptually. The difficulty is in applying it correctly when the data is incomplete or contradictory. Trust the ABG when you have it. Trust the trend when the numbers look normal. Trust your clinical observation when the equipment gives you a clean reading but the patient clearly is not exchanging gas well. That gap between the monitor and the patient is where nursing judgment actually lives.