The Actual Mechanism
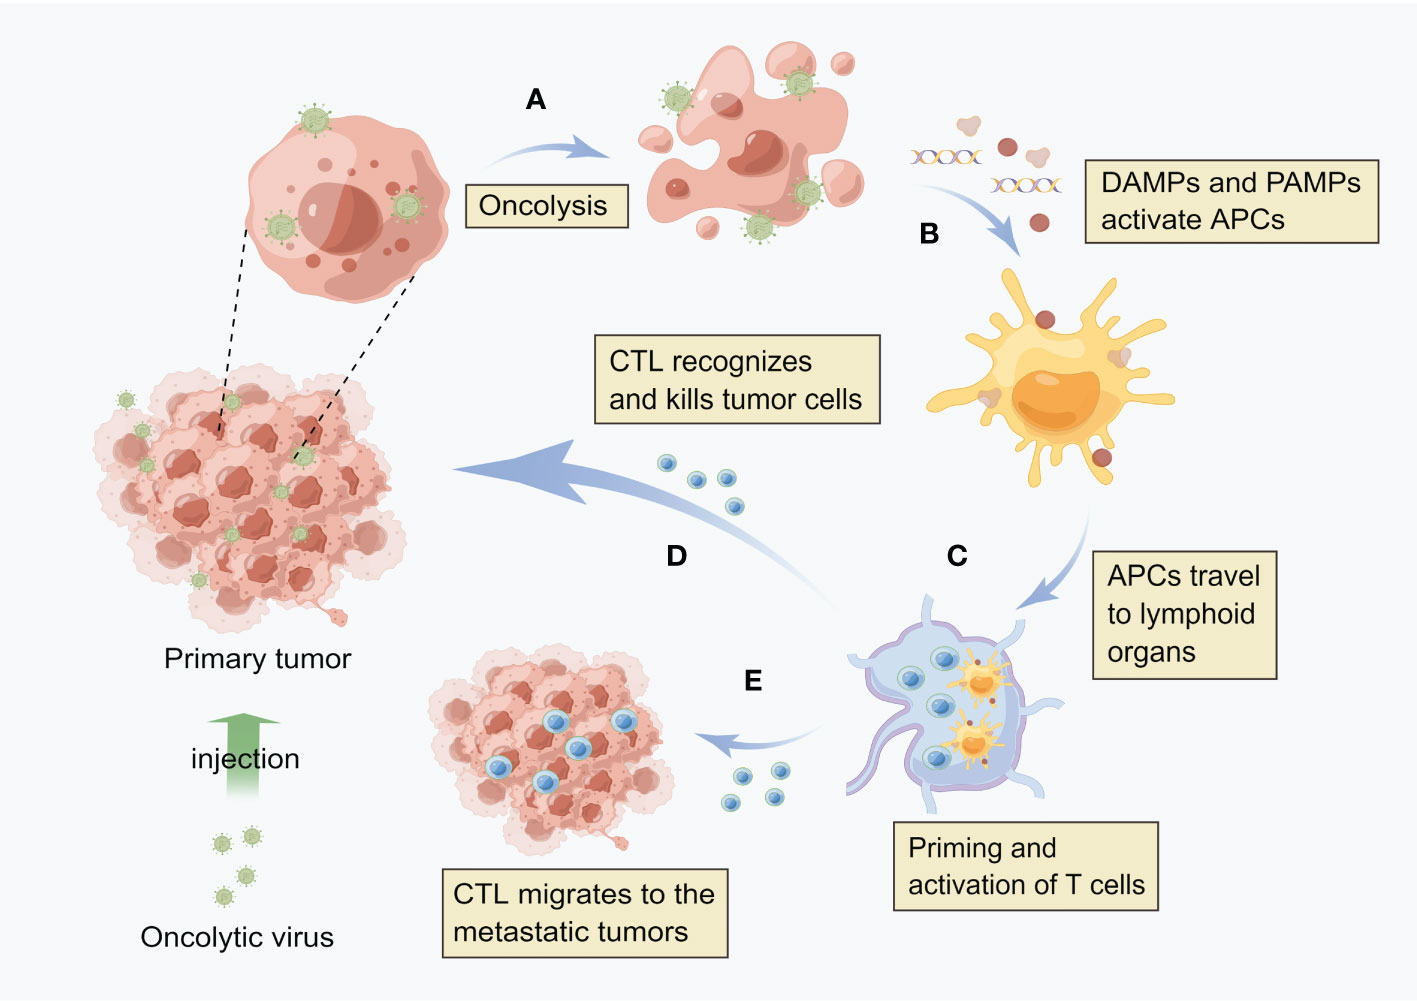
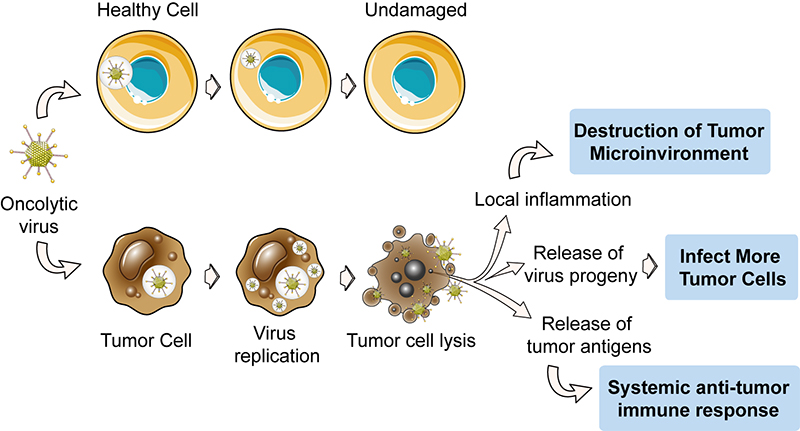
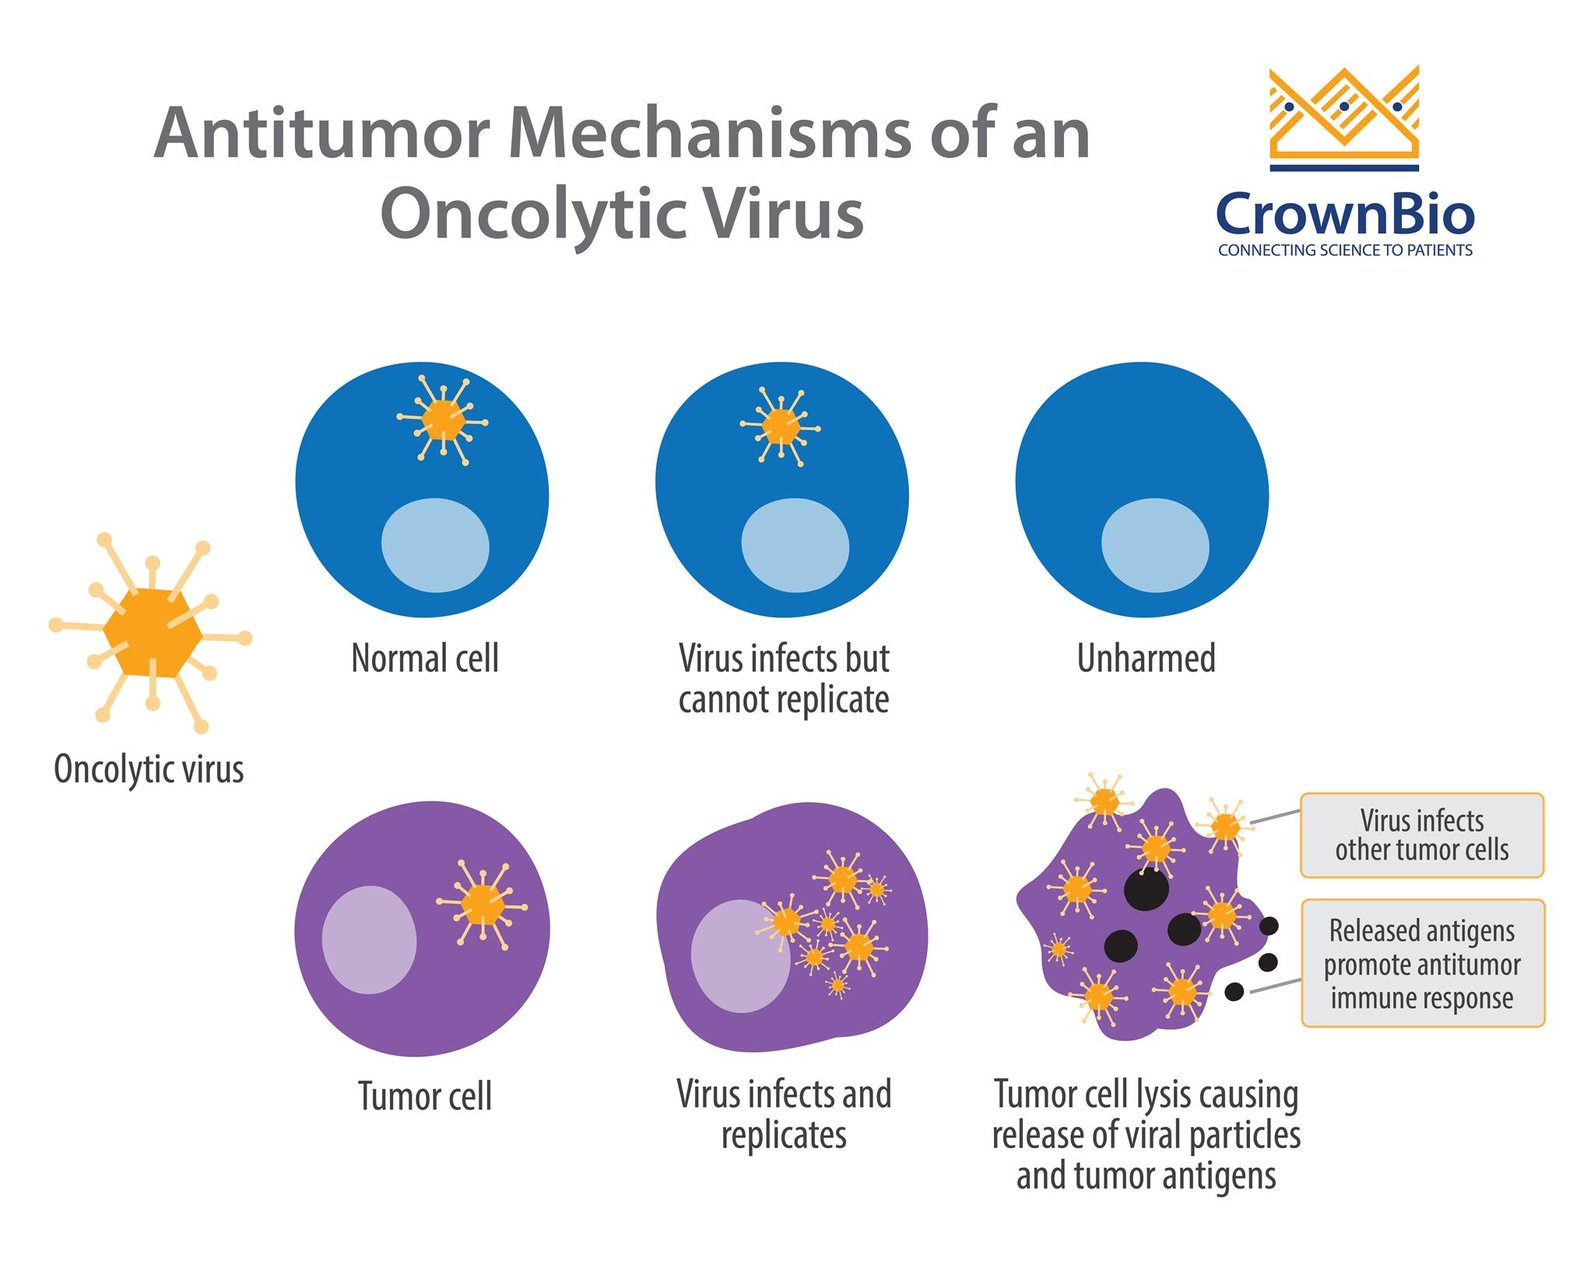
It starts with a virus — not a manufactured drug molecule, but a living organism that replicates inside cancer cells. Most oncolytic viruses are engineered from common pathogens like herpes simplex, vaccinia, or reovirus. The virus is modified so it can replicate efficiently in cancer cells but not in healthy ones. This selectivity usually comes from mutations that make the virus dependent on pathways that are hyperactive in cancer cells, such as the RAS or interferon signaling pathways. When the virus enters a cancer cell, it hijacks the cell's replication machinery, produces thousands of new viral particles, and then lyses the cell. The newly released virions go on to infect neighboring tumor cells. That's the direct oncolysis part. But the indirect effects are arguably more important. When the tumor cell bursts, it releases tumor-associated antigens, danger signals like DAMPs, and viral components that alert the immune system. This turns the tumor into an in-situ vaccine. Dendritic cells pick up those antigens, travel to lymph nodes, and prime T cells that can then recognize and attack remaining cancer cells throughout the body. That's the abscopal effect — the idea that treating one lesion can lead to regression in untreated metastases. It doesn't always happen, but when it does, it's dramatic.
How Does Oncolytic Virus Therapy Work in Clinical Practice
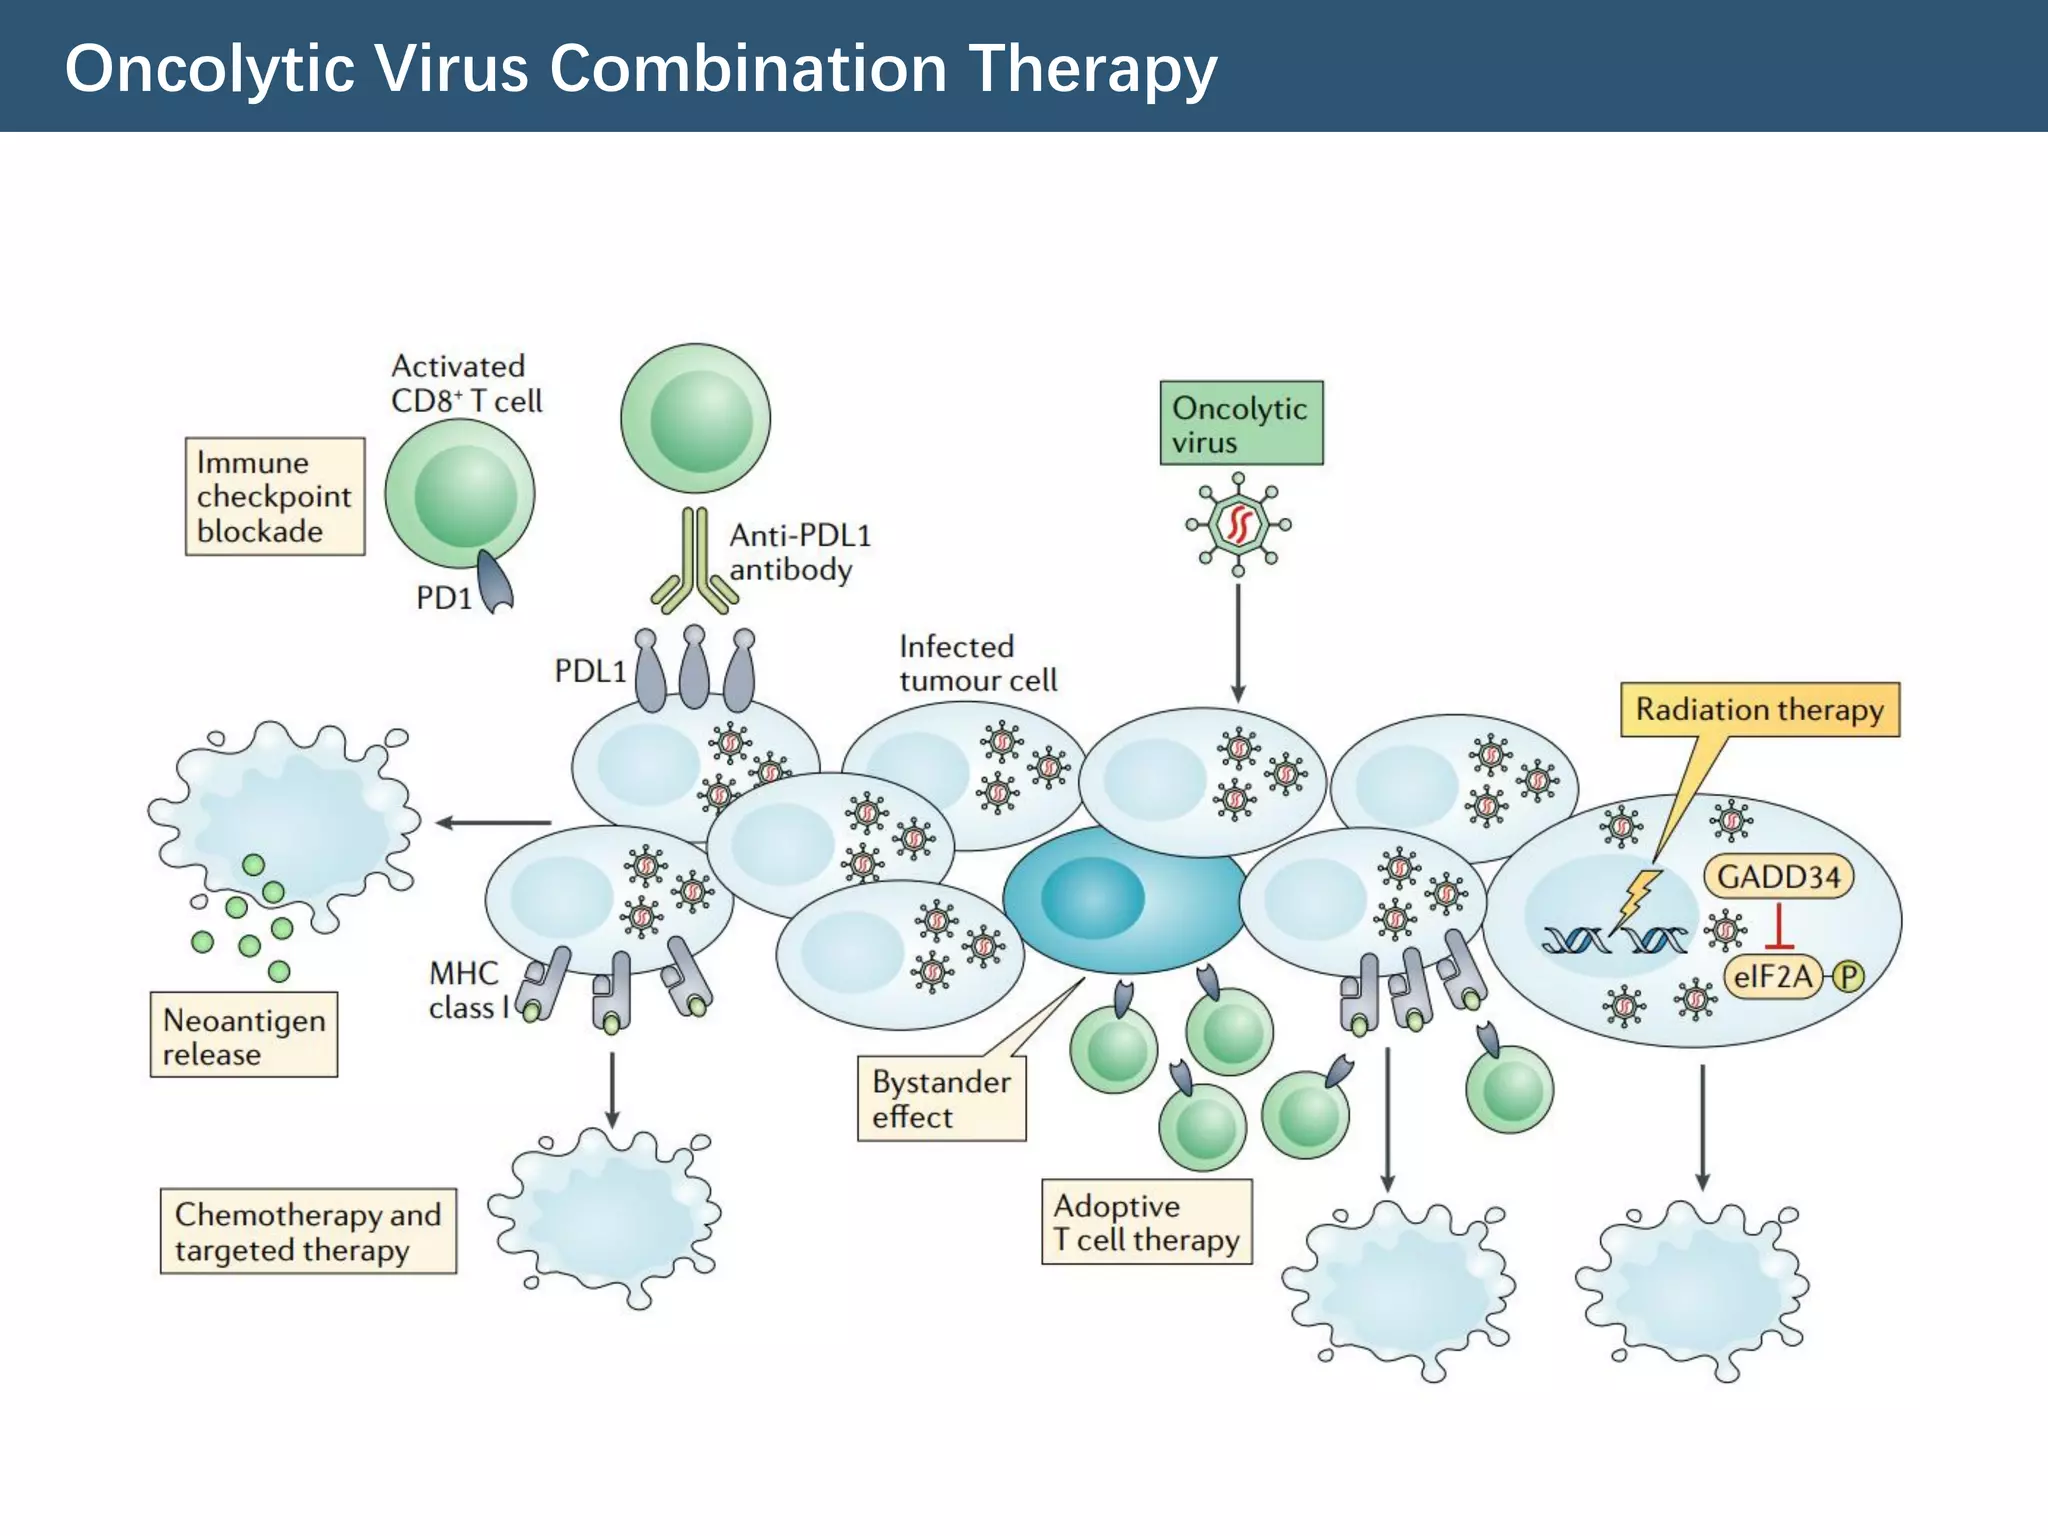
I've spent the better part of a decade watching this space, and the gap between the elegant mechanism and what happens in a real clinic is substantial. The approved agents are limited. Talimogene laherparepvec, known as T-VEC, is the only FDA-approved oncolytic virus so far, approved in 2015 for advanced melanoma. It's a modified HSV-1 that carries a GM-CSF transgene, meaning it's designed to both lyse tumor cells and recruit dendritic cells locally. You inject it directly into accessible lesions, usually the skin or subcutaneous nodules, at doses around 10^6 to 10^8 PFU per injection. Patients typically get up to six intratumoral injections over several months, depending on response. The administration itself is straightforward but finicky. The virus has to be kept on ice from thaw to injection. It degrades quickly at room temperature. Once injected, you have to make sure the lesion is actually accessible — deep visceral metastases are off the table for direct injection. Most trials that show the best results involve subcutaneous or cutaneous disease because you can actually reach it. I saw a phase II trial where they tried systemic delivery with a vaccinia-based vector and got almost no tumor penetration because the patient's pre-existing neutralizing antibodies cleared the virus from the bloodstream within minutes. That's a recurring problem. Most humans have been exposed to the parental viruses used in oncolytic therapy, which means they already carry IgG antibodies that neutralize the therapeutic vector before it ever reaches the tumor. You can't easily predict who has these antibodies, and there's no reliable way to overcome it without immunosuppression, which introduces its own risks. Here's something that isn't talked about enough: the tumor microenvironment itself is hostile to viral spread. Solid tumors have high interstitial pressure, a dense extracellular matrix, and poor vasculature. Even if the virus successfully infects the cells near the injection site, the newly produced virions struggle to move through the tumor mass. Studies using imaging have shown that viral distribution within a tumor is typically patchy — you get a shell of infection around the needle track and then dead zones further out. That's why combination strategies are so much more promising. Pairing oncolytic viruses with checkpoint inhibitors like anti-PD-1 or anti-CTLA-4 antibodies has shown consistent synergy in trials. The virus opens the door by causing immunogenic cell death and making the tumor more visible to the immune system, and the checkpoint inhibitor removes the brakes on the T cells that the virus helped activate. The IPONICS trial and several others have demonstrated this, though the response rates are still in the 20 to 40 percent range depending on the cancer type and combination used.
Another practical issue is dosing. There isn't a standardized dose-response curve for most oncolytic viruses. Unlike chemotherapy, where you can calculate a dose based on body surface area and know roughly where the therapeutic window sits, viral dosing depends on variables — the vector, the route of administration, the tumor type, the patient's immune status, pre-existing immunity. Some protocols use escalating doses starting at 10^6 PFU and going up to 10^10 PFU per cycle. The side effects at lower doses are usually mild — fever, flu-like symptoms, fatigue — but at higher doses you can get serious toxicity, including encephalitis with certain HSV-based vectors if the virus spreads beyond the tumor. I reviewed a case where a patient developed herpetic encephalitis after high-dose intravenous administration of a modified HSV-1, and the trial had to be paused for safety reviews. It's rare, but it's real, and it's why most successful programs stick to intratumoral delivery whenever possible. The other major limitation is that oncolytic virus therapy doesn't work for every cancer. The literature is dominated by melanoma and bladder cancer data because those are the cancers where the biology is most favorable — high mutational burden, existing immune infiltration, and accessible lesions. When you try it in pancreatic cancer or glioblastoma, the results are significantly worse, and I don't think that's just because those tumors are harder to inject. The microenvironment in pancreatic cancer is extremely dense with fibrotic stroma, and glioblastoma has the blood-brain barrier to contend with. Both create physical barriers to viral spread that most current vectors simply can't overcome. There are engineered second-generation vectors being developed to address this — things like RGD peptide modifications to improve tumor targeting, or armor genes to resist interferon responses — but none of them are clinically validated yet. If you're looking at this from a treatment perspective, the honest answer is that oncolytic virus therapy is still largely experimental outside of T-VEC for melanoma. The pipeline is active — there are over 50 clinical trials running worldwide — but most of them are in early phases. The economics are also unfavorable. Manufacturing oncolytic viruses under GMP conditions is expensive and low-yield compared to synthesizing a small-molecule drug. Each batch is essentially custom-made, which drives costs well above what insurance protocols are comfortable covering. I've seen centers turn patients away not because the therapy wasn't appropriate but because the logistics of cold-chain storage, specialist injection training, and monitoring for adverse events made it impractical in a community oncology setting.
Get the Full Details