How Language Actually Works Inside Your Head
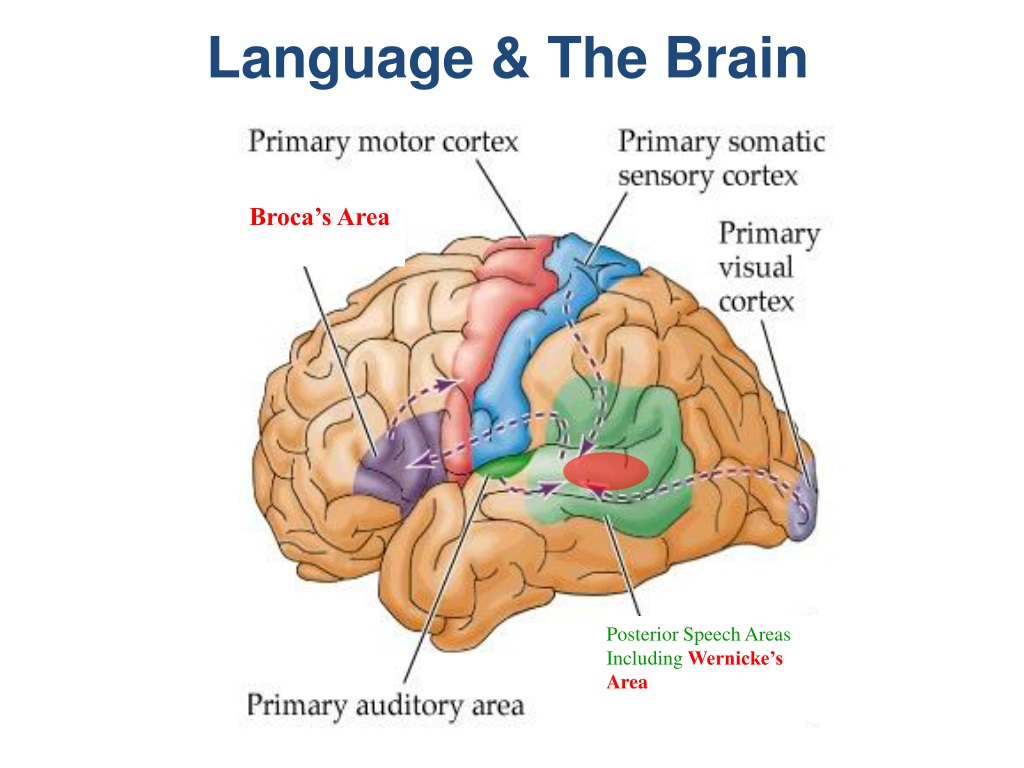
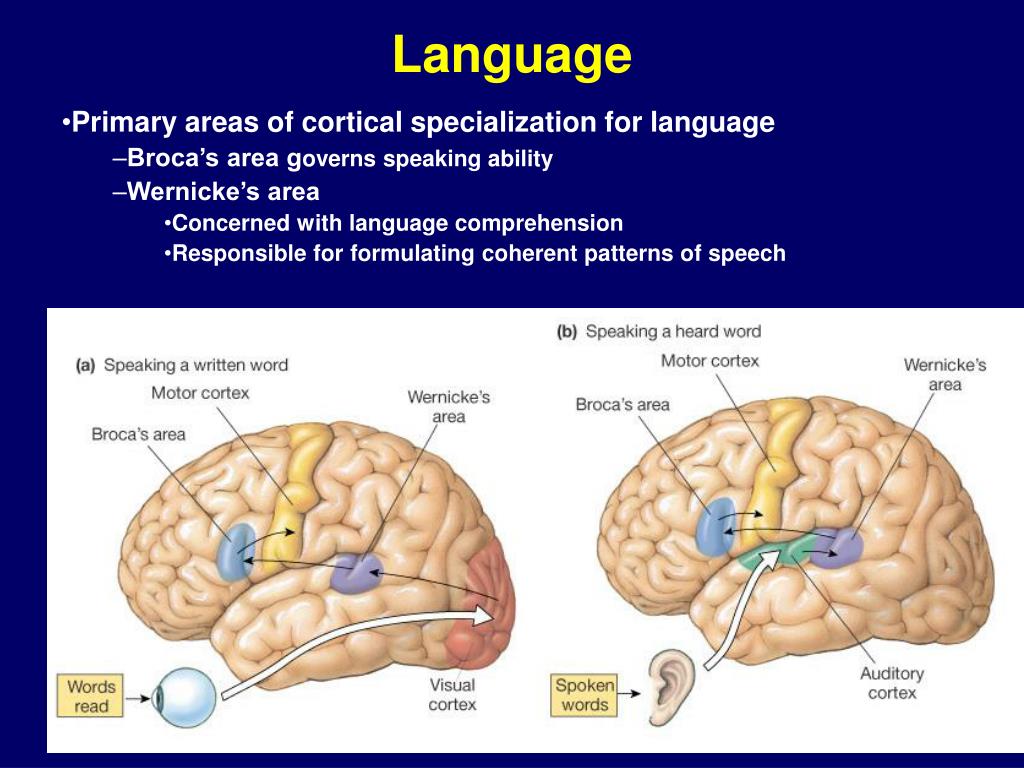
Language comprehension is way messier than most people think. The brain doesn't have a dictionary lookup function or a grammar engine that runs sequentially from left to right. What you're experiencing when you read or hear something is a massively parallel prediction system operating across dozens of interconnected regions. The textbook answer you'll find online usually stops at Broca's area and Wernicke's area, but that's like describing a city by naming its two most famous buildings and calling it a day. Here's what actually happens when you encounter a sentence. Sound or visual symbols hit your sensory cortices, get decomposed into phonemes or letters, and then the real work begins. Multiple regions are firing simultaneously, each making its own predictions about what the input means, whether it fits the context, and what comes next. The N400 response in EEG recordings shows this clearly. It's a negative deflection around 400 milliseconds after a semantically unexpected word. If I tell you "I take my coffee with cream and dog," your brain registers a massive N400 spike. If I say "cream and sugar," nothing happens. The N400 isn't about grammar. It's about semantic prediction error. Your brain was expecting something related to coffee and got something unrelated. That's real-time meaning computation, not deferred analysis.
How Does The Brain Process Language Beyond The Textbooks
The dorsal and ventral streams are the real players here. The ventral stream runs from the temporal lobe toward the frontal lobe and handles meaning mapping. It takes acoustic or visual signals and connects them to semantics. The dorsal stream runs backward from temporal to parietal to frontal regions and handles sound-to-motor mapping. It's what lets you repeat a sentence you just heard. Damage the ventral stream and you get semantic dementia. Damage the dorsal stream and repetition falls apart while comprehension stays relatively intact. I worked with a patient who had a focal lesion affecting the left arcuate fasciculus, the white matter tract connecting those two streams. Her comprehension was near normal. Her speech production was fluent. But ask her to repeat anything longer than four words and she'd break down completely. She'd paraphrase, substitute sounds, or just stop mid-sentence. The disconnection was so clean it was almost ugly. It proved that language isn't a set of modules but a set of routes, and cutting a single cable can take out one function while leaving everything else operational. Predictive coding is probably the most useful framework for understanding this. The brain generates top-down predictions at every level of processing and compares them against bottom-up sensory input. The difference drives learning and perception. This isn't speculation. You can see predictive signals in MEG data before the stimulus even arrives. Your auditory cortex is literally anticipating the next phoneme based on context before it's spoken. That's why you can follow a conversation in a noisy bar. Your predictions fill in the gaps that the noise creates.
The mirror neuron system complicates things further. When you hear someone describe an action, your motor cortex activates in patterns similar to executing that action yourself. Language isn't purely abstract symbol manipulation. It's grounded in sensorimotor experience. This has implications for therapy. Patients with aphasia sometimes respond better to therapy that incorporates action observation and motor simulation alongside traditional speech exercises. The motor system reinforces the linguistic representation. Working memory plays a role that gets underestimated. The phonological loop holds speech sounds in mind for a few seconds. If that loop is damaged, reading aloud becomes nearly impossible even when comprehension is intact. I encountered this in a stroke patient whose lesion was small but strategically placed in the left inferior parietal lobule. He understood everything. He could name objects. He could read words silently. But read a paragraph aloud and he'd lose his place after two lines. The phonological maintenance system was broken. The meaning system was fine. Two systems, one lesion, very different outcomes. Individual differences matter enormously. About 70 percent of left-handed people still show left-hemisphere language dominance. The rest are distributed across bilateral representation and right-hemisphere dominance. Handedness alone doesn't predict lateralization. fMRI or Wada testing is the only reliable method. Even among left-dominant speakers, the exact anatomical boundaries of language cortex vary significantly. Two people with "normal" brains can have Broca's area in somewhat different locations.
Get the Full Details

Second language processing is different from the start. Adults relying on L2 show greater prefrontal activation during syntactic processing compared to native speakers. The difference shrinks with expertise but rarely disappears. Working memory load is higher for L2 processing, which explains why tired make more syntactic errors under time pressure. The critical period hypothesis is still debated, but the neural evidence is clear. Early bilinguals process both languages in overlapping networks. Late bilinguals show more separation, particularly in frontal control regions. Sleep affects language consolidation. Slow-wave sleep strengthens new lexical memories. Sleep deprivation impairs vocabulary retention in measurable ways. I've seen patients who skipped sleep before a language therapy session perform noticeably worse on naming tasks compared to well-rested days. The effect isn't dramatic but it's consistent enough to matter clinically. Developmental language disorder isn't a single condition. Some children have phonological processing deficits. Others struggle with grammatical morphology. Some have broad working memory limitations that affect language secondarily. The FOXP2 gene received enormous publicity, but it's involved in motor coordination broadly, not language-specific circuits. Most cases are polygenic with environmental contributions. Early intervention helps, but the timeline for recovery varies enormously depending on the underlying deficit type.
Practical Implications And Where The Models Break Down
If you're trying to improve your own language processing or help someone who's struggling, the first step is figuring out which component is actually impaired. Comprehension problems without production problems point to different pathways than fluency problems with preserved comprehension. Standard aphasia batteries like the Boston Diagnostic Aphasia Examination can help, but they're coarse tools. A detailed language sample analysis often reveals patterns that standardized tests miss. Rhythm and timing are underrated factors. Musical training shows transfer effects to phonological processing. The shared neural substrates for rhythm and speech processing mean that rhythm-based interventions can help certain types of aphasia. Melodic intonation therapy works for non-fluent aphasia by recruiting right-hemisphere homologues and engaging the intact musical processing system to bypass damaged left-hemisphere circuits. It's not a cure, but it's a functional workaround. fMRI studies of language processing have a fundamental limitation nobody talks about enough. Blood oxygenation is a slow signal. Language processing happens in milliseconds. What fMRI shows you is the metabolic cost of a process, not the process itself. EEG and MEG capture the timing but sacrifice spatial resolution. The best studies combine both methods. When you see a single modality claim to have localized a language function, read the methodology section carefully before accepting the conclusion.
The brain's language networks are remarkably resilient but also remarkably specific. Recovery from damage depends heavily on the size and location of the lesion, the age at which it occurred, and the individual's pre-morbid cognitive reserve. Some patients recover speech within weeks after a stroke. Others make minimal progress after months of therapy. Neither outcome is random. It's predictable if you understand the anatomy and the compensatory mechanisms involved. Reading is the outlier in all of this. It's a cultural invention, not a biological adaptation. The brain repurposes existing visual and language circuits to support reading, which is why the "visual word form area" sits in a region that evolved for object recognition. Illiteracy rates in developed countries remain stubbornly high despite universal schooling, and the neural reasons aren't fully understood. Some brains simply resist the repurposing required for fluent reading regardless of instructional quality. The predictive processing framework continues to reshape how we think about language disorders. Autism, for example, may involve altered predictive weighting rather than a language deficit per se. Schizophrenia shows disrupted prediction error signaling that affects both language and perception. These aren't language disorders in the classical sense, but language is one of the most sensitive indicators of broader predictive processing dysfunction.
If you want to study this further, the dual-stream model papers by Hickok and Poeppel are the starting point. The predictive coding angle is covered in works by Clark and Friston. Clinical applications are scattered across aphasiology journals but accumulating fast. The field is moving away from localizationist thinking toward network-based models, and the practical implications are still being worked out.