The Exchange You Need to Survive Every Second
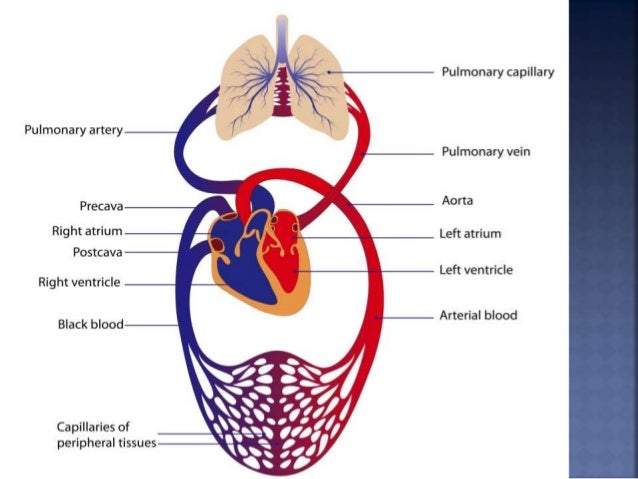
Both systems are essentially transport networks that never shut off. One moves gas, the other moves fluid. When they line up correctly, your cells get oxygen and dump carbon dioxide without you thinking about it. The mechanics are brutal in their simplicity, but the coordination is where most people misunderstand what is actually happening. Start at the alveoli. Each one is a tiny sac lined with capillaries so thin the red blood cells have to slow down and often deform to pass through. Oxygen crosses the alveolar membrane and binds to hemoglobin inside those cells. At the same time, carbon dioxide diffuses the other direction, out of the blood and into the air space you will soon exhale. That is the entire transaction. Everything else is plumbing. The heart sits between the two circuits. The right side pushes deoxygenated blood into the pulmonary arteries toward the lungs. The left side receives the freshly oxygenated return from the pulmonary veins and pumps it out through the aorta to the rest of the body. Pulmonary circulation runs at lower pressure than systemic circulation because the lung tissue cannot handle high pressure. If that pressure differential breaks, you get pulmonary edema fast.
I spent a weekend troubleshooting a home spirometer setup once and realized the real bottleneck is not the device accuracy, it is how shallow breathing during stress skews the numbers. People will take quick, shallow breaths and then blame the meter. The workaround was to have them sit for three minutes first, breathe slowly through the nose, and then take the reading. Consistency matters more than peak numbers. Hemoglobin saturation is the linchpin. At normal arterial partial pressure of oxygen around 100 mmHg, hemoglobin sits at roughly 97% saturation. Drop the partial pressure to 60 mmHg and you are still around 90%, but below that the curve goes steep. This is why a person can feel fine at mild altitude and then crash quickly when saturation drops further. The shape of the oxyhemoglobin dissociation curve does the heavy lifting here. The respiratory system also buffers blood pH through carbon dioxide elimination. When you hold your breath and CO builds up, blood becomes more acidic. Chemoreceptors in the brainstem detect that shift and force you to breathe. It is not about oxygen running out, it is about pH. Athletes who hyperventilate before shallow water activities are playing with this exact mechanism and it can lead to blackouts because the CO signal never triggers before oxygen drops too low.
Ventilation-perfusion matching is the detail beginners usually miss. Not every alveolus receives exactly the same amount of blood flow, and not every lung region gets identical air. The body adjusts by constricting vessels in poorly ventilated areas and dilating them where airflow is good. When this matching fails, like in pneumonia or pulmonary embolism, you get dead space ventilation or shunting, and oxygenation suffers disproportionately to the amount of lung tissue involved. The venous return also relies on the respiratory pump. When you inhale, the diaphragm drops, thoracic pressure falls, and blood gets pulled toward the heart. Exhaling reverses that. Breathing patterns directly affect preload, which means heart output is coupled to respiratory rhythm even without any chemical exchange happening. Heart failure patients often develop periodic breathing patterns because this coupling is disrupted. One practical limitation is that neither system compensates well for simultaneous high altitude and metabolic demand. At elevation, the partial pressure gradient for oxygen drops across both alveoli and tissues. Training helps over weeks, but acute exposure still stresses both circuits. The workaround is gradual ascent, not brute force adaptation.
Get the Full Details