
Spinal Decompression Therapy: What Actually Happens in the Clinic
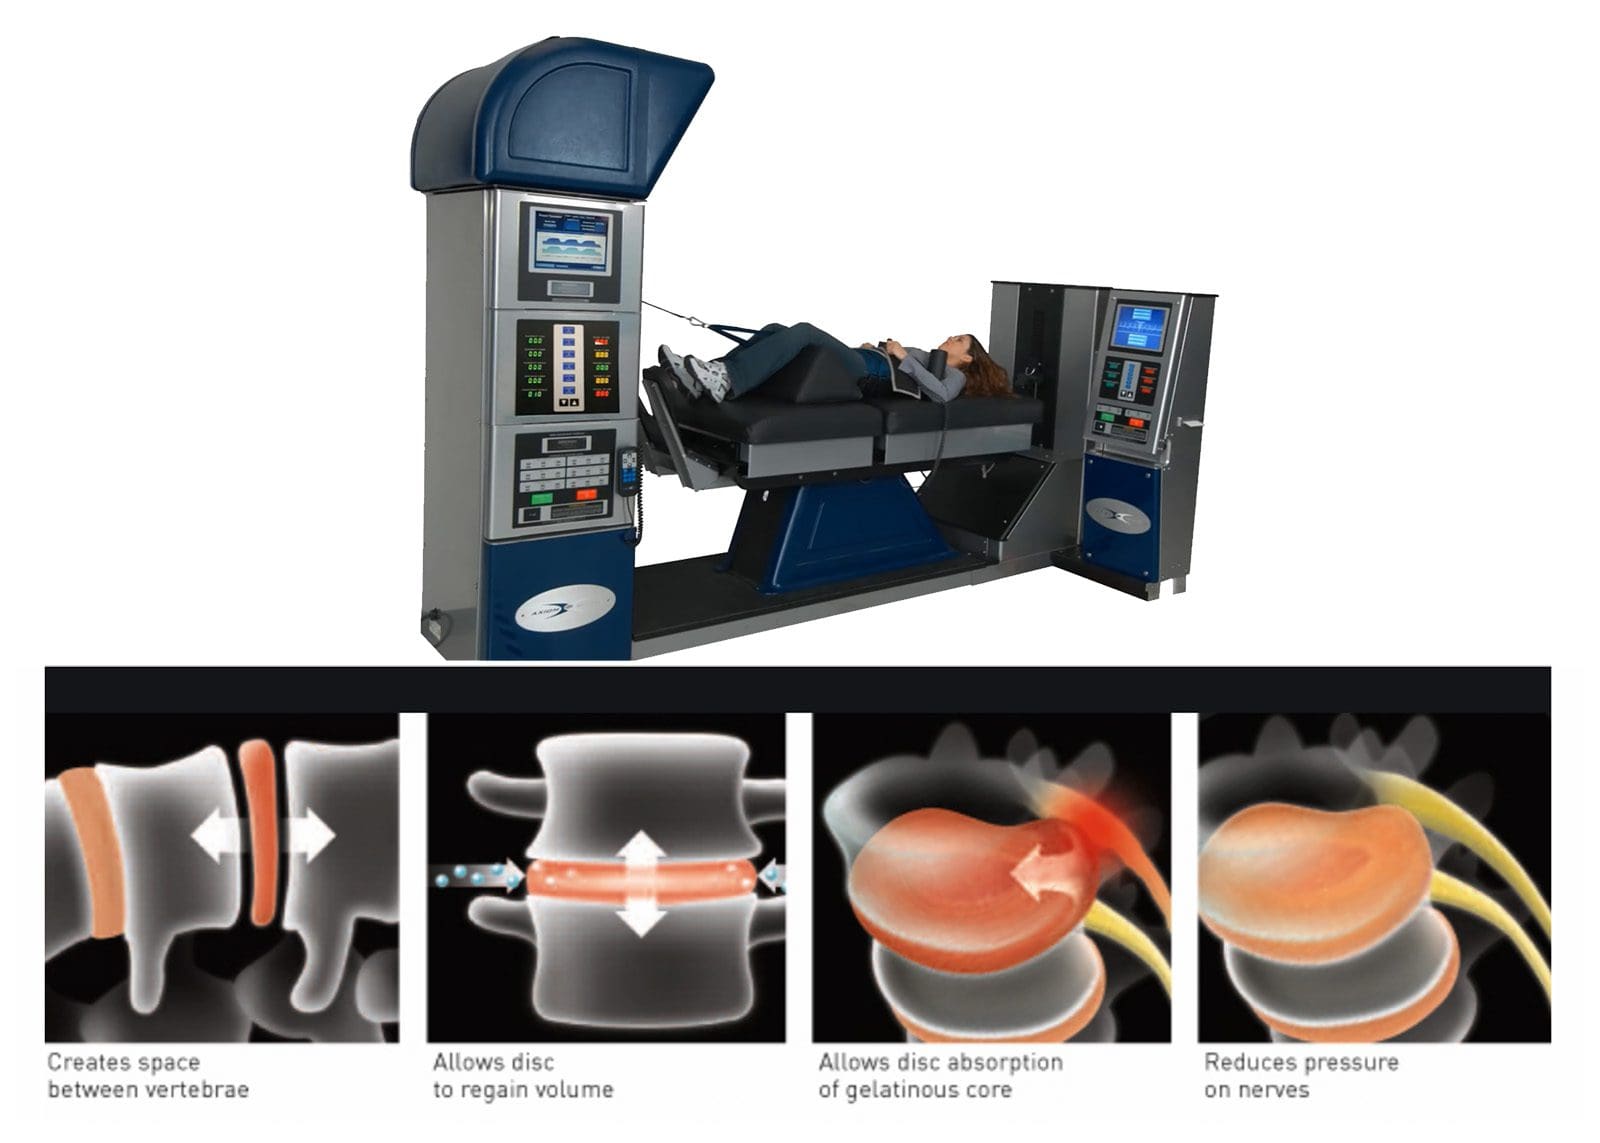
I spent about six months dealing with a recurring L4-L5 disc issue before I started taking this seriously. My physio kept mentioning decompression as something worth trying, but I was skeptical. After a bunch of failed approaches — standard traction, epidural injections, the usual anti-inflammatory route — I just decided to go all in on it. What I learned from that experience is probably worth writing down. Let's get the mechanics out of the way first. Spinal decompression therapy uses a motorized table to gently stretch the spine at specific angles and forces. The goal is to create negative pressure inside the intervertebral discs, which can help retract bulging or herniated material away from nerve roots. It's not magic. It's biomechanics.
How Effective Is Spinal Decompression Therapy
The research is messy, but here's the honest picture. A 2020 systematic review in the Journal of Neurosurgery: Spine looked at multiple randomized controlled trials and found moderate-quality evidence supporting decompression for lumbar radiculopathy. That means leg pain from a compressed nerve, not just back ache. For pure mechanical back pain without nerve involvement, the evidence drops to low quality. The effect sizes are also modest — typically a reduction of about 2 to 3 points on a 10-point pain scale over a full course of treatment. A typical course runs 12 to 20 sessions, each lasting 30 to 45 minutes. You lie on the table, straps go around your pelvis and sometimes your shoulders, and the machine applies a controlled pulling force — usually between 25 and 50 percent of your body weight. The key is that it's intermittent. The machine pulls, then relaxes, then pulls again. That cycling is what differentiates medical-grade decompression from simple static traction. The relax phases allow the paraspinal muscles to settle, which is crucial because if those muscles are guarding, the disc doesn't actually decompress. Here's something most people don't realize: the angle matters more than the force. Pulling straight vertical isn't the same as angling the table slightly. A slight flexion or extension of 5 to 10 degrees changes which disc levels get the most relief. For L4-L5 issues, slight extension tends to open that posterior space better. For L5-S1, a bit of flexion helps. I learned this the hard way during my second round of treatment when my therapist adjusted the angle and I felt immediate relief — the same settings had done nothing the week before.
There's a specific edge case I ran into that I want to mention. About halfway through my treatment, I noticed that sessions were losing their effectiveness. The pain relief was shorter, sometimes lasting only a few hours instead of the full day. I mentioned this to my therapist, and we discovered the problem was that I'd been doing my regular gym routine — specifically deadlifts and heavy squats — on the days between sessions. The spinal loading was essentially undoing the work. We changed the protocol: no axial loading exercises between sessions, plus I added in some McGill curl-ups and bird dogs to build core stabilization without spinal compression. The improvement timeline shifted dramatically after that adjustment. Now for the counter-intuitive part that trips up a lot of beginners. More is not better. Some clinics push high force settings — 50 to 60 percent of body weight — thinking stronger pull equals better results. But there's a window where the force becomes too much and your body responds with protective muscle spasm, which actually increases intradiscal pressure. The sweet spot is usually 25 to 40 percent for most people. If you're sore or spasming the day after a session, the force was too high, not too low. Another thing: decompression doesn't "fix" a disc. It creates conditions where the disc can heal. The nucleus pulposus rehydrates, the annular fibers get a chance to scar over, and the inflammatory cascade around the nerve root calms down. But if you're still doing the things that caused the problem — prolonged sitting, poor lifting mechanics, weak core — the cycle repeats. I've seen that happen to patients after they stop treatment and go right back to their old habits.
Get the Full Details
The real limitations deserve their own section. This therapy does nothing for spinal stenosis caused by bone overgrowth. If you have facet hypertrophy or ligamentum flavum thickening narrowing the canal, stretching the spine won't address the compression. In some cases, extension-based decompression can actually worsen stenosis symptoms. It also doesn't work for cauda equina syndrome — that's a surgical emergency, not a therapy question. And if you have severe osteoporosis, the pulling force risks vertebral compression fractures. Some clinics screen for this with a quick DEXA scan or at least a thorough history, but not all do. Cost is another practical barrier. A full course at a proper clinic runs anywhere from $2,000 to $5,000 depending on your location and insurance coverage. Some insurance plans cover it with a physician referral and documented failure of conservative treatment. Others won't touch it. I had to pay out of pocket for three months before mine kicked in, which was a real strain. What tends to work well alongside decompression is a structured rehab program focusing on core stabilization and hip mobility. The McGill Big Three — curl-up, side plank, and bird dog — have the best evidence base for this. Adding in neural gliding exercises for the sciatic nerve can also help, especially if you have persistent leg symptoms. Heat therapy before sessions and ice after seems to help some people manage the post-session soreness.
If you're considering this, the practical steps are: get a clear diagnosis from a spine specialist first — you need to know exactly what level and what type of disc issue you're dealing with — then find a clinic that uses a computerized, closed-loop system with force feedback. Those are the ones that adjust in real time based on your tissue response. Cheap unbranded tables without load cells are essentially just expensive traction devices. Ask about the protocol they follow, how they determine force parameters, and whether they combine decompression with active rehabilitation. A clinic that only offers passive treatment is probably not giving you the best outcome. From my own experience, the therapy did help, but it wasn't the dramatic reversal I'd seen advertised online. It was gradual — maybe 20 percent improvement after the first five sessions, another 30 percent by session ten, and then a plateau. The final 20 to 30 percent of recovery came from the strengthening work I was doing outside the clinic. Decompression opened the door, but I had to walk through it with actual rehabilitation.


