The Short Answer
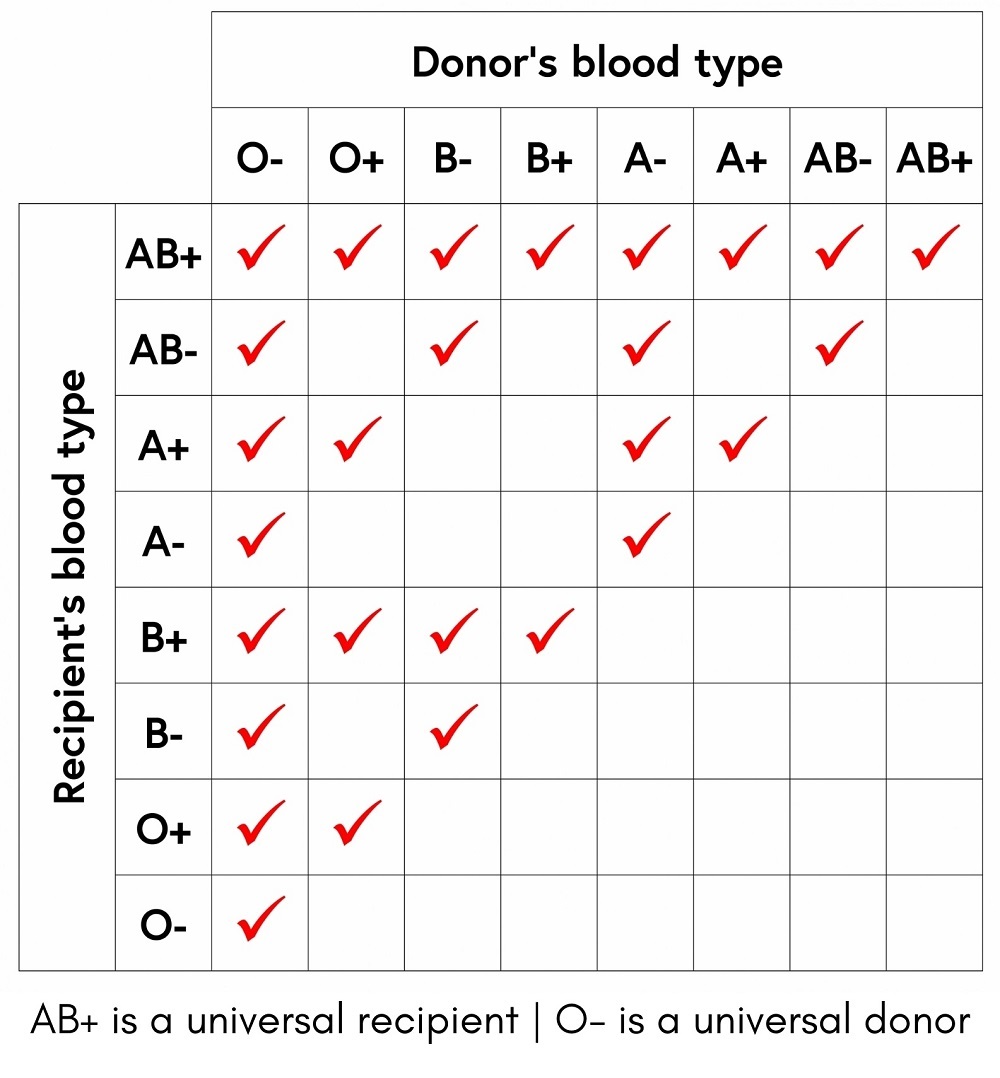
Most people say eight. A, B, AB, and O each split into positive and negative, giving you eight common blood types. That's what your doctor checks and what's written on your blood donor card. But the real number is much higher if you actually look at what's going on in transfusion medicine. The International Society of Blood Transfusion recognizes 46 distinct blood group systems as of my last check, containing somewhere around 360 antigens. An antigen is just a protein or sugar molecule on the surface of a red blood cell. So technically, every person carries a unique combination of those markers, which means you could argue there are millions of possible blood types depending on how you define "type." In practice, clinicians only care about the ones that matter for safe transfusions. The ABO and Rh systems account for the vast majority of clinical decisions. Everything else comes up occasionally, usually when someone has had multiple transfusions or has certain genetic backgrounds. I remember dealing with a patient who typed as O positive on the standard panel but then developed antibodies against a Kell antigen after a routine surgery. The initial workup was completely normal because Kell isn't part of the standard pre-transfusion screen at most hospitals. It took about three extra days of immunohematology testing before we could find compatible blood. That delay wasn't catastrophic because the patient wasn't bleeding out, but it was stressful for everyone involved and would have been much worse if the need had been urgent.
Why the Confusion Exists
Pop science articles and school textbooks almost always stop at eight. That's because eight is the number relevant to casual knowledge. Blood drives tell you which of the eight types you are. Dating compatibility charts (which are pseudoscience, by the way) also use the eight-type model. It's the version of the truth that gets printed on lunchboxes. The medical world doesn't work that way. Blood banks maintain databases that track dozens of antigen systems. When a patient needs a transfusion and has developed antibodies beyond ABO and Rh, the lab has to match on things like Duffy, Kidd, MNS, and Kell. There are rare phenotypes like the Bombay blood group where the person appears to be type O but actually lacks the H antigen that makes A and B antigens possible in the first place. Those people can only receive blood from other Bombay donors, and there are very few of them in most populations.
Practical Implications
If you're just curious about your own blood type, eight is all you need. Get tested at a clinic or a donation center and you'll get one of the eight results. If you're in healthcare or dealing with a complex transfusion case, the answer becomes far more nuanced and sometimes frustrating. One thing beginners in this area tend to miss is that antibody screening isn't a one-time thing. A person can develop new antibodies over time after exposure through pregnancy or previous transfusions. I've seen cases where a patient was fine for years, then suddenly reacted to blood that had been considered compatible. The workaround is extended phenotype matching for anyone who needs regular transfusions, especially patients with sickle cell disease or thalassemia. It costs more in upfront testing but prevents the kind of hemolytic reactions that can be fatal. The downside of going deeper into blood typing is that not all hospitals have the same level of immunohematology capability. Smaller facilities might only do ABO and Rh typing and a standard antibody screen. If a complex case comes up, they have to send samples to a reference lab, which adds time and cost. This is one reason why trauma protocols sometimes rely on O negative universal donor blood rather than waiting for full matching — it's faster and avoids the worst incompatibilities in an emergency.
Get the Full Details

Bottom line: eight types for everyday life, dozens of systems and hundreds of antigens when you actually need to transfuse safely. The gap between those two numbers is where most of the complexity lives, and it's easy to overlook until something goes wrong.