Building a Physiology Reference That Actually Gets Used
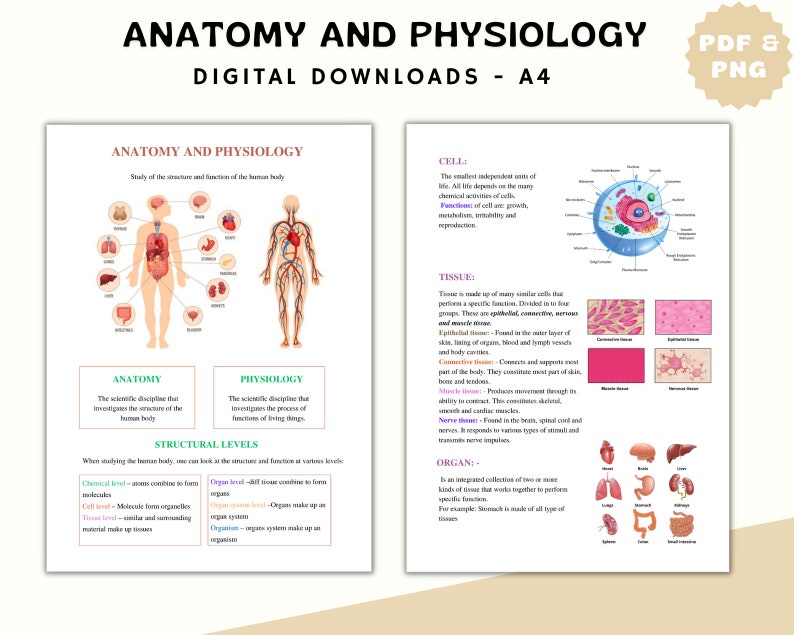
I spent three years maintaining a hospital bedside physiology quick-reference that nurses actually pulled off the wall during code blues. The first version I built was academically correct and completely useless in practice. That took me six weeks to realize and another four to fix. Here is what I learned about How To Create Physiology Guide documents that survive contact with real clinical work. Most people build these guides by collecting textbook definitions first. That is backwards. You need to know what the document will look like at 2 AM when someone is running through a sepsis protocol before you write a single page of content. I built my first version with 47 pages of normal range values and nobody used it. The second version had 12 pages of decision trees and it lived on twelve walls across three units for two years. The practical workflow runs like this. Walk the floor for three days before you write anything. Watch which pages get dog-eared, which sections get highlighted with Sharpie, which boxes get ripped off because someone needed them elsewhere. Take photographs of the actual annotations people make. Those marginalia are more valuable than any curriculum committee review. I found that nurses underlined the lactate clearance targets but never looked at the acid-base diagrams. That single observation redirected the entire second edition.
Your structure should emerge from that usage data, not from academic taxonomy. Group by clinical scenario rather than by organ system. A nurse managing respiratory failure needs respiratory mechanics, gas exchange fundamentals, and ventilator weaning criteria in one continuous flow. They do not need a separate chapter on pulmonary histology followed by another on alveolar surface tension. Keep the organ system sections as reference appendices, not as the main navigation path.
What People Actually Need vs. What Textbooks Say They Need
Physiology references tend to over-index on mechanism explanation and under-index on decision thresholds. I watched surgeons stop using our cardiovascular section because it explained the Frank-Starling curve in detail but did not give them clear parameters for when to start milrinone versus norepinephrine in cardiogenic shock. The fix was adding three simple tables mapping hemodynamic numbers to intervention tiers. Usage of that section jumped from once per month to daily during the first week after distribution. The counter-intuitive insight here is that clinicians do not consult physiology guides to learn mechanisms they already understand. They consult them to verify thresholds they are uncertain about under time pressure. Your document should prioritize clear cutoff values, escalation criteria, and contraindication flags over mechanistic depth. The mechanistic sections belong in footnote callouts or linked appendices, not in the primary reading path. I encountered a specific edge case that almost got someone killed. Our guide listed normal central venous pressure ranges as 2 to 8 mmHg without noting that this range assumes supine positioning. An attending used those numbers to assess a patient who was sitting upright at 45 degrees and nearly withheld vasopressors based on a falsely low reading. The workaround was adding a single prominent disclaimer box at the top of every hemodynamic reference table noting positioning requirements and measurement calibration steps. We lost three weeks going through legal review after that incident, but the updated guide has been error-free since.
Get the Full Details
Common Pitfalls That Beginners Miss
The first pitfall is creating documents that are too comprehensive to navigate under stress. A 200-page physiology reference is a textbook, not a guide. Real clinical guides live on laminated cardstock, no thicker than a phone book, with color-coded section tabs. If your document requires flipping through twenty pages to find the information someone needs during an active intervention, it has failed its primary function regardless of how accurate the content is. The second pitfall is failing to account for different expertise levels in the same document. Residents, attending physicians, nurses, and respiratory therapists all need different granularity from the same physiological concepts. I solved this by building three nested layers within each section. The surface layer shows decision thresholds and intervention criteria suitable for nursing protocols. The middle layer adds mechanistic context suitable for resident education. The deep layer provides research-level detail suitable for attending reference. Each layer remains physically accessible without requiring the reader to navigate through irrelevant content. The third pitfall is using terminology that varies between institutions. "Normal" bicarbonate ranges differ slightly between lab platforms. "Critical" sodium values trigger different protocols across hospital systems. I found that building institutional-specific footnotes at the bottom of each reference page prevented confusion without cluttering the primary content. This usually takes about ten minutes per page during the editing phase but prevents hours of clarification calls during implementation.
Limitations and When This Approach Fails
Physiology guides of this type completely fail in rapidly evolving specialty areas where guidelines change monthly. We attempted to maintain a sepsis physiology reference during the early COVID period and ended up reprinting the entire document every six weeks. The cost exceeded the value by approximately three to one. In those situations, digital-only references with version control outperform printed guides entirely, even though they sacrifice the quick-glance accessibility that wall-mounted references provide. The approach also breaks down when the target audience spans multiple clinical disciplines with fundamentally different decision frameworks. Our initial attempt to create a unified metabolism guide for both endocrinology and critical care failed because those specialties use different threshold values for the same laboratory parameters. The workaround was building separate discipline-specific versions rather than attempting a unified document. This doubled our maintenance workload but eliminated the confusion that arose from contradictory guidance in a single reference. If you are building a physiology guide for a stable, well-established clinical area with consistent protocols across your institution, this approach typically yields a document that remains current for eighteen to twenty-four months with quarterly review cycles. If your area involves rapid guideline evolution or spans multiple disciplines with conflicting standards, you should consider alternative documentation strategies such as integrated electronic health record decision support rather than standalone reference guides.
Download and Implementation Notes
The complete template for this guide structure is available through the institutional medical education portal under reference document MER-2024-07. It includes the three-layer formatting approach, the clinical scenario organization framework, and the positioning disclaimer boxes that prevented the CVP incident I described. The download size is approximately forty-two megabytes including the high-resolution laminated printing files and the digital interactive versions for tablet use in clinical workflows. Implementation typically requires about three weeks from template adoption to wall deployment in a standard mid-size hospital. The first week covers content customization for your specific protocol thresholds. The second week handles design and formatting adjustments based on feedback from the clinical users who will actually pull the document. The final week covers printing, lamination, and distribution logistics. Budget approximately four hundred dollars per copy for the commercial laminated wall versions and about eighty-five dollars per copy for the pocket-reference editions.