The Initial Assessment Misconception
Most behavioral consultants walk into their first session thinking they are there to collect data. They are not. They are there to establish whether this client relationship is even possible before investing two weeks of intensive intervention planning into a family that will disappear after the second session. The initial assessment is a triage tool disguised as a comprehensive evaluation. The people who treat it like a paperwork exercise burn out by month three. The ones who use it to actually decide what to do next stay in the field. An initial assessment for behavioral consulting serves three purposes simultaneously. You need to determine if the presenting problem is behavioral, environmental, or something outside your scope like an untreated medical condition or a neurodevelopmental disorder that requires a different specialist. You need a preliminary behavioral definition rough enough to track progress but specific enough to share with a caregiver who does not understand terms like "differential reinforcement." And you need to assess the family system, the support structure, the consistency of implementation, and the likelihood that recommended strategies will actually be followed in that household. I have watched consultants spend forty-five minutes on a functional behavior assessment interview only to recommend a token economy that was impossible to implement because the child alternated between three homes each week and none of the adults communicated with each other. The assessment looked thorough on paper. It was useless in practice. The workaround I started using was simpler than I expected. I ask about living arrangements and consistency of routines before I ask about any specific behavior. If the home structure cannot support the intervention I am considering, I note that immediately and pivot to strategies that work within constraint rather than trying to fix the environment first.
How To Do A Initial Assessment For Behavioral Consultants
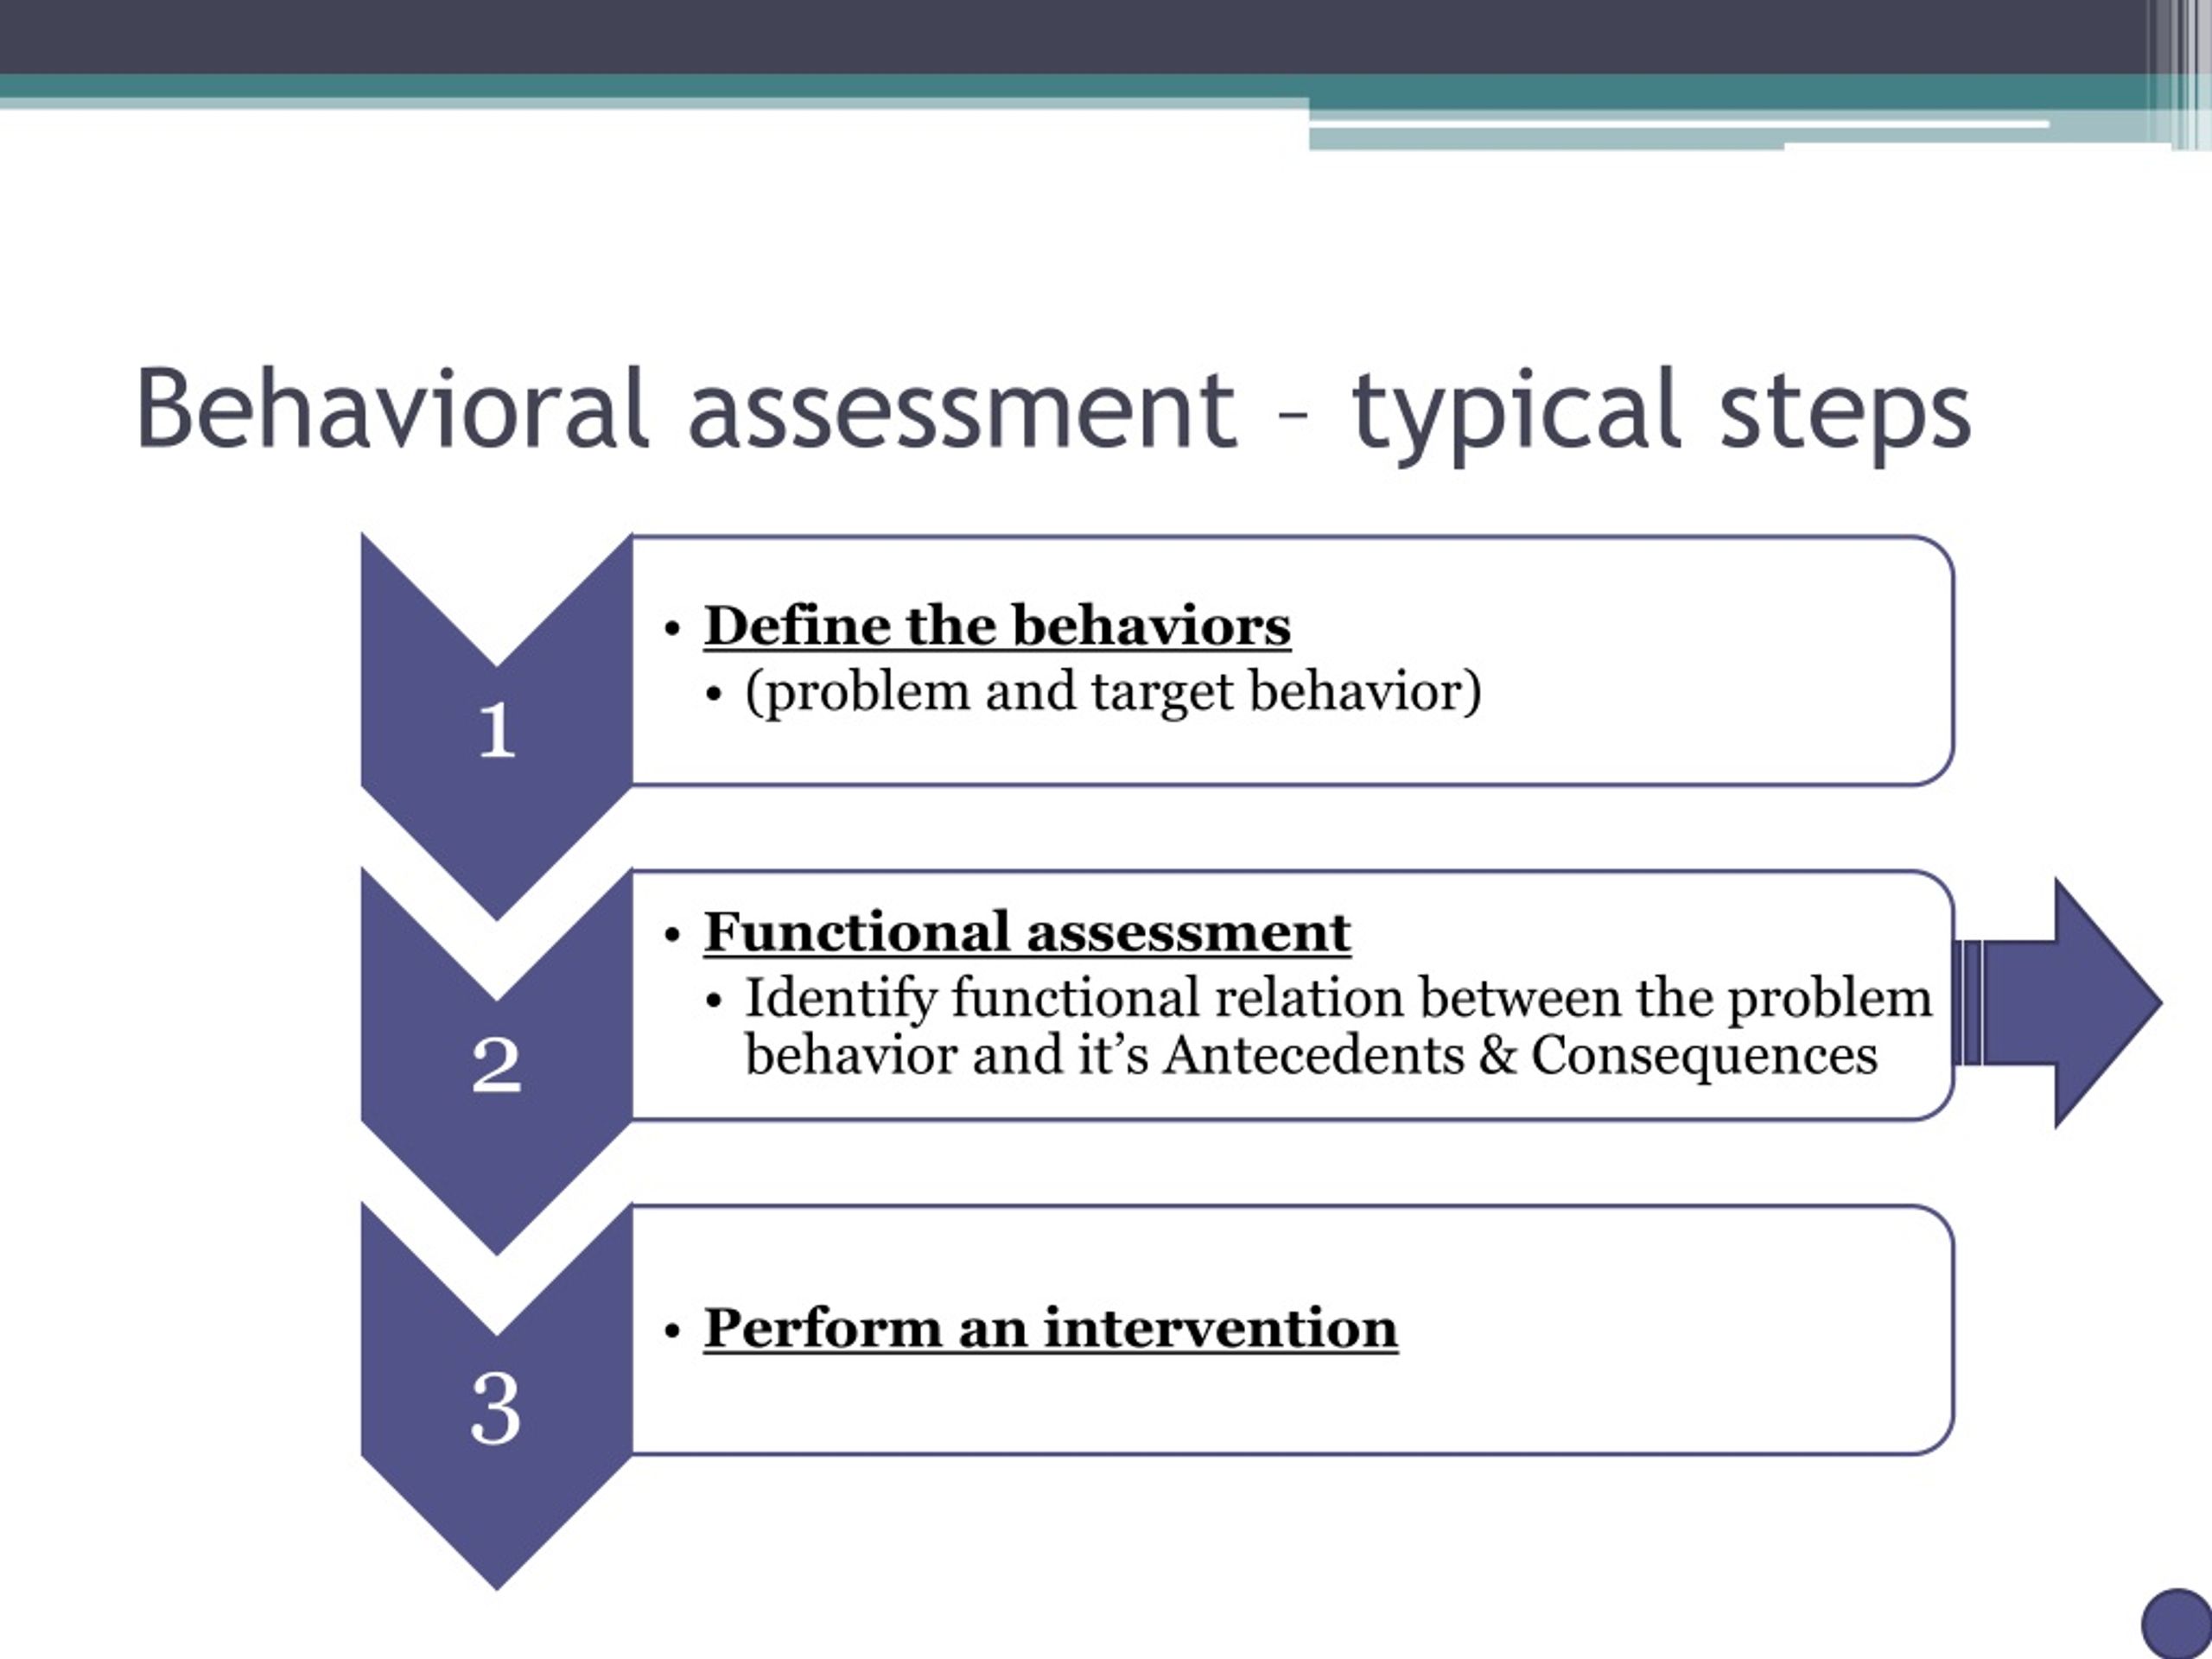
The standard process breaks down into five phases that overlap more than most training programs admit. First, you gather the referral information and understand what prompted contact. Second, you conduct a semi-structured interview with the primary caregiver or stakeholder. Third, you observe the relevant behavior in its natural context when possible. Fourth, you develop a working hypothesis about the function of the behavior. Fifth, you determine whether you accept the case and outline a preliminary treatment approach. Each phase takes less time than people assume. A thorough initial assessment for behavioral consultants usually runs between sixty and ninety minutes total across one or two sessions. Anything longer at this stage is often consultation by avoidance, filling time because the assessor is uncomfortable making a real judgment call. Here is where beginners consistently miss the mark. They chase the perfect ABC data set before they ever define what they are measuring. ABC data, meaning antecedent-behavior-consequence recording, is valuable but it is not the starting point. You define the target behavior operationally first. If you cannot describe the behavior in observable, measurable terms that two independent raters would agree on, you do not have a behavior yet, you have a complaint. I had a case once where a mother described her son's "aggression" and every piece of data I collected showed it was primarily property destruction during transition times, not interpersonal aggression at all. The intervention for aggression and the intervention for property destruction during transitions are different things. We were nearly booked for a full program before someone actually defined what was happening. The interview phase should follow a structured format but not a rigid script. Use open-ended questions early to let the informant tell you what they consider the problem. Then narrow down. Ask about the frequency, duration, intensity, and latency of the behavior. Ask what happens right before and right after. Ask when the behavior does not occur because that tells you more than the occurrences themselves. I keep a mental checklist that covers medical history, developmental milestones, current medications, school performance, sibling dynamics, parental mental health, and socioeconomic factors that affect treatment feasibility. None of these are optional. A child on stimulants for ADHD presents differently than one who is not. A household where food security is a concern cannot reliably implement the same reinforcement schedule as one where that is not a factor. These details shape everything.
Observation during the initial assessment is often skipped or done poorly because consultants feel pressure to move quickly to intervention. I spend at least twenty minutes in direct observation whenever the situation allows. I do not take data during that first look. I watch for patterns. I note the physical layout of the space, the proximity of caregivers, the presence of triggers, and the natural consequences that already occur. This unstructured look catches things structured rating scales miss. One client, a teenage boy referred for "defiance," spent most of his assessment sitting in the corner of the room reading. The defiance only appeared when his father entered the space and began giving instructions. The function was clear by the end of the second observation session: escape from demands, not generalized opposition. The parents had been trying attention-oriented reinforcement for months because they assumed the behavior was about power. It was about avoiding tasks the teen found overwhelmingly difficult. Twenty minutes of quiet observation redirected an entire treatment plan. The working hypothesis is where most assessments either succeed or fail publicly. You are not proving anything at this stage. You are generating a plausible explanation that can be tested through intervention. State your hypothesis clearly and then actively try to disconfirm it. If the behavior only occurs when a specific adult is present, that changes the hypothesis compared to behavior that occurs equally across all adults. If the behavior stops when the child has an escape route and escalates when that route is blocked, the function is likely different from behavior that continues regardless of environmental modifications. I use a simple format: "I believe [behavior] serves the function of [function] because [evidence], and I will know I am wrong if [disconfirming evidence appears]." Writing it this way forces you to think about what would change your mind, which prevents confirmation bias from running the assessment. The acceptance decision is the part nobody trains for. After the assessment you must decide whether to take the case, refer out, or recommend a different level of service. Sometimes the answer is no, and that is professionally appropriate. I turned down a case last year where the presenting problem required medical psychiatry intervention first, and the family was not ready to address the underlying condition. I gave them a written summary of my findings and three referrals to specialists before I closed the file. The consultant who took that case anyway spent six weeks trying to behaviorally manage a condition that needed medication adjustment, and the family ended up blaming themselves for "failing" the intervention. That outcome is preventable.
Get the Full Details

Documentation during and immediately after the assessment matters more than people realize. Your notes become the foundation for the treatment plan and the baseline data against which progress is measured. I use a standardized template that includes identifying information, referral source, present ing problem statement, developmental and medical history, interview summary, observation notes, working hypothesis, assessment instruments used, diagnostic impressions if applicable, treatment recommendations, and risk factors. The template takes about twelve minutes to fill out properly if you are organized during the session. Rushing documentation after the fact usually doubles the time and introduces errors. There are limitations to the initial assessment that no textbook acknowledges directly. It is a snapshot in time, not a movie. Behaviors change across contexts and over time, so your hypothesis may be partially wrong even when the assessment was conducted correctly. Caregiver recall is unreliable, especially under stress. Self-report measures are influenced by social desirability and parental guilt. Observer effects mean the client may behave differently when being watched. No single assessment resolves these problems entirely. The workaround is redundancy. Use multiple data sources, multiple informants, and multiple observation sessions when possible. Accept that your first hypothesis will be refined or revised, and build that expectation into your timeline from day one. One counter-intuitive finding from years of doing this work: the quality of the initial assessment correlates more strongly with how well the consultant listens than with how many standardized instruments they administer. The Abell-Anderson Functional Assessment Interview, the Motivation Assessment Scale, and the Func tional Assessment Rating Tools are useful but they are supplements, not substitutes, for clinical judgment built through careful listening and pattern recognition. I have seen consultants with comprehensive test batteries miss obvious environmental triggers because they were too focused on scoring protocols. I have also seen consultants with a clipboard and ten good questions identify the maintaining variables in a single session because they paid attention to what was not being said.
The final output of an initial assessment should be a clear, written summary that the family can read and understand, a testable hypothesis, and a concrete recommendation about next steps. If you leave the session without those three things, you did not complete the assessment, you completed an interview that happened to take a long time. The summary should be one to two pages maximum. Families do not read four-page clinical reports. They read one page and decide whether to trust you. That decision determines whether the intervention ever starts.