Getting the Stethoscope Right Before You Even Think About Writing It Down
Most people skip the warm-up and jump straight into documentation. That is backwards. I was dealing with a patient at 0400 hours—COPD exacerbation, loud wheezes everywhere—but my stethoscope hadn't been warmed. The tubing was cold metal from the supply cart. The patient tensed up immediately, breath-holding, and I spent twenty minutes trying to get through the anterior lung fields before I remembered to run the bell and diaphragm under warm water. By then I had already missed two distinct rhonchi because the patient was too uncomfortable to cooperate. Run the diaphragm in your palm for thirty seconds. Check the room temperature. If it is below sixty-eight degrees Fahrenheit, breathe on the metal. This matters more than anything in the documentation section that follows because the moment a patient feels unsafe or cold, their breathing changes and you are documenting the wrong thing anyway.
How To Document Lung Sounds
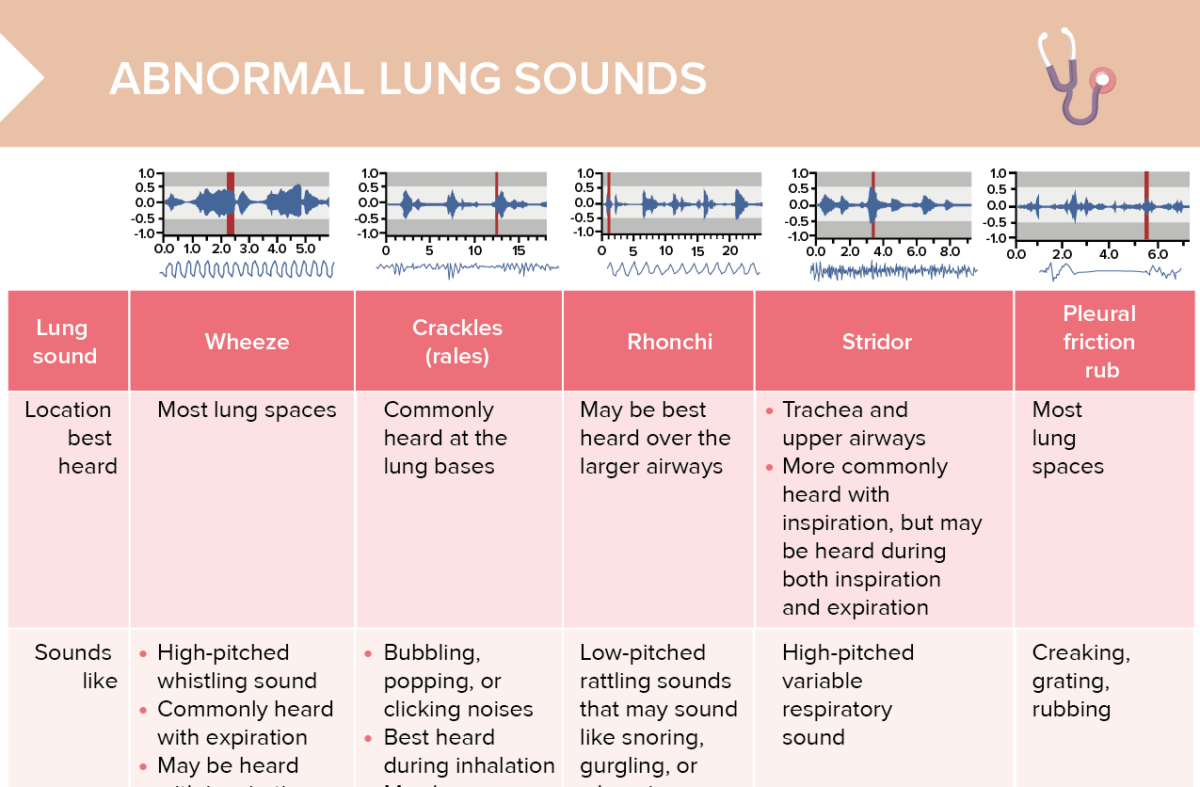
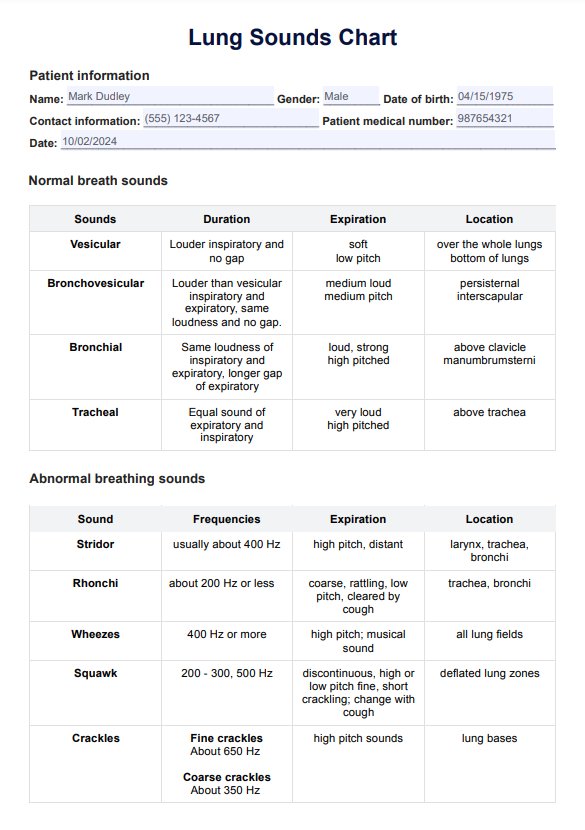
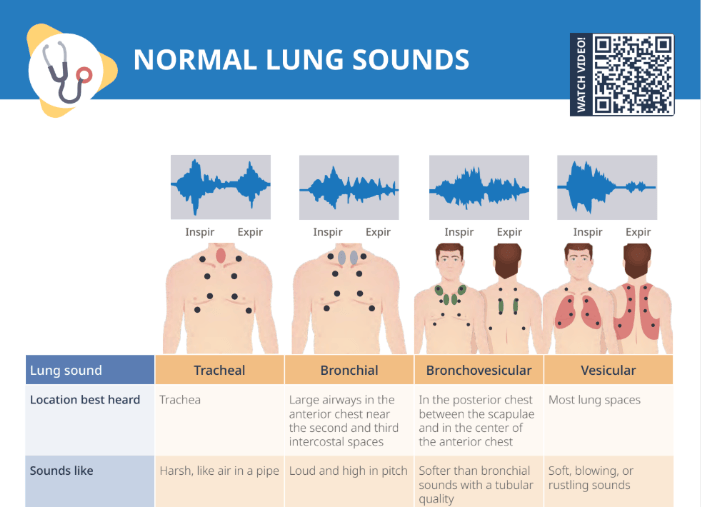
The standard framework most facilities use is basically location, character, intensity, and timing. Start with the location. Be specific. "Right upper lobe" is better than "right lung." Use anatomical landmarks: the second intercostal space at the midclavicular line, the scapular border at T6-T7 for posterior bases. Write it out like that. Later, when you are transferring care and someone asks what you heard at the left base, you will be glad you included the vertebral level instead of just writing "left lower lung." Character comes next. Choose the precise term. Crackles—fine, coarse, mid. Wheezes—monophonic or polyphonic. Rhonchi. Stridor. Pleural rub. Don't write "abnormal sounds" or "crackly." Those phrases mean nothing on paper. A fine crackle at the bases is different from a coarse crackle at the apices, and the documentation should reflect that difference because treatment pathways diverge based on exactly which sound you heard where. Intensity is usually graded on a one to four scale. Zero means absent. One is barely audible. Two is normal breath sounds. Three is increased. Four is loud enough to hear with the stethoscope slightly lifted off the chest. I have seen people use this scale incorrectly for years. They grade a wheeze by how loud it is instead of grading the underlying breath sounds beneath it. The two things are separate. Document breath sound intensity separately from the adventitious sound intensity. A patient can have breath sounds rated two with pleural rub rated three. Those are not the same measurement.
Timing matters especially for crackles. Early inspiratory crackles point to different pathology than late inspiratory or even expiratory crackles. Fine crackles that appear at end-inspiration are classically associated with pulmonary fibrosis or heart failure. Coarse crackles that persist through expiration suggest bronchitis or pneumonia. Write when in the respiratory cycle you heard them. This single detail is what separates a useful clinical note from a generic one.
Get the Full Details

Practical Workflow I Use At Every Bedside
I do posterior fields first. The patient is sitting up, usually more comfortable, and the lung bases are the most common place for pathology to hide anyway. I work symmetrical—right side then left side at each level. Apex, mid-lung, base. Then anterior. Same approach. I document as I go rather than trying to hold everything in my head. A small notepad works fine. I transfer it to the chart later. Here is a specific problem I ran into that changed how I document. A few years ago I was covering a floor shift and heard what I thought were bilateral basilar crackles. I documented it quickly and moved on. The next morning the respiratory therapist flagged the note and pointed out that the patient was actually producing secretions—productive cough with thick yellow sputum. What I had called crackles were likely coarse rhonchi that cleared after coughing. I retried the assessment post-cough and the sounds had completely changed. From that point forward I started always noting whether the sounds cleared with coughing. It takes ten extra seconds and prevents a massive documentation error that could lead someone down the wrong treatment path.
Common Mistakes That Will Get You in Trouble
The biggest issue I see is over-documenting. Students and new clinicians will write "crackles present" without specifying where, when, or how they behaved. Then the attending asks a follow-up question and you have nothing to fall back on because you didn't capture the detail in real time. Re-auditing later rarely recovers the information because memory is unreliable and the patient may have changed position or treatment by then. Another mistake is using vague descriptors like "diminished" without context. Diminished breath sounds can mean poor air movement, obesity, muscle guarding, or a large body habitus. Each of those has different implications. Specify what you think is causing the diminishment or at least note the patient's build and positioning. A lean patient with diminished sounds at the right base is a different clinical picture than an obese patient with globally diminished sounds. I also see people documenting lung sounds without noting the patient's position. Sitting upright, supine, and lateral decubitus positions shift fluid and air distribution significantly. If you assessed the patient lying flat and documented basal crackles, someone reading that note later won't know whether those were positional or pathological without you stating the position explicitly.
What This Method Doesn't Do Well
Lung sound documentation has hard limits. It cannot reliably detect early pneumonia in a noisy environment. It is operator-dependent to an uncomfortable degree. Two clinicians listening to the same patient at the same time can document different findings if their experience levels differ. Pulse oximetry and imaging often catch pathology before auscultation does. Do not let lung sound documentation create a false sense of comprehensive assessment. It is one data point. When the clinical picture doesn't match your auscultation findings, trust the rest of the picture and escalate, don't force the documentation to fit. Electronic health record templates sometimes make this worse by giving you checkboxes instead of requiring narrative. I have seen notes where someone checked "crackles present" and nothing else. No location. No timing. No character specification. That checkbox is legally a record of an assessment that never actually happened in the detail required. Fill the fields or write the narrative. A partial template entry is worse than no entry because it implies thoroughness that wasn't there. If you want something faster than handwriting, I use a voice dictation tool synced to my EHR. It cuts my documentation time from about four minutes per patient to roughly ninety seconds. The quality is good if you speak clearly and slowly. It struggles with medical terminology if you rush. Dictating "fine late-inspiratory crackles bilaterally at the left lower lobes posteriorly" takes about six seconds. Dictating it while walking between rooms and thinking about your next task turns it into garbage. Slow down for the dictation. The EHR will thank you.