The Ground-Level Guide To Preparing For A Pelvic Exam
Pelvic exams are routine, but the prep work most people get wrong falls into two buckets: things that actually matter and things that are pure theater. I stopped guessing after my third attempt where the speculum didn't even open fully because I hadn't told the physician I was on my period. Here's what you need to know before you go. Timing is the first lever you can pull. Schedule the appointment between days 10 and 20 of your cycle, if you can manage it. Days 1 through 5 are basically a no-go unless there's an urgent reason, because blood obscures the view of the cervix and the sample quality for pap smears degrades fast. I learned this the hard way when a tech had to scrape three times on a day-4 visit just to get an adequate sample, and they still flagged it as "unsatisfactory" in the report. That meant a repeat in eight weeks, which cost me half a day off work and another co-pay. Do not use vaginal products for at least 48 hours before the exam. This includes tampons, menstrual cups, spermicides, antifungal creams, douches, and scented lubricants. Even the over-the-counter anti-itch creams that people grab without thinking can leave a residue that skews results or irritates the mucosa during the exam itself. I once had a patient who used a hemorrhoid cream the night before and came in with significant burning during the speculum insertion. She was mortified. Neither of us wanted that. It was easily preventable.
Empty your bladder right before the exam. Full bladders press against the uterus and ovaries, making palpation less informative and more uncomfortable. There's no benefit to holding it. They won't ask you to arrive with a full bladder unless they're doing a transabdominal ultrasound at the same time, and even then the sonographer will tell you when to hold and when to go.
What People Get Wrong About Prep
The biggest misconception is that you need to do a deep vaginal cleanse beforehand. You don't. Normal hygiene with warm water on the outside is sufficient. Scrubbing inside or using harsh soaps disrupts the flora and can cause micro-tears, which makes the exam painful and can introduce bacteria into the upper tract. I've seen patients who swear by "extra cleaning" come in with contact dermatitis on the vulva. The speculum touches that tissue directly. It's not worth it. Another common error: showing up in restrictive clothing. The exam requires you to get down to your underwear or fully nude from the waist down. Tight jeans, shapewear, or complicated belts add unnecessary friction and time to a process that already makes people uncomfortable. Wear something loose. A dress or sweatpants and a loose top takes 30 seconds to manage. Saved me about five minutes in a back-to-back scheduling scenario where every minute counted.
Get the Full Details

The Speculum Problem Nobody Talks About
Speculums come in three standard sizes: narrow, medium, and wide. Most people assume the narrow one is the default, but it's not always the right call. A narrow speculum on a patient with a tight introitus or vaginismus can cause significant pain and may not provide adequate visualization. Conversely, a wide speculum on someone who is very relaxed and has regular anatomy might feel like overkill. I ran into a case last year where a patient had had painful exams her entire adult life. The standard approach was a narrow speculum with extra lubricant, but the lubricant was interfering with the cytology slide. The workaround was using a warm speculum—running it under warm water for 30 seconds—and switching to a pediatric speculum despite her being nulliparous. The smaller blade width combined with the warmth reduced the stretch reflex enough that she could tolerate it. We got a clean sample on the first try instead of the three attempts she'd had over the previous two years. It's a small detail most general practitioners don't consider, but it matters.
What To Expect During The Actual Exam
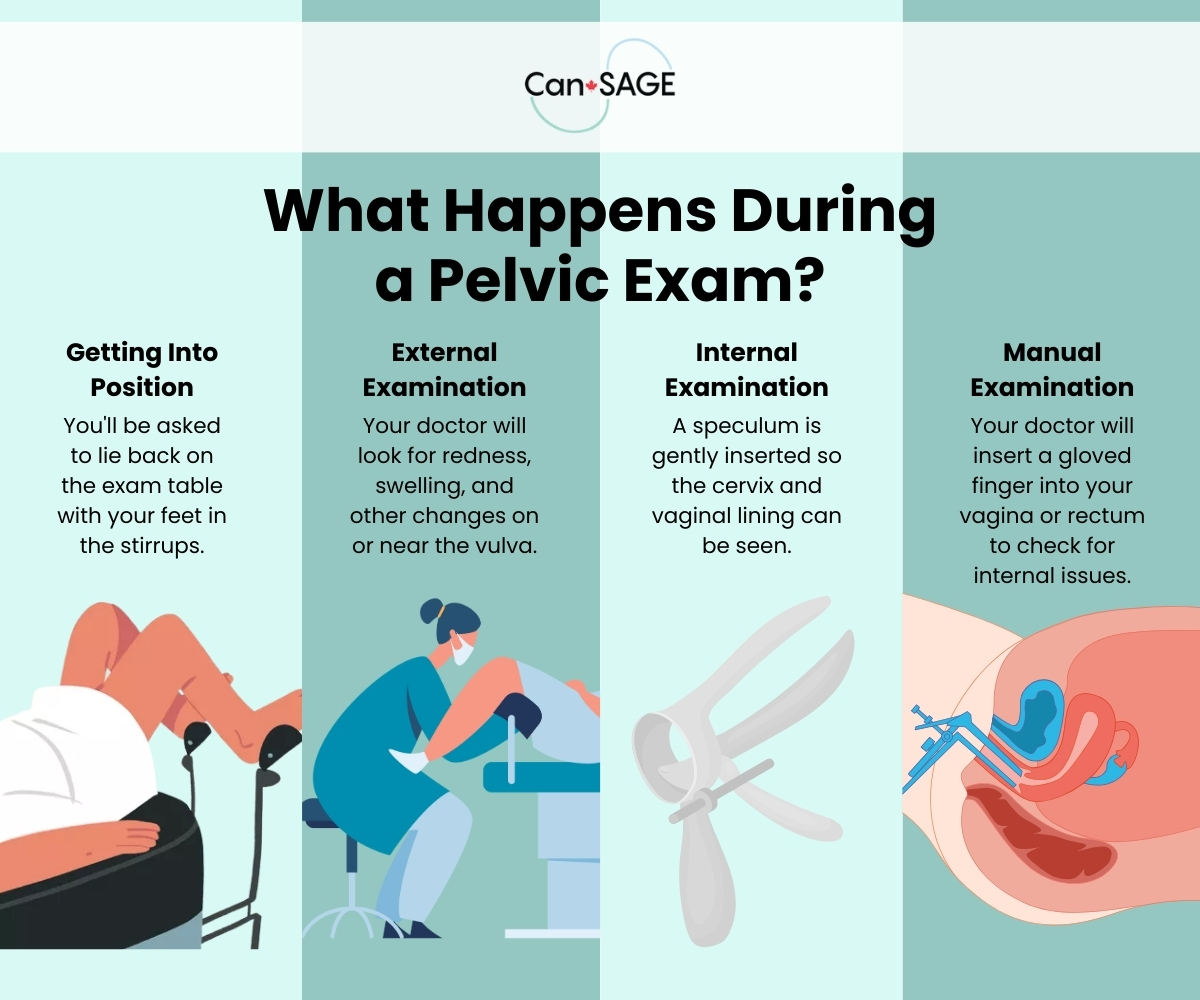
The bimanual portion involves the provider inserting gloved, lubricated fingers into the vagina while pressing on your lower abdomen with the other hand. This assesses the size, shape, and mobility of the uterus and ovaries. It's where most discomfort comes from, and it's usually over in 30 to 60 seconds if everything is normal. The speculum portion is longer. It should take about one to two minutes. The provider inserts the speculum, opens it gently, and examines the cervical os and vaginal walls. If they're collecting a pap smear, they'll use a small brush or spatula to gather cells from the transformation zone. This takes maybe 10 seconds. The whole external portion, including draping and undressing, usually runs 10 to 15 minutes for a standard annual exam. If they're doing a transvaginal ultrasound as part of the same visit, plan for an additional 10 to 15 minutes. The probe goes into the vagina and gives a much clearer image of the uterus and ovaries than the abdominal approach. It's more comfortable than most people expect because there's no pressure on the bladder.
Practical Details That People Skip
Bring a pad, not a tampon, for the day of the exam. If you're on your period and the provider decides it's still acceptable to proceed, you'll need something external. Tampons are impossible to manage in a bathroom stall with a paper drape on the table. I've watched people fumble with that for ten minutes while the clinic waited. It's awkward for everyone. If you have a history of pelvic pain, endometriosis, or prior surgeries, say something. Not as a complaint, but as a heads-up. The provider needs to know to go slower with the bimanual exam or to avoid certain positions. I once had a patient with a History of two C-sections who came in for a routine exam. The provider pressed firmly on the lower abdomen without knowing the scar tissue situation. She winced. That's unnecessary. Ask for a smaller speculum if you're anxious or have had painful exams before. You don't need to justify it. The statement "I'd prefer the smallest one you have" is enough. A good clinician will make it happen without comment. A bad one will make you feel like you're being difficult. Note which kind you're dealing with and adjust your future visits accordingly.

The Follow-Up Piece
After the exam, you may spot a tiny amount of bleeding if the cervix was irritated during the pap smear collection. This is normal and resolves within a day. If bleeding continues beyond 24 hours or you experience significant cramping, call the office. Don't wait until your next scheduled visit. Pap smear results typically come back in one to two weeks. Some clinics use an electronic patient portal; others call. If you haven't heard anything within 14 days, follow up. Results don't self-report. I've seen patients assume silence means good news, then find out three months later that an abnormal result was sent to a mailbox they never checked. If your pap comes back as ASC-US or worse, don't panic but do act. The standard next step is colposcopy, which is a magnified examination of the cervix with biopsy if needed. It's outpatient, takes about 20 minutes, and is done in the same office. The numbing medication isn't always necessary because the biopsies are tiny, but it depends on how many spots they need to sample.
When To Reschedule Instead
Reschedule if you're actively menstruating heavily. Light spotting is fine; a full flow makes the sample unreadable. Reschedule if you've had a recent vaginal infection and are still on treatment. The inflammation changes the cellular appearance and leads to false positives. Wait until the treatment is complete and you've had no symptoms for at least 48 hours. Reschedule if you've had a recent IUD insertion. The cervix is often slightly inflamed afterward, and the exam can be unnecessarily uncomfortable. Two weeks is a safe window. I had a patient who came in four days after an IUD placement and nearly cried during the bimanual exam. She could have avoided that entirely by calling and moving it back. The preparation itself is straightforward. The biggest factor in a good exam isn't the prep—it's finding a provider who listens when you say something hurts and adjusts accordingly. No amount of pre-exam hygiene or timing optimization fixes a clinician who rushes through it. Spend the time finding the right person. It makes every subsequent exam significantly easier.