Getting an accurate reading without the electronics
I’ve spent years taking blood pressures by hand in clinics that didn't have working digital units, and honestly, once you get the rhythm down, it's more reliable than you'd think. The problem isn't really the technique itself—it's the patience. People quit too early, or they pump way too hard and miss the real numbers entirely. I see it constantly. Here's what actually happens when you use a manual cuff, step by step, the way I've trained people to do it without overcomplicating things.
How To Use A Manual Blood Pressure Cuff Properly
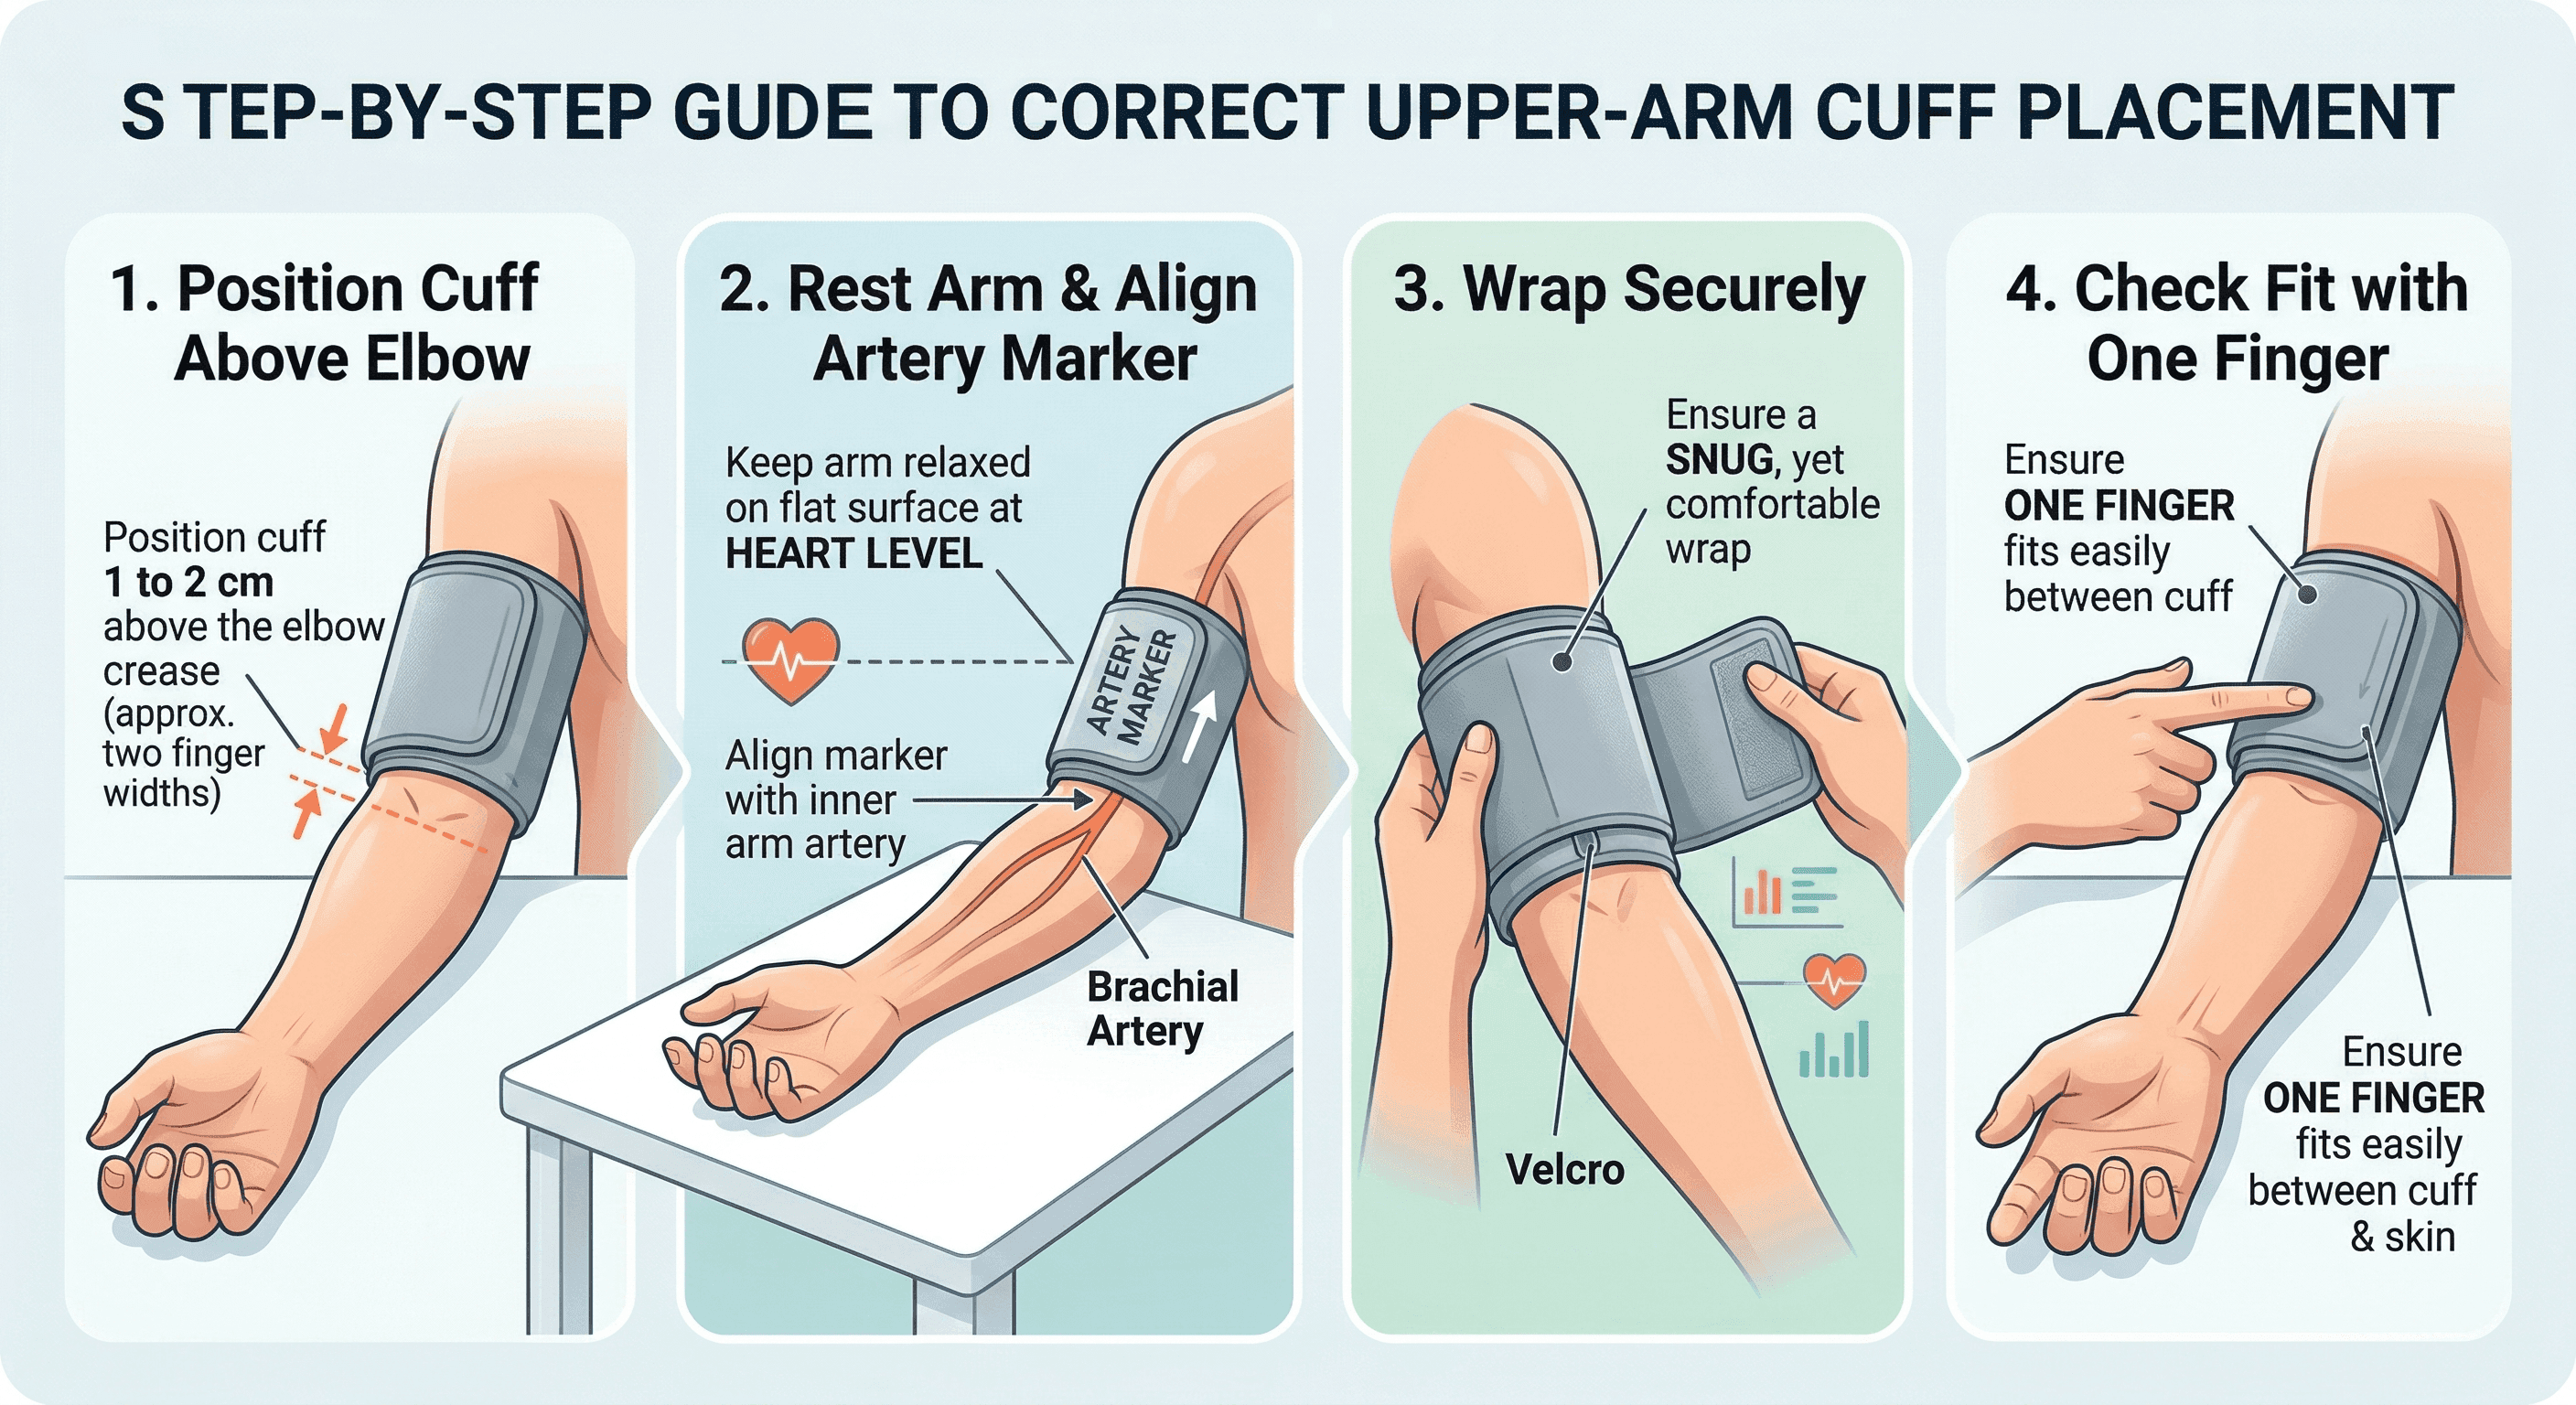
First, pick the right cuff size. This matters more than most people realize. If the bladder inside the cuff doesn't cover about 80 percent of the arm's circumference at the midpoint, your reading will be off. I've seen readings jump 15 to 20 millimeters of mercury just from using a standard adult cuff on someone with a larger arm. Measure the arm before you start. Always. Have the person sit with their back supported, feet flat on the floor, and arm resting at heart level. Not dangling. Not raised above the head. Just resting on a surface so the arm is relaxed and the cuff is level with the right atrium of the heart. If the arm is hanging down, gravity adds pressure and your reading goes up. If it's raised above heart level, the reading drops. This alone accounts for a huge number of inaccurate home readings I've had to redo. Wrap the cuff around the bare upper arm. The bottom edge should sit about two centimeters above the antecubital fossa—that's the crease in the elbow. Don't stuff the tubing under the arm or let it kink. I've pulled readings that were completely off because the tubing was compressed under the person's own weight when they shifted during inflation.
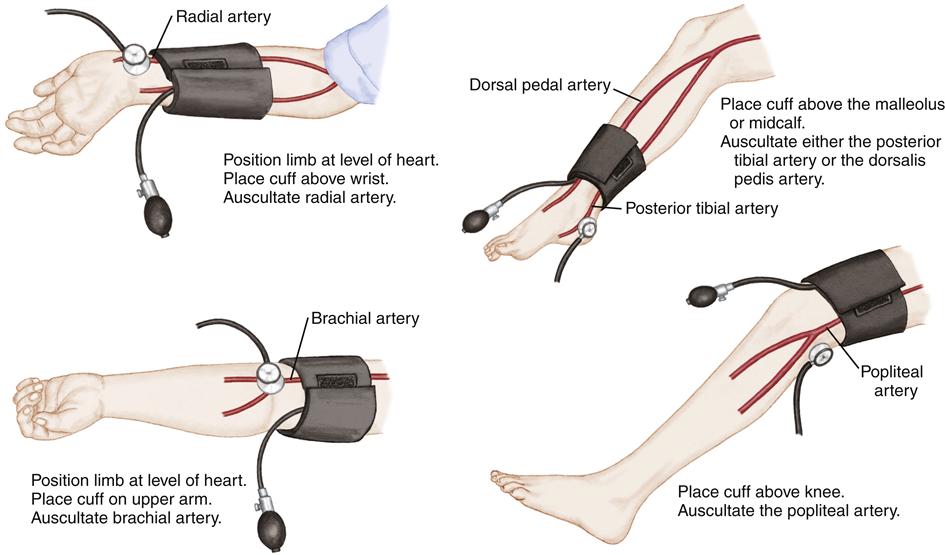
Locate the brachial artery. Run your fingers along the inside of the arm, just medial to the biceps tendon, and find where the pulse is strongest. Place the bell or diaphragm of your stethoscope there. You're not guessing. Press firmly enough to create a seal but not so hard that you occlude the artery yourself. A small adjustment of a few millimeters can mean the difference between hearing crisp Korotkoff sounds and hearing nothing at all, especially in patients with higher body mass. Now inflate. Close the valve on the bulb and pump up to about 180 millimeters of mercury, or until you can't hear anything anymore through the stethoscope. Then deflate slowly. About two to three millimeters of mercury per second is the target. Faster than that and you'll miss the first sound. Slower and you waste time, and the patient gets uncomfortable holding still. I usually count down from whatever number I see as the first thump appears, then I note each subsequent sound as it fades. The first Korotkoff sound—the first clear tap—is your systolic. The point where the sounds disappear entirely is your diastolic. In some patients, especially older adults, you might hear a brief murmur or muffling before the sounds completely vanish. That's K4, and it's not the diastolic. Stick with K5, the disappearance point. If the sounds go all the way down to zero, which happens occasionally in severe aortic regurgitation or other conditions, then you use K4 as a reference but note it clearly. I've had cases where the sounds just tapered into a whisper and never fully stopped, and writing down both numbers with a note saved the clinician from misreading the data.
Get the Full Details
Deflate the cuff completely and wait at least thirty seconds before taking a second reading. Take two readings, average them. If they're more than four millimeters apart, take a third. That's standard practice and it cuts down on random error significantly.
Common mistakes I actually see people make
The biggest issue is talking while you're taking the reading. Blood pressure goes up when the patient talks. It's not a theory. I've had patients who would explain their symptoms mid-measurement and the systolic would climb ten to fifteen points between the first and second attempt. Just tell them to stay quiet and don't let them justify themselves. Another thing: rolling the sleeve up too tight. A constricting band of fabric above the cuff acts like a tourniquet. I once took a reading on a patient whose sleeve was rolled tight above the elbow and the systolic was thirty points higher than it should have been. Had to pull the sleeve down and re-do it. Bare skin is the standard for a reason. And don't use the same arm every time if one arm has known vascular issues. If someone has a history of dialysis fistula, lymph node dissection, or arterial disease in one arm, use the other. I learned this the hard way when a patient came in with what looked like wildly inconsistent readings, and after checking both arms I found a sixty-millimeter discrepancy due to unilateral subclavian stenosis. That kind of thing won't show up if you only ever measure one side.
When manual doesn't work
Let me be clear about where this method falls apart. In noisy environments—emergency departments, busy clinics with multiple conversations happening—your ability to isolate Korotkoff sounds degrades fast. Digital oscillometric devices handle that better in real-world conditions, even though they have their own accuracy issues at the extremes. If you can't hear the sounds clearly, don't guess. Move to a quieter setting or use a device with an audible display. Patients with atrial fibrillation are another problem. Their pulse is irregular, so each beat produces a different sound intensity. The first Korotkoff sound might appear at 140 one moment and 120 the next. I usually take three readings and report the range rather than a single number. Writing down just one reading in that situation gives a false sense of precision. Obese patients with very dense tissue can make auscultation nearly impossible even with a good stethoscope and quiet room. In those cases, palpation only gives you systolic pressure—you press the cuff up until you can no longer feel the radial pulse, then note that number. It's less complete but better than a wrong number from guessing through the noise. I'll also adjust the stethoscope placement slightly distal in these cases since the brachial artery sits deeper, but don't press harder to compensate. You'll just compress the artery and cut off the sound yourself.
Manual cuffs require practice to be accurate. My first twenty or so readings were all over the place. The difference between a good reading and a bad one usually comes down to how steadily you deflate and whether you actually locate the artery correctly instead of just placing the stethoscope wherever feels convenient. Both of those things improve with repetition, not theory. If you're learning this for clinical work, get supervised practice on at least thirty patients before you trust your own numbers. Compare your readings against a trained colleague's. The discrepancy will tell you what you need to fix faster than any manual can.