
Why The Chart Looked Wrong Even Though The Numbers Were Right
I spent three years debugging a medication error that turned out to have nothing to do with medication. The pharmacist had double-checked the dose. The computer had flagged nothing. The nurse had verified the patient wristband against the MAR three times. What actually happened was that two different IV pump manufacturers used identical-looking alarm tones for completely different fault states, and the night shift tech had been responding to a fluid-air-detector alarm as if it were a completion beep. He stopped pumping, left the line attached, and walked away. The patient got nothing for forty-seven minutes before someone noticed the drip was static. This is the thing most people miss when they first encounter human factors work: the error wasn't human in any meaningful sense. The system had stacked failure modes until the only surviving variable was a person who happened to be tired. Human factors isn't about blaming the tired person. It's about mapping the stack.
What Human Factors In Healthcare And Patient Safety Actually Means
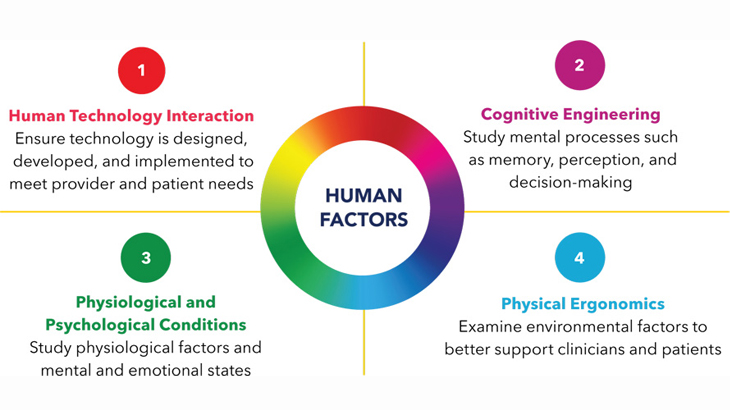
Human factors is the applied study of how people interact with tools, environments, procedures, and each other in clinical settings, with the explicit goal of designing those interactions so that mistakes become harder to make and easier to catch. It borrows from psychology, ergonomics, industrial engineering, and systems theory. The working definition you'll see in practice is straightforward: if a task regularly produces errors under normal conditions, the task is poorly designed, not the people doing it. There are a few pillars that show up constantly:
- Work as imagined versus work as done — Procedure manuals describe one thing. Real clinical work describes another. The gap between them is where incidents live.
- Near-miss reporting — Serious events are rare. Almost-events are common. If you only study the rare events you get a distorted picture. Near-miss data is noisy but far more informative per dollar spent.
- Latent conditions — Organizational decisions made months or years earlier, like staffing ratios, procurement choices, or layout changes, sit dormant until they combine with an active trigger. The latent condition is usually invisible to anyone looking at the event in isolation.
- Resilience engineering — Not just preventing failure, but understanding how staff actually adapt to keep things running when the standard procedures break down. Those adaptations are data, not deviance.
Most healthcare organizations treat these as separate programs. They shouldn't be. A near-miss report about a look-alike drug label means nothing unless you also know what the staffing pattern was that day and whether the pharmacy technicians had recently adapted their verification routine because the barcode scanner was slow. Connected, those three data points tell a story. Alone, they're anecdotes. I've watched too many hospitals hire consultants, run a series of workshops, produce a binder nobody reads, and call it human factors. That's not human factors. That's compliance theater. Here's what actually moves the needle. First, pick one high-volume, medium-severity process and study it without touching it. Shadow the work for a full shift. Don't interview anyone yet. Just watch. Write down every interruption, every work-around, every time someone says "I usually just skip this part because..." and every moment where a tool fights the person using it. You'll collect more signal in four hours of direct observation than in six focus groups.
Get the Full Details
Second, map the actual workflow, not the published one. I use a simple swim-lane diagram: patient flow across the top, roles across the side, and decision points marked as diamonds. You'll immediately see where handoffs create information loss. In my experience, the handoff between discharge planning and pharmacy reconciliation is where the most preventable harm hides. It's also the handoff everyone thinks they've already solved. Third, triangulate. Take your observation notes, run them against near-miss reports from the same department over the previous twelve months, and overlay them with staffing and layout data. Patterns emerge that single-source analysis never shows. One hospital I worked with found that fall events in a specific wing spiked every Tuesday between 2 and 4 PM. The initial conclusion was patient condition. The real cause was that physical therapy rounds for that unit ended at 1:45, leaving patients alone and unsupervised during a window when several were on new diuretics. Fixing the therapy schedule reduced falls by sixty-three percent. No new equipment. No new policy. Here's the part people resist: you have to measure the design, not the person. That means tracking metrics like time-to-completion for routine tasks, error rates at specific handoff points, and cognitive load proxies like interruption frequency per hour. It also means accepting that your first hypothesis will probably be wrong. In my experience, the obvious explanation accounts for maybe thirty percent of incidents. The rest lives in the interaction between schedule pressure, tool friction, and unclear accountability.
Counter-Intuitive Things That Take Years To Learn
One thing that consistently surprises people is that adding more safeguards often increases risk. This is the paradox of defensive design. Every checklist item, every confirmation prompt, every redundant signature creates cognitive overhead. When the overhead gets high enough, people start skipping steps mechanically, which means the safeguards exist on paper but not in practice. I once audited a pre-operative timeout process that had grown to seventeen verification points over five years. The average timeout took nine minutes. Surgeons were reading through the list aloud without looking at the patient. We cut it to five essential items and the compliance rate went up while the actual safety margin improved. Fewer steps, better attention. Another one: alarm fatigue isn't a behavior problem. It's a signal-to-noise ratio problem. I've seen units replace "education campaigns" about alarm response with actual engineering fixes — adjusting threshold values to match patient acuity, silencing non-critical alarms during specific care windows, and standardizing alarm tones across device families. The behavioral interventions had almost no measurable effect. The engineering changes reduced nuisance alarms by roughly seventy percent within six weeks. The third counter-intuitive finding is that high-reliability organizations aren't the ones with the fewest errors. They're the ones where errors surface quickly and get analyzed honestly. If your incident reporting rate is low, that's usually a sign that people aren't reporting, not that nothing is happening. I once joined a facility where the annual reportable events numbered in the single digits across ten thousand inpatient days. The real number, estimated from near-miss patterns and workflow analysis, was closer to two hundred. The gap wasn't data quality. It was culture.
When Human Factors Analysis Actually Fails
I need to be blunt about the limits, because I've seen practitioners treat this framework as a universal key. It isn't. Human factors analysis breaks down in situations where the root cause is genuinely bad faith — intentional sabotage, fraud, or deliberate policy violation. No amount of workflow redesign stops someone who decides to steal supplies or falsify records. You need security and compliance systems for that, not ergonomic interventions. It also struggles when organizational priorities are fundamentally misaligned. If leadership signals that throughput matters more than safety, no amount of human factors work will change outcomes. I've sat in meetings where the safety team presented findings that would require hiring additional staff or reducing patient volume. The recommendation was filed under "future consideration" and nothing changed. The problem wasn't the analysis. It was the budget conversation that followed.

A third limitation is speed. Human factors investigations take time. A proper workflow analysis for a single clinical process, done thoroughly, usually runs four to eight weeks from observation to final report. If you need answers tomorrow, you're looking at a root cause analysis, which is faster but shallower. Neither replaces the other. They serve different purposes. When human factors analysis hits these walls, the practical alternative is to combine it with process engineering and resource allocation changes. Sometimes the right answer isn't better design, it's more staffing. Sometimes it's removing a step entirely. Sometimes it's admitting that a particular workflow is impossible under current constraints and escalating past the department level.
A Practical Framework You Can Use Next Week
Here's something concrete. I use a modified version of the Swiss Cheese Model combined with a simple failure mode and effects analysis. It takes about three hours to apply to any single process. Start by listing every step in the process, from trigger to completion. For each step, ask: what could go wrong here? Not what has gone wrong. What could. This forces you to think beyond past incidents. Then rank each failure mode by severity and likelihood using a simple high-medium-low scale. Don't overcomplicate the scoring. The goal is prioritization, not precision. Next, identify the existing defenses for each failure mode. Is there a check? A warning? A double-verification? A physical constraint? Rate each defense as strong, weak, or absent. This is where you'll find the most useful data. Most processes have more defenses on paper than in practice, and the gap between the two is your intervention target.
Finally, propose changes ranked by effort and impact. I prefer changes that reduce reliance on human vigilance. A barcode scan that blocks administration until the match is confirmed is better than a reminder sticker on the pump. A standardized tray layout that makes missing instruments visually obvious is better than a checklist item. Design choices that make the right action the easy action consistently outperform training-based interventions over time.

Human Factors In Healthcare And Patient Safety: The Part Nobody Wants To Hear
The honest takeaway is that this work doesn't produce quick wins. It produces slower, steadier improvements that accumulate. A well-run human factors program in a mid-size hospital will prevent maybe two to five serious incidents per year across the entire organization. That sounds small until you multiply it across dozens of hospitals and realize how many of those prevented incidents involve people you know. The method requires patience, access to real data, and the willingness to criticize systems without blaming individuals. It also requires admitting that some problems can't be designed away and need structural solutions instead. If you're looking for a toolkit that makes you feel proactive without committing to the long work, this isn't it. If you're looking for a way to actually reduce harm, it's one of the few approaches that has a track record of doing exactly that. I've been doing this long enough to stop expecting elegant solutions. The work is mostly boring. It's watching people work, noticing where they struggle, and making small adjustments that compound. The IV pump alarm story from the beginning didn't get fixed with a memo. It got fixed because someone traced the problem through three departments, two vendors, and a scheduling mismatch before landing on a tone standardization policy that affected twenty-three different device models across four floors. That's the job. Slow, connected, unglamorous, and occasionally the difference between a near-miss and a reportable event.


