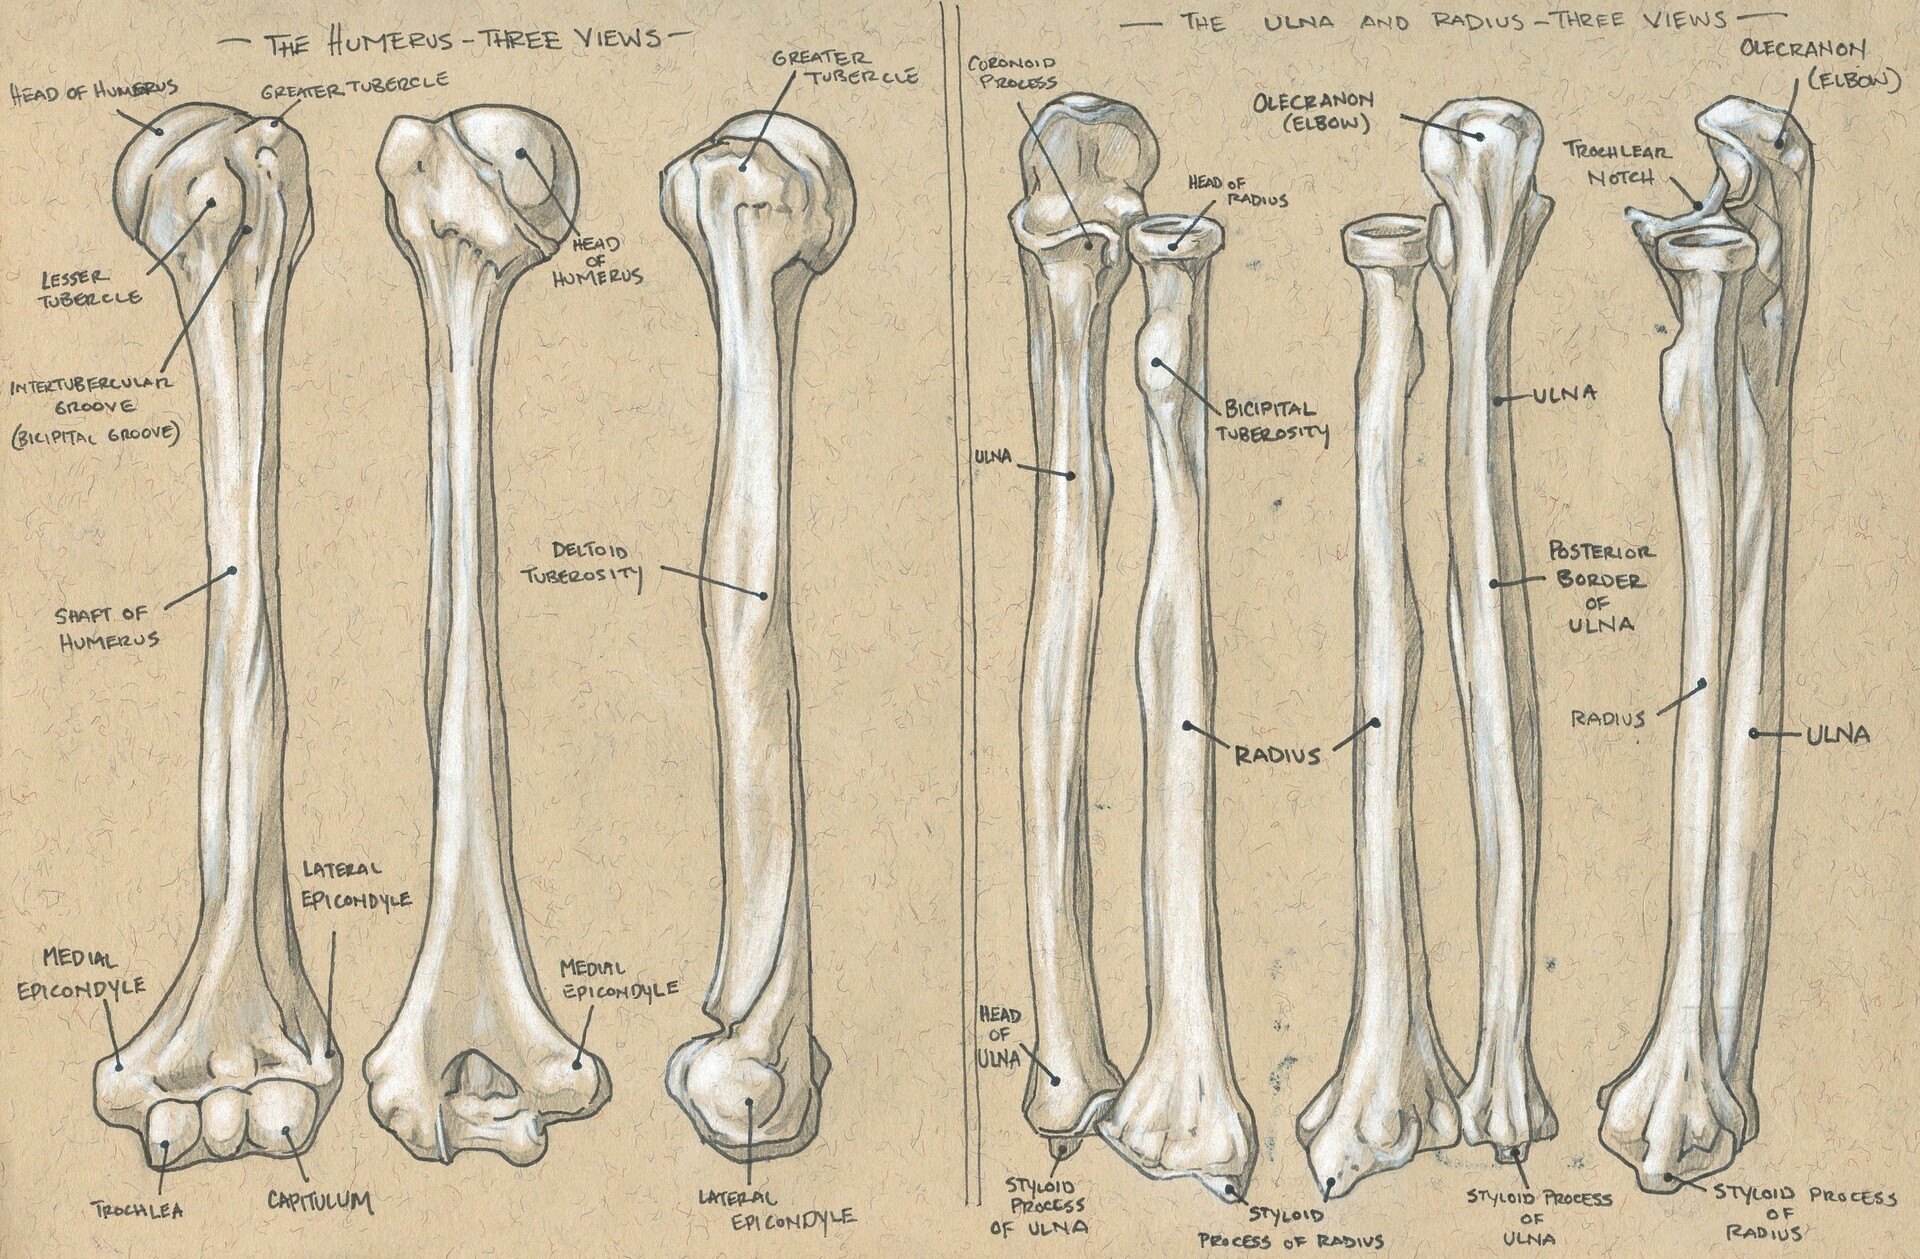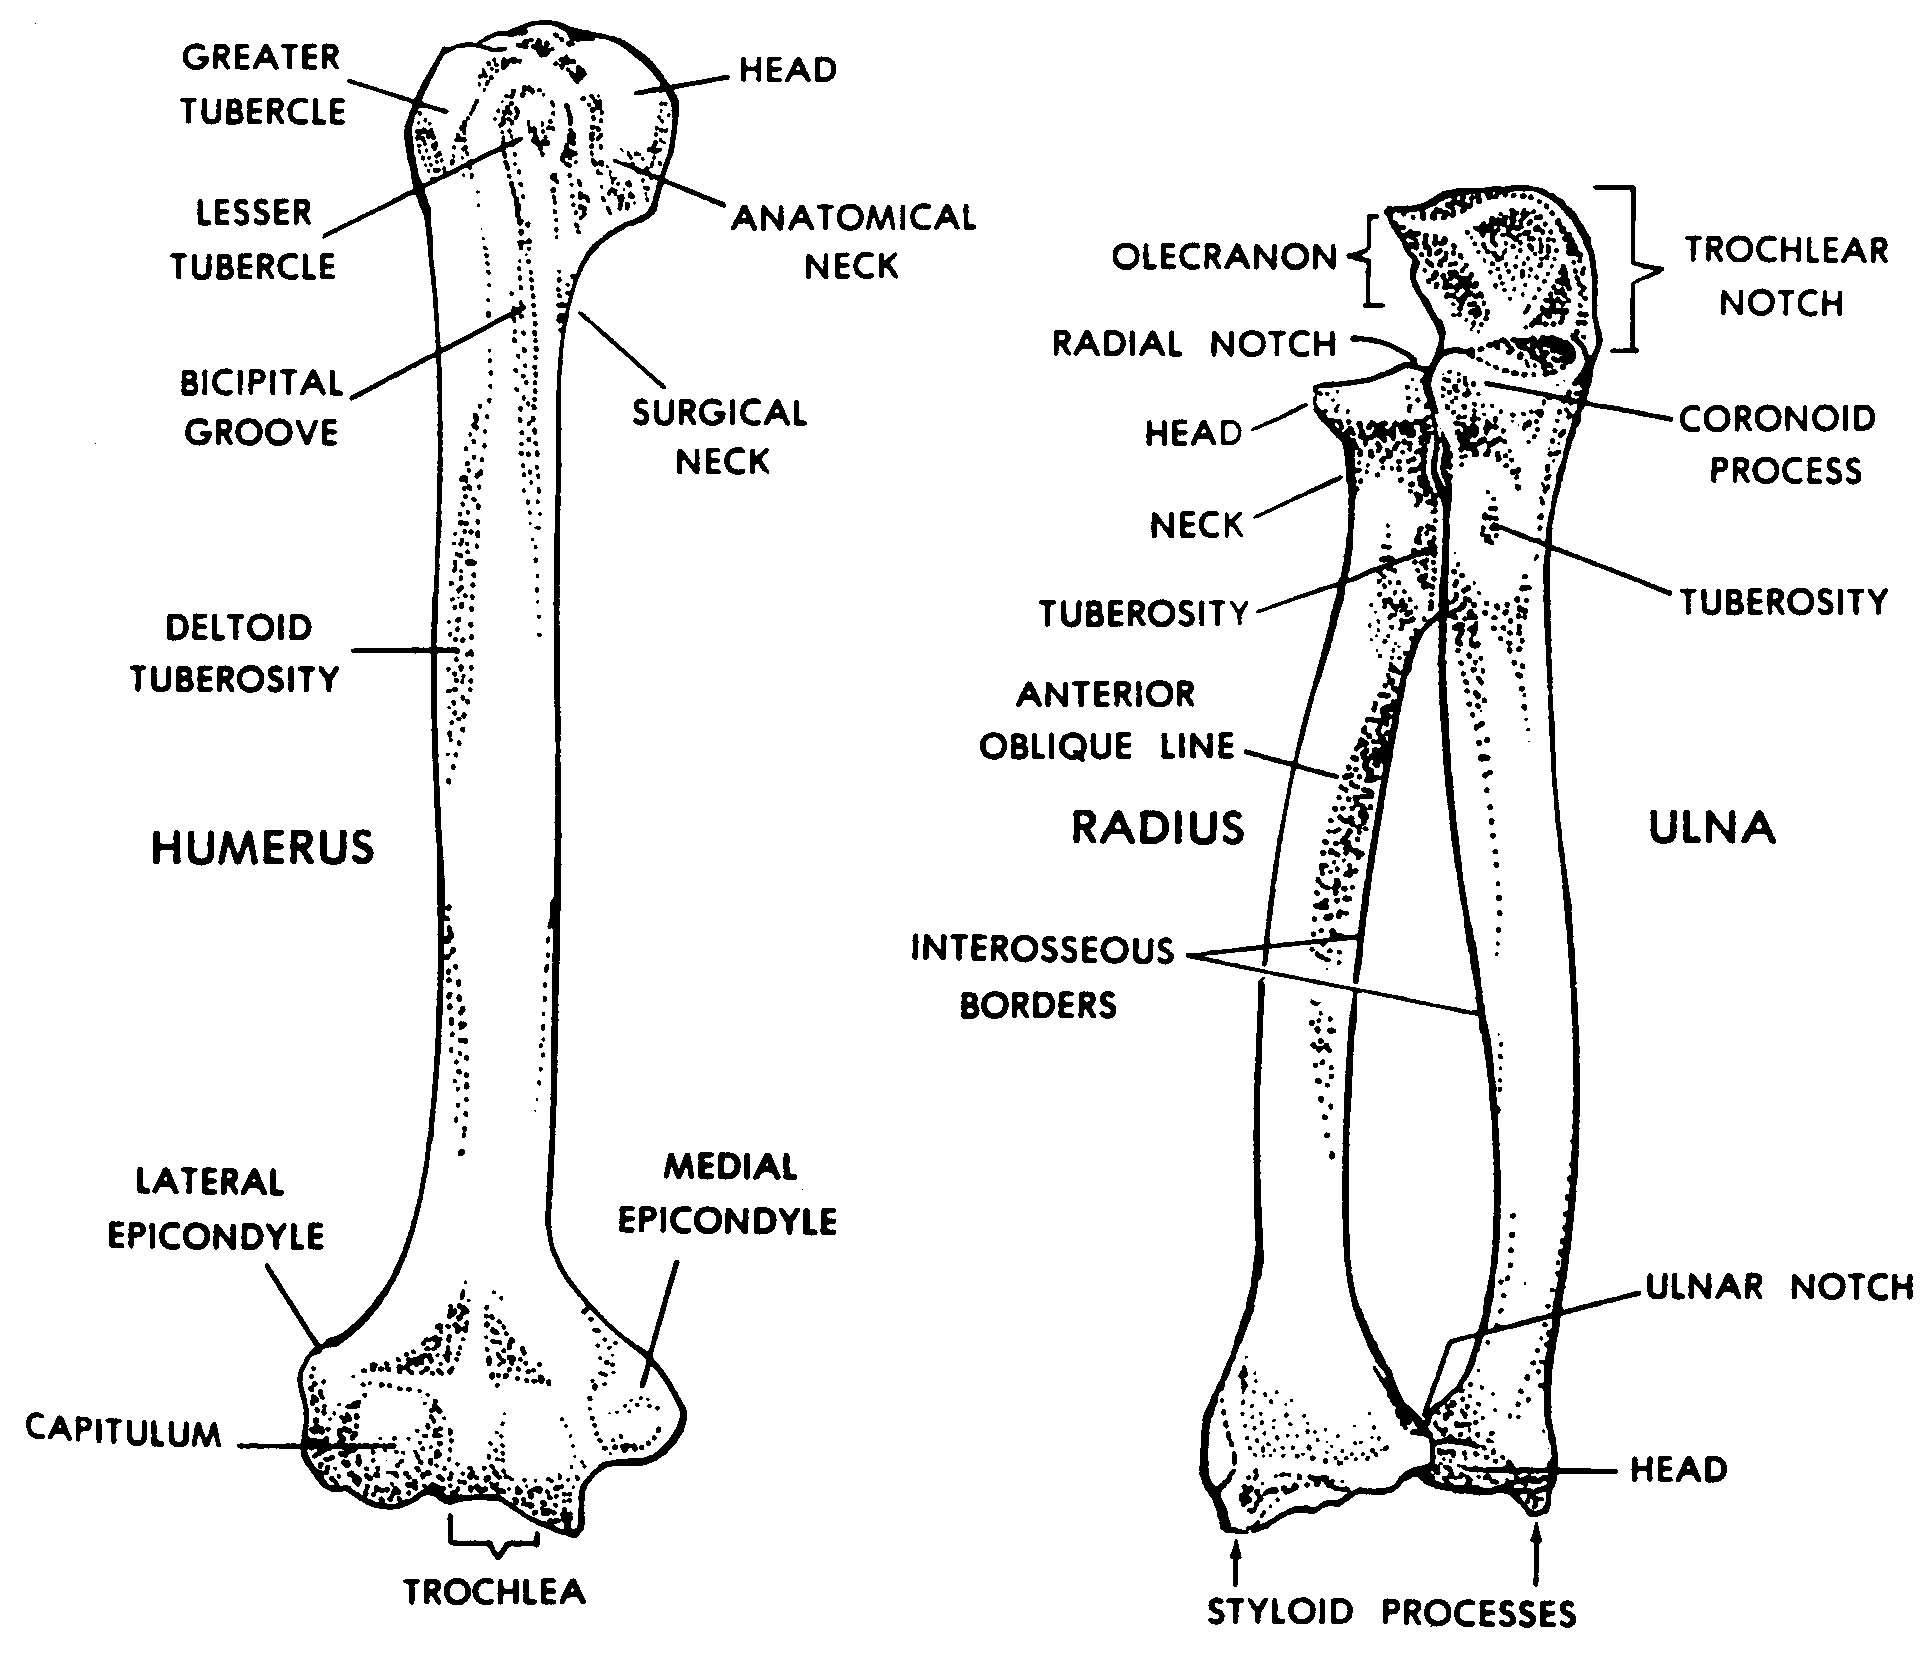
Understanding the Humerus, Radius, and Ulna: What Actually Matters
The humerus is the long bone of the upper arm. It runs from the shoulder joint down to the elbow. The radius and ulna are the two bones in the forearm. They sit side by side from the elbow to the wrist. That is the basic breakdown most anatomy textbooks give you. But if you are trying to actually understand how these bones work together - or if you are dealing with fractures, surgical planning, or imaging interpretation - the textbook stuff falls apart pretty quickly. When I first started reading radiographs and talking to orthopedic surgeons, I thought I had this down cold. Then I saw a Case 22 from 2019 - Monteggia fracture variant where the radial head dislocated but the ulnar fracture was a hairline crack running obliquely at a weird angle. The initial read missed it entirely because everyone was looking at the wrong spot. This happens more often than you would think, especially when the humerus fractures are also involved and you have multiple injury sites to sort through. The humerus itself has some nuances that are easy to miss. The surgical neck - that's the area just below the greater tuberosity - is the most commonly fractured part of the humerus in adults. But the shaft itself is also a frequent fracture site, and those carry risk to the radial nerve because the nerve wraps right around the posterior aspect of the humeral shaft. If you are reading X-rays or CT scans and you see a mid-shaft humerus fracture, you need to be checking for radial nerve involvement. Patients with radial nerve palsy from humerus fractures often present with wrist drop and inability to extend their fingers. That is a real clinical problem, not just a textbook fact.
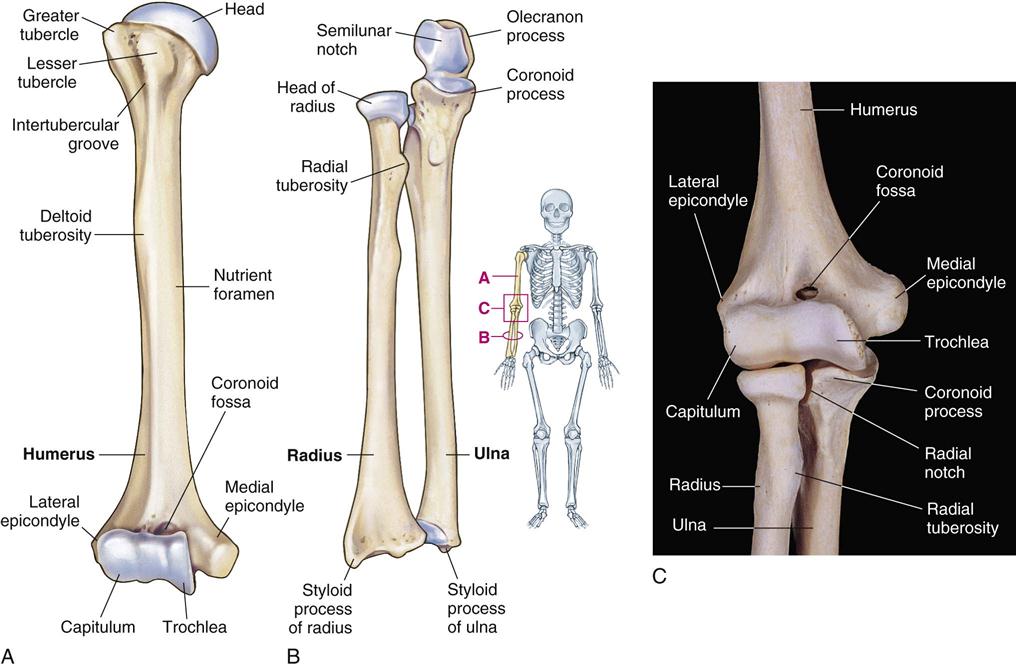
Then there is the elbow joint itself, which is where all three bones meet up in a complicated arrangement. The humerus articulates with both the radius and ulna, but not in a simple hinge. The capitulum of the humerus connects with the head of the radius. The trochlea of the humerus connects with the trochlear notch of the ulna. This dual articulation is what allows both flexion-extension and pronation-supination. But it also means that intra-articular fractures around the distal humerus are notoriously difficult to manage surgically. Getting the joint surface perfectly reduced matters enormously because any step-off of even a couple millimeters leads to post-traumatic arthritis down the line. I worked with a trauma team once where they were debating between an open reduction internal fixation versus a total elbow arthroplasty for a comminuted distal humerus fracture in an elderly patient. The ORIF was technically feasible but would have required multiple plates and screws with a high risk of hardware irritation later. The arthroplasty route meant losing some range of motion but gave the patient a predictable functional outcome much faster. They went with the arthroplasty. That decision would have been harder without solid anatomical knowledge of how the humerus, radius, and ulna actually interact at the joint surface. The radius and ulna each have their own issues. The ulna is the simpler of the two - straighter, less mobile, and its main role is providing the hinge for elbow flexion and extension through the trochlear notch. The radial head specifically acts as a secondary stabilizer against valgus stress. When the medial collateral ligament of the elbow is compromised, the radial head takes on more importance. I have seen cases where a fractured radial head was removed thinking it was expendable, only to watch the elbow gradually develop valgus instability over the following years. That is a pitfall worth remembering.
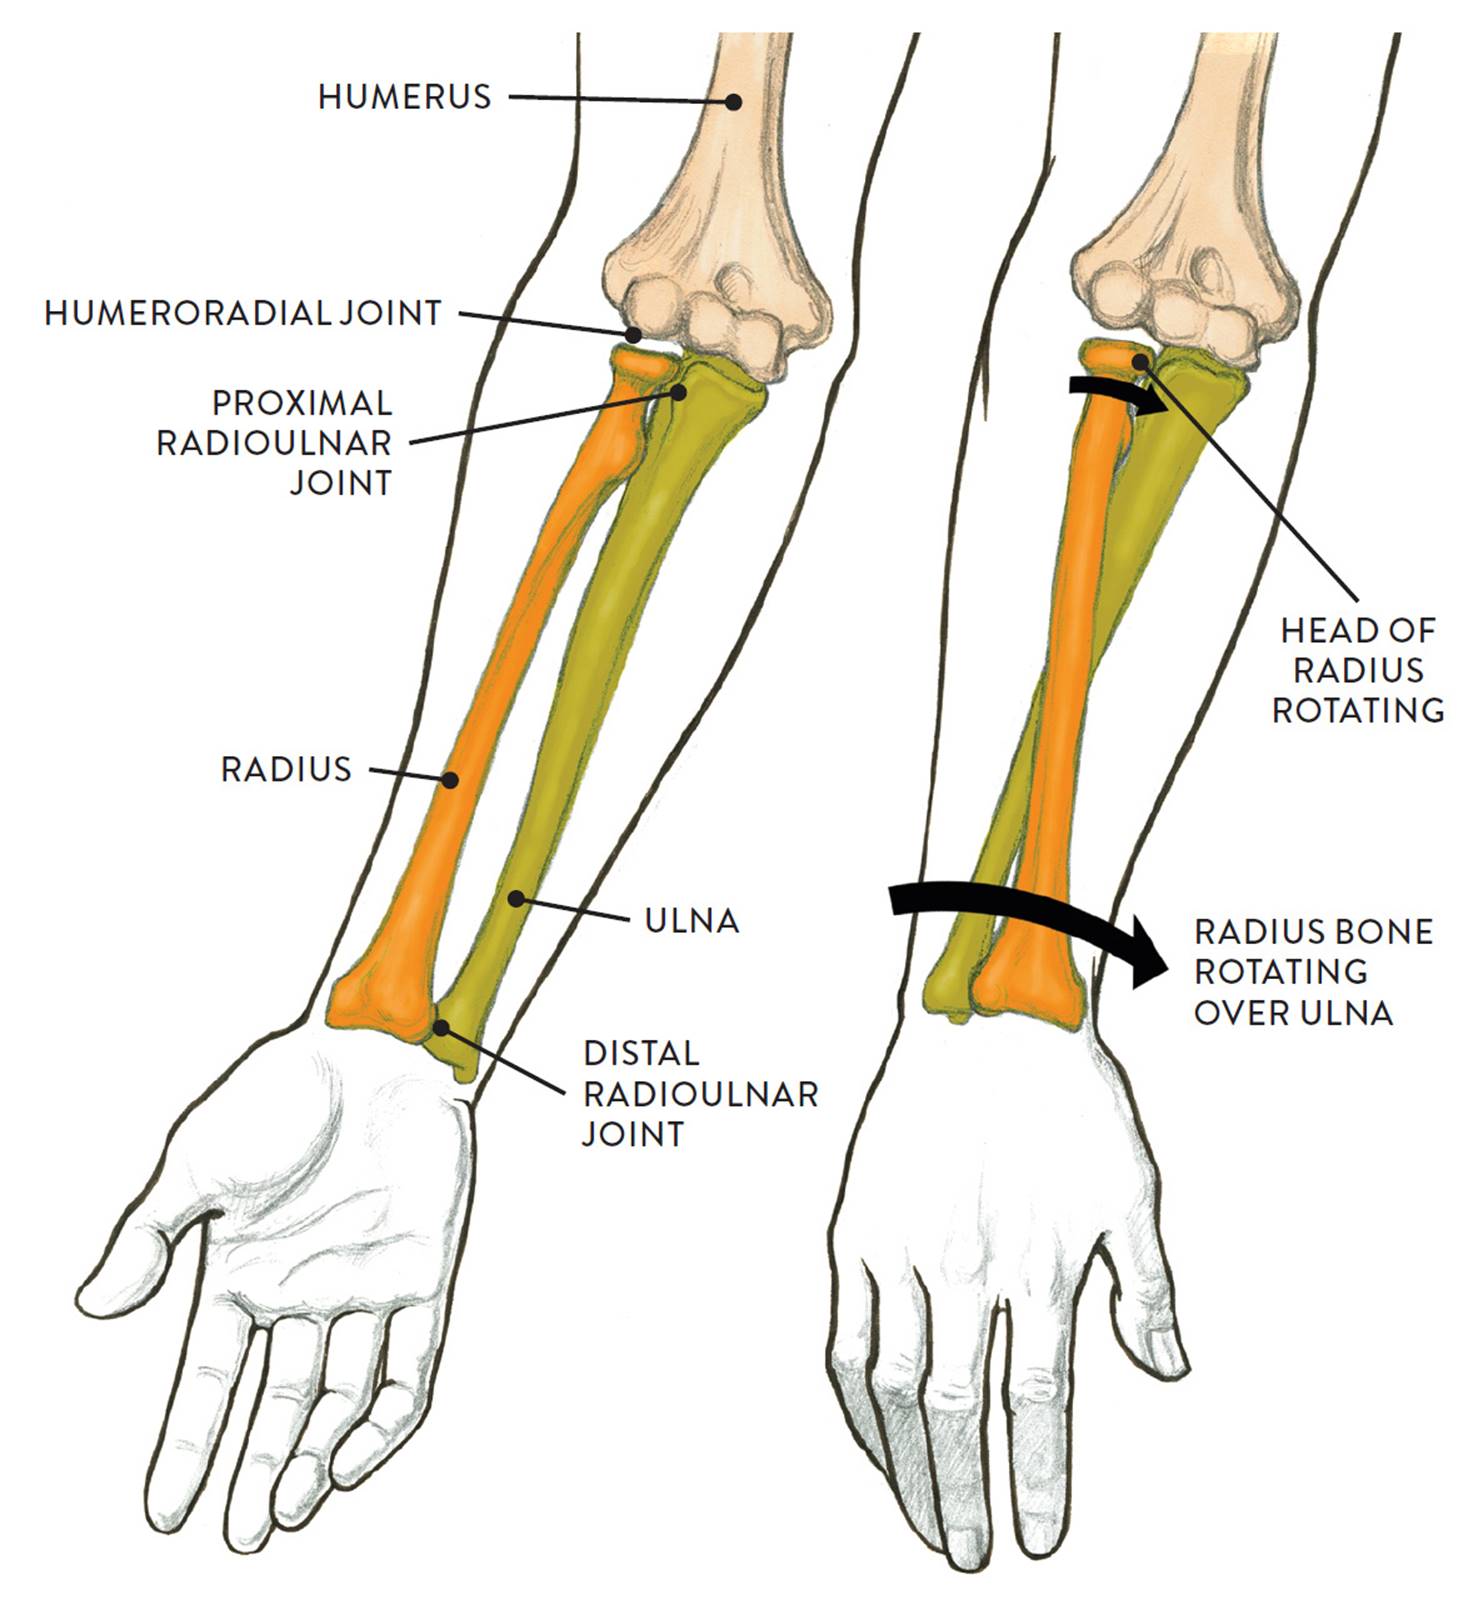
The radius is the bone that does the interesting work at the wrist and forearm rotation. Its head articulates with the capitulum of the humerus proximally, and its distal end - the articular surface - articulates with the carpal bones. The proximal radioulnar joint and the distal radioulnar joint together allow pronation and supination. The interosseous membrane connecting the two bones transfers force between them. During a fall on an outstretched hand, the impact force travels through the radius and then across that membrane to the ulna. That is why distal radius fractures (Colles fractures, Smith fractures) are so common - the radius takes the brunt of the load. One thing that catches people off guard is the relationship between the radius and ulna during forearm rotation. When you pronate and supinate, the radius actually crosses over the ulna. On a standard AP X-ray of the forearm, the two bones should appear parallel. If they are crossed or overlapped in an unexpected way, you should question whether the positioning is correct or whether there is a structural abnormality. I once spent twenty minutes puzzled by an X-ray before realizing the technologist had internally rotated the arm instead of keeping it neutral. The anatomy looked wrong not because anything was broken but because the presentation was off. When you are dealing with actual fractures involving these bones, here is what matters practically. For humerus shaft fractures, the treatment algorithm depends heavily on the fracture pattern and the patient's neurovascular status. Non-displaced fractures can often be managed conservatively with a Sarmiento brace. Displaced fractures or those with nerve involvement typically need surgical fixation. Intramedullary nailing and plating are the two main approaches. Plates tend to have lower non-union rates but require larger incisions. Nails are less invasive but have a higher risk of radial nerve irritation during insertion.
Get the Full Details
Forearm fractures in adults are different from pediatric forearm fractures in a critical way. Adults typically need surgical fixation for both-bone forearm fractures because the interosseous membrane relationship must be restored precisely to maintain forearm rotation. A malunion of even a few millimeters can significantly reduce supination and pronation range. Children, on the other hand, remodel remarkably well and many both-bone fractures heal acceptably with casting alone. This is one of those areas where applying adult protocols to pediatric cases - or vice versa - leads to bad outcomes. If you are studying this for clinical purposes, I would recommend focusing on the anatomical relationships at the elbow and wrist rather than memorizing every muscular attachment point. Understanding how the humerus, radius, and ulna move relative to each other during flexion, extension, pronation, and supination will serve you better than rote memorization. The Musculoskeletal Radiology section of Radiopaedia has decent case collections. The Orthobullets franchise is useful for quick reference on fracture management. But honestly, nothing replaces looking at actual imaging studies and correlating them with surgical notes when you can find them. The proximal humerus fracture classification system (the Neer classification) divides fractures into segments based on displacement of four parts: the humeral head, the greater tuberosity, the lesser tuberosity, and the humeral shaft. Two or more parts displaced by more than one centimeter or forty-five degrees of angulation defines a two-part fracture, and so on. This matters because three-part and four-part fractures have different blood supply implications - the humeral head gets its blood supply mainly from the anterior circumflex humeral artery, and displaced fractures can compromise that. Avascular necrosis is a real complication of proximal humerus fractures, particularly in four-part fractures where the head is essentially freed from its soft tissue attachments.
At the distal end, the radial articular surface has a natural palmar tilt of about ten to fifteen degrees and a radial inclination of roughly twenty-five degrees. When you are assessing distal radius fractures, measuring these angles on the X-ray tells you immediately whether the reduction is anatomical or not. Loss of palmar tilt means the wrist is now extended relative to normal, which changes the mechanics of the entire carpus. Ulnar variance matters too - if the radius is shortened significantly after a fracture, the ulna becomes relatively longer and that can lead to ulnar impaction syndrome later on. There is also the Essex-Lopresti injury, which is a triple injury involving the radial head, the interosseous membrane, and the distal radioulnar joint. It is easy to miss because the radial head fracture looks straightforward on the initial X-ray. But if you do not also evaluate the distal radioulnar joint and assess for disruption of the interosseous membrane, you will miss the longitudinal instability that defines this injury. The classic presentation is radial head fracture plus wrist pain distally. Patients often complain that their wrist hurts after what they thought was just an elbow injury. MRI or CT arthrography can help confirm the diagnosis if you suspect it, but sometimes you need to maintain a high index of suspicion from the start. For anyone preparing for practical exams or clinical rotations, the key insight is that these three bones do not function in isolation. The humerus sets the stage for elbow motion. The radius and ulna together create forearm rotation and wrist mechanics. Disruption at any level affects the entire kinetic chain. A poorly healed humerus fracture can alter elbow biomechanics enough to cause secondary problems at the wrist. A malunited radius can throw off the entire pronation-supination cycle. The takeaway is to always evaluate the full limb, not just the obvious injury site.