Understanding the Basics
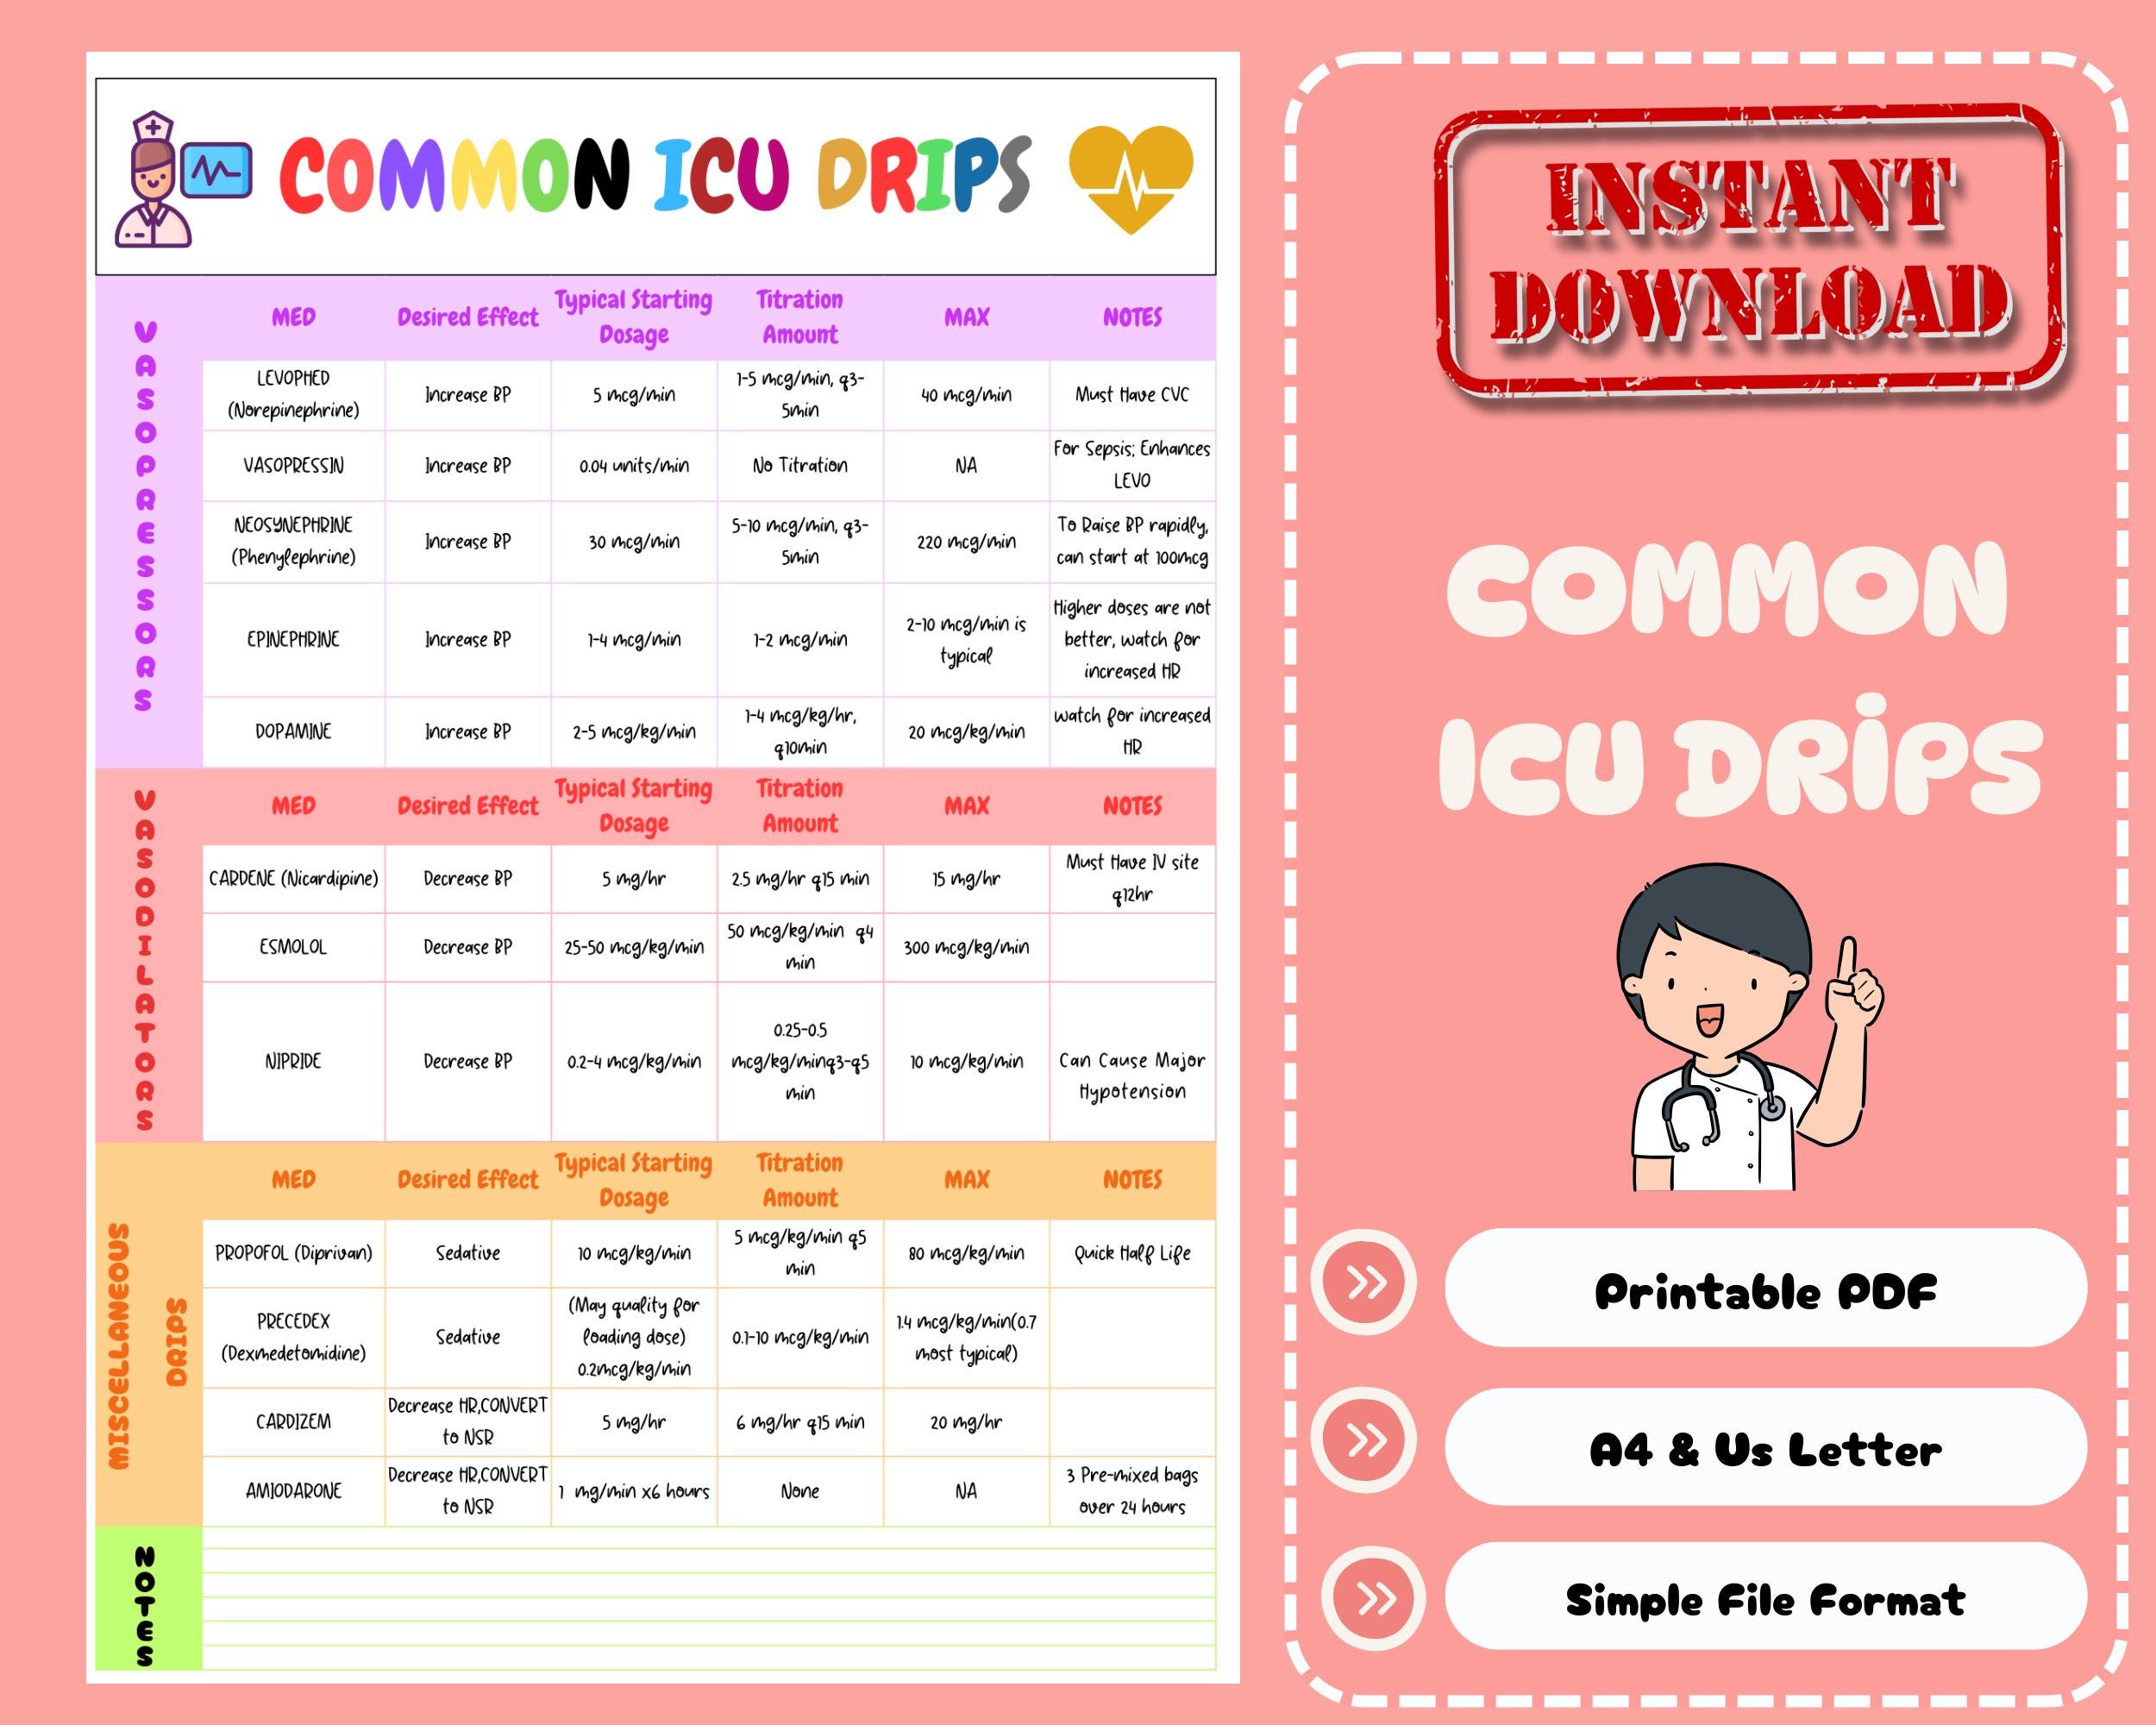
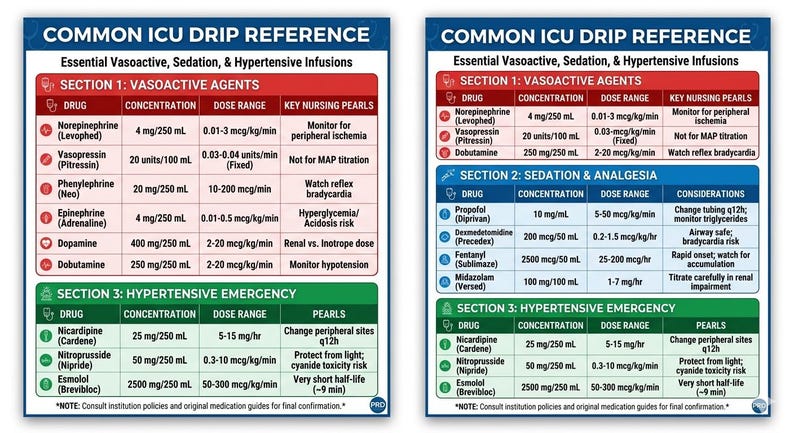
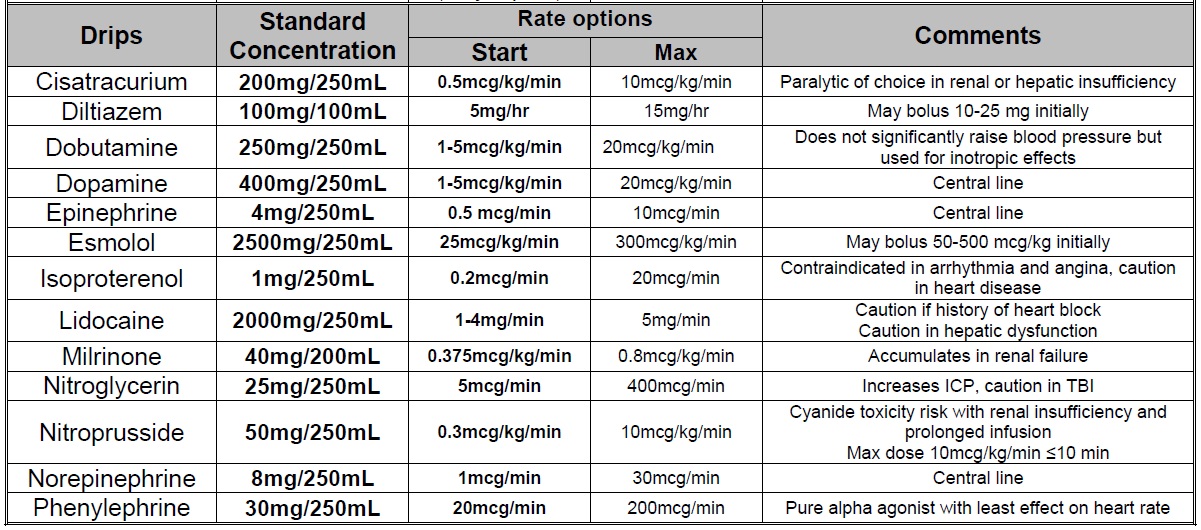
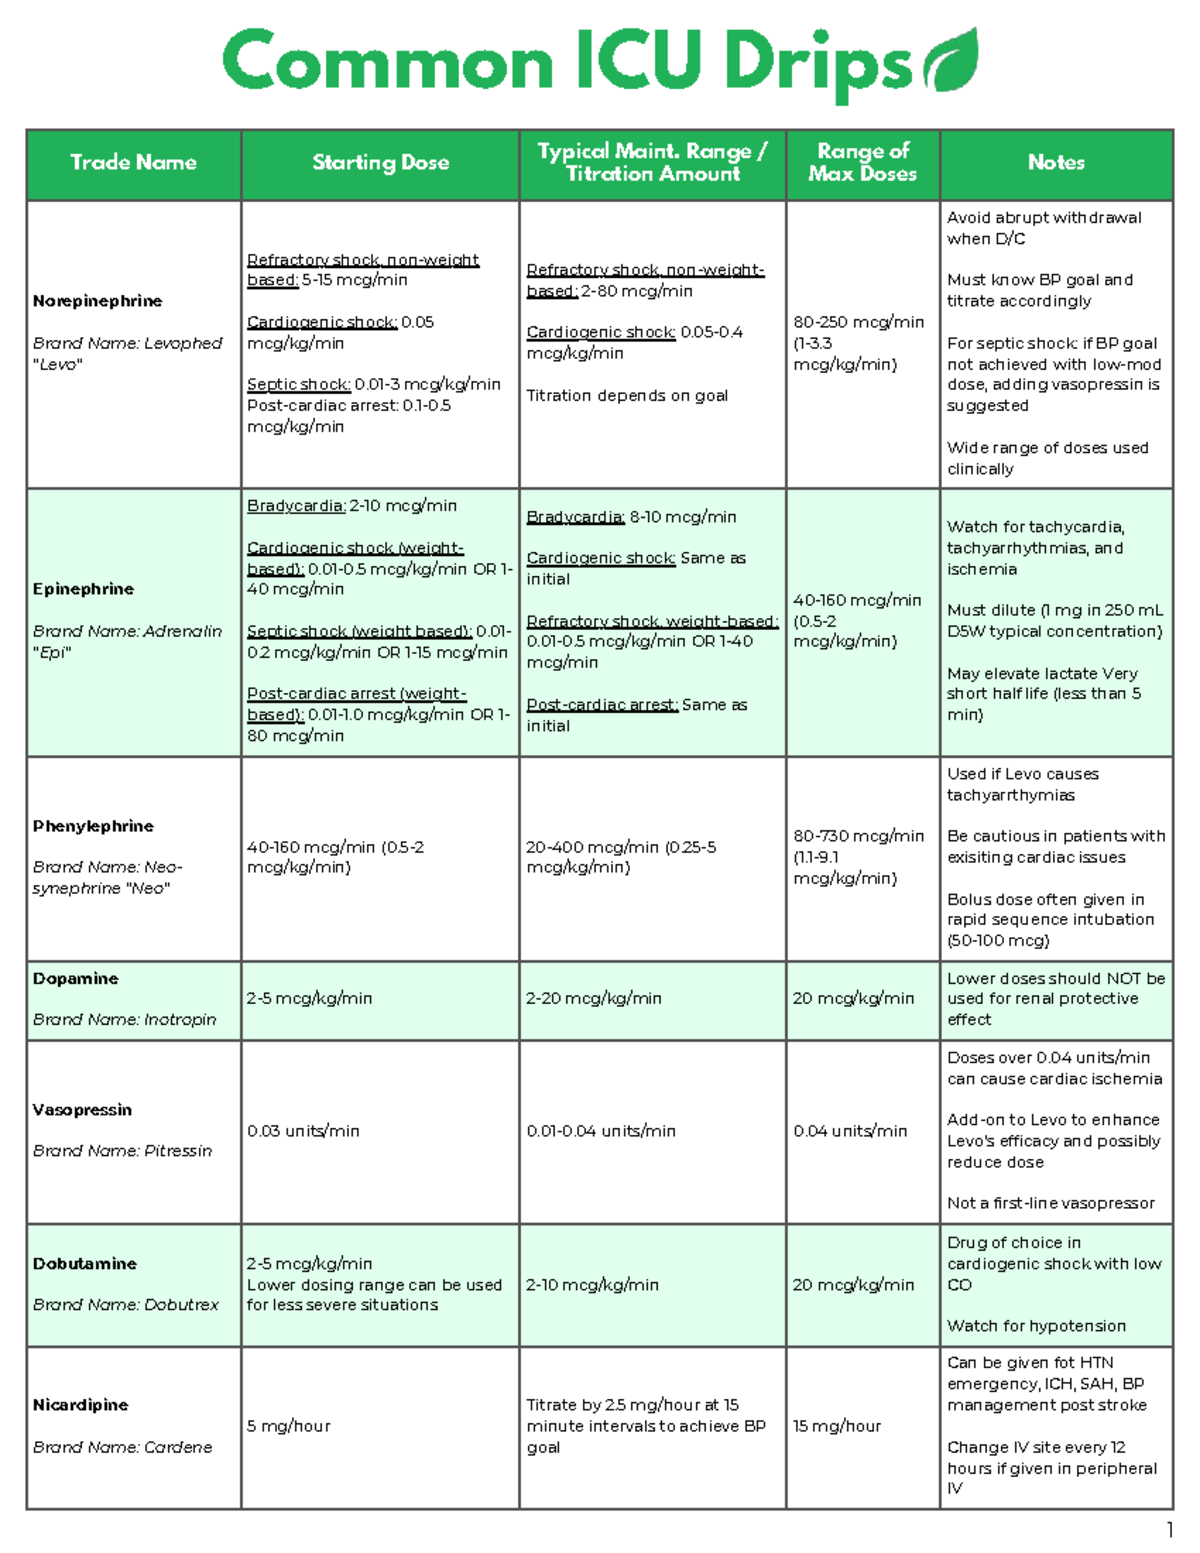
An ICU drip infusion chart is a reference tool that helps nurses and providers calculate medication dosages, flow rates, and dilutions at the bedside. It typically contains pre-computed tables for common vasopressors, sedatives, antiarrhythmics, and other continuous infusions. The goal is to reduce math errors during high-stress situations when every second counts. Most pocket guides follow a similar format. You find the drug concentration on the left side, locate the patient's weight in kilograms across the top, and follow the row and column to find the milliliters per hour needed to deliver a specific dose in mcg/kg/min or mcg/min. Some guides go further and include weight bands, allowing you to quickly find the appropriate rate without calculating for a specific weight.
ICU Drip Infusion Chart Pocket Guide
I've carried folded laminated charts in my scrub pocket for years. They're not glamorous, but they've saved me more times than I can count. There's nothing worse than pulling up a dose on the pump while a patient's blood pressure is dropping and you're second-guessing your calculation. The chart removes that hesitation. Here's how most people use it. Let's say you're starting norepinephrine on a 82-kilogram patient. Your order is 0.1 mcg/kg/min. You locate the norepinephrine section, find the concentration you have on hand (let's say 4 mg in 250 mL D5W), then cross-reference with the patient's weight. The chart tells you the flow rate in mL/hr directly. You program the pump and move on.
Weight Band Tables vs. Specific Weight Charts
There are two main approaches. Weight band tables assign patients to narrow weight ranges. A chart might say anyone between 70 and 80 kg on norepinephrine at 0.1 mcg/kg/min gets 6 mL/hr. The advantage is speed. You don't need an exact weight. The disadvantage is slight dosing imprecision. For most vasopressors, that difference between 0.09 and 0.11 mcg/kg/min won't matter clinically. For drugs with narrow therapeutic windows like nicardipine or propofol for sedation, it might. Specific weight charts require the exact kilogram weight but give you the precise rate. Many ICUs prefer this for titratable drips where small changes matter. The tradeoff is that you need the weight on hand. Guessing or rounding leads to errors. I always verify the weight at the time of the order, not from admission days ago.
Get the Full Details
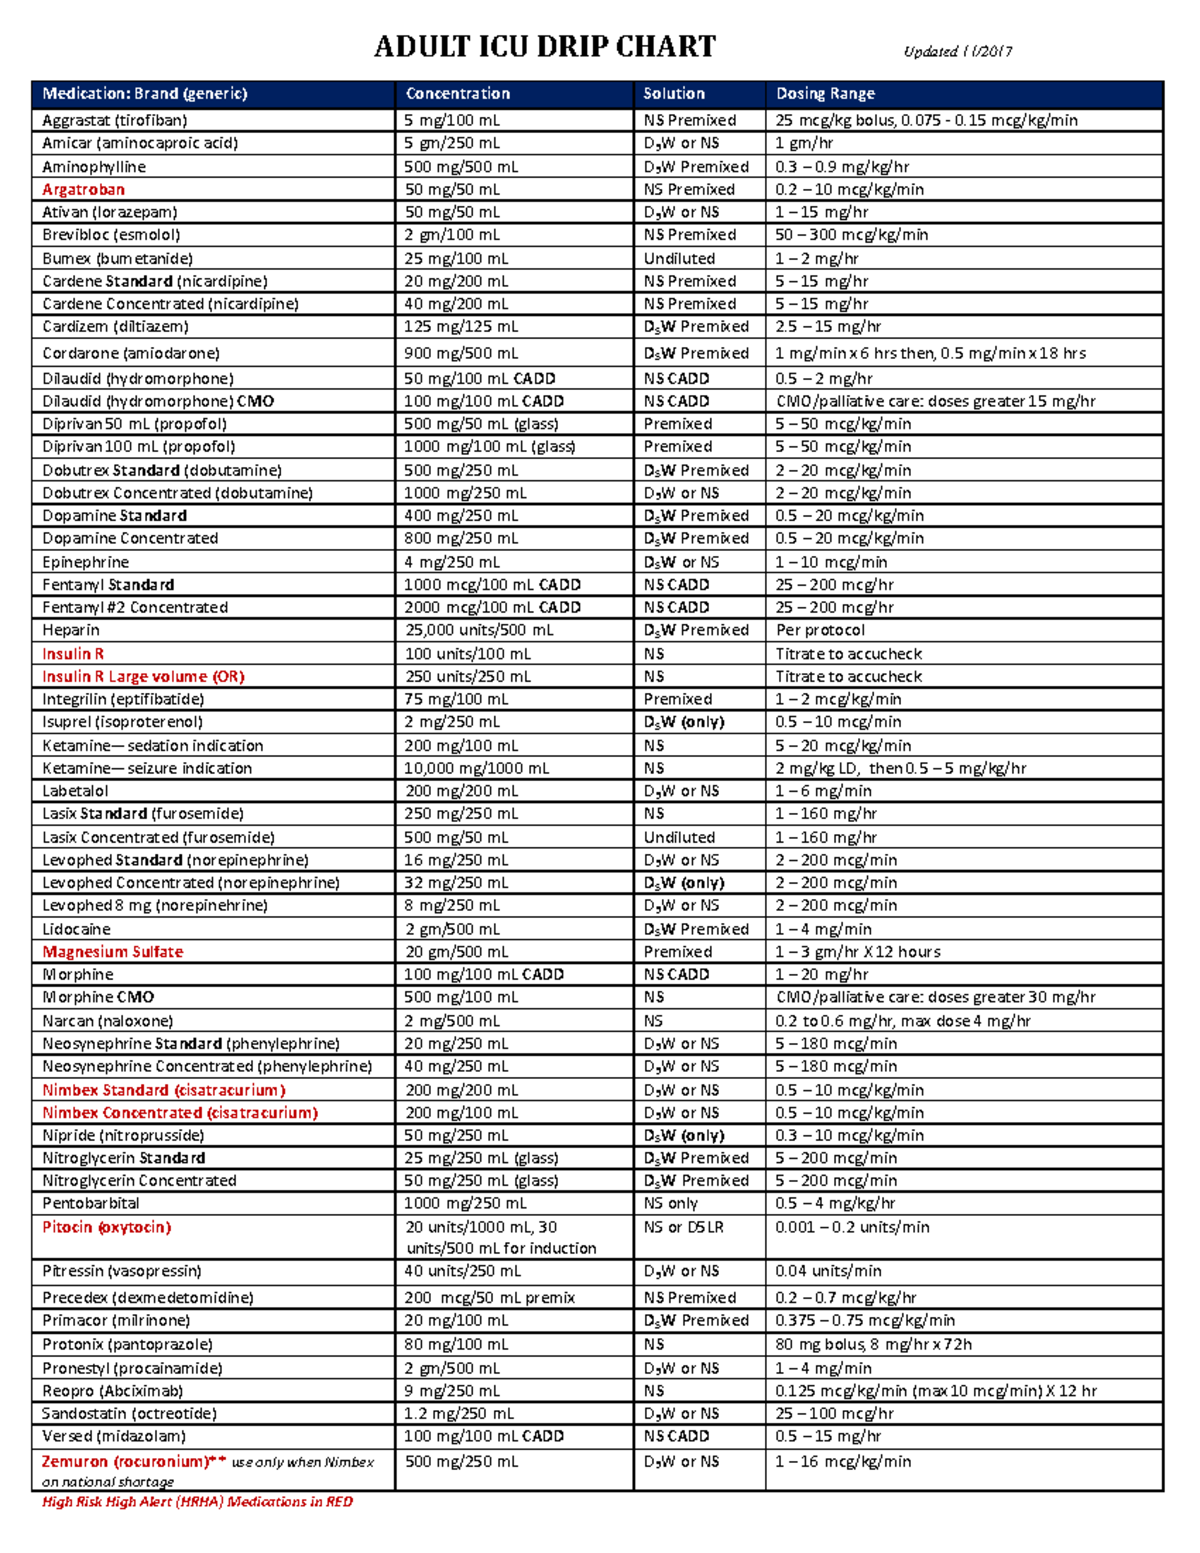
A Problem I Faced and How I Worked Around It
One night, I was running a nitroglycerin drip for a patient with hypertensive emergency. The order was 50 mcg/min. The chart I had was organized by mcg/kg/min, not absolute mcg/min. I'm 38 weeks pregnant with a toddler at home and still working double shifts, so I wasn't thinking clearly. I grabbed the nearest weight band, did a manual conversion, and set the pump. Ten minutes later, a colleague checked my work and caught that I'd used the wrong concentration bracket. The bag was 50 mg in 250 mL, not the 100 mg I had initially assumed because the label was partially obscured by tape from another nurse's notes. Since that incident, I developed a personal checklist before programming any pump. First, verify the bag concentration printed on the label. Second, confirm whether the chart uses weight-based or absolute dosing for that drug. Third, restate the final mL/hr calculation out loud to myself. It takes twelve seconds and has prevented at least three near-misses since. I also switched to keeping a dedicated pen and never writing over or around existing labels on infusion bags.
What the Charts Get Wrong
No pocket guide is perfect. Most assume standard IV bag sizes and concentrations. If your pharmacy prepares custom dilutions, the chart becomes useless unless it has a section for compounded concentrations. I've seen charts that don't account for actual available vial sizes, leading to situations where the calculated concentration doesn't exist in practice. Another gap is drug stability information. A chart might tell you the flow rate for dopamine but won't warn you that your prepared bag has been running for 24 hours beyond its stability window. Always check the pharmacy label for expiration after compounding. The chart doesn't substitute for that. Pediatric dosing is another area where most adult-focused guides fall short. If your unit treats children, you need a separate pediatric reference. Adult charts applied to a 15-kilogram child will grossly overdose them. I've seen units where the same laminated card sits on every pump station, and residents pull it out for pediatric cases without realizing it's only validated for adults over 50 kg.
Practical Tips That Actually Help
Keep the chart laminated and hole-punched so it attaches to your badge or clipboard. Folded paper gets wet, greasy, and illegible within a week. I use a small binder clip to hold mine to my uniform. It's always there when I need it. Verify the chart version matches your institution's formulary. Hospital A might stock phenylephrine as 10 mg in 250 mL. Hospital B uses 20 mg in 250 mL. A chart from a different hospital will give you wrong rates. Before relying on any published guide, compare its drug concentrations against your pharmacy's standard preparations. If they don't align, annotate the chart or request a custom version from your unit's clinical pharmacist. Practice the calculation method on paper before you trust it at the bedside. Pick five common drips, five different weights, and work through each one. If you can do it in under three minutes per calculation, you're ready. If it takes longer, keep practicing. Speed matters when a patient codes.

When to Stop Using the Chart
Electronic health record integrated pump programming is replacing paper charts in many hospitals. Some systems automatically calculate the infusion rate based on the order, patient weight, and available drug concentrations. If your unit has this, use it. Double-check the displayed rate against your own mental calculation before pressing start. The EHR is correct most of the time, but not all of the time. I've seen order entry errors propagate into pump settings without any manual verification step. When electronic systems are unavailable, such as during power failures or in resource-limited settings, the paper chart is your safety net. That's when having a reliable reference matters most. I've worked nights where the pumps went offline and we were running gravity drips with manual flow regulation. The chart let us calculate rates fast enough to keep patients stable until backup power restored the infusion pumps.
Where to Find One
Many nursing schools and critical care societies distribute free pocket guides. Check with your hospital's education department or unit manager. Some pharmacies print institutional versions with locally relevant concentrations. If you need a general reference, search for "critical care infusion pocket reference" or "vasopressor calculation guide" from reputable nursing publishers. Avoid random downloads from unverified websites. Outdated drug concentrations in a downloaded PDF can be dangerous. The best chart is the one you actually carry and use. A fancy reference sitting on a desk does nothing for a patient. Keep yours accessible, keep it current, and keep practicing the math even when the chart makes it easy.