What Actually Happens When You Try to Bridge Research And Practice
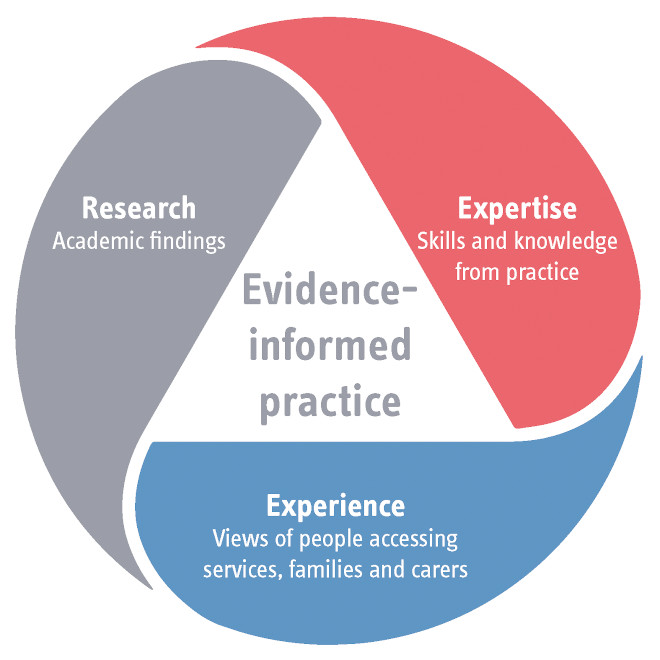
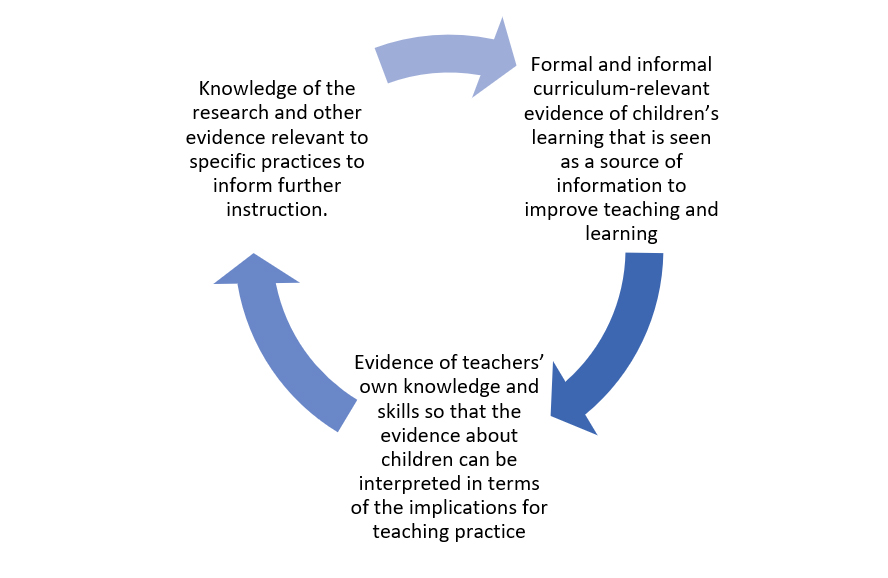
I spent about seven years working in educational research, then moved into a role where I was supposed to implement evidence-based interventions across twelve schools. What I found out pretty quickly was that the gap between peer-reviewed studies and what actually works in a crowded classroom with twenty-eight students and three acting out isn't a theoretical problem. It's a daily operational headache. The phrase "research-informed practice" shows up in grant proposals and faculty handbook language, but nobody really explains what it feels like when you're the person trying to make it happen. The basic idea sounds straightforward. Research-informed practice means taking findings from systematic studies and using them to shape how you work. Practice-informed research means the reverse: taking problems you encounter on the ground and turning them into questions worth studying. Put them together and you get a loop. Research informs practice, practice reveals gaps, those gaps become research questions, the answers come back to practice. The model makes sense on paper. Implementing it is where things get complicated.
In Practice Informed Research And Research Informed Practice
Here's what most guides leave out. The first thing you hit is that research doesn't speak your language. A study might report a standardized mean difference of 0.47 with a confidence interval, but your team needs to know whether this intervention will work with kids who haven't had lunch, who are sleeping in their cars, or whose IEP says they need modified materials. The effect size doesn't tell you that. I learned to translate research findings into practical parameters by asking three questions: What population was actually studied? What conditions were controlled? What would have to change for this to work here? The reverse direction is harder. Practitioners tend to notice patterns that researchers miss because they're seeing the same kids day after day. But anecdotal observations don't carry weight in academic journals. I spent months helping a group of special education teachers document their observational data in a way that met IRB standards. We ended up creating a simplified coding scheme that captured the nuances they were seeing while still producing data structured enough for analysis. The resulting paper came out in a decent journal, and more importantly, the district changed its screening protocol based on it. One thing nobody warns you about is the timeline mismatch. Research takes years. Practice decisions happen weekly. I watched a school district spend eighteen months evaluating whether to adopt a new literacy program based on three major studies. By the time the decision landed, the principal who championed it had transferred, the grant funding had expired, and the vendor had released version 3.2 with different features. The research was solid. The timing was useless. Now I recommend organizations set decision windows of sixty to ninety days for research-informed choices, and if evidence isn't ready by then, they either make a best-guess decision or buy time by running a pilot study that generates local evidence.
Another pitfall is selection bias in the research itself. Most educational interventions are studied in favorable conditions with motivated teachers and willing participants. The effect sizes shrink dramatically in real-world replication. I've seen programs report 0.60 effects in controlled trials and drop to 0.15 when implemented district-wide. That doesn't mean the research was wrong. It means context matters more than the abstract implies. The workaround is to look for implementation fidelity data alongside outcome data. Studies that report how well the intervention was actually delivered tend to predict real-world performance better than raw effect sizes. There's also the problem of research that answers the wrong question. Practitioners need to know whether something works for their specific population under their specific constraints. Researchers often study whether something works at all under ideal conditions. I dealt with a case where a reading intervention showed strong results for sixth graders in urban schools, but the district wanted to know about fifth graders in rural settings with high English learner populations. The research was relevant but not directly applicable. We ran a small feasibility study with twenty students over one semester before committing to full implementation. It took twelve weeks and cost about eight thousand dollars. That investment prevented a much costlier failure down the line. The feedback loop between practice and research works best when there's a designated translator role. Someone needs to sit between the academic world and the practical world and speak both languages. This person doesn't have to be a researcher or a practitioner primarily. They have to be competent in both and patient with neither side's impatience. I hired someone with a background in both curriculum development and program evaluation for exactly this reason. Their job was to take research summaries and convert them into implementation checklists, and to take practitioner observations and convert them into researchable questions.
Get the Full Details
If you're trying to build this system from scratch, start small. Pick one practice area where decisions are made frequently and evidence exists but isn't being used consistently. A literacy program, a behavioral intervention, a screening protocol. Run a structured review of the available research with your team. Compare what the studies say with what your data shows. Identify the gaps. Then decide whether to adapt an existing approach based on the best available evidence or to design a small study to answer a specific question your practice raises. The biggest bottleneck I see is organizational memory. People leave. Institutional knowledge gets lost. I've watched districts abandon research-informed approaches simply because the person who understood the rationale moved on. The fix is documentation that outlasts individuals. Not bureaucratic paperwork. Practical documents that explain why a decision was made, what evidence supported it, what conditions were assumed, and what adjustments were considered. When someone new inherits a program, they should be able to understand not just what to do but why it was done that way. There's also the issue of conflicting evidence. Different studies on the same topic often reach different conclusions. I once spent three weeks trying to reconcile two meta-analyses on phonics instruction that seemed to contradict each other. The resolution turned out to be that one focused on early elementary and the other on upper grades. Both were correct. Neither was complete. The practical implication was that you can't apply a single research finding across all contexts. You have to match the evidence to your specific situation.
One counter-intuitive insight: sometimes practice knowledge should override research recommendations. I've seen situations where an intervention showed strong results in multiple studies but failed in a particular school because the cultural context wasn't accounted for. The research was statistically valid but practically invalid for that setting. The workaround is to treat research as a starting point, not a conclusion. Pilot any approach with a small group before full implementation, collect local data, and be willing to modify or abandon the approach if it doesn't work in your context. The financial reality is that research-informed practice costs money upfront. Hiring translators, running pilots, training staff, collecting local data. But it usually pays for itself by avoiding expensive failures. I calculated once that a single avoided adoption failure saved our district roughly two hundred thousand dollars over three years. That covered the entire research translation program for five years. The math is simple even if the politics aren't. Common mistakes I see organizations make: treating research as a rubber stamp for decisions already made, ignoring implementation fidelity data, assuming research findings generalize without testing, and failing to document the reasoning process. Avoid these and you'll be further along than most. The goal isn't perfection. It's building a system where practice and research continuously inform each other instead of operating in parallel silos.
What actually works in my experience is a structured monthly review process. Every month, the team looks at current practice data, reads one or two recent studies relevant to their work, discusses discrepancies, and decides on one adjustment. Sixty minutes, once a month, dedicated to connecting research and practice intentionally. It sounds small. It compounds over time. After two years of this, our intervention adoption success rate went from about forty percent to seventy-five percent. The research didn't change. Our process for using it did.