What You Actually Need to Know Before Starting Intravesical Therapy
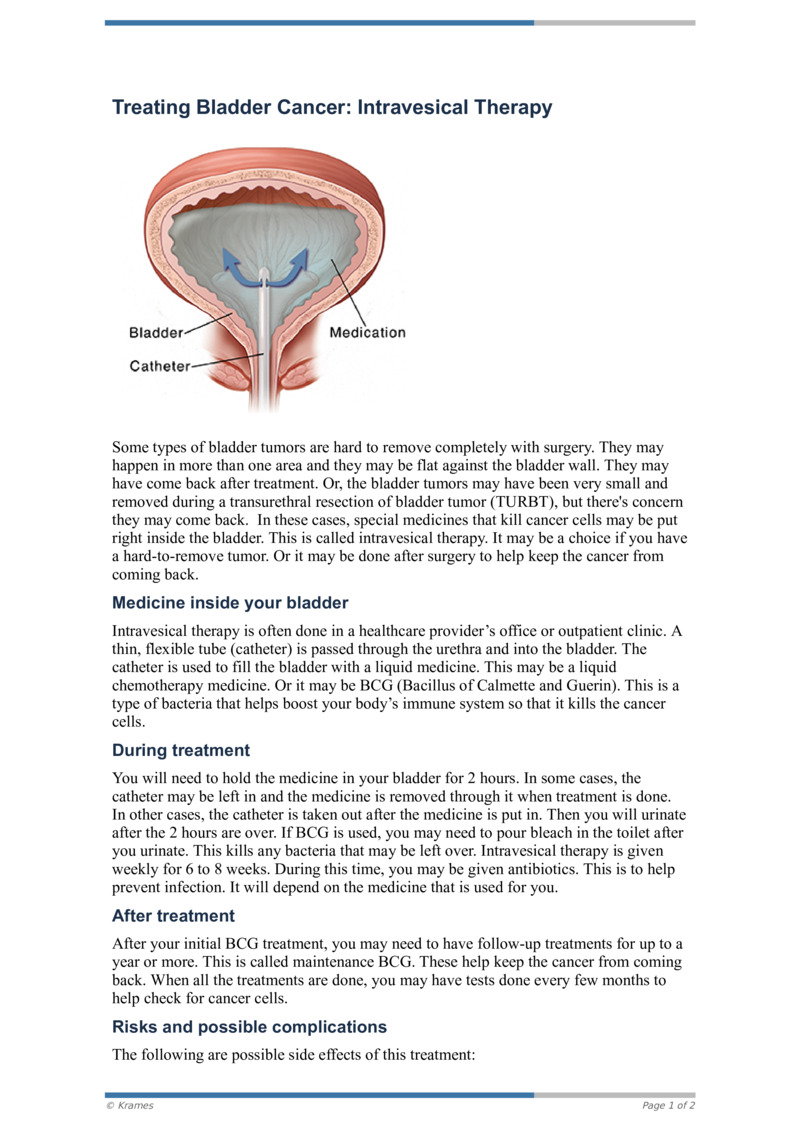
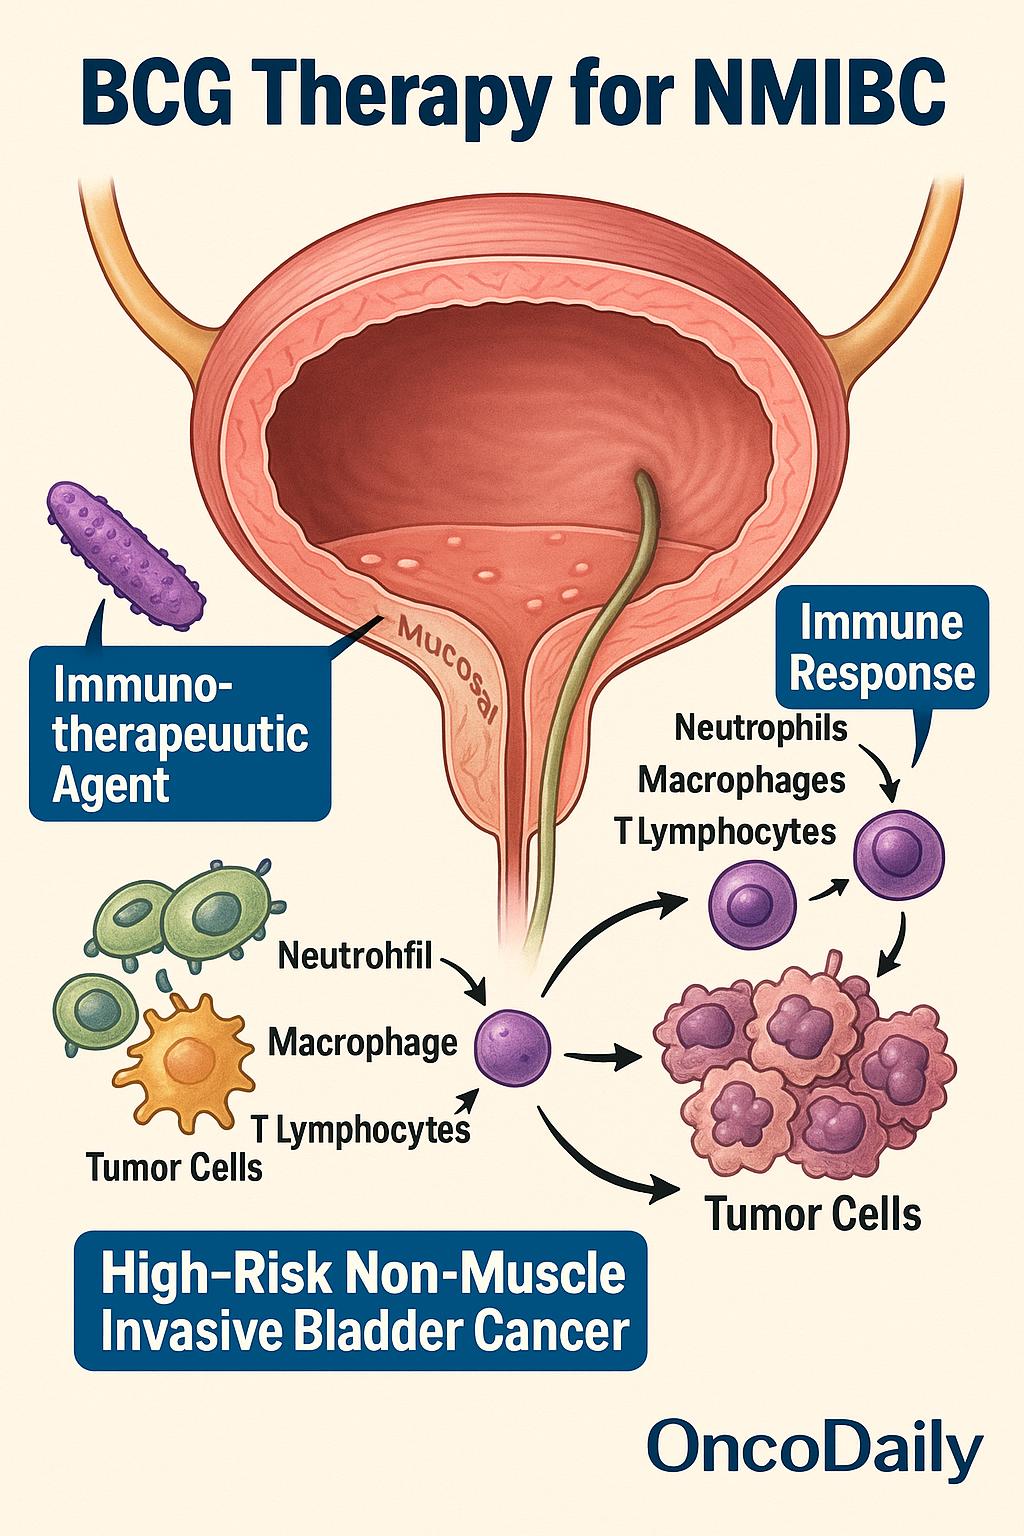
Intravesical therapy means instilling medication directly into the bladder through a catheter. For bladder cancer patients, the two most common agents are BCG (bacillus Calmette-Guerin) and mitomycin C. They serve different purposes but share the same basic delivery method. I've sat through more of these treatments than I care to count, both as a clinician and as someone who's watched patients deal with the reality of them. The procedure itself is straightforward. A urologist or nurse passes a small catheter into the bladder, drains any remaining urine, then instills the medication. The patient needs to hold it there for about an hour, changing position every fifteen minutes so the liquid contacts all the bladder walls. After that, you void it out. That's basically the whole thing. BCG is the workhorse for non-muscle-invasive bladder cancer. It's used as an immunotherapy after TURBT (transurethral resection of bladder tumor). The standard induction is six weekly instillations, followed by maintenance treatments at three, six, nine, twelve, eighteen, and twenty-four months. That comes from the SWOG protocol, and there's solid data behind it showing reduced recurrence and progression rates.
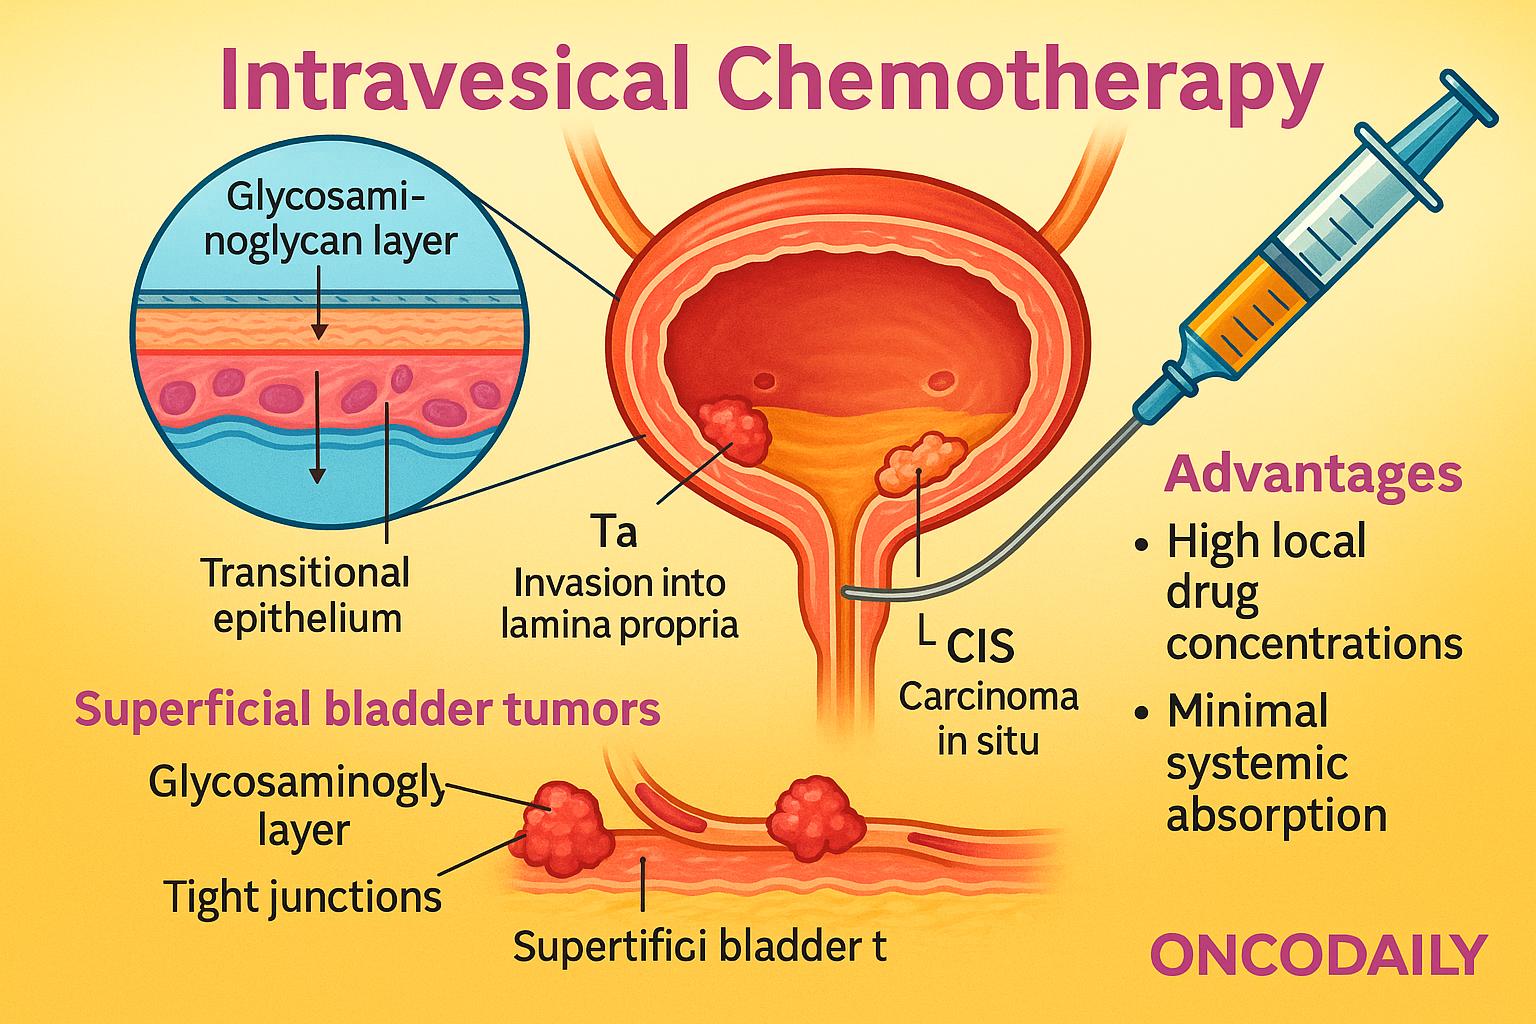
Mitomycin C is different. It's a chemotherapy agent, not an immunotherapy. It's typically given as a single post-operative instillation within twenty-four hours of TURBT to kill any cells that might have been shaken loose during surgery. Some protocols also use it in cycles for patients who aren't candidates for BCG. The key difference is timing. If you're giving BCG, you usually wait a week or so after TURBT to let the bladder heal. Mitomycin goes in right away because it needs to contact those raw surfaces while they're still vulnerable. I remember a case where a patient had a bad reaction to the positioning instructions. The standard protocol says to roll from your back to your left side, then your right side, then lie on your stomach. But this particular patient had severe lower back pain from a previous surgery and literally could not get onto their stomach. We tried working around it by having them do shorter position changes, staying on their sides longer, and essentially accepting that the anterior bladder wall wouldn't get as thorough coverage. It's not ideal, but it's better than skipping treatment entirely. The bladder is a pretty efficient sac though, and even incomplete contact seems to provide meaningful protection in many cases.
What Actually Happens During These Treatments
The side effects are where things get complicated. BCG causes what basically feels like a really nasty urinary tract infection in most patients. Frequency, urgency, burning, sometimes blood in the urine. These symptoms can last a few days after each instillation. Most people manage them with phenazopyridine, increased fluid intake, and sometimes a low-dose steroid. If the symptoms are severe enough, you might skip a treatment or delay it. There's a specific complication that catches people off guard. BCG fever. Some patients run a low-grade temperature after treatment, usually on the second or third day. It's inflammatory, not infectious, but it can feel terrible. I've seen patients present to the ER thinking they had a serious infection. The trick is to distinguish it from actual sepsis. A true BCG fever typically responds to ibuprofen or acetaminophen and resolves within forty-eight hours. If the fever persists beyond that or goes above 101.5, you need to start considering mycobacterial infection and possibly begin anti-tuberculosis treatment with rifampin, isoniazid, and ethambutol. One thing most patients don't understand is that symptom severity doesn't necessarily correlate with treatment effectiveness. I've seen patients who had brutal side effects from BCG and excellent outcomes, and others who barely felt anything and still did well. Don't try to game the system by requesting less frequent dosing just because you want to avoid discomfort. The schedule exists for a reason.
Get the Full Details
Mitomycin C side effects are generally milder. Chemical cystitis, some discomfort, occasionally a brief episode of hematuria. Much more tolerable for most people. The trade-off is that BCG tends to be more effective for preventing recurrence in high-risk patients, which is why it remains first-line for many cases.
When Intravesical Therapy Isn't Enough
Let me be clear about the limitations. Intravesical therapy does not cure muscle-invasive bladder cancer. If the cancer has grown into the muscular layer of the bladder wall, you need more aggressive treatment, typically radical cystectomy or sometimes trimodality therapy with TURBT plus radiation and chemotherapy. These treatments are for non-muscle-invasive disease, which includes Ta, T1, and carcinoma in situ (CIS). Even within non-muscle-invasive disease, there are scenarios where intravesical therapy alone falls short. Patients with multiple recurrent tumors, those with high-grade CIS that doesn't respond to BCG, or individuals who develop BCG-refractory disease may need to consider alternative approaches. Clinical trials with newer agents like pembrolizumab or gene therapy with p53 adenovirus are options worth discussing. Some patients move straight to early cystectomy, especially if they have variant histology or poor-risk features. The biggest mistake I see patients make is treating intravesical therapy like a guaranteed fix. It's a tool, not a cure. Surveillance with regular cystoscopies is equally important. The therapy reduces risk, but it doesn't eliminate it. You still need those follow-up scopes at three months, six months, and then periodically after that.
If you're facing this treatment, ask your urologist about your specific risk category, the rationale for choosing BCG versus mitomycin, and what the plan is if the first round doesn't work. Those conversations matter more than anything else you can read online.