What the Exam Actually Tests
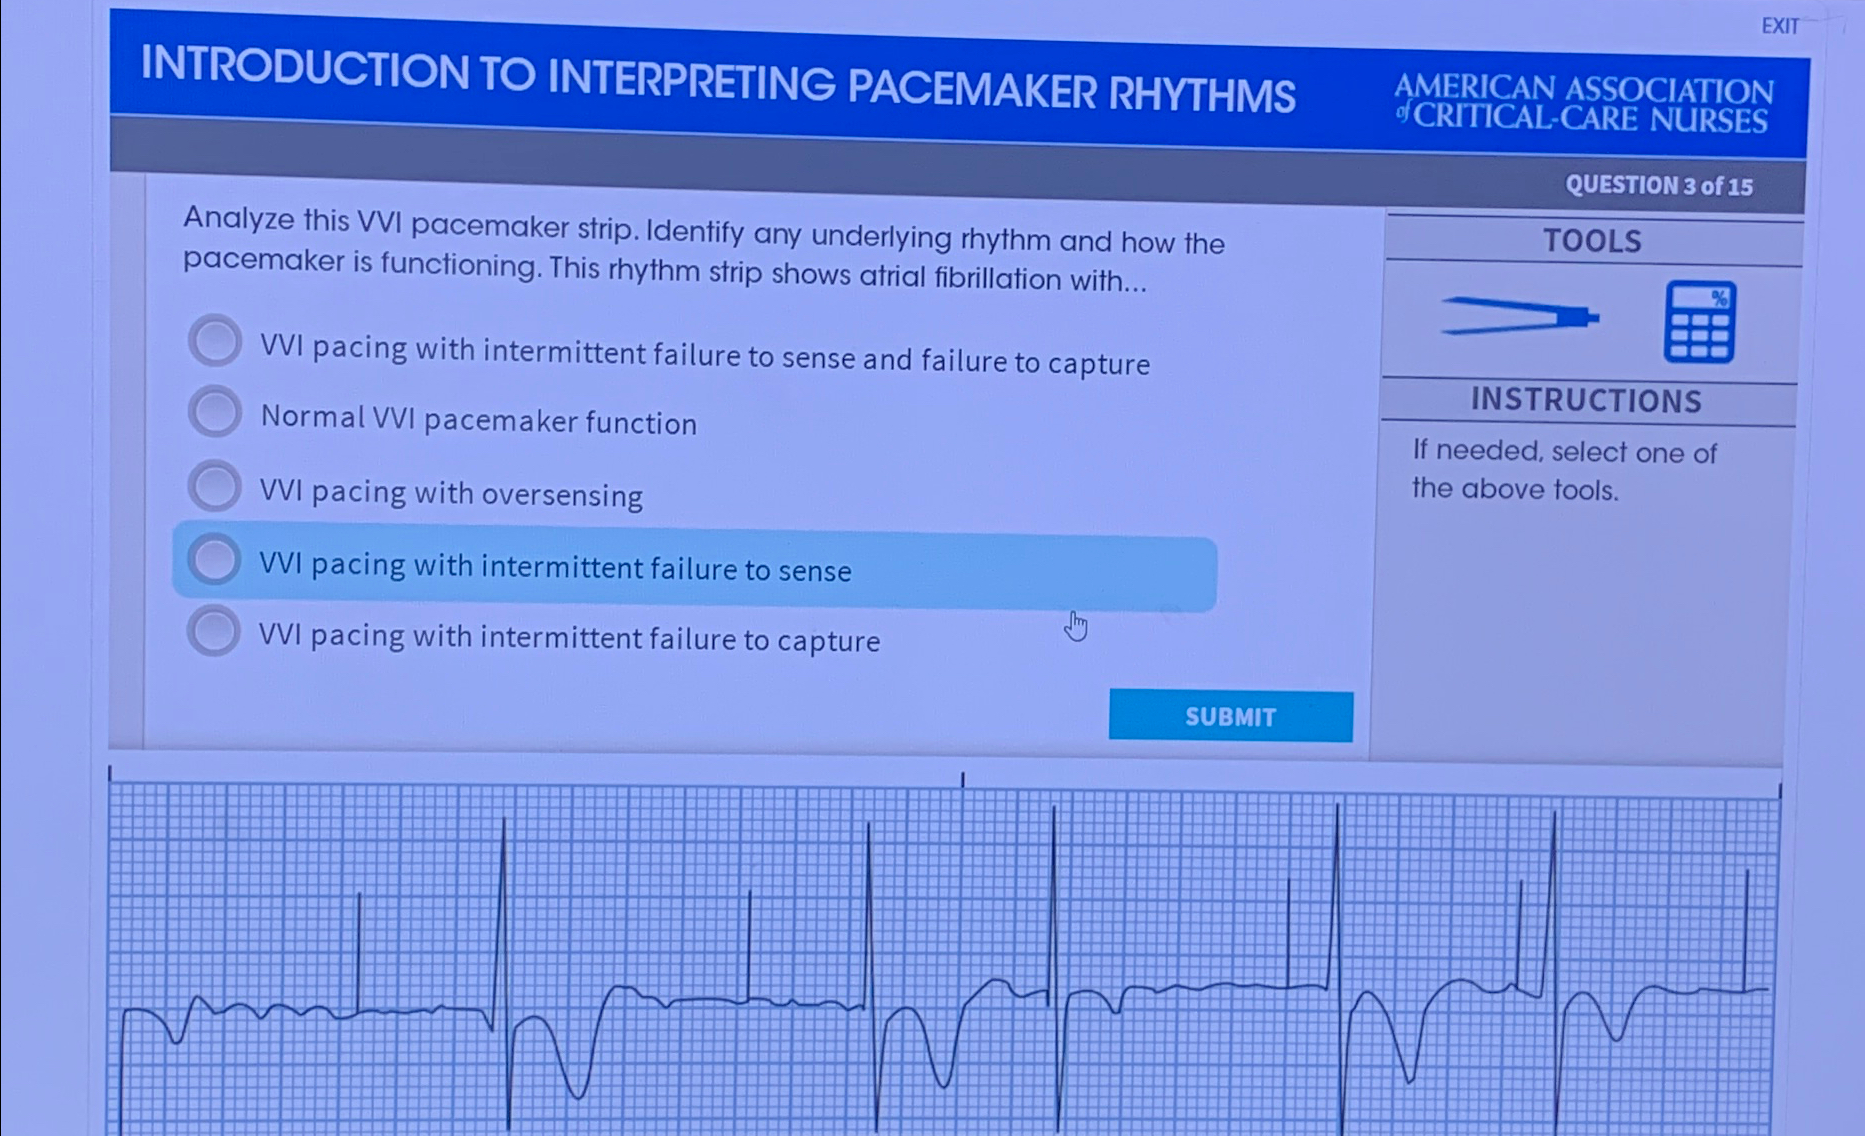
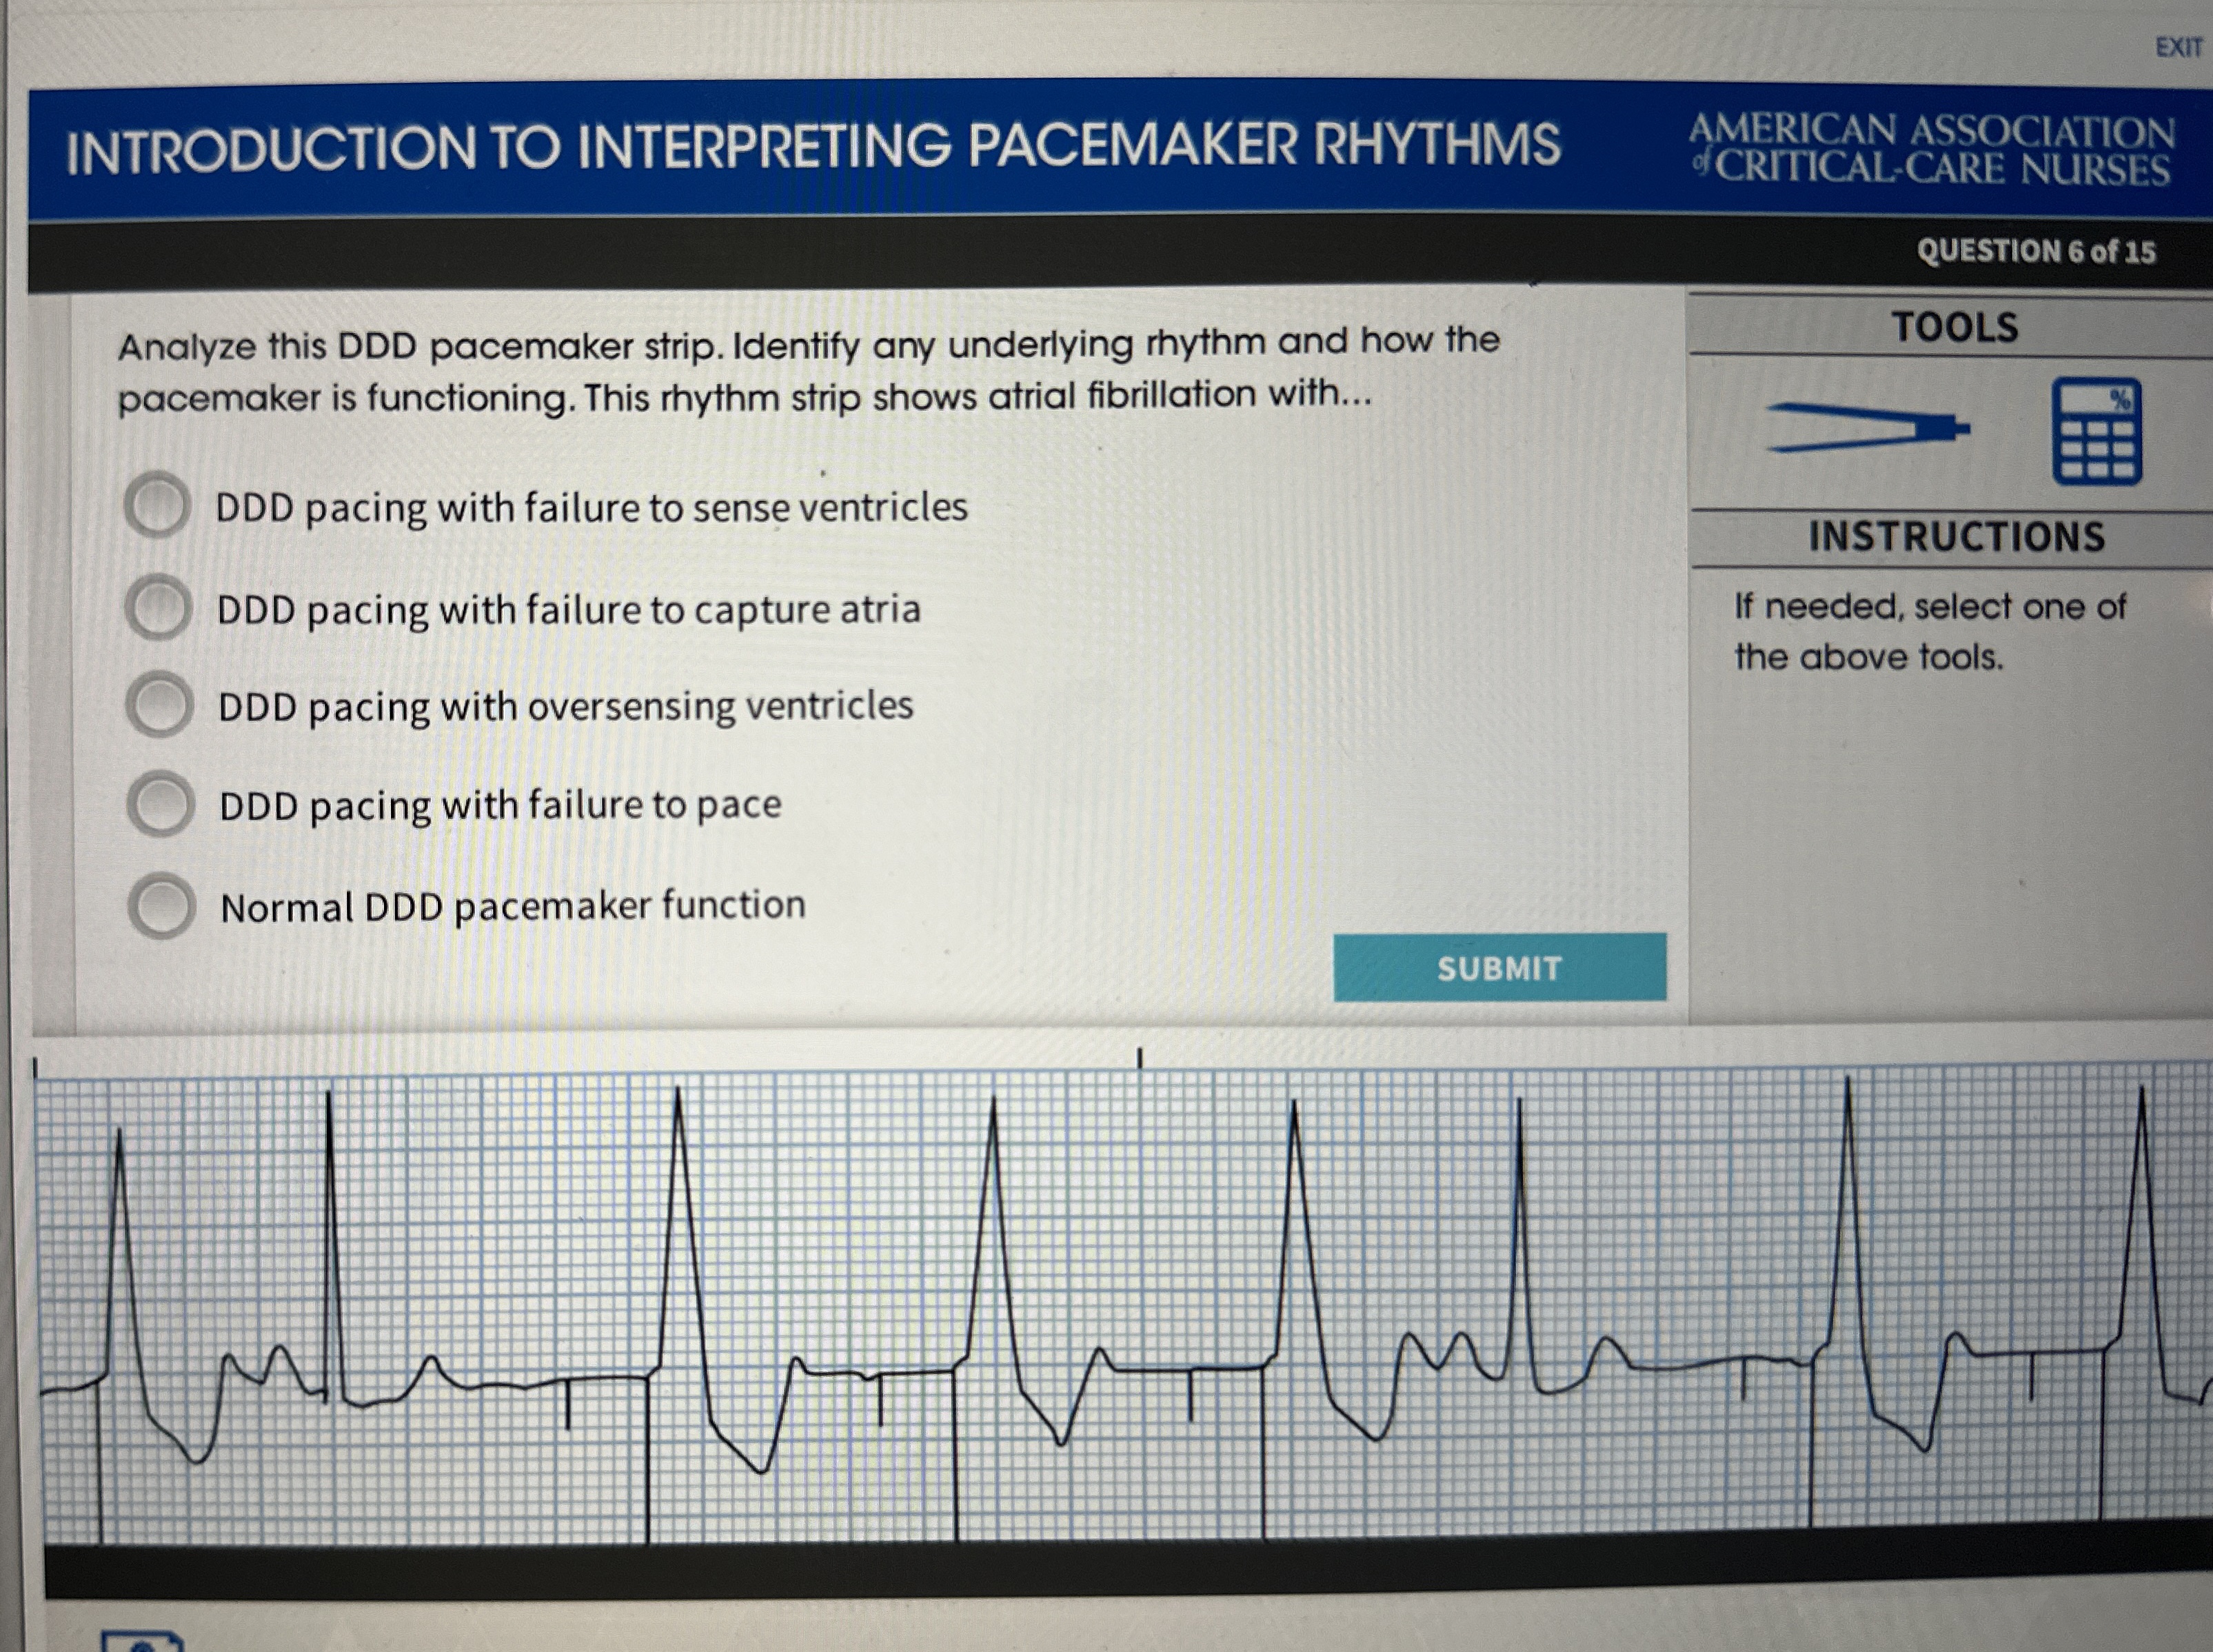
The Introduction To Interpreting Pacemaker Rhythms Exam is less about memorizing definitions and more about pattern recognition under time pressure. You will see strips that look identical at first glance but have one critical difference—a missed capture, a change in sensing threshold, a lead wire fracture. The exam rewards people who check every detail before committing to an answer. I go through a fixed mental checklist every time I see a strip, and it keeps me from making avoidable mistakes. The sequence matters because skipping steps is how you miss a problem that shows up clearly if you slow down even slightly. First, I identify whether there is a pacemaker present. Look for spike artifacts—sharp vertical deflections that are narrower than a QRS complex. Some modern devices produce very small spikes, sometimes barely visible, so I check the atrial and ventricular channels separately. If the strip has only one visible channel, I note that limitation before proceeding.
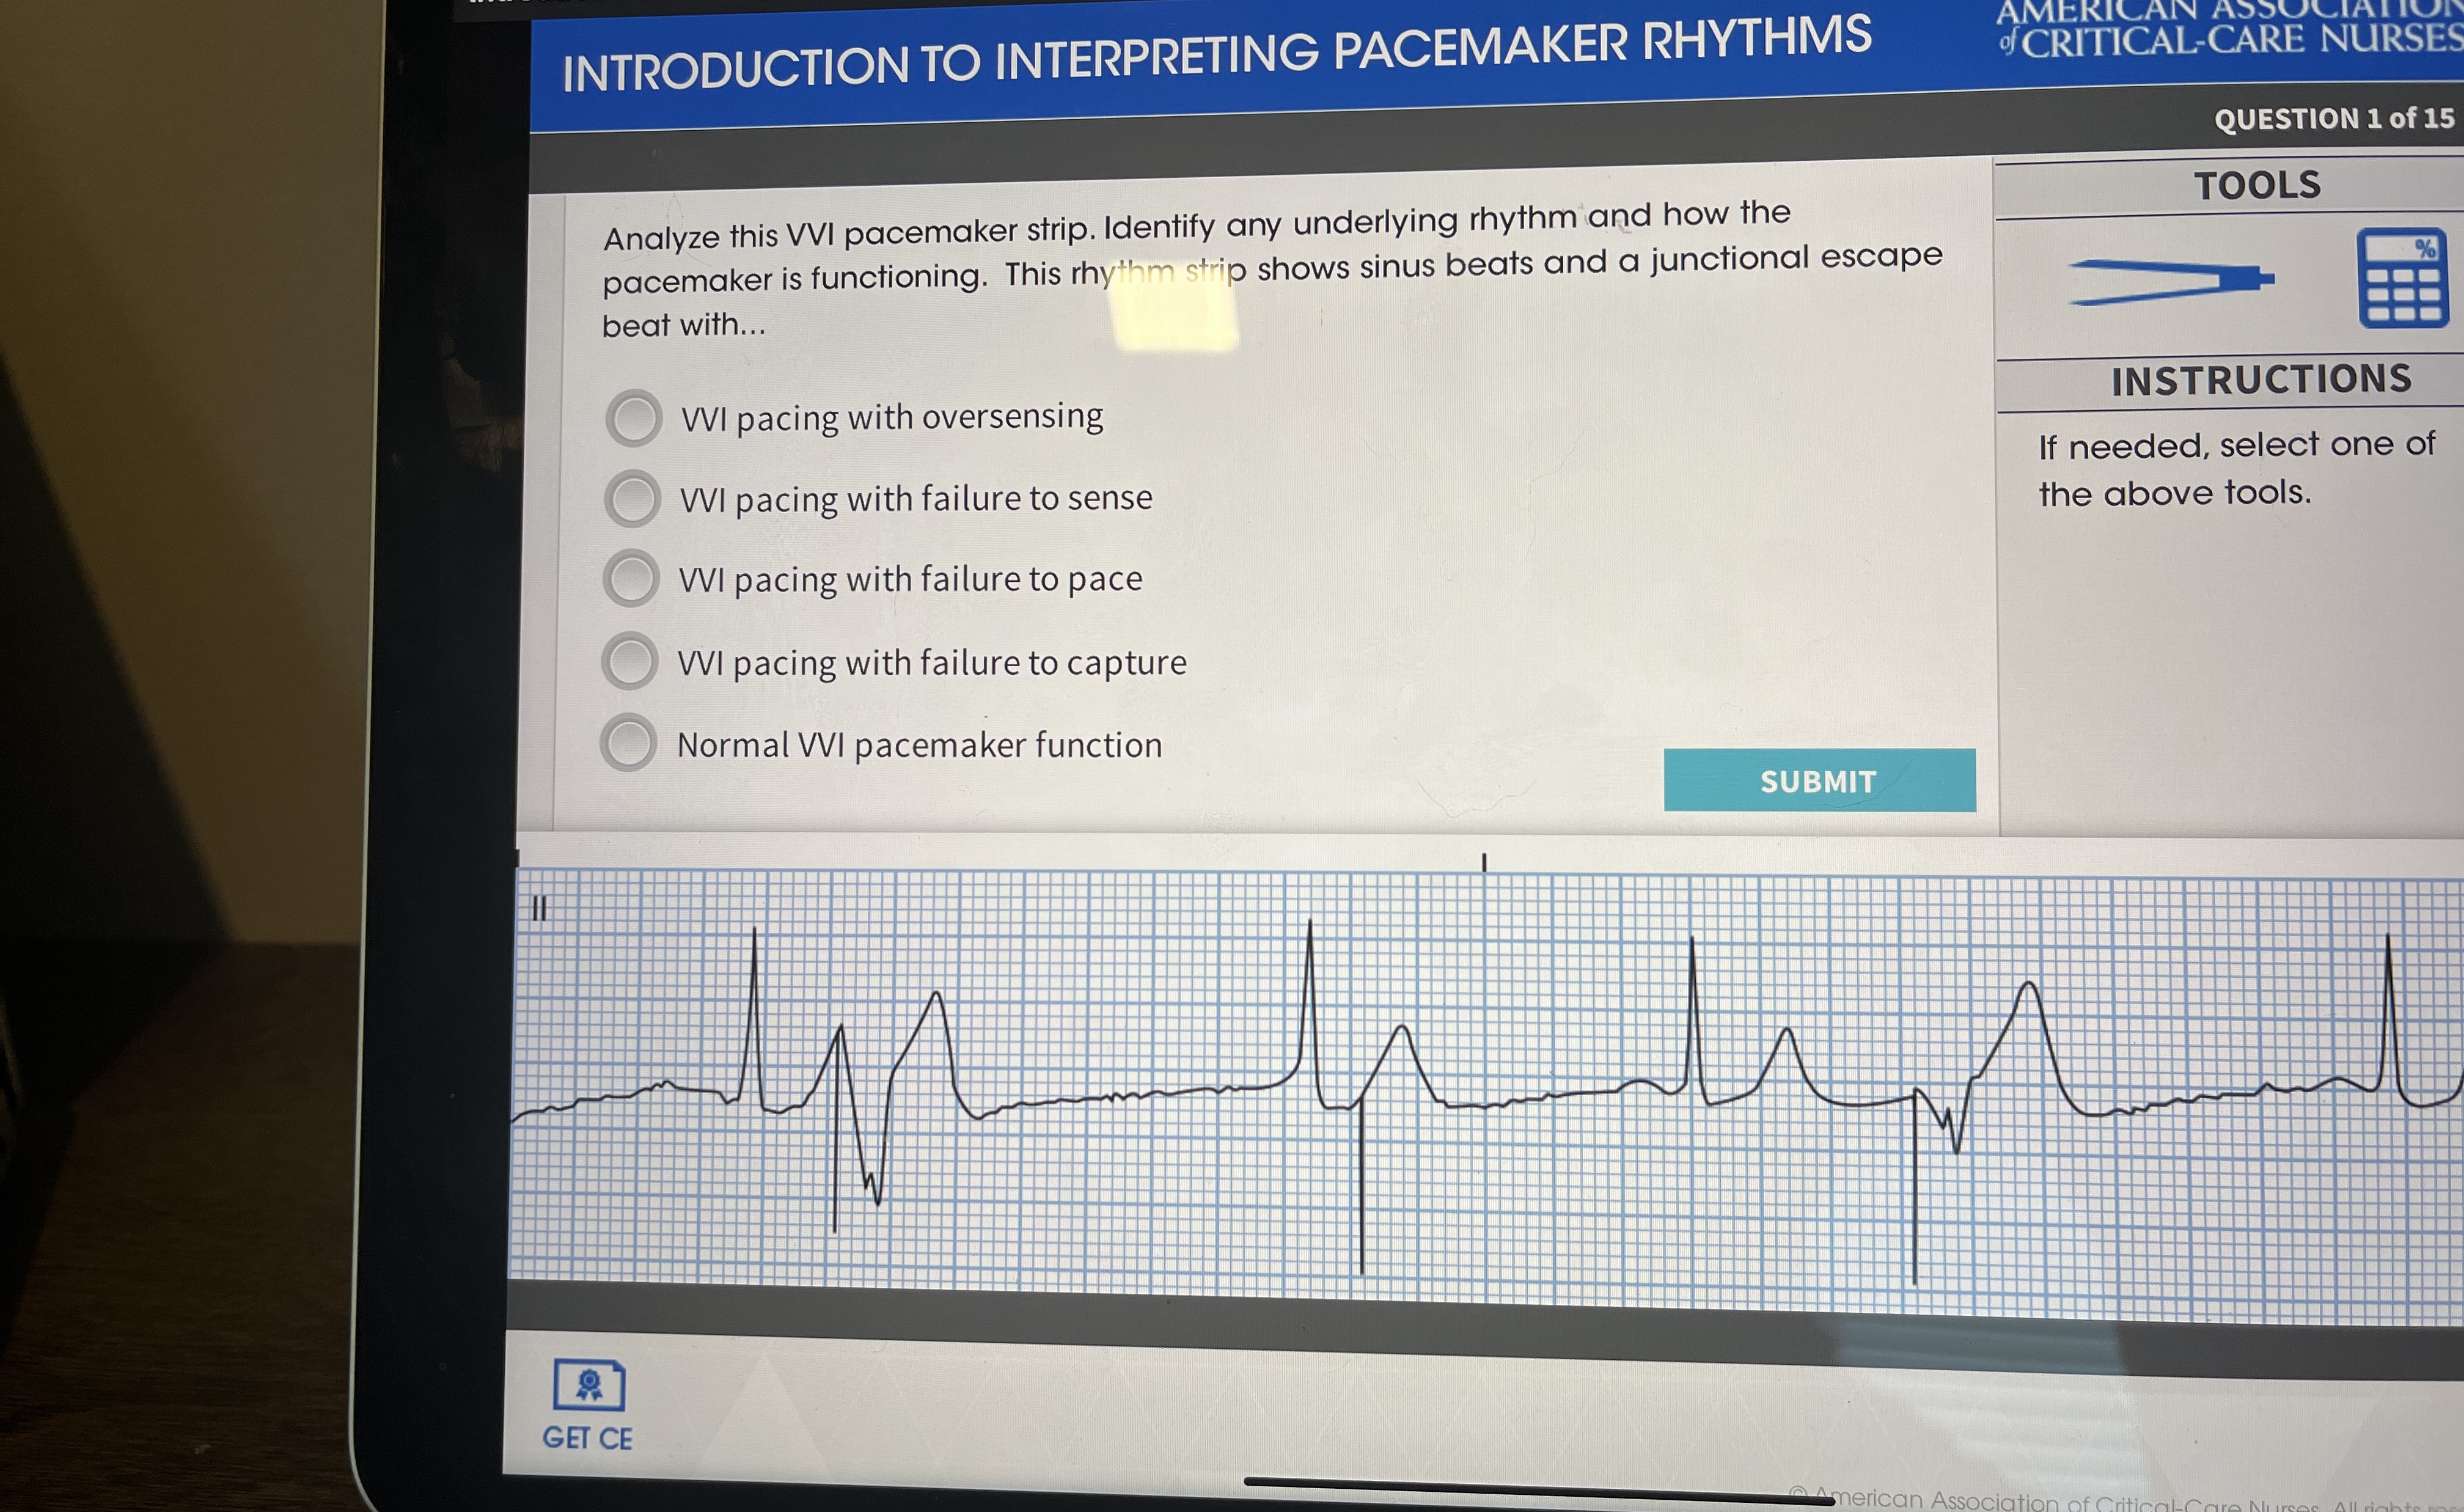
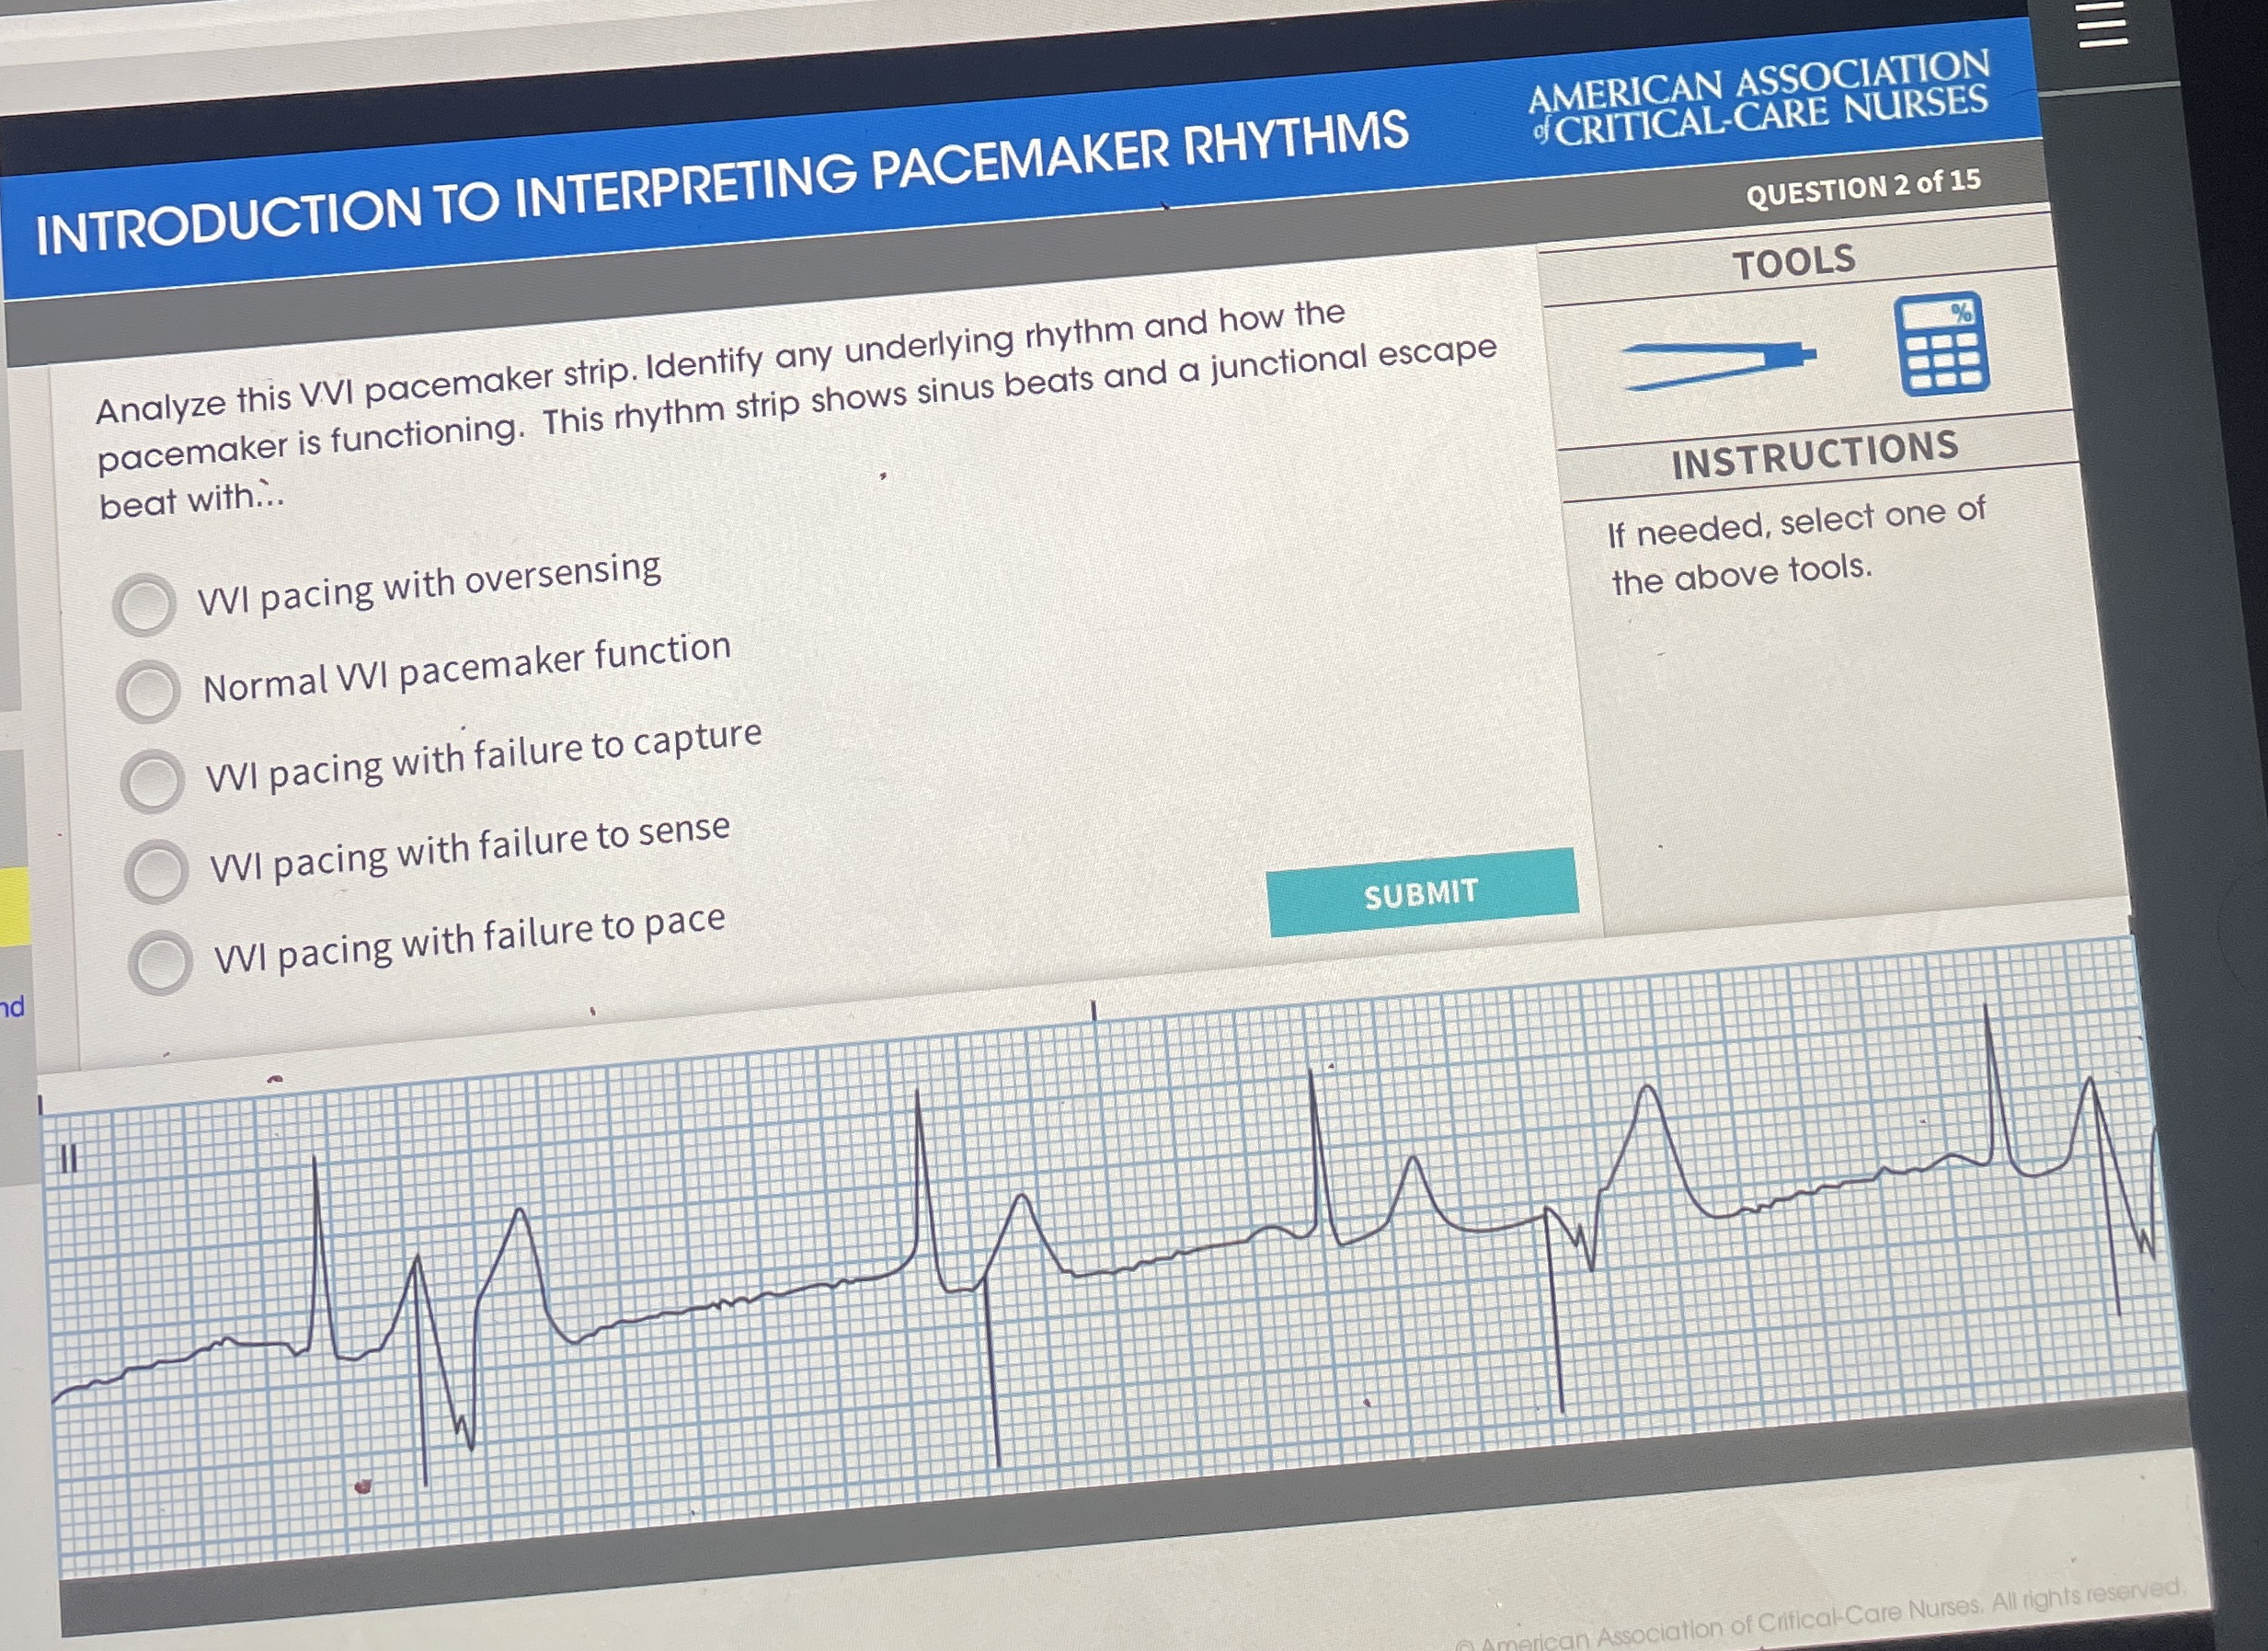
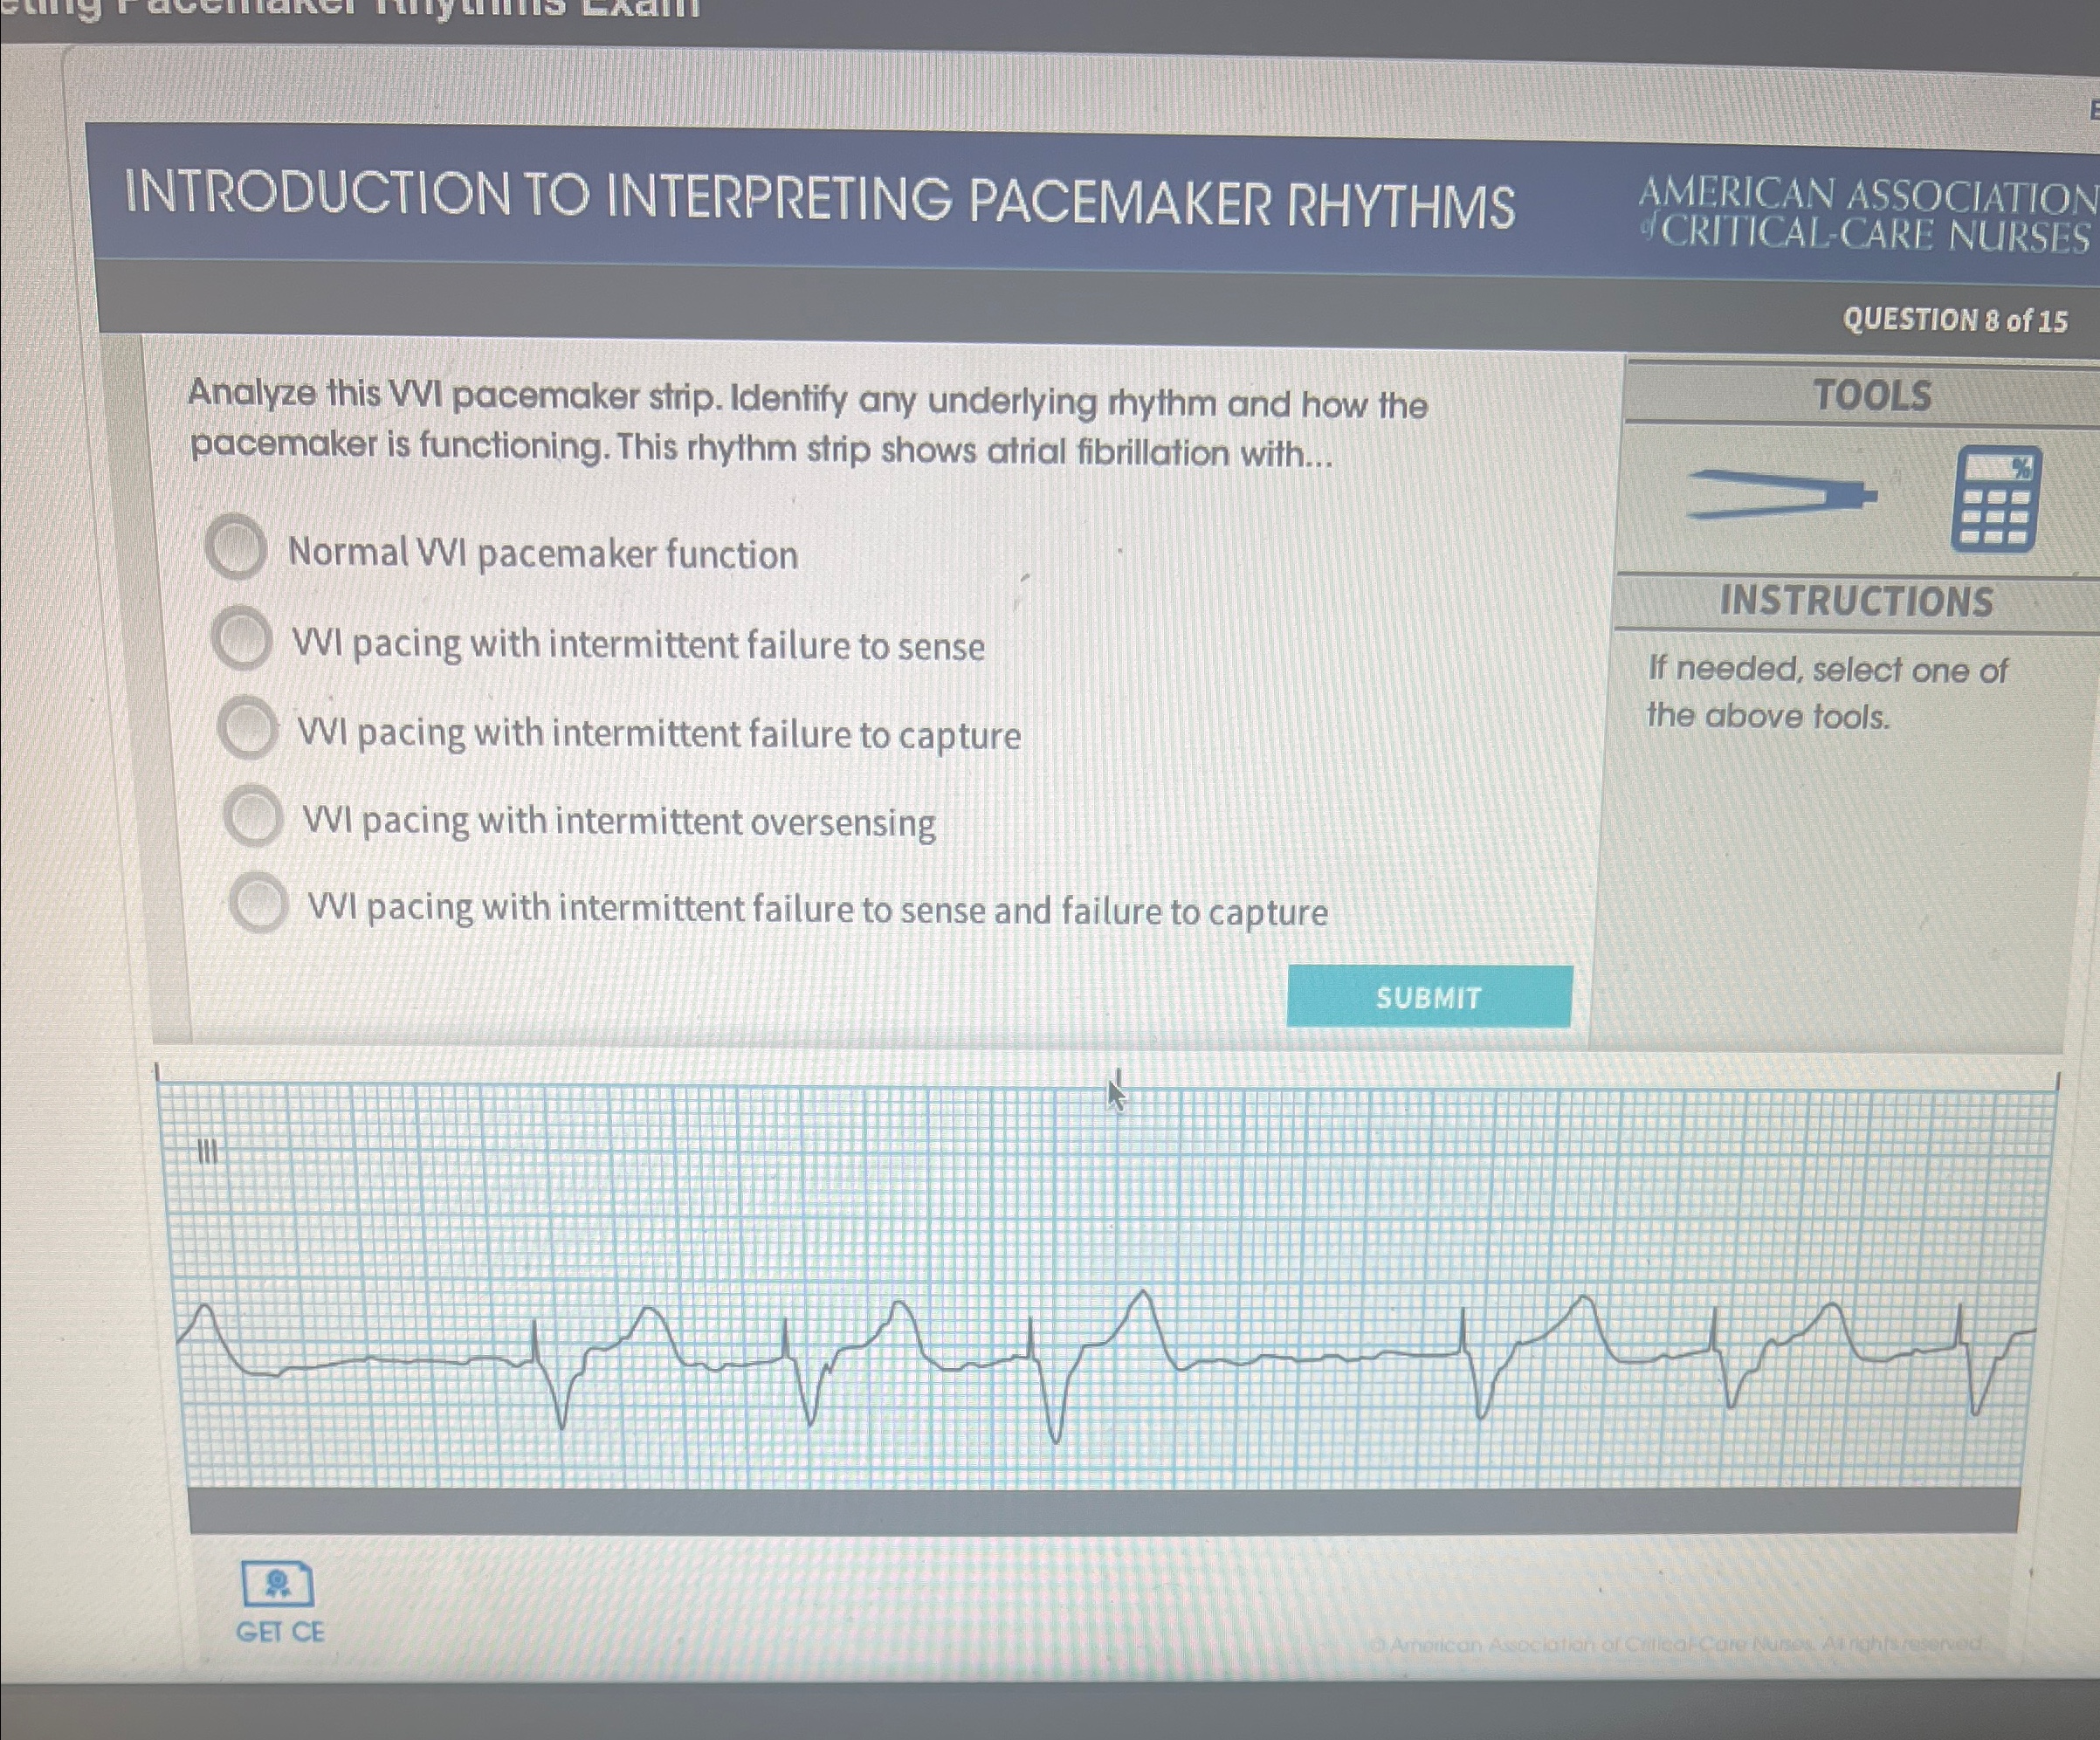
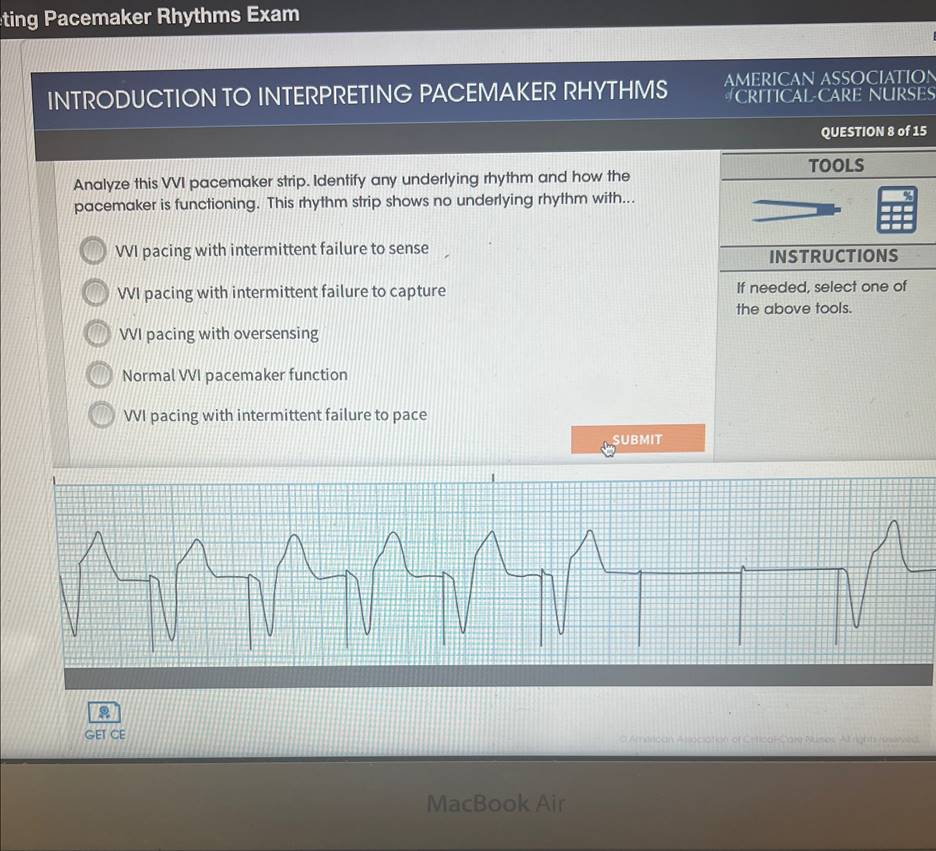
Second, I determine the underlying rhythm. Is there sinus P-wave activity? Is there a junctional escape? Is the baseline completely flat? This step matters because the pacemaker mode interpretation depends entirely on what the native rhythm is doing. A dual-chamber pacemaker in a patient with normal sinus rhythm behaves very differently from one in complete heart block. Third, I assess pacing. Are spikes followed by depolarizations—capture? If a spike appears and nothing follows, that is a non-captured beat, and the clinical implication changes everything. I look at this systematically for both atrial and ventricular channels. Fourth, I evaluate sensing. Does the pacemaker appropriately detect native beats and inhibit its output? If native QRS complexes appear without being inhibited, that indicates undersensing, which is a common exam question and a real clinical problem.
Fifth, I determine the mode. The standard notation uses five positions: chamber paced, chamber sensed, response to sensing, output modulation, and antitachycardia function. For exam purposes, you generally need to correctly identify the first three positions. DOO is dual out, OOO; AOO is atrial out, oxygen out; VVI is ventricular voltage, ventricular inhibition, inhibited; DDD is dual, dual, dual. Most exam strips will feature DDD or VVI modes. Sixth, I check the rate. Is the pacing rate appropriate? Are there signs of competition between the pacemaker and the intrinsic rhythm? Pacemaker-mediated tachycardia shows up on exams occasionally, and recognizing it requires seeing a consistent 1:1 retrograde conduction pattern with the pacemaker tracking every sinus P wave.
Get the Full Details
Common Pitfalls I See Students Miss
One thing that trips people up repeatedly is failing to distinguish between pseudo-undersensing and true undersensing. During the refractory period after a paced beat, the device is supposed to ignore electrical activity. If you see spikes and QRS complexes that look like they are occurring too close together, check whether the native beat falls within the device's refractory window. It might be perfectly appropriate behavior, not a malfunction. Another frequent error is misidentifying T-wave oversensing. A paced rhythm with prominent T waves can cause the device to misinterpret the T wave as a QRS complex, leading to inappropriate inhibition. On an exam strip, this looks like the pacemaker suddenly stops firing, then restarts after a long pause once the T waves disappear. The underlying rhythm remains regular, which is the key clue. I also notice students rushing through lead identification. An exam might show you a strip labeled "V1" without explicitly telling you it is a ventricular channel strip. You need to know that a single-channel strip showing narrow spikes followed by wide QRS complexes is almost certainly a ventricular lead in V5 or V6 position, and that affects how you interpret capture and sensing.
A Real Problem I Encountered
I was grading practice strips last year and came across one that looked like a straightforward VVI pacemaker rhythm at first glance. The spikes were regular at 70 beats per minute, and each spike was followed by a QRS. Everything looked fine until I measured the interval between the spike and the QRS onset. It was 120 milliseconds, which is within normal capture threshold, but then I noticed the PR interval of the intrinsic beats was varying—sometimes 200 milliseconds, sometimes 450. The student who took the strip had labeled it as simple VVI with normal capture, but the varying PR intervals on the underlying rhythm suggested the patient was actually in a sick sinus syndrome with intermittent sinus pauses, and the pacemaker was responding appropriately by pacing during those pauses. The key was recognizing that the VVI mode does not track P waves, so the varying intrinsic rates were irrelevant to the pacing mode—it was still appropriately functioning VVI. This kind of strip requires you to separate what the device is doing from what the heart is doing, and most exam questions deliberately mix the two to see if you can untangle them. The exam assumes you will interpret static strips. In clinical practice, pacemaker rhythms are dynamic. Rate-adaptive pacing changes the pacing rate based on activity. Demand pacing inhibits during intrinsic beats. The exam strips freeze a moment in time, which means you might see a single mode of operation when the device is capable of switching between multiple modes. This is not a flaw in the exam—it is a limitation of the testing format. Know that the strip you are interpreting represents one instant, and do not assume the device is incapable of other behaviors just because you only see one pattern. Grab actual rhythm strips from a clinical source rather than relying solely on textbook examples. Real strips have artifact, baseline wander, and variable amplitude. They look nothing like the clean textbook diagrams, and the exam sometimes includes strips with significant noise. Learning to extract useful information from a noisy strip is a skill that only comes from exposure to messy data.
Time yourself. The exam typically gives you roughly 90 seconds per strip. Practice reading a strip, forming an interpretation, and writing it down within that window. Speed without accuracy is worthless, but accuracy without speed means you will not finish. Focus on the strips that confuse you. If you can identify VVI and DDD rhythms confidently, spend your remaining study time on edge cases: pacemaker-mediated tachycardia, lead fracture patterns, diastolic depolarization, and battery depletion modes. These are the strips that separate passing scores from top scores. Download free strip banks from cardiology society websites and hospital training portals. Many institutions publish their ECG and rhythm strip question banks openly. The patterns repeat across different sources, so working through multiple banks builds recognition faster than re-reading the same material.
When This Method Fails
If you have never seen an actual ECG strip before attempting the exam, no amount of structured study will replace visual exposure. The pattern recognition component is genuinely visual, not theoretical. A student who has only read about pacemaker spikes without seeing hundreds of them on actual strips will struggle regardless of how well they understand the underlying physiology. In that case, the most effective workaround is to spend at least two weeks reviewing rhythm strips daily before attempting any timed practice exams. You need the visual database in your head before you can reliably apply the analytical framework. Additionally, if the exam uses a platform that does not allow scrolling or zooming on the strips, your ability to measure intervals precisely is limited. In those cases, rely more on gross pattern recognition than on precise millisecond measurements. Know the approximate normal values—PR interval 120 to 200 milliseconds, QRS duration less than 120 milliseconds for normal, pacing spike to QRS onset typically 40 to 100 milliseconds for ventricular pacing—but do not panic if you cannot measure them exactly on screen.
Final Notes
The Introduction To Interpreting Pacemaker Rhythms Exam tests a specific visual literacy. You learn it the same way you learn any visual pattern recognition task: through repeated, deliberate exposure and structured analysis of each strip. There is no shortcut around seeing the strips. Start with the basics, work through increasingly complex examples, and train yourself to notice the small details that change the entire interpretation. That is what separates a competent reader from one who is merely guessing.