Let me clear something up right away
There is no established standard of care for Iv Therapy For H Pylori, because H. pylori lives in the stomach lining and is a bacterium, not a systemic infection that typically requires intravenous delivery. The standard treatment is oral: a combination of two antibiotics plus a proton pump inhibitor for 10 to 14 days. I have had patients show up asking for IV treatment after seeing wellness clinic ads, and the honest answer I give them every time is that it is not indicated. When someone brings up IV therapy for H. pylori, they are usually running into one of two things. Either a functional medicine or integrative clinic is offering IV nutrients like glutathione, vitamin C, or zinc as adjunctive support during standard oral treatment. Or they are confusing H. pylori with a completely different condition that genuinely does require IV antibiotics, like a bloodstream infection or severe pneumonia. The first scenario is where I see the most confusion. IV glutathione or high-dose vitamin C is not going to eradicate H. pylori. It also will not replace the antibiotic regimen that actually clears the bacteria. What it might do is support liver function or reduce oxidative stress while the patient is on a heavy oral antibiotic course. I have seen patients feel slightly better on their days off between antibiotic doses when they get a IV nutrient drip, but that is a quality-of-life difference, not a therapeutic one for the infection itself.
I ran into a specific case last year involving a 62-year-old patient with refractory H. pylori who had already failed two rounds of clarithromycin-based triple therapy and one round of levofloxacin-based quadruple therapy. She was desperate. A clinic she found online recommended IV ampicillin-sulbactam as a way to bypass gastrointestinal absorption issues. I reviewed the literature with her and explained that H. pylori is not an organism you treat systemically with IV beta-lactams unless there is a documented complication like gastric bleeding or perforation requiring hospitalization. The bacteria sit in the mucus layer and intracellular spaces of the gastric epithelium. Oral amoxicillin and clarithromycin achieve far better concentrations in gastric tissue than any IV regimen would because they are specifically designed to concentrate there. We ended up doing a biopsy-guided susceptibility test and then using a high-dose bismuth quadruple therapy with metronidazole and tetracycline, which cleared the infection. The IV ampicillin idea was a dead end.
What Actually Works
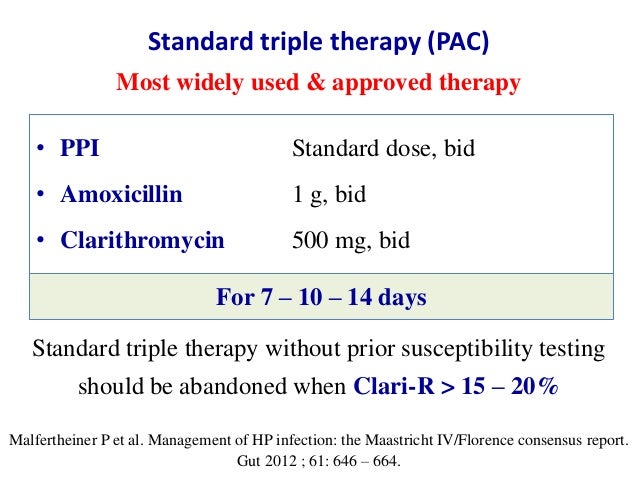
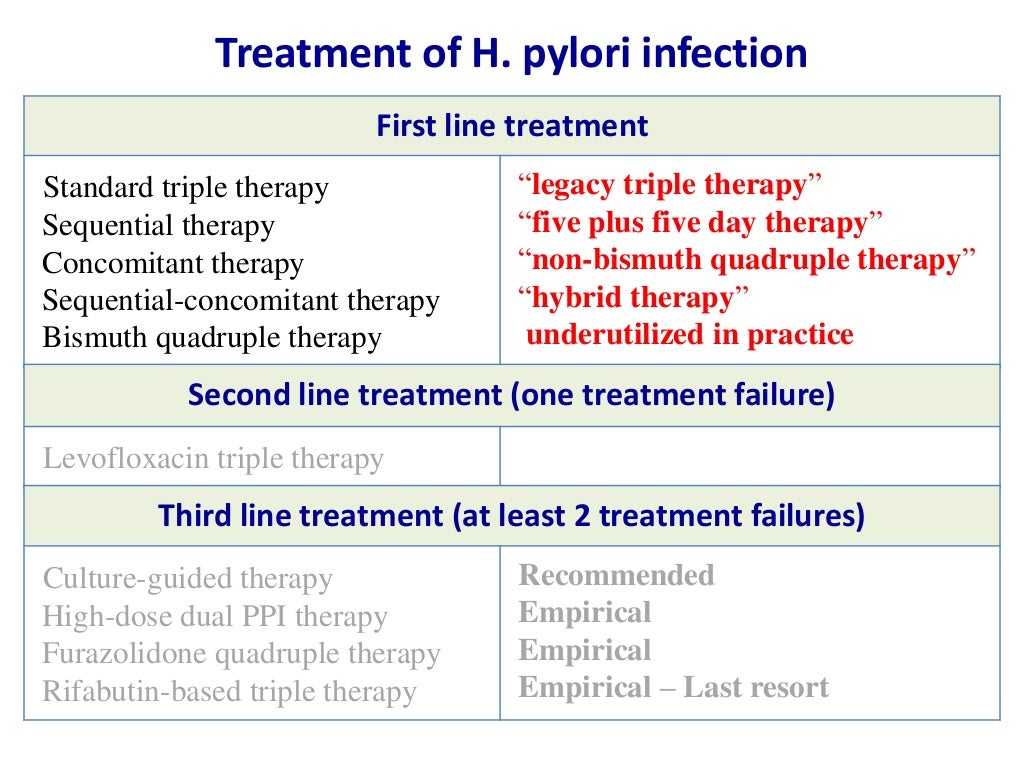
If you have H. pylori and your first-line treatment has failed, the next step is not IV therapy. It is culture and sensitivity testing or a PCR-based resistance panel on a gastric biopsy specimen. This tells you whether your strain is resistant to clarithromycin, metronidazole, or levofloxacin. Without that information, you are just rotating antibiotics blind and burning through options until you find one that works. Most guidelines now recommend this approach after first-line failure rather than the old pattern of just trying a different oral combination and hoping for the best. Ideally, you want treatment that gets at least 90 percent eradication rates. Bismuth quadruple therapy for 14 days still hits around that mark even in areas with moderate clarithromycin resistance. If your strain is resistant to both clarithromycin and metronidazole, which happens more often than people realize, you are looking at levofloxacin-based triple therapy or rifabutin-based regimens. Rifabutin is not a first-line drug anywhere, but it works when everything else has failed, and the cost is usually not prohibitive. There is also a newer vonoprazan-based regimen that is gaining ground. Vonoprazan is a potassium-competitive acid blocker, not a traditional PPI, and it maintains a higher and more stable intragastric pH. That matters because most of the antibiotics used for H. pylori are acid-sensitive or work better in a less acidic environment. In clinical trials, vonoprazan plus amoxicillin dual therapy for 14 days achieved eradication rates above 90 percent even with clarithromycin-resistant strains, which is notable because dual therapy used to be considered inadequate.
Get the Full Details
Why People Keep Asking About IV Options
The reason this question comes up repeatedly is that standard treatment is rough. Three or four oral pills taken three or four times a day for two weeks will upset your gut. Nausea, metallic taste, diarrhea, and abdominal cramping are the norm, not the exception. Some patients simply cannot tolerate the oral regimen well enough to complete it. When you are in that position, it is understandable that you would look for an alternative route of administration. The problem is that even if you deliver the antibiotics intravenously, you are not solving the core issue. IV amoxicillin does penetrate gastric tissue adequately, but the dosing schedule required to maintain effective concentrations in the stomach lining is cumbersome and not standard practice. IV metronidazole is an option in hospitalized patients who cannot take anything by mouth, but it is not a superior treatment for otherwise healthy outpatients. And IV clarithromycin essentially does not exist in a clinically useful form for this indication. So when a patient tells me they cannot tolerate the oral pills, my first response is to split the dose differently, add an antiemetic, or switch to a formulation with better GI tolerability. A 14-day bismuth quadruple regimen with diluted oral metronidazole and subcolloidal bismuth subcitrate tends to be better tolerated than clarithromycin-based therapy for most people. If they still cannot complete oral treatment, then we discuss whether hospitalization for IV metronidazole plus IV ampicillin is warranted, but that is rare.
Iv Therapy For H Pylori in Practice
When an integrative clinic offers IV therapy alongside H. pylori treatment, what you are usually paying for is a vitamin or mineral drip administered through a peripheral IV line. The most common components are vitamin C, glutathione, B-complex vitamins, and magnesium. These are not antibacterial agents. They do not kill H. pylori. They may help with recovery from the antibiotic side effects, reduce inflammation, or correct deficiencies that develop during a prolonged course of antibiotics that disrupts gut absorption. I have observed that some patients who receive these drips report fewer symptoms between antibiotic doses. I do not attribute this to any direct effect on the bacteria. It is more likely that rehydration, electrolyte replacement, and antioxidant support improve how the patient feels while their body is processing a heavy antibiotic load. The infection still clears or does not clear based entirely on whether the oral antibiotic regimen is effective against the specific strain. One edge case I want to mention involves patients with severe malabsorption syndromes, such as those with short bowel syndrome or advanced Crohn's disease affecting the stomach and proximal small intestine. In these patients, oral antibiotics may not reach therapeutic levels in the gastric mucosa because the absorptive surface area is too limited. Here, IV antibiotic therapy can be clinically justified, but it is an exception driven by the malabsorption, not by the H. pylori infection itself. I managed one such patient who had extensive small bowel resection and persistent H. pylori colonization. We used IV ampicillin-sulbactam for six weeks while simultaneously trying to optimize her enteral nutrition to restore enough absorptive capacity for oral therapy. It took months, but it worked. That is not a routine scenario.
The Real Bottleneck
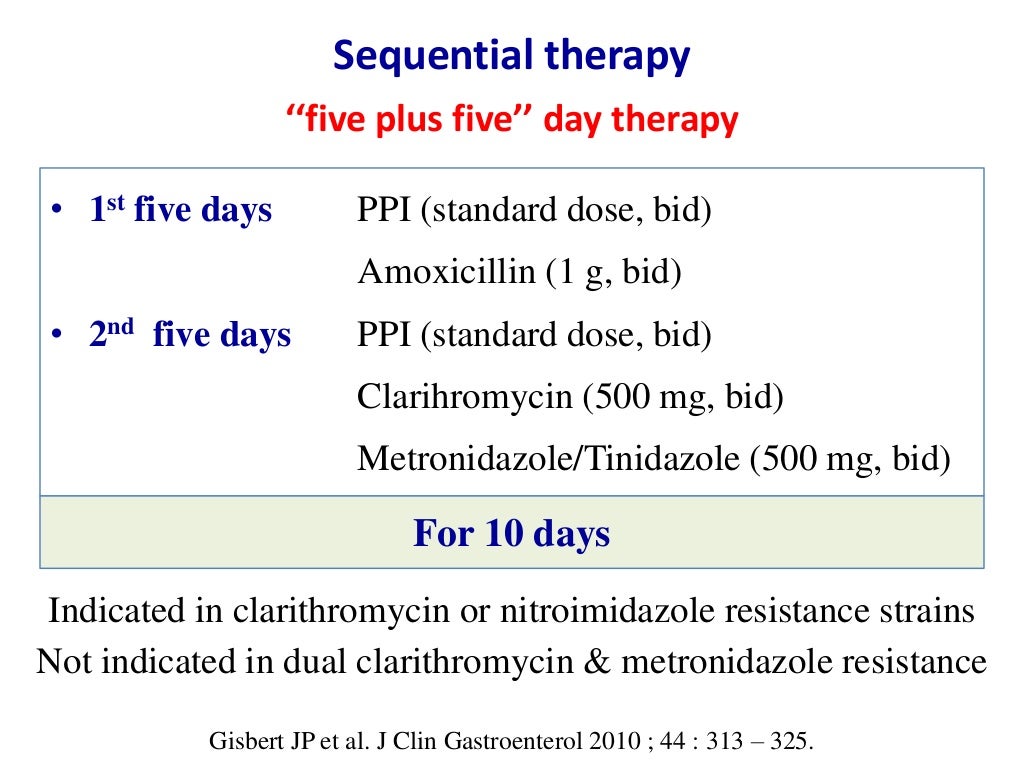
The biggest bottleneck in H. pylori treatment is not the route of administration. It is antibiotic resistance. Clarithromycin resistance alone exceeds 20 percent in many parts of the world and is higher in certain geographic regions. Metronidazole resistance is even more variable but commonly reaches 40 to 50 percent in areas with heavy nitroimidazole use. When you pick a regimen without knowing the resistance profile, you are essentially gambling. I have seen patients complete full courses of what should have been effective therapy and still test positive because the strain was resistant to one of the antibiotics and nobody checked. The workaround is straightforward in principle but underutilized in practice. After a treatment failure, get a gastric biopsy and run a susceptibility test before starting the next regimen. If you do not have access to that, use a regimen that accounts for the highest likely resistance patterns in your area. In high-clarithromycin-resistance regions, that means skipping clarithromycin entirely and going straight to bismuth quadruple therapy or vonoprazan-based dual therapy. In areas with high metronidazole resistance, you might consider a regimen that avoids metronidazole or doubles the dose and extends the duration.
Bottom Line
IV therapy is not a standard or recommended treatment for H. pylori in the vast majority of cases. It has a narrow role in patients with malabsorption or those who cannot tolerate oral medications due to other medical conditions. For typical H. pylori infection, the evidence supports oral antibiotic regimens, ideally guided by susceptibility testing after the first treatment failure. IV nutrient drips may improve how a patient feels during treatment but do not increase eradication rates. If a clinic is selling IV therapy as a primary treatment for H. pylori, that claim is not supported by clinical evidence.