
Managing Social Media for a Major Medical Institution
It's louder than you'd expect just managing day-to-day posts. Johns Hopkins Medicine Social Media operates across dozens of verified accounts on X, Facebook, Instagram, LinkedIn, and YouTube, each serving different audiences from patients and caregivers to medical researchers and prospective students. The complexity comes from the fact that every single post carries institutional risk. A misattributed statistic, a poorly worded treatment claim, or a viral reply that spirals into misinformation can generate serious legal and reputational exposure. The social media operations at Hopkins span several functional layers. There's the main institutional feed covering research breakthroughs, hospital news, and community health messaging. Then there are department-specific accounts run by individual schools or clinics, each with their own editorial calendars and sometimes their own content teams. The division of labor between the central communications office and individual departments creates friction that most outsiders don't see until they're in the room. The central team handles crisis communications, official statements, and high-visibility announcements. Department accounts push clinical research highlights, physician spotlights, and program-specific recruitment content. Some departments have enough autonomy to hire their own social media coordinators. Others rely entirely on the central office to draft and schedule everything. This hybrid model works adequately until two departments post conflicting information during an active situation, which happened during a flu season spike a few years back. The fix was establishing a shared approval workflow where time-sensitive clinical content could bypass the normal chain without sacrificing compliance review.
The Operational Reality
I've spent years watching how these systems actually function under pressure. The first thing people misunderstand is that healthcare social media is not primarily about engagement metrics. Likes and retweets matter for brand awareness campaigns, but the real work is accurate information delivery at scale. During the early months of COVID, the Hopkins social media operation was fielding thousands of redirect requests from users asking for triage guidance. The central team couldn't handle it alone, so they built a tiered response system routing general questions to existing FAQ pages while flagging emerging patterns to the clinical advisory group for rapid content updates. That shift cut response times from roughly forty-five minutes down to under eight on the critical queries. The second misconception is that compliance slows everything down. It does, but strategically. Having a medical professional or legal reviewer sign off on posts about treatments, drug trials, or procedural outcomes prevents the kind of liability incidents that sink other health systems. The tradeoff is real. A breaking research announcement that could have been posted within an hour often waits four to six hours for the full review cycle. The workaround I've seen work best is pre-clearing template language for recurring content types — trial recruitment posts, vaccination reminders, seasonal health advisories — so that when something time-sensitive drops, only the variable information needs fresh review rather than the entire post structure.
Tools and Infrastructure Behind the Accounts
Most large medical institutions run their social media through enterprise scheduling platforms like Sprout Social or Hootsuite Enterprise, integrated with their CRM and analytics stacks. Hopkins uses a combination of dedicated listening tools to monitor brand mentions and sentiment across all platforms simultaneously. The listening side is where the unglamorous work lives. Setting up boolean search strings that capture misspellings of drug names, department abbreviations, and physician handles requires ongoing maintenance. A string that works in January will pull irrelevant noise by March if nobody adjusts it. The analytics reporting layer connects social engagement data to broader institutional KPIs. For Johns Hopkins Medicine Social Media, this means correlating post performance with website traffic to specific patient education pages, call volume to information lines, and even referral patterns to certain clinics. That last part is the difficult one. Attribution between a social post and a patient calling a clinic is inherently messy, and any dashboard claiming precise conversion numbers is selling something. The more honest approach tracks directional trends — did calls increase in the week following a vaccination awareness campaign? Was there a measurable uptick in page views for the relevant resource hub? Those answers are useful without pretending to be exact.
Get the Full Details
Common Pitfalls and What Actually Fails
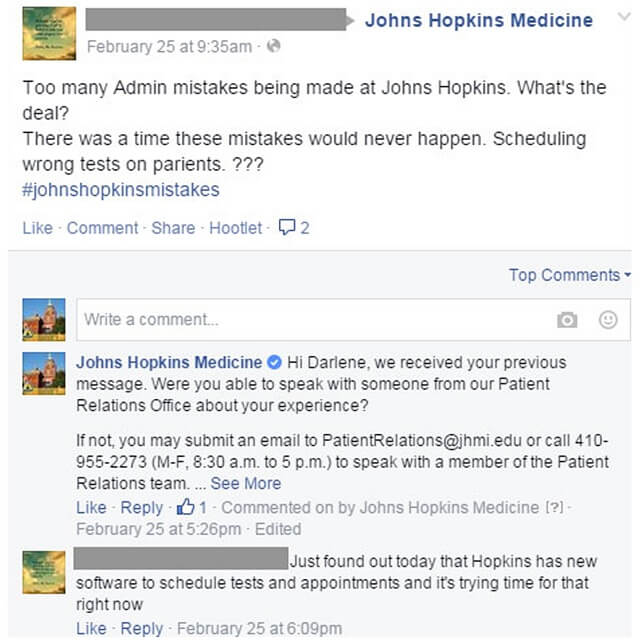
The biggest operational failure point I've observed is the assumption that one team can manage tone across all platforms. A LinkedIn post targeting physician recruitment reads completely differently from an Instagram Reel aimed at young parents, and the voice guidelines have to reflect that. I worked with a system that tried to enforce a single brand voice across every channel. The result was LinkedIn posts that sounded stiff and Instagram content that felt forced. They eventually relaxed the guidelines to allow department-level voice adaptation within broad guardrails, and engagement improved across both platforms within a quarter. Another persistent problem is volunteer or intern turnover. Healthcare social media roles are frequently filled by graduate students or communications interns on short terms. Knowledge about account passwords, platform quirks, and existing content calendars disappears when people leave. The standard solution is maintaining a living handbook with login details stored in a proper credential manager, documented workflow checklists, and archived calendar history. Without that infrastructure, onboarding someone new takes weeks instead of days, and mistakes compound during the gap. There's also the issue of response ownership. When a patient comments asking about symptoms or treatment options, someone has to respond or route the message appropriately. I've seen healthcare systems get burned when social media staff answered clinical questions directly instead of directing people to contact their provider or call the nursing triage line. The policy everywhere I've worked is blunt: never provide medical advice on social media. Always redirect to appropriate clinical channels. It's mundane to implement but critical to enforce consistently.
The Limits of What This Approach Can Do
No social media operation at a major medical institution can prevent misinformation from spreading. When a false claim about a treatment or vaccine goes viral, the institutional response is always reactive, no matter how fast the monitoring tools are. The best any team can do is maintain a stockpile of evidence-based rebuttal content that can be deployed within hours rather than days. Hopkins has done this effectively during high-profile moments, pulling pre-approved myth-busting graphics and linking to peer-reviewed sources without getting drawn into argument threads. Engagement baiting the other way never helps the institutional position. The system also struggles with real-time coordination during active crises. If a hospital emergency triggers simultaneous press releases, social posts, email alerts, and website banners, the timing has to be synchronized across communications, IT, legal, and clinical leadership. Any misalignment produces the appearance of confusion even when the underlying response is sound. I've sat in meetings where the social media team was ready to post a statement five minutes before legal wanted it held for an additional review cycle. Those decisions are rarely comfortable and usually require a designated authority to make the final call under pressure. What remains effective about Johns Hopkins Medicine Social Media is that it was built with the understanding that healthcare institutions operate differently from commercial brands. The metrics that matter are different. The risk profile is different. The accountability structures are different. Anyone trying to apply a standard corporate social media playbook to a hospital system will produce content that feels wrong to the audience even if the engagement numbers look fine on paper. The departments that get it right are the ones that accept the constraints upfront and design their workflows around them rather than fighting against them.



