Understanding the Two Main Types of Nephrons in the Kidney
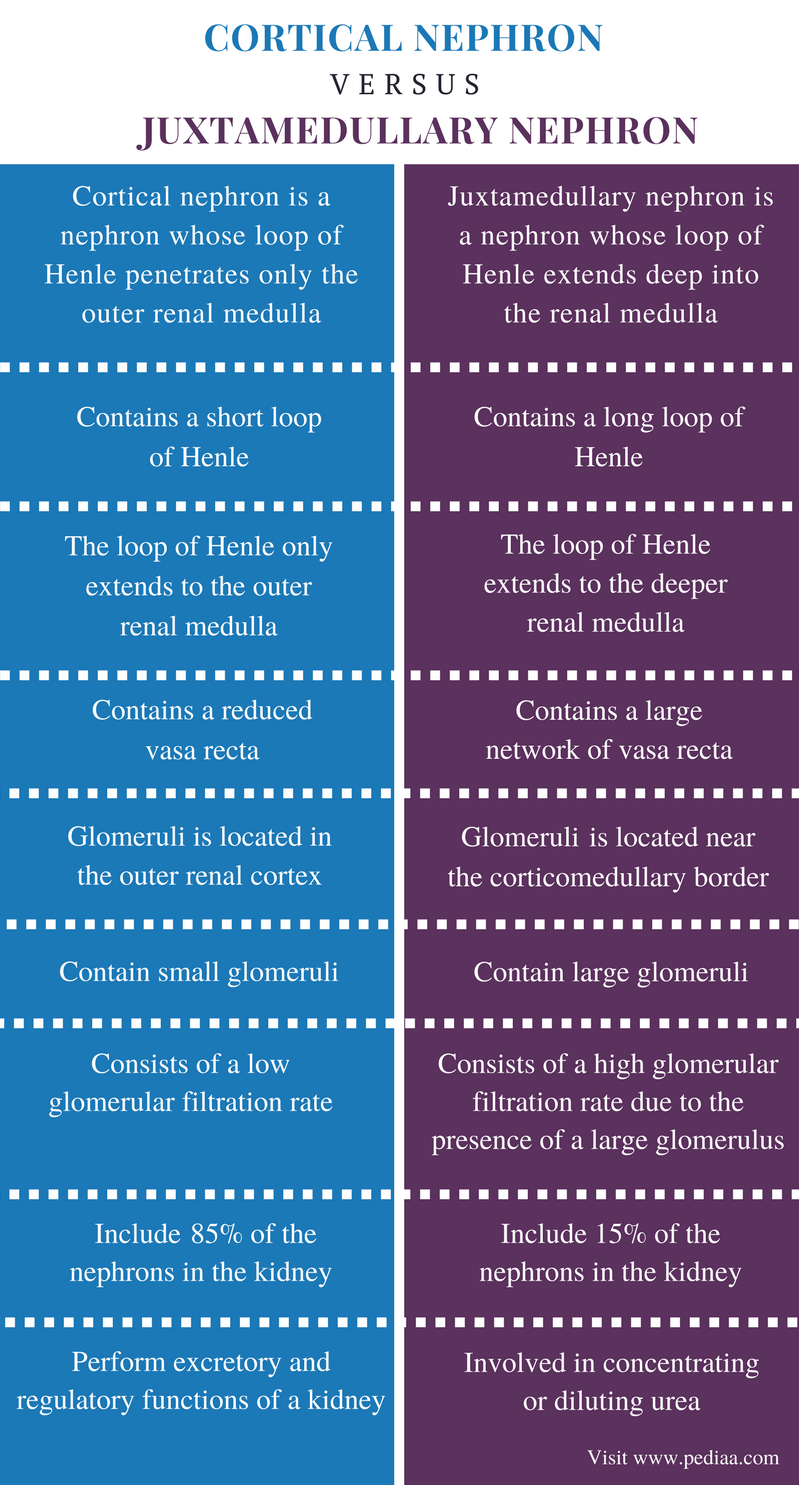
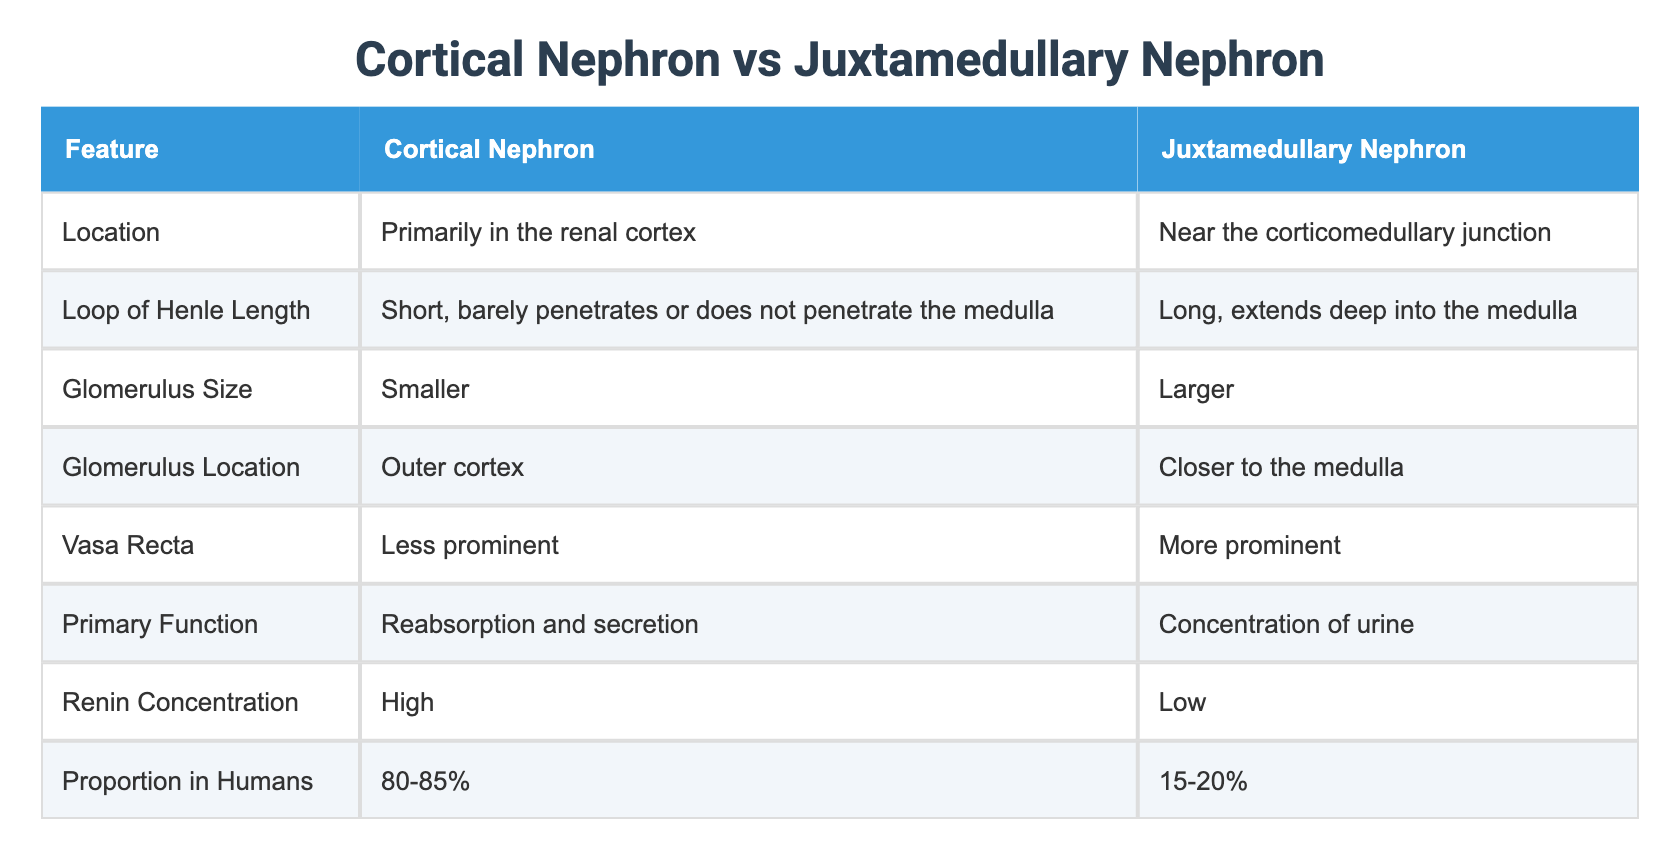
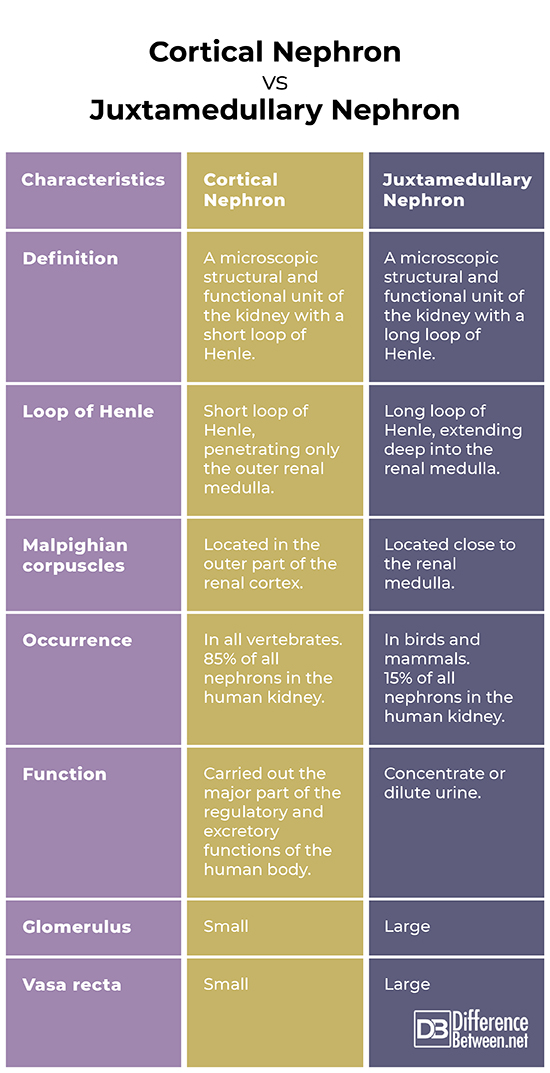
The kidney contains two structurally and functionally distinct types of nephrons. They are not interchangeable. They serve different purposes, respond differently to physiological stress, and their relative distribution varies by species and health status. Most textbooks present them side by side without emphasizing just how different they actually are in practice. I ran into this when reviewing renal histology samples under a microscope and trying to map functional output to structural type. The distinction matters more than you would think from a standard lecture. Cortical nephrons make up about 85 percent of the total nephron population in a human kidney. Their renal corpuscle sits in the outer cortex. The loop of Henle dips only slightly into the medulla, often not past the outer stripe of the outer medulla. This means the vasa recta capillary network around them is less extensive. They rely more on peritubular capillaries for reabsorption and secretion. Filtrate handling here is efficient for routine osmolarity regulation but contributes less to the concentration gradient needed for producing concentrated urine. Juxtamedullary nephrons account for roughly 15 percent but are disproportionately important. Their glomeruli sit deep in the cortex near the corticomedullary junction. The loops of Henle plunge deep into the inner medulla, sometimes reaching the tip of the pyramids. These long loops create and maintain the osmotic gradient through countercurrent multiplication. The surrounding vasa recta act as countercurrent exchangers, preserving that gradient. Without juxtamedullary nephrons, the kidney cannot produce urine significantly more concentrated than plasma. This is not a minor detail. It is the reason you can survive with limited water intake.
Juxtamedullary Nephron Vs Cortical: Structural and Functional Differences
The structural differences drive everything else. Juxtamedullary nephrons have larger afferent and efferent arterioles relative to their size. Their efferent arterioles form the vasa recta, a long looping capillary system. Cortical nephrons have efferent arterioles that branch into a dense peritubular capillary network wrapping around the proximal and distal tubules in the cortex. This anatomical arrangement determines how each type handles solute and water. GFR differs between the two types. Juxtamedullary nephrons typically have a higher single-nephron glomerular filtration rate. The filtration fraction is also slightly higher. This means more plasma is filtered per unit time, but it also means these nephrons are more vulnerable to ischemic injury when renal blood flow drops. I saw this play out in a case where a patient with severe hypotension from sepsis developed acute tubular necrosis primarily affecting the outer medulla and deep cortex. The juxtamedullary nephrons took the hit first because they depend on steady perfusion to maintain their long loops and the vasa recta. Angiotensin II responds differently to each type. It preferentially constricts the efferent arterioles of cortical nephrons at low concentrations, helping maintain GFR during mild volume depletion. At higher concentrations, it constricts afferent arterioles across both types, which is useful for conserving sodium but harmful if prolonged. This is why chronic angiotensin-converting enzyme inhibitor use requires monitoring of creatinine, especially in patients with underlying renal artery stenosis affecting the deeper nephron beds.
Nephron count and compensation deserve attention. Humans are born with roughly one million nephrons total, and about 150,000 of them are juxtamedullary. Loss of nephrons through disease is not replaced. The remaining nephrons hypertrophy. This compensation works for a while but increases intraglomerular pressure and accelerates sclerosis in surviving units. The juxtamedullary nephrons are particularly important to preserve because losing them degrades concentrating ability faster than losing an equivalent number of cortical nephrons. A patient who loses juxtamedullary function may present with polyuria and isosthenuria before any significant drop in overall GFR becomes apparent. There is a common misconception that cortical nephrons are the "standard" and juxtamedullary ones are specialized variants. They are both standard. Neither is primitive or secondary. The 85 to 15 split reflects a balance between efficiency in routine filtration and the need for extreme concentration ability when conditions demand it. Evolution did not design one as a backup for the other. In pathological conditions like diabetes insipidus, the damage is primarily functional rather than structural. The loops of Henle in juxtamedullary nephrons still exist, but without adequate antidiuretic hormone, the collecting ducts cannot respond to the gradient those loops created. The water reabsorbed in the proximal tubule remains in the filtrate regardless of what the loop did. This is why patients with central diabetes insipidus produce large volumes of dilute urine even though their juxtamedullary architecture is intact. Desmopressin replaces the missing hormone, and the concentrating mechanism resumes. It is a straightforward treatment once the diagnosis is correct, but misdiagnosing partial nephrogenic diabetes insipidus as central can waste weeks because the kidney itself is unresponsive to the analog.
Get the Full Details
Another practical point: when you are studying renal physiology or reviewing lab values, remember that serum osmolality and urine osmolality tell you about the functional state of the juxtamedullary system more than the cortical one. A urine osmolality below 100 mOsm/kg indicates either a profound water excess or a failure of the medullary gradient. Values between 300 and 900 reflect mixed function. Above 1200 means the juxtamedullary nephrons and the collecting duct response are working well together. Anything in between warrants a water deprivation test to distinguish primary polydipsia from partial defects. The bottom line is that the distinction between these two nephron types is not academic. It shows up in clinical decisions about fluid management, drug dosing, and interpreting renal function tests. Knowing which type is affected by a pathology changes the management approach. Cortical nephron loss mostly reduces filtration capacity. Juxtamedullary nephron loss reduces the ability to concentrate or dilute urine independently of filtration rate. Both matter. One matters differently.