What Actually Happens When You Treat Levator Ani Syndrome With Physical Therapy
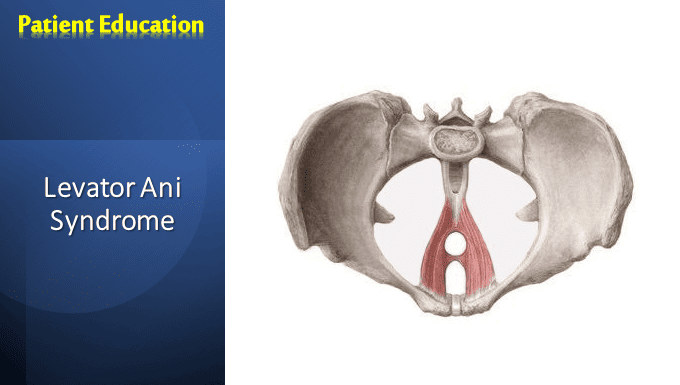
Most people walking into a pelvic floor PT clinic for levator ani syndrome expect one thing: someone pressing on the inside of the rectum and telling you to relax. That's part of it, yes, but the actual work is more complicated than that. The levator ani complex — puborectalis, pubococcygeus, iliococcygeus — is a group of muscles that often develop chronic hypertonicity without any clear external cause. You sit, you stress, you breathe shallowly for months or years, and suddenly you're feeling a constant dull ache or sharp spasm deep in the pelvis. Not during bowel movements necessarily. Not during sex necessarily. Just... there. All the time. I've worked with patients whose symptoms mapped almost perfectly onto levator ani syndrome, and another group where the pain was actually referred from the hip flexors or piriformis, and nobody caught it for six months because everyone assumed it was the pelvic floor. One patient in particular — male, early 40s, chronic lower pelvic pain for two years — had been doing internal releases on his own with a bioparrot wand for eight months before he finally saw a pelvic floor PT who actually assessed the rest of his kinetic chain. Turns out his left hip flexor was so shortened it was pulling on the psoas, which was tethering the lumbar spine, which was altering his breathing pattern, which meant his diaphragm wasn't descending properly, which meant his pelvic floor had zero slack to work with. The levator ani was just the final domino. We spent the first three sessions working on his diaphragmatic breathing and hip flexor length before we ever talked about internal work. His pain dropped from a seven to a three in four weeks.
Levator Ani Syndrome Physical Therapy
Here's the practical breakdown of what an actual course looks like. Initial evaluation takes about 60 minutes and involves an external assessment of the spine, hips, and abdomen, followed by an internal rectal or vaginal exam to palpate the levator ani muscles specifically. The therapist is feeling for trigger points, bands of tension, asymmetry, and referral patterns. They're pressing along the puborectalis sling, the iliococcygeus plane, and the coccygeal attachments. You'll be asked to bear down, to contract, to relax. This is where most patients get surprised — the exam itself can reproduce your exact symptoms, sometimes worse than what you feel day to day. It's uncomfortable but not damaging, and it gives the therapist a map. From there, treatment typically involves a combination of internal myofascial release, external myofascial release, down-training techniques, and lifestyle modification. Internal release uses lubricated gloved fingers or small tools like the Periflex or Wiggly Buddy to press into trigger points within the levator ani. Each point is held for 30 to 90 seconds until you feel a release — a melting or softening sensation — not until it hurts. The old school approach of "no pain no gain" doesn't apply here. Aggressive internal work on an already hypertonic muscle usually makes it worse. You'd be surprised how many patients come in having done their own internal work too aggressively and ended up in worse shape than when they started. Down-training is the part people skip and regret. This means teaching the pelvic floor to lengthen and relax rather than just "strengthen." Standard Kegel exercises are almost never appropriate for levator ani syndrome and usually make things worse. Instead, you're working on reverse Kegels — gentle bearing down without engaging the abs or glutes — diaphragmatic breathing with full pelvic floor descent on the inhale, and progressive relaxation sequences. One technique that works well: lying on your back with knees bent, placing one hand on your chest and one on your lower abdomen, breathing so that only the abdominal hand rises on the inhale and falls on the exhale. The goal is to feel the perineum descend slightly with each breath. At first you won't feel much. That's normal. After a few weeks it becomes more noticeable.
External work targets the surrounding musculature that contributes to the problem. The adductors, glutes, piriformis, hip flexors, and abdominal wall all have fascial connections to the pelvic floor. Tightness anywhere in that ring creates tension elsewhere. I recommend starting with gentle stretching of the inner thighs and hip rotators, plus foam rolling the glutes and the quadratus lumborum. The QL is an underrated player here — it attaches to the 12th rib and the transverse processes of L1 through L4, and its fascial continuity runs directly into the pelvic diaphragm. A tight QL changes the resting position of the pelvis in subtle but significant ways. Bowel retraining is another component that gets ignored. Constipation and straining keep the levator ani in a chronic state of overload. If you're not having regular, soft, complete bowel movements, the internal work you're doing in PT is fighting an uphill battle. Increased fiber, adequate hydration, and possibly a gentle osmotic laxative like polyethylene glycol can make a real difference. Don't use stimulant laxatives long term. They create dependency and can worsen pelvic floor dyssynergia over time. The timeline is somewhere between 8 and 16 sessions over 3 to 6 months for most people. Some improve faster. Some don't improve as much as they'd like. There's no way to predict it precisely. What I can tell you is that patients who do their home exercises consistently — daily diaphragmatic breathing, daily gentle stretching, daily awareness practice — tend to progress faster than those who only work on the muscles during appointments. The PT sessions are guidance. The actual remodeling happens in the 23 hours a day you're not in the clinic.
Get the Full Details

There are cases where pelvic floor physical therapy simply won't solve the problem. If the pain is primarily neuropathic — pudendal neuralgia, for instance — or if there's an underlying structural issue like pelvic congestion syndrome or endometriosis, PT alone will fall short. You need the right diagnosis first. Another limitation: some patients have such severe hypertonicity and guarding that they can't tolerate internal examination for months. In those cases, you start entirely external — breathing work, external release, nerve gliding, and gradual desensitization — before even attempting internal work. Pushing too early just reinforces the fear-tension cycle. Also worth noting: this isn't cheap. A full course of pelvic floor PT can run anywhere from $2,000 to $6,000 out of pocket depending on your location and insurance coverage. Some insurance plans cover it with a physician referral. Some don't. Check before you commit. You can find a qualified therapist through the American Physical Therapy Association's Pelvic Health section or the Herman and Wallace Pelvic Rehabilitation Institute directory. Look for someone with a GCS or WCS credential, or at minimum extensive pelvic health continuing education. Not all physical therapists are trained in this, and the ones who aren't can do more harm than good by applying generic protocols to a highly specific problem. The one piece of advice that matters most: stop trying to manage this alone for longer than three months. Levator ani syndrome doesn't typically resolve on its own, and the longer you wait, the more entrenched the neuromuscular patterns become. Chronic hypertonicity creates its own feedback loop — the muscle stays tight because the nervous system perceives a threat, and the nervous system perceives a threat because the muscle stays tight. Breaking that loop requires professional guidance. Everything else is just maintenance after the real work is done.