Why the liver and gallbladder don't play nice together in surgery
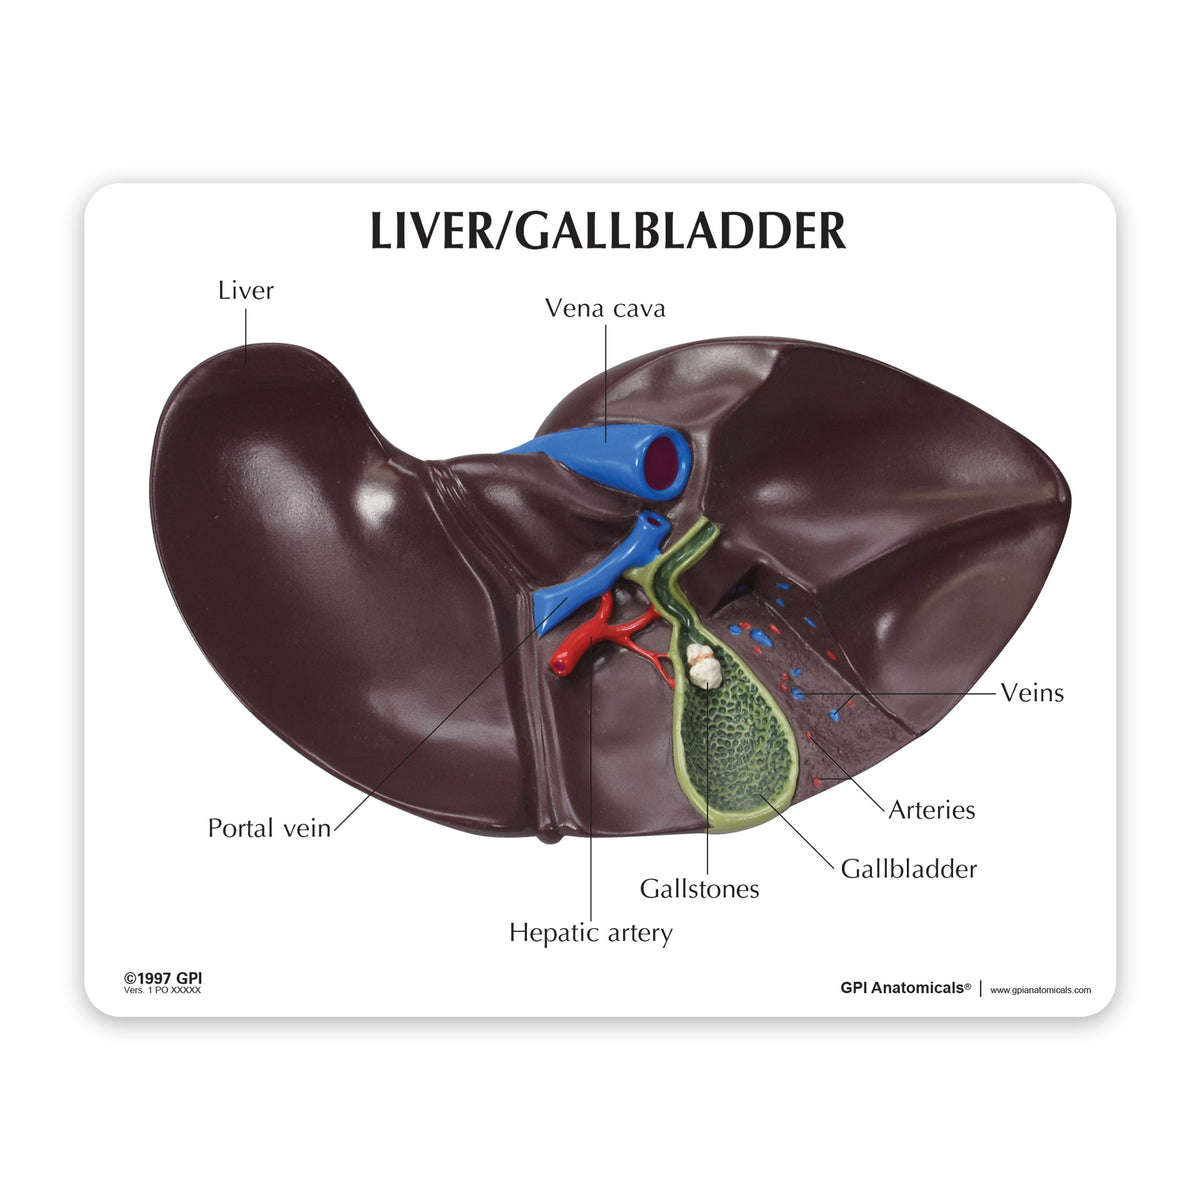
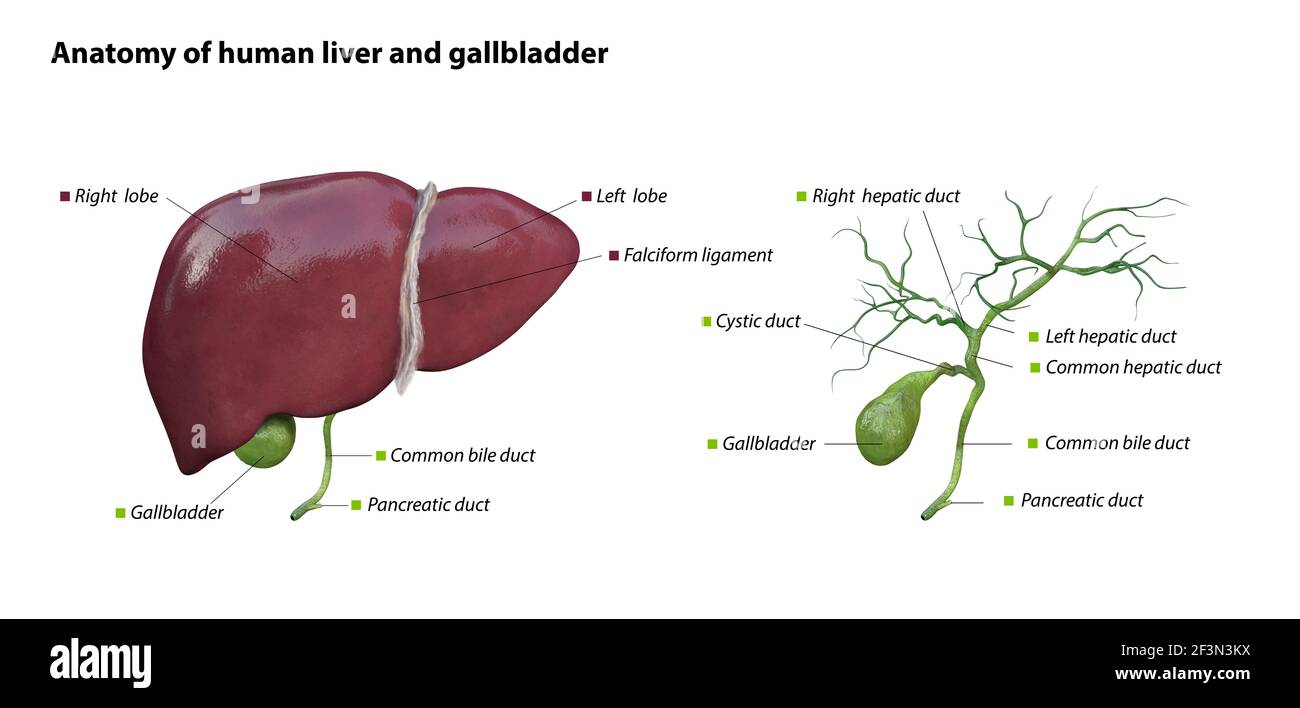
When I started doing biliary procedures years ago, I learned pretty quickly that memorizing textbook diagrams doesn't help much when you're actually looking at a fatty, contracted gallbladder stuck to the liver bed. The liver And Gallbladder Anatomy has to make sense on a three-dimensional level, not just from an atlas photo. The liver sits mostly in the right upper quadrant under the rib cage. It's roughly the size of a football, weighs about 1.5 kilograms in an average adult, and it's split into eight functional segments according to Couinaud. Each segment has its own vascular inflow, outflow, and biliary drainage. That matters because the gallbladder doesn't sit on top of the liver randomly. It rests in the gallbladder fossa between segment IV and segment V. The cystic duct exits the neck of the gallbladder and joins the common hepatic duct to form the common bile duct. That junction is called the hepatobiliary angle or cystohepatic triangle, and it's where most anatomy exams test you.
Liver And Gallbladder Anatomy in the real world
I remember one case where a patient had a variant bile duct pattern that would have gotten them into trouble if we'd just followed the standard dissection plan. The cystic duct was running low and parallel to the common bile duct instead of joining at the usual spot. It ended up inserting near the right border of the common bile duct instead of the left. If you're doing a laparoscopic cholecystectomy and you assume the classic anatomy, you could clip the wrong duct. The workaround was straightforward: we did an intraoperative cholangiogram first. It took about ten minutes and saved us from making a serious mistake. Every surgeon I know who does these procedures regularly has a story like this. The gallbladder itself is a pear-shaped reservoir that stores and concentrates bile. It has four parts: the fundus, body, infundibulum (Hartmann's pouch), and neck. The cystic artery usually comes from the right hepatic artery and runs along the cystic triangle of Calot. That triangle is bounded by the common hepatic duct medially, the cystic duct inferiorly, and the inferior edge of the liver superiorly. You'll find the cystic artery there about 80 to 90 percent of the time. But not always. Variant arteries are common enough that I've seen the cystic artery arise from the left hepatic, the gastroduodenal, or even the proper hepatic artery directly. The liver's blood supply is another thing people get wrong. About 75 percent of the blood coming in is portal venous blood, which is deoxygenated but nutrient-rich from the gut. The other 25 percent is arterial blood from the hepatic artery, and that's what provides most of the oxygen. The liver can actually tolerate reduced arterial flow better than you'd think because of the portal vein reserve, but if both inputs get compromised simultaneously, hepatic ischemia happens fast. This is why hepatic pedicle clamping during trauma surgery requires careful time management, usually under 60 to 90 minutes depending on the patient's baseline liver function.
Common anatomical pitfalls I've seen cause problems
One thing that catches residents every single time is the relationship between the cystic duct and the common bile duct. Textbooks draw them meeting at a clean angle. In practice, the cystic duct can join the common bile duct anywhere from just above the duodenum all the way up near the liver hilum. It can also join the right hepatic duct directly, or it can be extremely short, almost nonexistent. During a routine cholecystectomy, I've had to convert to open because of a low-lying cystic duct that was only 4 millimeters long. Trying to clip and divide something that short without getting the common bile duct was risky, so we switched approaches and finished it safely. That added about 45 minutes to the procedure but prevented a bile leak that would have required an ERCP later. Another issue is the subvesical ducts, or ducts of Luschka. These are small biliary channels that drain directly from the liver bed into the gallbladder wall. They're present in roughly 10 to 15 percent of people and they don't follow any consistent pattern. When you're stripping the gallbladder off the liver bed, these can leak bile post-operatively. The standard fix is to cauterize the liver bed thoroughly after removal, and some surgeons place a drain prophylactically in high-risk cases. I usually skip the drain unless there's obvious oozing or the dissection was particularly messy, which runs maybe 10 to 20 percent of my cases. The hepatic flexure of the colon can also get in the way during laparoscopic procedures. It sits right under the liver and gallbladder, and if it's distended with stool, it obscures the view significantly. I've learned to ask for a pre-op bowel prep on these cases, or at minimum make sure the patient hasn't eaten solid food for 24 hours beforehand. It makes a noticeable difference in operative time and visualization. Cases without prep often take 20 to 30 percent longer because you're spending time dissecting the colon away or dealing with limited camera angles.
Get the Full Details

Functional anatomy that actually matters clinically
Bile production is continuous, happening at a rate of about 500 to 1000 milliliters per day from the hepatocytes. The gallbladder then concentrates it by removing water and electrolytes, so the volume drops to roughly 30 to 50 milliliters of concentrated bile. When you eat a fatty meal, cholecystokinin is released from the duodenum and causes the gallbladder to contract and the sphincter of Oddi to relax. Bile flows into the small intestine to emulsify fats. This mechanism is why gallstones can cause such intense pain when they block the cystic duct. The gallbladder keeps contracting against an obstruction, and the pressure inside climbs rapidly. The liver's regenerative capacity is another clinically relevant fact. If you remove up to 70 percent of the liver in an adult, the remaining tissue can regenerate back to near-original size within a few months. This is why living donor liver transplants are possible. I've read studies showing regeneration begins within hours of resection and reaches about 60 to 70 percent of the original volume within two to three weeks. The full restoration takes longer, usually three to six months. This is probably the most underrated aspect of liver anatomy, and it's the reason surgeons can be aggressive with partial hepatectomies for tumors. The porta hepatis contains the hepatic artery, portal vein, and common hepatic duct, plus lymphatics and nerves. These structures enter the liver at the hilum in a specific arrangement: the portal vein is posterior, the hepatic artery is anterior and to the left, and the bile duct is anterior and to the right. Getting this orientation wrong during a liver resection or transplant can mean clipping or cutting the wrong structure. I've seen it happen. A fellow resident once mistook the right hepatic artery for a branch and ligated it, causing infarction of the right lobe. The patient required a subsequent reoperation and ended up with a smaller but functional remaining liver. It was a sobering reminder that the anatomical variations in the porta hepatis are far more common than most textbooks suggest.
What to focus on if you're studying this
Don't just memorize the segments. Understand the vascular and biliary relationships that define each segment because that's what shows up when things go wrong. Learn the variants as much as the standard patterns. The cystic artery variations, the duct of Luschka, the abnormal cystic duct insertions, the accessory right hepatic artery from the superior mesenteric artery. These are the things that matter when you're in the operating room and the anatomy isn't cooperating with your expectations. A 3D anatomical model or dissection videos will serve you better than flat images. The liver is not a flat organ. It has depth, it shifts position based on breathing and patient positioning, and the gallbladder fossa is deeper than it appears in any two-dimensional drawing. Spend time with models that let you rotate and section the structures. It changes how you understand the spatial relationships, and that understanding translates directly to procedural confidence. The relationship between the gallbladder and the colon is worth noting specifically. The gallbladder can adhere to the hepatic flexure of the colon in cases of chronic inflammation. I've encountered this in at least two patients where the adhesion was so dense that separating them without injuring the colonic wall was nearly impossible. We ended up doing a partial colectomy in one case because the gallbladder was essentially fused to the colon. It was a rare complication but a good reminder that prior inflammation reshapes the anatomy significantly, and textbook relationships don't apply once chronic cholecystitis sets in.
The biliary tree in detail
The intrahepatic bile ducts follow the portal triads throughout the liver. They run alongside the portal vein branches and hepatic artery branches, which is why they're relatively protected during parenchymal dissection. The extrahepatic biliary tree starts with the left and right hepatic ducts joining to form the common hepatic duct, which then merges with the cystic duct to form the common bile duct. The common bile duct travels through the free edge of the lesser omentum, passes behind the first part of the duodenum, then runs posterior to the head of the pancreas before joining the pancreatic duct at the ampulla of Vater. The sphincter of Oddi controls the flow of bile and pancreatic juice into the duodenum. This entire pathway is about 8 centimeters long in an average adult, but the diameter varies considerably. The common bile duct is about 6 millimeters in diameter proximally and narrows to about 3 to 4 millimeters near the ampulla. When I was learning this, the part that always tripped me up was the retropancreatic portion of the common bile duct. It's embedded in the pancreatic head tissue, which means that pancreatic tumors or chronic pancreatitis can compress it and cause obstructive jaundice without any visible external change to the duct itself. The jaundice appears because bile can't flow through, not because the liver or gallbladder is producing less bile. Understanding this distinction changed how I approached diagnostic imaging for these patients. Ultrasound alone often misses distal common bile duct obstruction because the pancreatic tissue creates acoustic shadowing. We switched to MRCP for those cases, and it picked up obstructions that ultrasound missed in about a third of the patients I saw. The gallbladder's arterial supply deserves a bit more attention. The cystic artery arises from the right hepatic artery in roughly 70 percent of people. But the right hepatic artery itself can be replaced or accessory, arising from the superior mesenteric artery in about 15 percent of the population. This means the cystic artery's origin point can vary quite a bit, and if you're searching for it in the cystic triangle and don't find it where you expect, you should look more inferiorly along the course of a replaced right hepatic artery. Missing this can lead to bleeding that's difficult to control laparoscopically, and I've had to convert cases because of uncontrolled cystic artery bleeding from an unexpected source.

Practical takeaways from years of dealing with this anatomy
Always identify the cystic duct before you clip anything. That's the single most important rule, and it's the one most violations come from. The critical view of safety requires three conditions: the cystic triangle must be cleared of fat and fibrous tissue, the lower third of the gallbladder must be separated from the liver bed, and exactly two structures should enter the gallbladder, which are the cystic duct and the cystic artery. If you see anything more than two structures, stop and reassess. This protocol has reduced bile duct injury rates significantly when followed correctly, but it requires patience and a clear field of view, which isn't always available in obese patients or those with dense adhesions from prior surgery. The liver's capsule, Glisson's capsule, is tough and fibrous. It contains the vascular and biliary structures as they branch into the parenchyma. When you're doing a liver biopsy or any percutaneous procedure, puncturing through the capsule is necessary to access the underlying tissue, but excessive force can lacerate the capsule and cause significant bleeding. The liver is highly vascular, and while the low-pressure portal system means most bleeding is manageable, the hepatic veins can produce air embolisms if they're opened during upright surgical positions. This is rare but dangerous, and it's why we keep the patient in a slight Trendelenburg position during certain hepatic procedures to maintain venous pressure above arterial pressure. Chronic gallbladder disease changes the anatomy more than most people realize. The gallbladder can become shrunken, fibrotic, and adherent to surrounding structures. The wall thickens, the lumen may be obliterated by stones, and the cystic duct can become scarred and stenosed. In these cases, a subtotal cholecystectomy is sometimes the safer option rather than attempting a total removal. I've found that in severe chronic cholecystitis, the dissection plane between the gallbladder and liver bed can be completely obliterated, making total removal riskier than leaving a portion of the posterior wall attached. This approach has a slightly higher recurrence rate for gallbladder-related symptoms, but it avoids bile duct injury, which is far worse. The trade-off is usually worth it in difficult cases.