Where the apical pulse actually is, and why it isn't always where the textbooks say
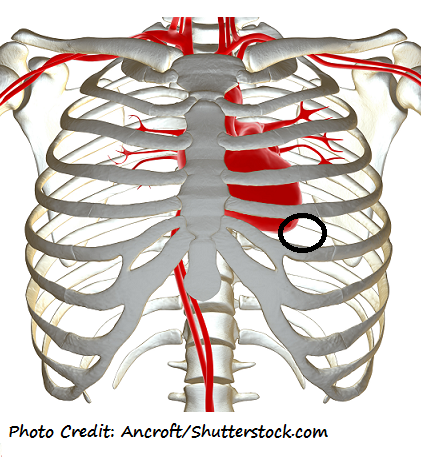
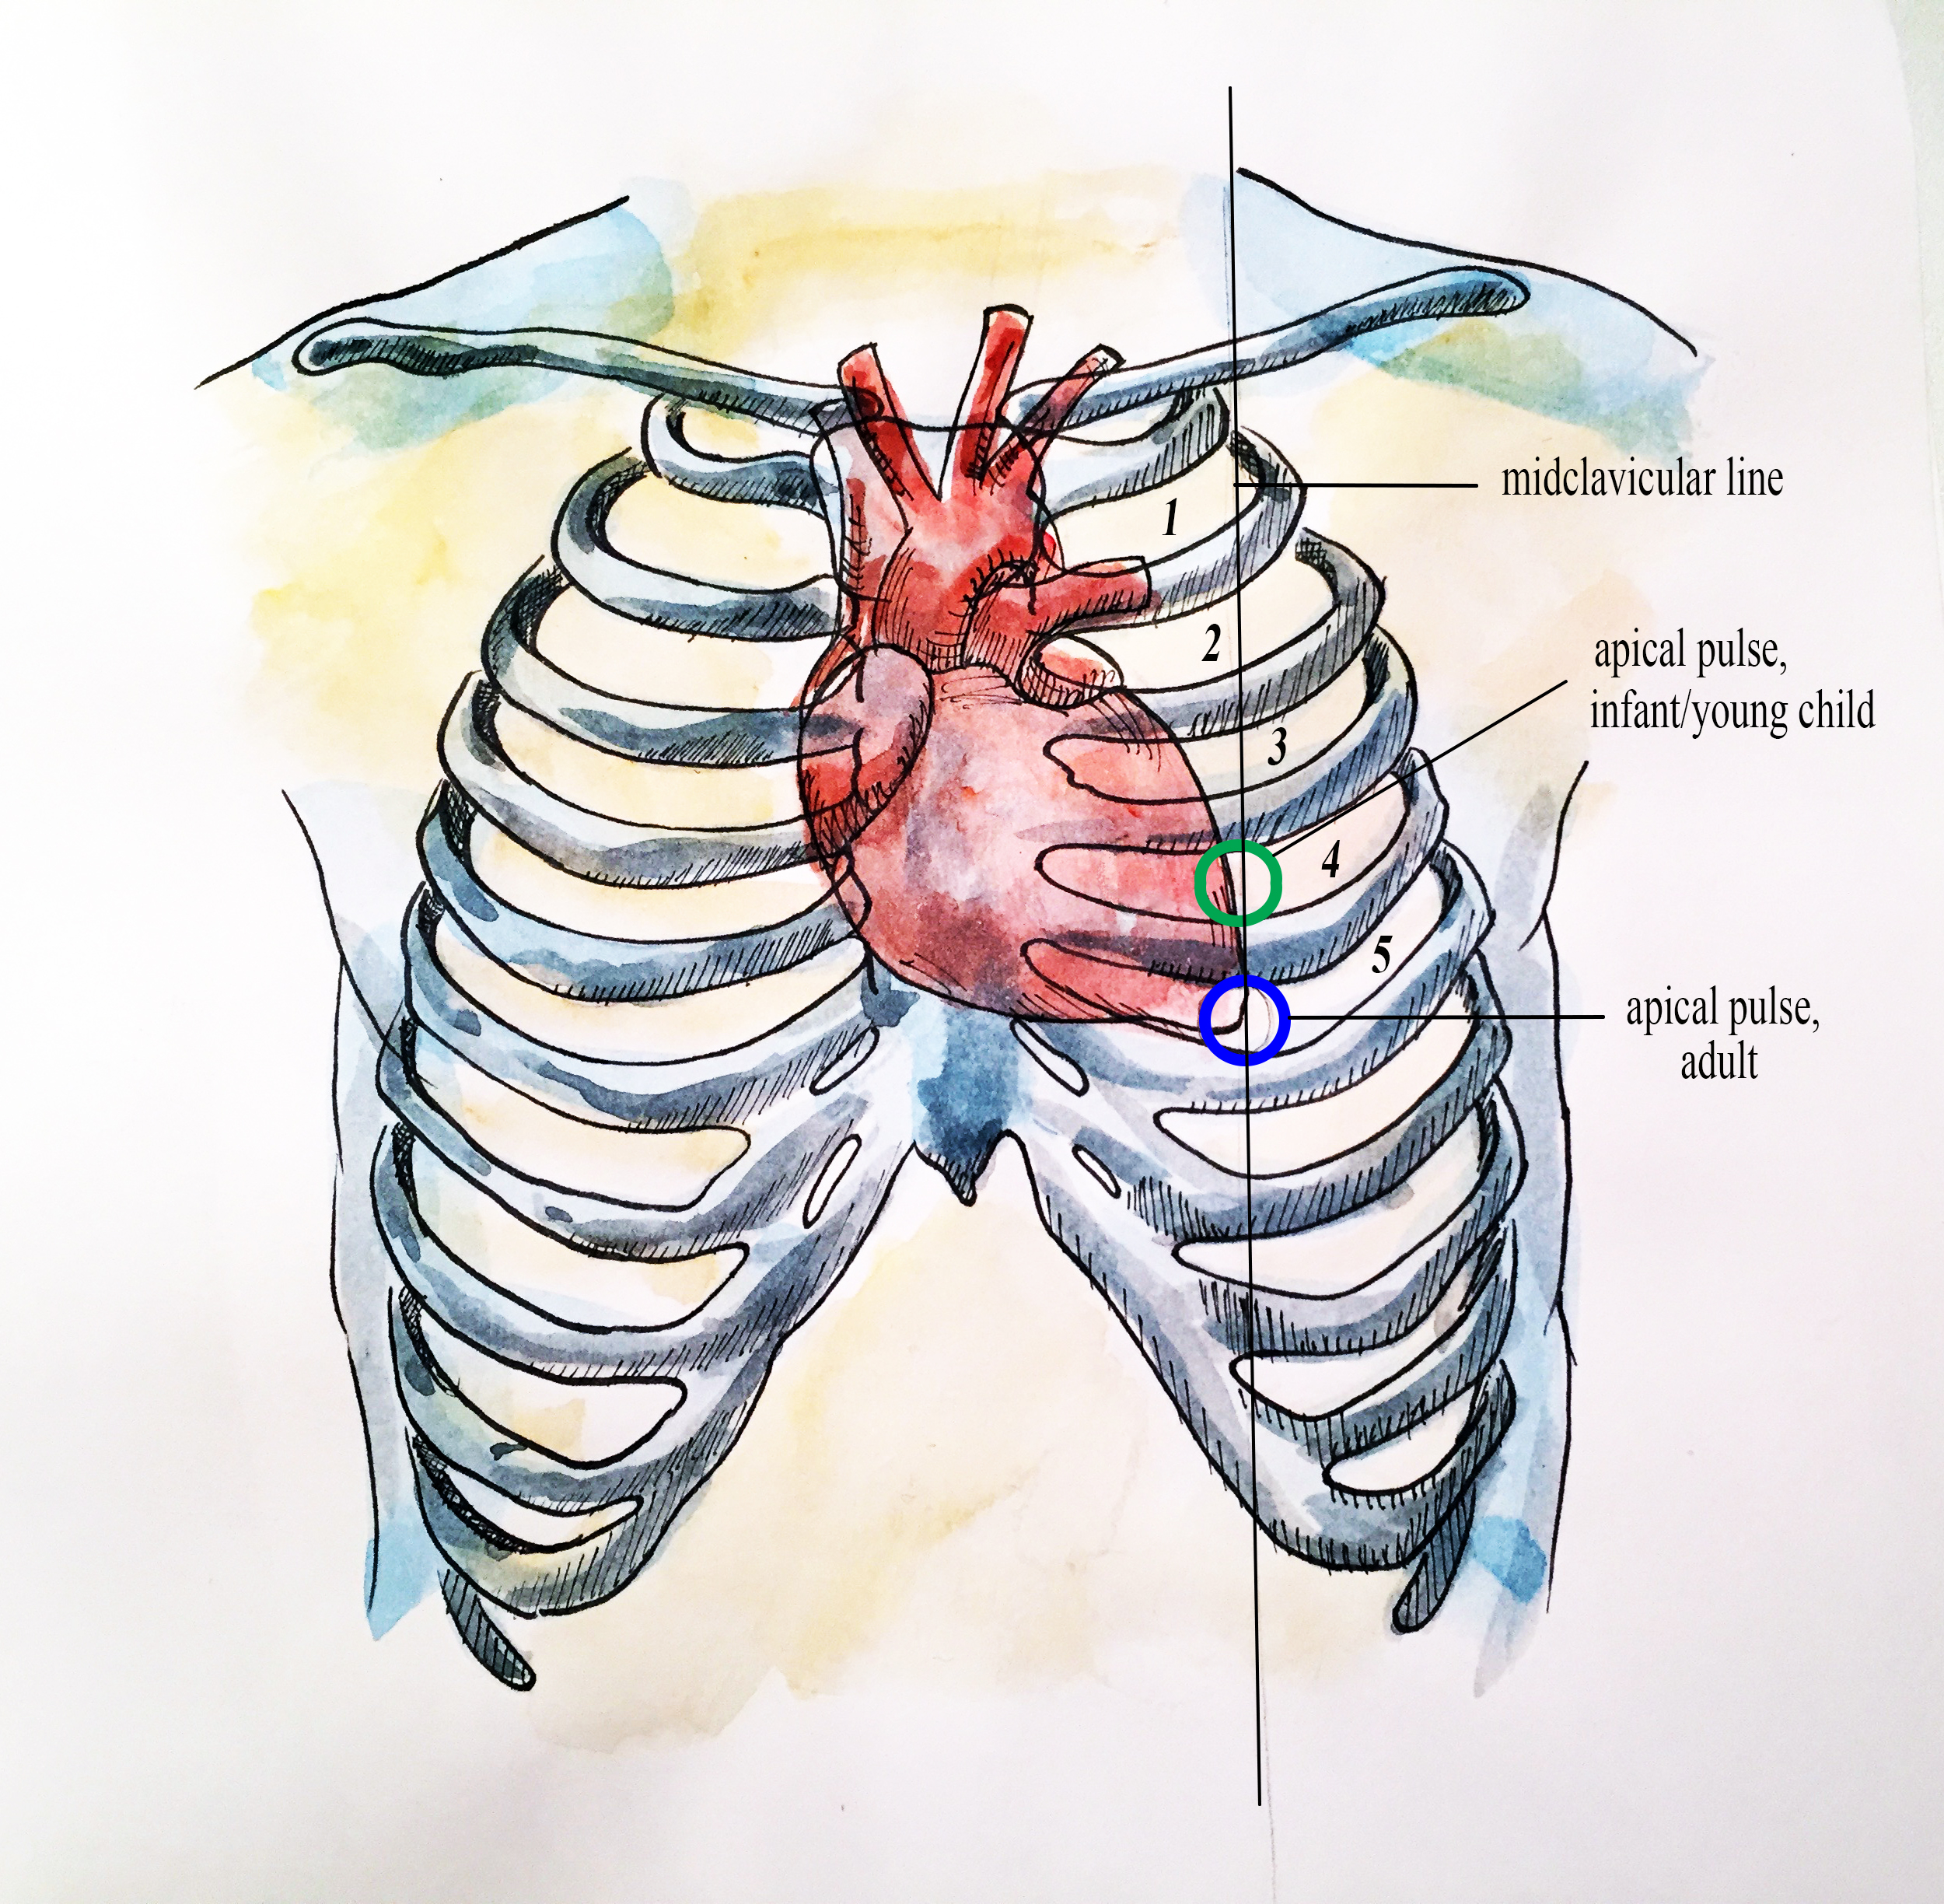
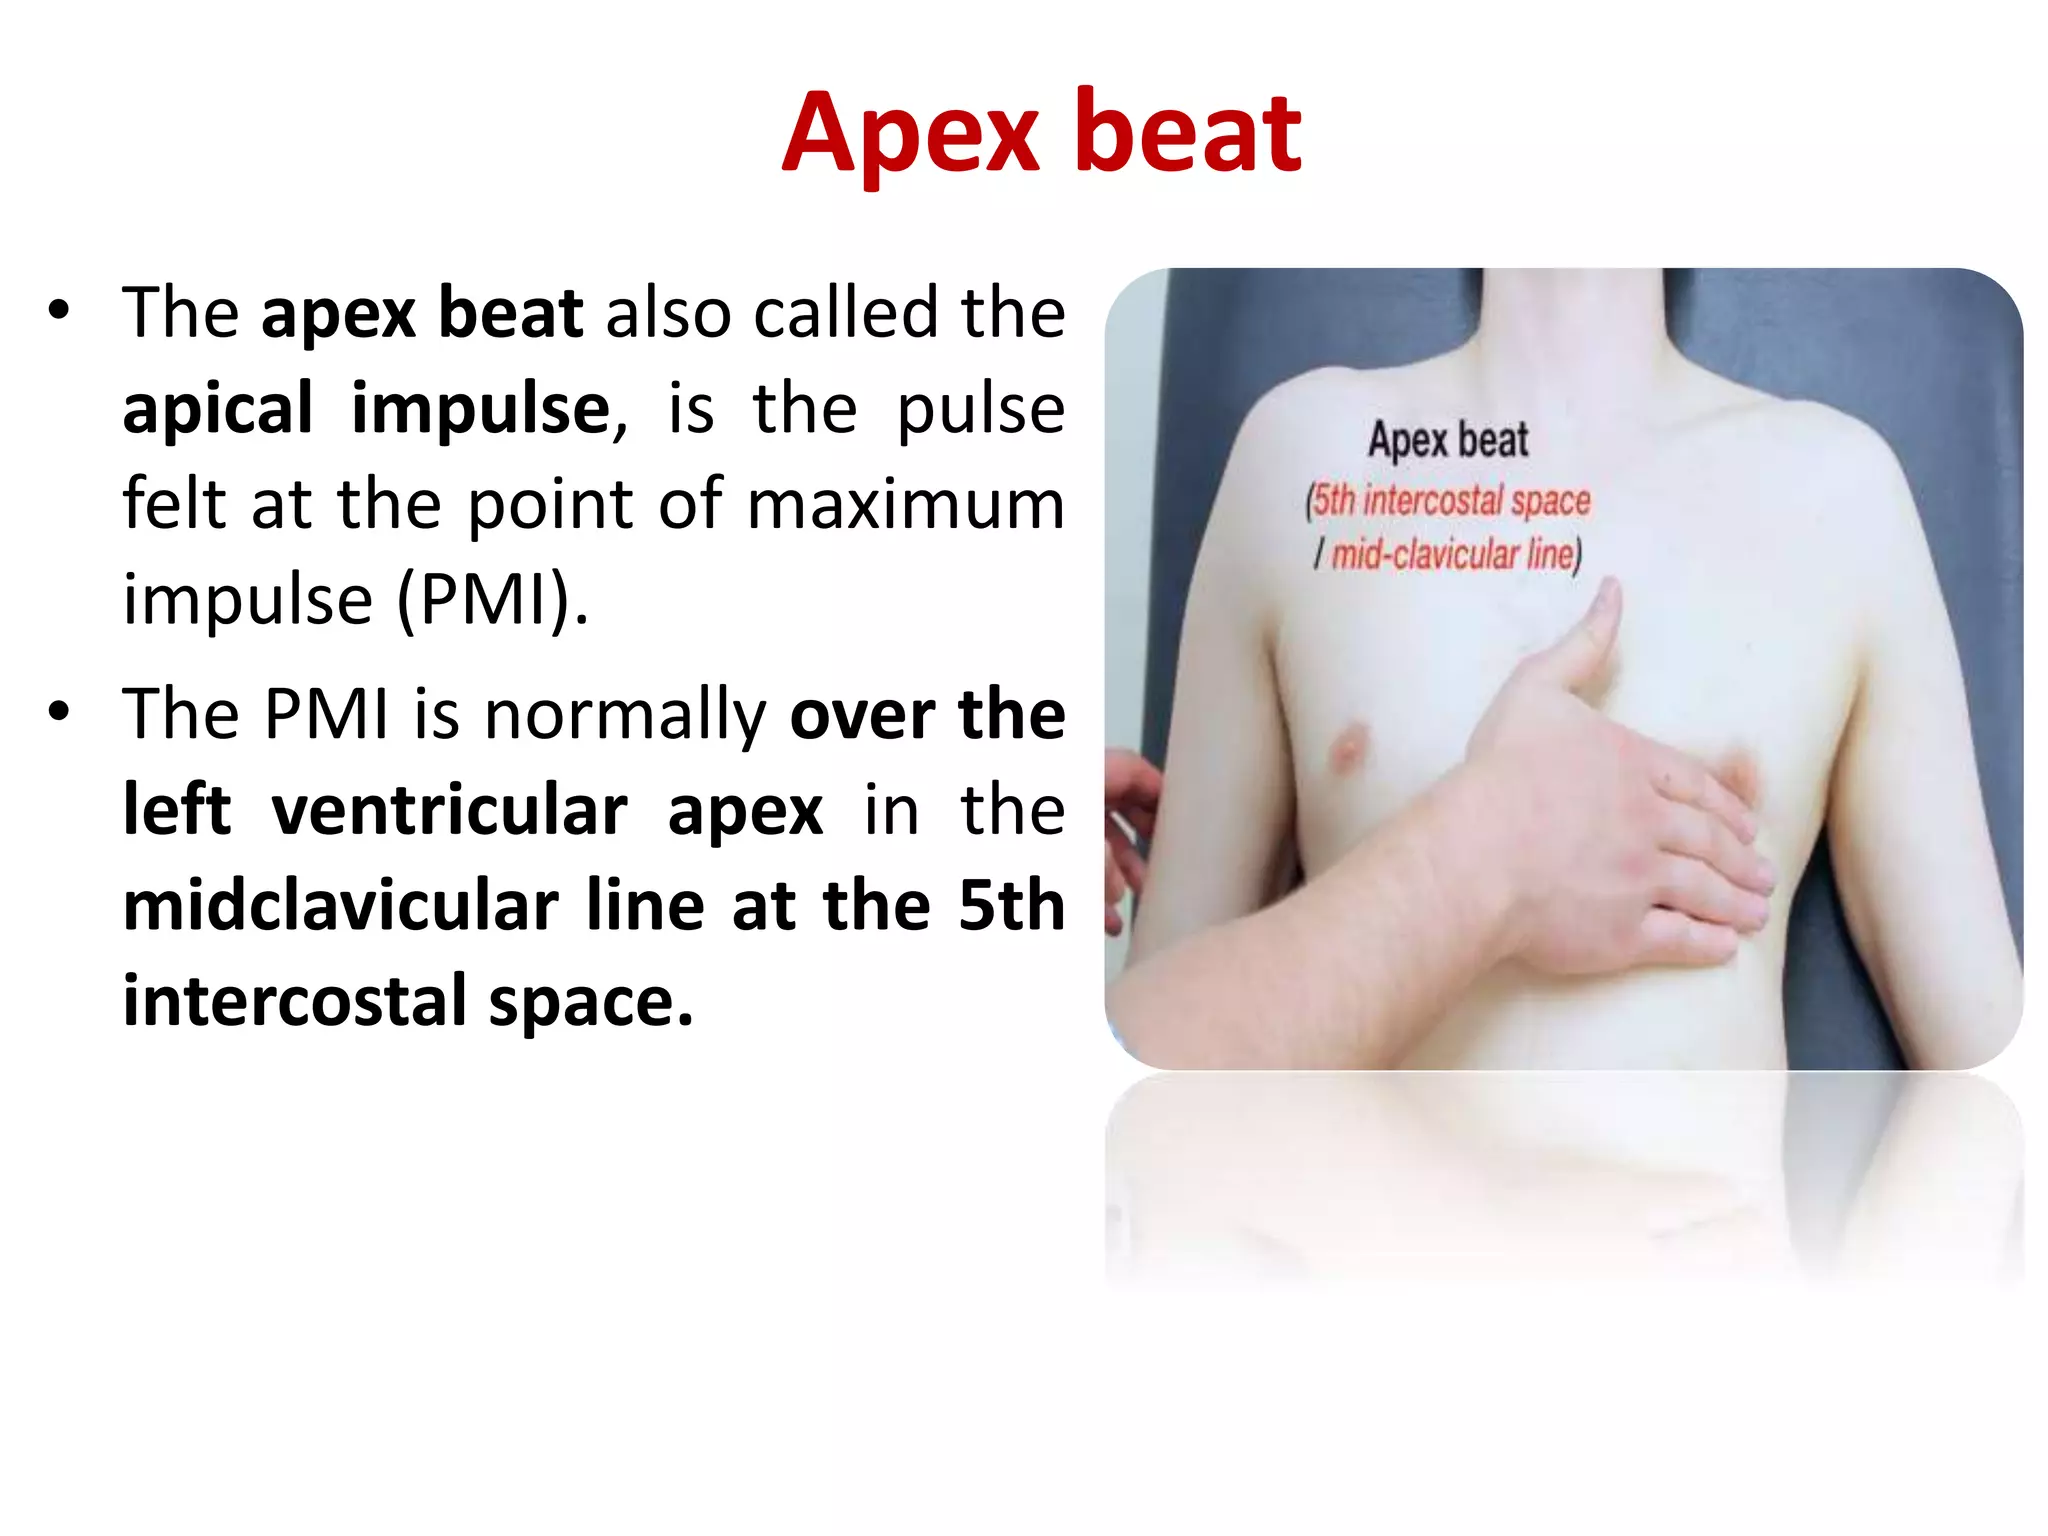
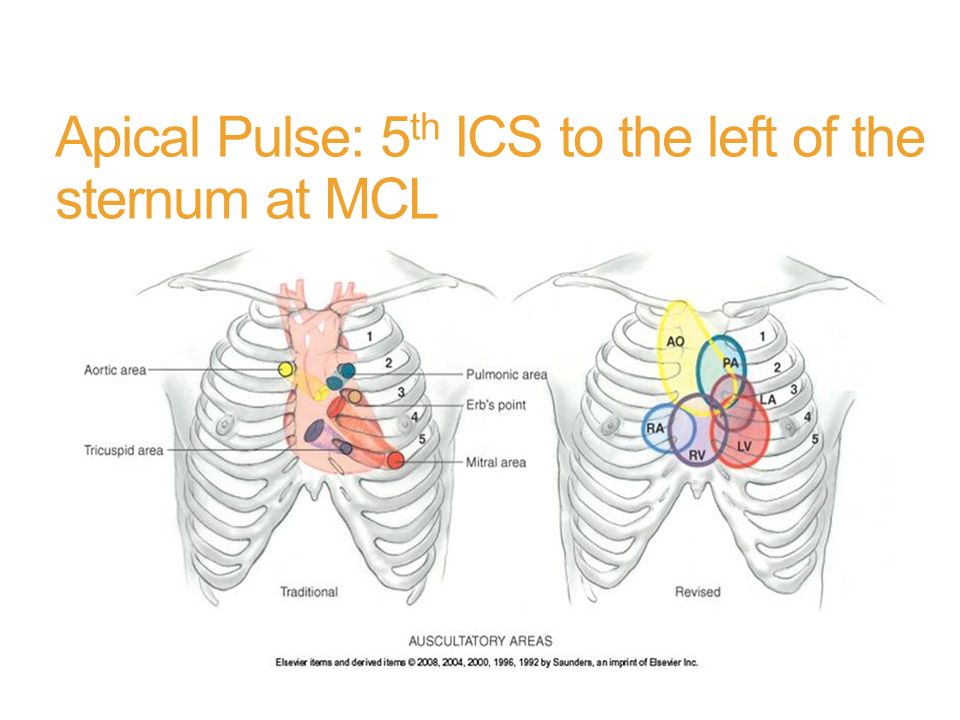
The apical pulse is the heartbeat you feel or hear best at the point where the heart's apex presses against the chest wall. In most adults, that's the fifth intercostal space at the midclavicular line on the left side. That's the textbook answer. It's also the answer that gets people in trouble when they stop paying attention to actual anatomy instead of memorizing landmarks. I need to talk about the method first because the definition alone won't save you when the patient doesn't match the diagram. Palpation is the starting point for everyone, especially if you're in a noisy environment or working with someone whose heart sounds are borderline. You find the point of maximal impulse, or PMI, by lightly pressing your fingertips along the left lower sternal border and then moving laterally and slightly superior until you feel a tapping quality. That tap is your apical pulse. Once you've got it with your fingers, you confirm it with a stethoscope by listening for the first heart sound, S1, at that exact spot. The midclavicular line is your vertical reference. Draw an imaginary line straight down from the midpoint of the clavicle. The fifth intercostal space is your horizontal reference. Count down from the second space. You can find the second space by locating the angle of Louis, that little bumpy ridge where the sternum meets the manubrium and body. The rib just below that ridge is the second rib, and the space underneath it is the second intercostal space. Count down four more spaces and you are at the fifth.
Here is where things get tricky. Obesity changes everything. In patients with a larger chest wall or significant breast tissue, the PMI shifts downward and laterally. I had a patient last year who was BMI 38, and the textbook location gave me absolutely nothing. I felt around the sixth and seventh intercostal spaces, closer to the anterior axillary line, and found the impulse there. Another option in those cases is to have the patient roll onto their left side. That maneuver brings the heart closer to the chest wall and often makes the apical pulse much easier to detect without guessing. Positioning matters more than people admit. Supine is fine for most routine checks, but the left lateral decubitus position is genuinely better for palpation and auscultation of the apical pulse. It should not be treated as a niche technique. I use it regularly when the bedside environment is loud or when I need to document a rhythm change and want the clearest possible signal. Sitting up and leaning forward also changes things, though it is more useful for hearing aortic valve sounds than for finding the apical pulse itself. Auscultation requires a bit more intention than just putting the bell or diaphragm on the chest and hoping for the best. Use the diaphragm. S1 is a higher frequency sound, and the diaphragm is built for that. Place it firmly at the point you identified by palpation, or at the standard fifth intercostal space if palpation was inconclusive. Listen for at least thirty seconds before you declare anything. Heart rate and rhythm are not always obvious in the first ten seconds, especially in atrial fibrillation where the intervals between beats vary in an unpredictable way.
There is a common misconception that the apical pulse rate always matches the radial pulse rate. It does not, and this is something I see missed constantly. In pulse deficits, which happen with premature ventricular contractions, atrial fibrillation, or poor cardiac output, the apical rate will be higher than the radial rate because not every ventricular contraction generates enough stroke volume to open the peripheral arteries. If you only check the wrist, you will underestimate the heart rate. Two-person assessment is the workaround. One person palpates the radial pulse while the other auscultates the apical pulse at the same time, counting for a full minute. The difference between the two counts is your pulse deficit. Left ventricular hypertrophy is another case where the standard location fails. An enlarged left ventricle pushes the apex downward and outward. I worked with a patient who had long-standing hypertensive heart disease, and the impulse was clearly in the sixth or seventh intercostal space, several centimeters lateral to the midclavicular line. Recording the location as the standard fifth space would have been wrong. Document the actual location you find, not the textbook ideal. Emphysema and hyperinflated lungs create their own problems. Air trapping pushes the diaphragm down and can shift the heart's position, making the apical impulse harder to detect by palpation. In those patients, auscultation is more reliable than palpation, and you may need to press the stethoscope slightly harder to get past the lung tissue. Even then, the sound can be muffled, and you might need to try multiple nearby positions to find the best acoustic window.
Get the Full Details

Documentation is where most people cut corners. Write down the exact intercostal space, the relationship to the midclavicular line, and the patient's position when you found it. If it is displaced, note that. If you had to use the left lateral position to detect it, record that too. A location without context is not useful to the next clinician who picks up the chart. They need to know what you actually did to find it, not what you wish you had found. There are limitations to this whole approach. The apical pulse assessment is operator dependent. Your skill, the patient's body habitus, the ambient noise, and the quality of your stethoscope all matter. There is no clean fix for any of that except experience and repetition. In patients with severe obesity, copious lung disease, or altered thoracic anatomy from prior surgery, you may simply not get a clear read. In those situations, an echocardiogram gives you far more information than a stethoscope ever will, and you should move straight to imaging rather than spending twenty minutes pressing on a chest wall that is not going to cooperate. I do not recommend relying on automated blood pressure cuffs or pulse oximeters to estimate apical rate in patients where rhythm accuracy matters. They sample peripherally. If there is any question about pulse deficit or irregular rhythm, they will give you a number that looks clean and is also wrong. The apical assessment remains the reference standard for a reason, even if it is tedious and uncomfortable for both parties.
The practical takeaway is straightforward. Find the PMI by palpation first. Confirm it with the diaphragm at S1. Account for body habitus, position, and displacement. Check for pulse deficits with a two-person count whenever rhythm is uncertain. Document the real location, not the memorized one. Anything less is just going through the motions.