Why Your Body Chemistry Goes Wild When You Drop Weight
Most people don't realize how much their hormones shift during significant weight loss. It's not just about willpower or calories. The endocrine system reacts to changes in body composition, and those reactions cascade through everything from sleep to libido to mood regulation. Here's what actually happens when you lose a meaningful amount of fat, and what you can do about it.
Understanding Loss And Hormone Therapy
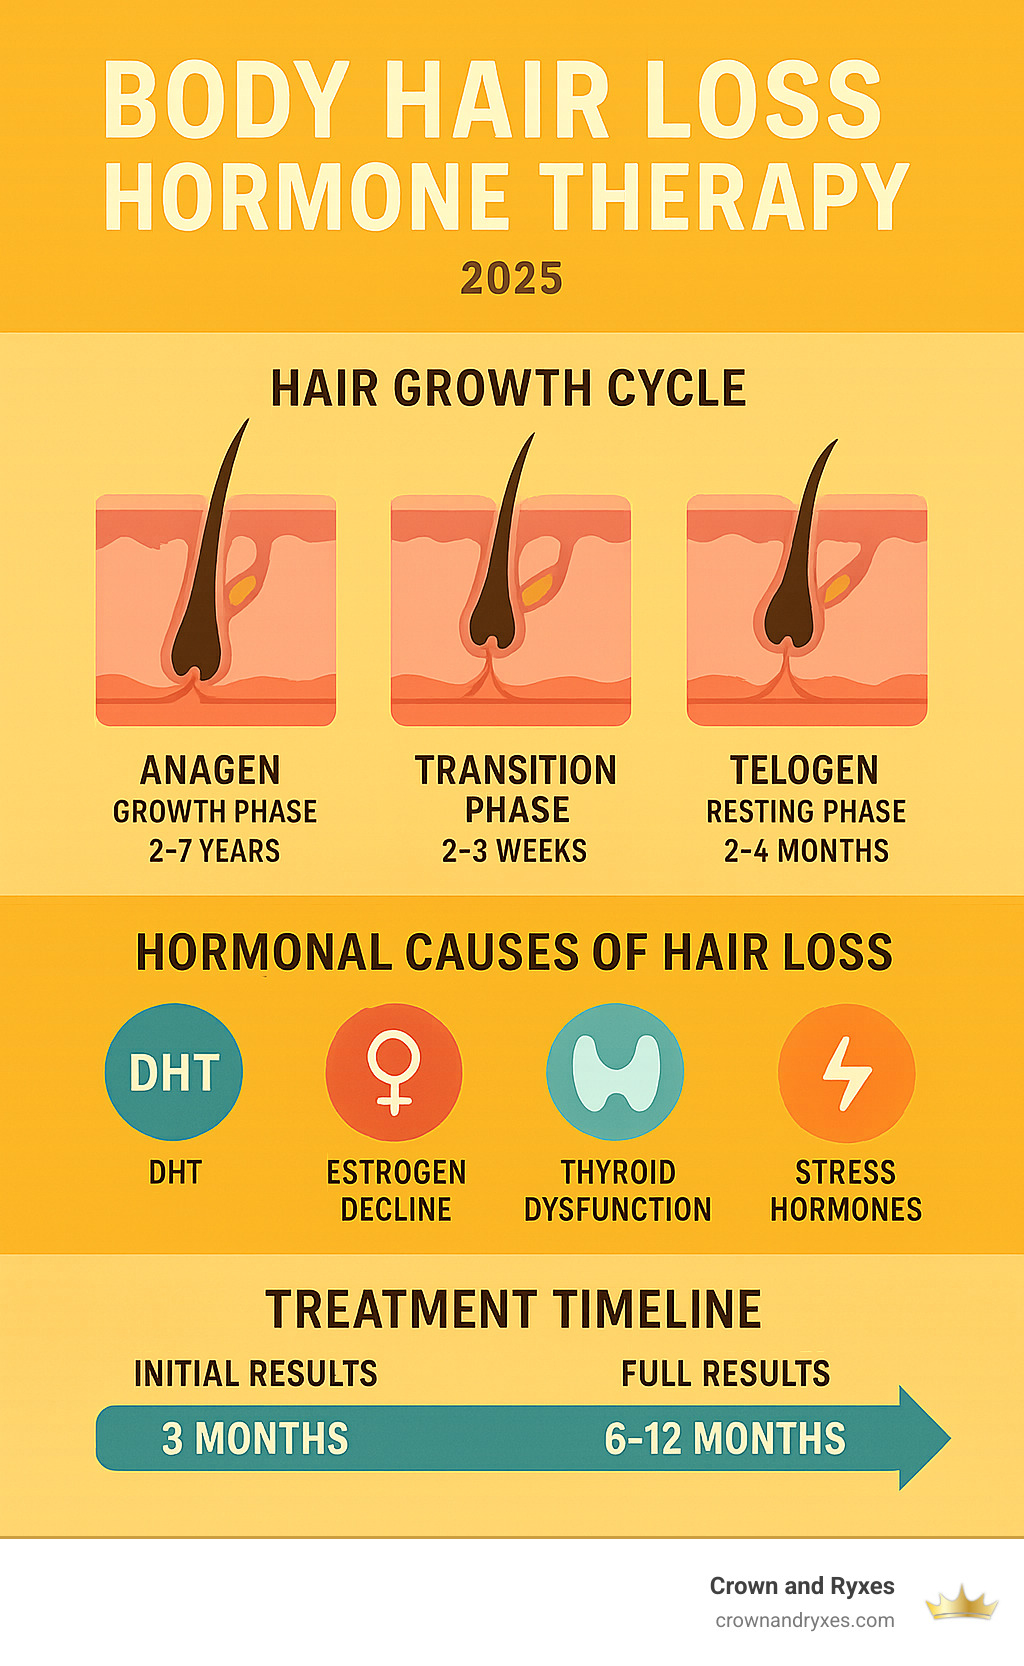
This isn't a single FDA-approved treatment. There's no drug specifically called "Loss And Hormone Therapy." What people are usually referring to is the intersection of two things: the hormonal disruptions that come with substantial weight loss, and the clinical interventions some providers use to manage those disruptions. That distinction matters because a lot of clinics blur the line between evidence-based hormone management and marketing. The hormonal changes are real though. Leptin drops sharply when body fat decreases. Leptin is produced by adipose tissue, so less fat means less leptin. Your brain interprets this as starvation. Ghrelin goes up, which drives hunger. Thyroid hormones (T3 and T4) can decrease, slowing your metabolic rate beyond what you'd expect from just having less body mass. Testosterone may decline in men, and women often experience menstrual irregularities. Cortisol can run elevated, which both promotes fat retention and breaks down muscle tissue. I've seen patients try to push through these symptoms by simply eating harder or training harder, and it doesn't work well. The body is fighting you at a biochemical level now.
What Actually Helps When Hormones Derail Progress
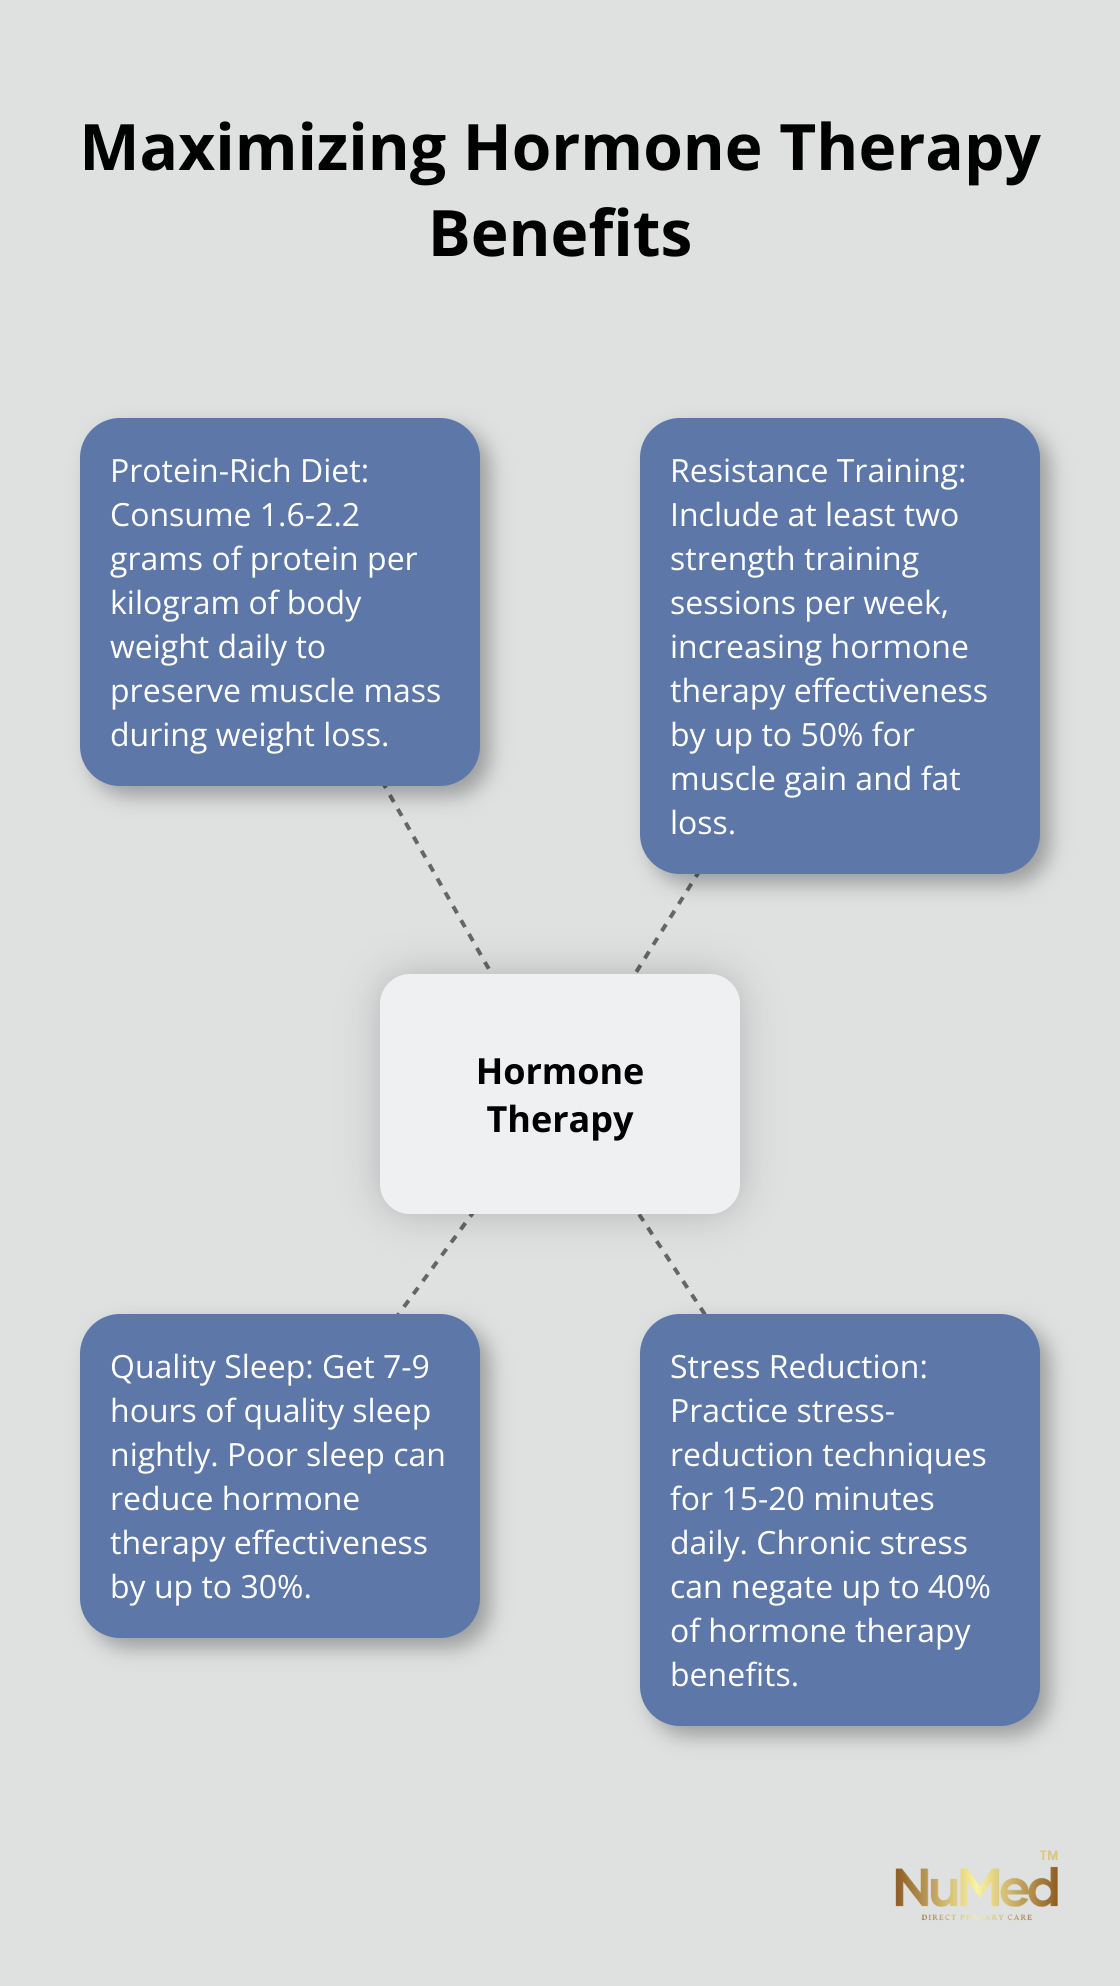
First, the basics that most providers mention but patients undervalue. Resistance training, especially compound lifts, helps preserve testosterone and maintain metabolic rate better than cardio alone. Adequate protein intake—closer to 1.6 to 2.2 grams per kilogram of body weight—supports both muscle retention and hormone production. Sleep matters enormously. Even one week of restricted sleep can reduce testosterone by 10 to 15 percent and increase ghrelin significantly. When lifestyle interventions aren't enough and blood work confirms clinically significant hormonal deficits, that's where medical hormone therapy enters the picture. This is prescription territory. Testosterone replacement for men with confirmed hypogonadism. Thyroid hormone supplementation if TSH and free T3 are abnormal. In women, cyclic progesterone or estrogen support during menopause or post-weight-loss amenorrhea. There's no universal protocol. A patient's numbers dictate everything. The standard approach involves comprehensive panels: total and free testosterone, SHBG, LH, FSH, estradiol, TSH, free T3, free T4, cortisol (salivary or serum), and leptin. Some clinicians also check vitamin D, iron studies, and inflammatory markers because deficiencies in these can mimic or worsen hormonal dysfunction.
Get the Full Details

Things People Miss About This Process
The biggest mistake I see is treating hormone therapy as a shortcut for weight loss itself. It isn't. Hormone optimization can remove a barrier—like low testosterone making it impossible to build muscle or low thyroid slowing everything down—but it won't cause weight loss on its own. Patients who expect TRT to melt fat are setting themselves up for disappointment and potential misuse. Another nuance: post-weight-loss hormonal changes can persist even after weight stabilizes. I had a patient who lost 60 pounds over 14 months and then maintained that weight for another year. His leptin was still suppressed, his thyroid panel still showed low T3, and his testosterone remained on the lower end. The body doesn't automatically reset just because you've hit a new stable weight. Some endocrine adaptations to reduced fat mass appear to be semi-permanent, which is why long-term monitoring matters more than most people expect. Also worth noting: artificial caloric restriction from bariatric surgery creates a different hormonal profile than diet-and-exercise weight loss. Ghrelin suppression after sleeve gastrectomy is dramatic and immediate, but other axes can behave unpredictably. If you're working with a patient who had surgical intervention, the hormone management approach needs to account for that separately.
Red Flags and What to Avoid
Beware of clinics that recommend hormone therapy based on symptoms alone without confirming abnormal lab values. Fatigue, low libido, and weight regain are nonspecific. They overlap with sleep apnea, depression, thyroid disease, medication side effects, and many other conditions. Treating symptoms without diagnostic confirmation leads to overprescription and masks whatever the actual underlying issue might be. Self-prescribing from online telemedicine services that don't do adequate baseline testing is another trap. I've reviewed lab work from patients who started testosterone on their own and then came in with hematocrits above 54 percent, suppressed natural testosterone production, and enlarged prostate issues they didn't have before. It's preventable with proper monitoring. If you're considering any form of hormone intervention, look for a provider who will order the full panel, discuss both risks and benefits, and commit to regular follow-up blood work. The typical monitoring schedule involves rechecking labs at 3 to 6 months after any change, then every 6 to 12 months once stable. That's not optional—it's standard of care.
The bottom line is that significant weight loss disrupts your endocrine system in measurable, sometimes persistent ways. Managing those disruptions with appropriate medical oversight can make a real difference in how you feel and whether you can maintain your results long-term. Ignoring them and hoping they'll resolve on their own rarely works out cleanly.