Getting the Lower Extremity Nerve Anatomy Right
The lower extremity nerves are a mess. That's the honest truth. The lumbosacral plexus gives rise to roughly six major peripheral nerves that carry motor, sensory, and autonomic fibers down each leg, and they branch, recombine, and anastomose in ways that make clean diagrams look deceptively simple. When you're actually trying to localize a lesion or plan a regional block, those clean diagrams become a liability. I work with this stuff clinically, mapping nerve pathways for nerve blocks and interpreting EMG studies. The theory is straightforward enough: L4 through S3 ventral rami form the lumbosacral plexus, which then produces the sciatic nerve, femoral nerve, obturator nerve, and the cutaneous branches like the lateral femoral cutaneous and saphenous. But the practical reality is that anatomy varies more than textbooks admit, and blindly following a textbook pathway will cost you time and patient comfort.
Lower Extremity Nerve Anatomy: What Actually Matters in Practice
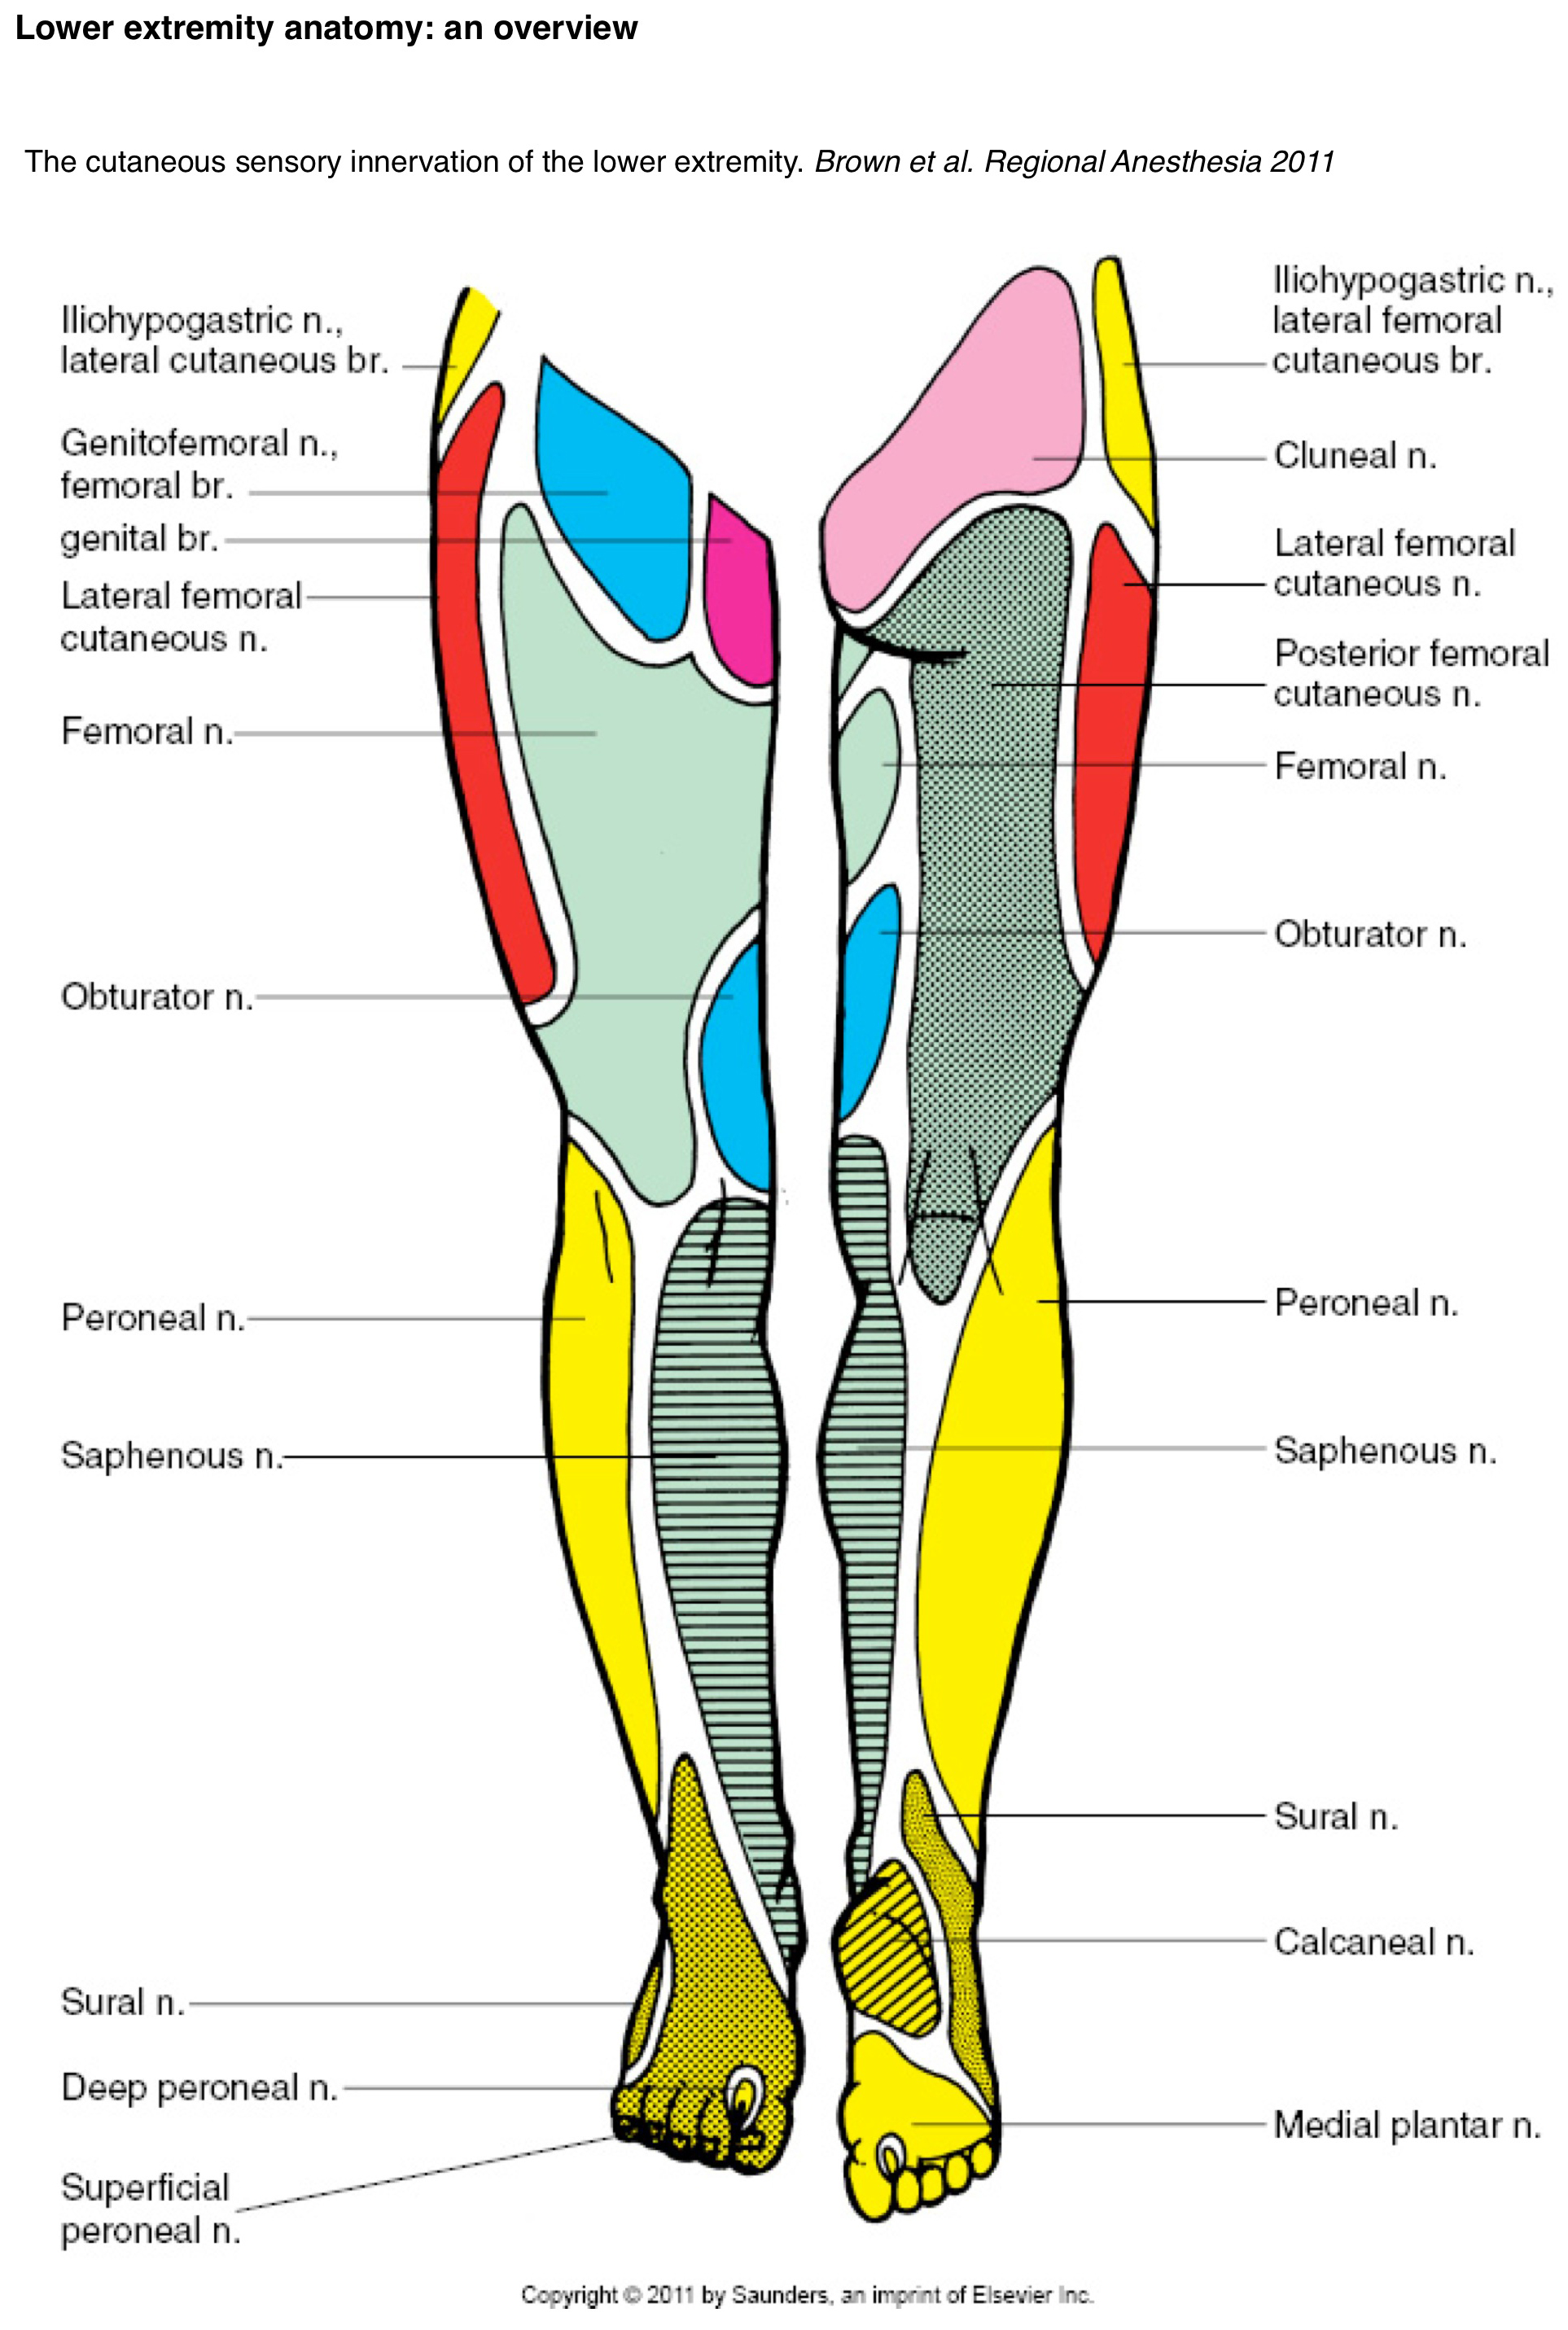
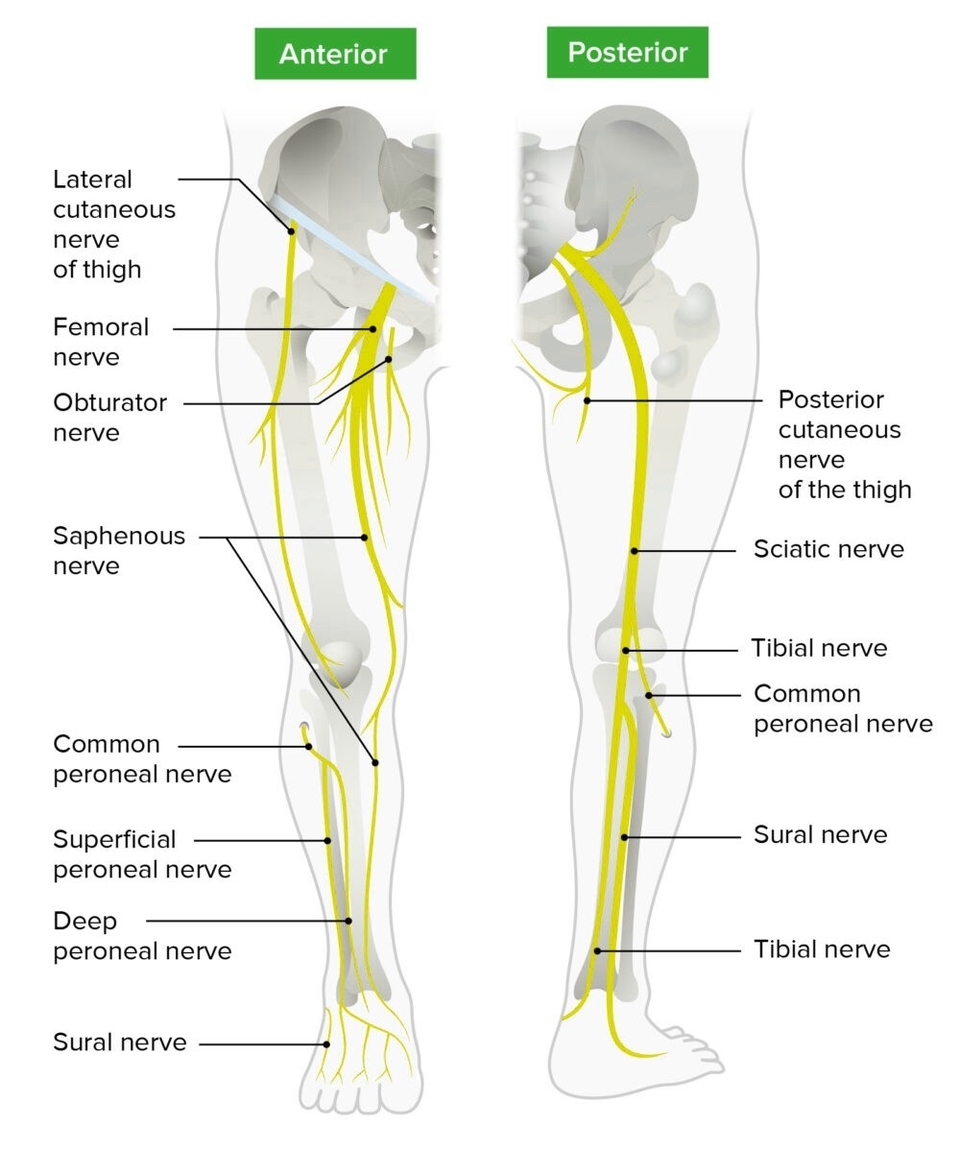
Let me start with the sciatic nerve because that's where most people run into trouble. It typically arises from the L4 through S3 roots, travels through the greater sciatic foramen below the piriformis, and then splits into the tibial and common peroneal divisions somewhere around the distal third of the thigh. Here's the part nobody emphasizes enough: that split happens at wildly different levels. In some people it's high, near the piriformis. In others it doesn't separate until just above the knee. If you're aiming for a sciatic nerve block at the gluteal level expecting a single target, you might miss entirely when the common peroneal component is already lying laterally, separate from the tibial portion. The femoral nerve is simpler but no less variable in clinical terms. It comes from L2 through L4, passes under the inguinal ligament lateral to the femoral artery, and gives off its motor branches to the quadriceps and its sensory branch, the saphenous nerve, which travels down the medial leg within the adductor canal. A common pitfall here is assuming that blocking the femoral nerve at the inguinal level will reliably numb the medial knee. The saphenous nerve has already branched off proximally in many patients, so a femoral sheath injection might spare the medial knee sensation entirely. If you need that area anesthetized, you're better off targeting the saphenous nerve directly at the adductor canal or even distally near the medial malleolus. The common peroneal nerve deserves more attention than it gets. It wraps around the neck of the fibula subcutaneously, and this is probably the most clinically vulnerable nerve in the lower extremity. Any tight cast, prolonged compression from positioning during surgery, or even aggressive CPR can injure it. The result is foot drop and sensory loss over the lateral lower leg and dorsum of the foot. I once had a patient who developed a complete peroneal palsy after a routine knee arthroscopy simply because the leg holder pressed against the fibular head for too long. The anatomy itself wasn't abnormal. The positioning was the problem.
Here's something most introductory resources skip over: the deep and superficial peroneal nerves have a variable relationship at the fibular neck. The deep peroneal nerve pierces the fibularis longus muscle and runs between it and the extensor digitorum longus. The superficial peroneal nerve stays more posterior. When you're doing a peroneal nerve block for foot surgery, you often can't reliably separate these two with a single needle pass. I've found that a dual-injection technique, or accepting a high peroneal block that captures both divisions proximal to their separation, gives more consistent results. This usually cuts the process down from twenty minutes of fiddling to about five, depending on your ultrasound quality and the patient's body habitus. The obturator nerve is another frequently overlooked structure. L2 through L4, it exits the psoas medial border, travels along the lateral pelvic wall, and passes through the obturator canal to innervate the medial thigh adductors. It also contributes articular branches to the hip joint. If you're doing a hip procedure and relying solely on a lumbar plexus block, the obturator contribution might be incomplete, leaving the patient with pain on medial thigh manipulation. Adding a dedicated obturator block component is standard practice for this reason, and it adds maybe three minutes to the procedure if you're using ultrasound guidance. Surface landmarks matter more than you'd think for the lateral femoral cutaneous nerve. It arises from L2 and L3, crosses the iliacus muscle, and pierces the inguinal ligament near the anterior superior iliac spine. Meralgia paresthetica, compression of this nerve, is one of the most common mononeuropathies I encounter. Tight belts, obesity, pregnancy, and even prolonged standing can compress it. The diagnosis is clinical: burning or numbness over the lateral thigh in an L2-L3 distribution with normal motor function and normal reflexes. Treatment is usually conservative. Weight loss, avoiding tight clothing, and occasionally a local steroid injection. Surgery is rarely indicated.
Get the Full Details

When you're studying Lower Extremity Nerve Anatomy for exams, memorize the root values and the major branches. When you're actually using this knowledge, memorize the variants and the failure modes. I've seen resident after resident waste time trying to identify a sciatic nerve on ultrasound that wasn't there in the expected location because the patient had a high bifurcation. They kept scanning laterally when they should have scanned more medially and more proximally. The tibial nerve follows the popliteal fossa, running deep to the soleus and then passing between the two heads of the gastrocnemius. It gives off the medial sural cutaneous nerve, which joins with the peroneal contribution to form the sural nerve. The sural nerve is the one you harvest for nerve grafts, and knowing its consistent anatomy through the posterior calf is useful. It lies between the gastrocnemius and the small saphenous vein, which makes it relatively safe to harvest if you stay in the right plane. One more practical point about the saphenous nerve. It's purely sensory and travels with the great saphenous vein from the adductor canal down to the medial ankle. This is why saphenous nerve blocks are so reliable for foot and ankle surgery when you only need medial sensation covered. The block is technically easy with ultrasound, taking maybe two minutes once you're proficient, and it avoids the motor blockade that comes with a femoral nerve block. For elderly patients with cardiac or pulmonary compromise, that distinction matters more than textbooks usually acknowledge.
The bottom line is that lower extremity nerve anatomy is not a static map. It's a set of probabilities. Knowing the probabilities lets you work efficiently. Not knowing them wastes everyone's time.