Getting Started with Manual Lymphatic Drainage Using the Jan Douglass Approach
The Jan Douglass method is a refined system of manual lymphatic drainage that pulls heavily from the Vodder technique but adds more structure to sequence and documentation. If you're coming from a general massage background, the first thing you need to unlearn is pressure. This is not a tissue-molding technique. You're working at the level of the superficial lymphatic capillaries, which means your stroke intensity should be light enough that the skin moves beneath your fingers without folding or dragging. Think roughly 30 to 60 grams of pressure, which is about the weight of a nickel resting on the skin. I ran into a specific problem early in my practice with a post-mastectomy patient who had developed mild arm swelling. I was pressing too hard on the proximal sites, essentially occluding the very channels I was trying to open. The patient reported a strange feeling of fullness rather than relief after the session, and the arm measurement didn't improve between visits. The workaround was straightforward but counterintuitive: I backed off the pressure significantly on the supraclavicular fossa and spent more time on respiratory priming before even touching the affected limb. Once I got the central drainage pathways actually moving through proper inspiratory expansion, the distal strokes had somewhere to go. That session took longer overall but produced measurable reduction where the previous three hadn't.
Lymph Drainage Jan Douglass: Core Principles and Setup
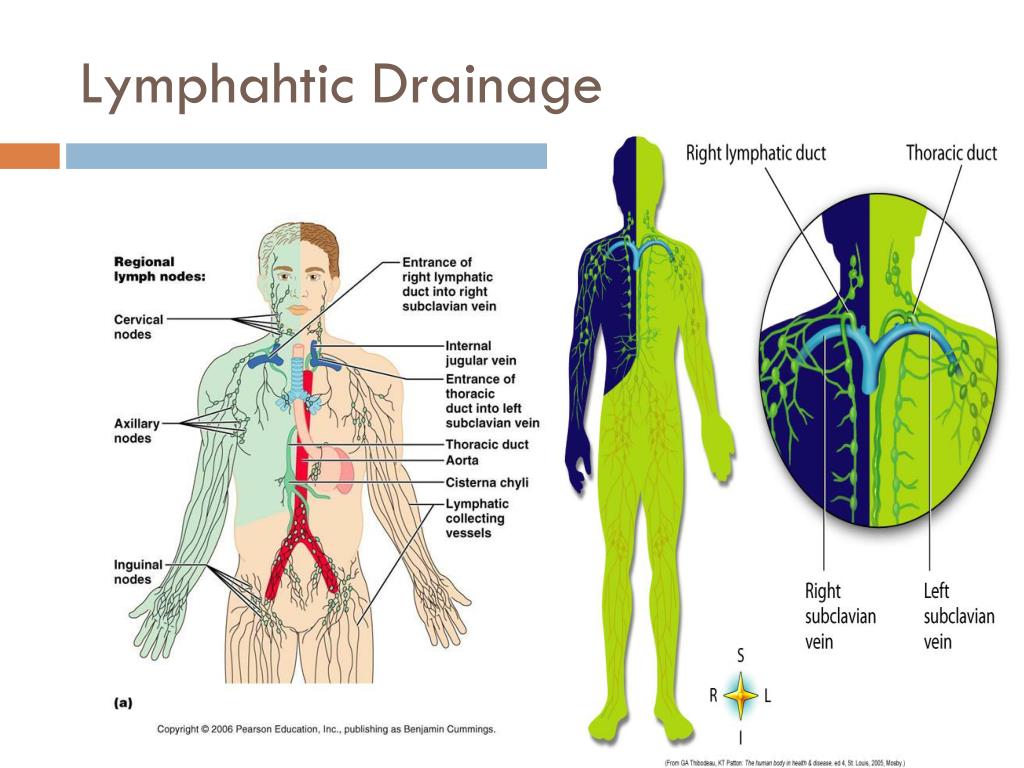
Jan Douglass emphasizes a strict proximal-to-distal sequence, meaning you always clear the central lymph nodes before working on any peripheral area. Her approach also places heavy weight on the initial thoracic pump mechanism. Before you do anything else, you're establishing rhythm through diaphragmatic breathing patterns that create negative intrathoracic pressure, which pulls lymph toward the venous angle. Here's the practical breakdown of a standard session sequence: Phase one: Respiratory priming. Have the patient supine. Place your hands on their lower ribcage and upper abdomen. Guide them through slow nasal inhalations that expand the ribs laterally and the abdomen upward, then prolonged exhales through pursed lips. Do this for about three to five minutes. You're not just calming the patient, you're mechanically stimulating the thoracic duct and right lymphatic duct entrance points. In my experience, skipping this step on patients with significant bilateral congestion wastes the rest of the session. The fluid has nowhere to go if the central pumps aren't cycling.
Phase two: Supraclavicular and cervical node opening. Using your fingertips, apply those light strokes in a fanning pattern over the supraclavicular fossae. Move from the clavicle upward toward the base of the neck, then medially toward the sternocleidomastoid. Ten to twelve repetitions on each side. Then work the cervical chain along the anterior and posterior borders of the sternocleidomastoid. Again, feather-light contact. The skin should ripple slightly under your digits. If the skin is moving with you, you're pressing too hard. Phase three: Quadrantanatomic drainage. This is where the Douglass methodology gets specific. She divides the body into quadrants and recommends treating each quadrant independently, always routing toward the nearest regional node basin. For the upper extremity, you're working toward the axillary nodes. For the lower extremity, toward the inguinal nodes. For the torso above the umbilicus, toward the axillary basin. Below the umbilicus, toward the inguinal basin. Never cross the midline directly. Always route around. Phase four: Retention and repetition. Each stroke pattern gets held at the terminal point for two to three seconds before returning to the origin. The hold allows the lymphatic vessel to fill. The return stroke is lifted completely off the skin. Don't drag back. Lift, reposition, stroke again. A typical quadrant gets eight to twelve complete cycles before you move on.
Get the Full Details

One thing beginners consistently mess up is the return phase. They slide their hand back to the starting position while maintaining contact, which defeats the negative pressure valve mechanism inside the lymphatic capillaries. You lift entirely. It feels awkward at first because you're making more total movements per session. That's normal. The extra movements are the point.
Common Clinical Applications and Nuances
The Douglass method is most frequently applied to secondary lymphedema management, particularly post-cancer-surgery swelling. It's also used for chronic venous insufficiency with a lymphatic component, post-traumatic edema, and recurrent cellulitis prevention protocols. What most sources don't emphasize is that this technique is a management tool, not a curative one. If you have a patient with Stage 2 or 3 lymphedema, MLD will reduce volume temporarily and help with comfort, but it does not regenerate destroyed lymphatic vessels. The swelling returns if sessions stop. Be honest with patients about that from day one. Another counter-intuitive detail: patients with significant fibrosis orStage 3 lymphedema often tolerate MLD poorly at first. The tissue is already compromised and the light strokes can feel ineffective or even irritating. In those cases, I usually start with very short sessions of ten to fifteen minutes focused entirely on proximal clearance and breathing, then gradually introduce distal work over four to six visits. Jumping straight into full quadrant drainage on a fibrotic limb creates more congestion because the proximal pathways aren't ready to handle the increased load. Contraindications matter here too. Active deep vein thrombosis, untreated cardiac congestive failure, active malignancy in the treatment field, and acute infectious processes like cellulitis are hard stops. I've seen practitioners attempt drainage on limbs with active infection because "reducing swelling will help." That's wrong. You can propagate bacteria systemically by increasing lymphatic flow through an infected field. Always check for warmth, redness, and fever before placing your hands on a limb.
The documentation piece that Douglass stresses is often neglected in training programs. Measure and record limb circumference at standardized points before and after each session. Track weight if the patient has bilateral involvement. Without baseline measurements, you're guessing whether the technique is doing anything. Most patients won't perceive a difference after a single session even when objective measurements show improvement. The subjective feeling of lightness usually takes four to six sessions to register.

Practical Setup Notes
You need a treatment table with pillows for arm and leg positioning, a small towel roll for wrist support, and a clock. Sessions typically run forty-five to sixty minutes for a full-body protocol. A single quadrant might take fifteen to twenty minutes. If a patient can only commit thirty minutes, prioritize the most symptomatic area and the proximal drainage sites. Don't half-ass every quadrant. A focused twenty-minute session on one area with proper proximal prep produces better outcomes than a rushed full-body pass. The learning curve for proper stroke mechanics is about six to eight weeks of supervised practice. Your hands need to develop the proprioceptive feedback to gauge pressure correctly. I recommend practicing on yourself first. Put a coin on your own sternum and practice strokes so light that the coin doesn't slide. If the coin moves, you're pressing too hard. Jan Douglass's published materials and training certificates are available through lymphology association channels and specific manual therapy education providers. There's no single downloadable manual that covers the full system because much of the technique is hands-on and sequence-dependent. Look for certified training courses rather than relying solely on video content if you're planning to use this clinically. The pressure and rhythm details don't transfer well through screen instruction alone.