Understanding Arm Lymph Node Anatomy
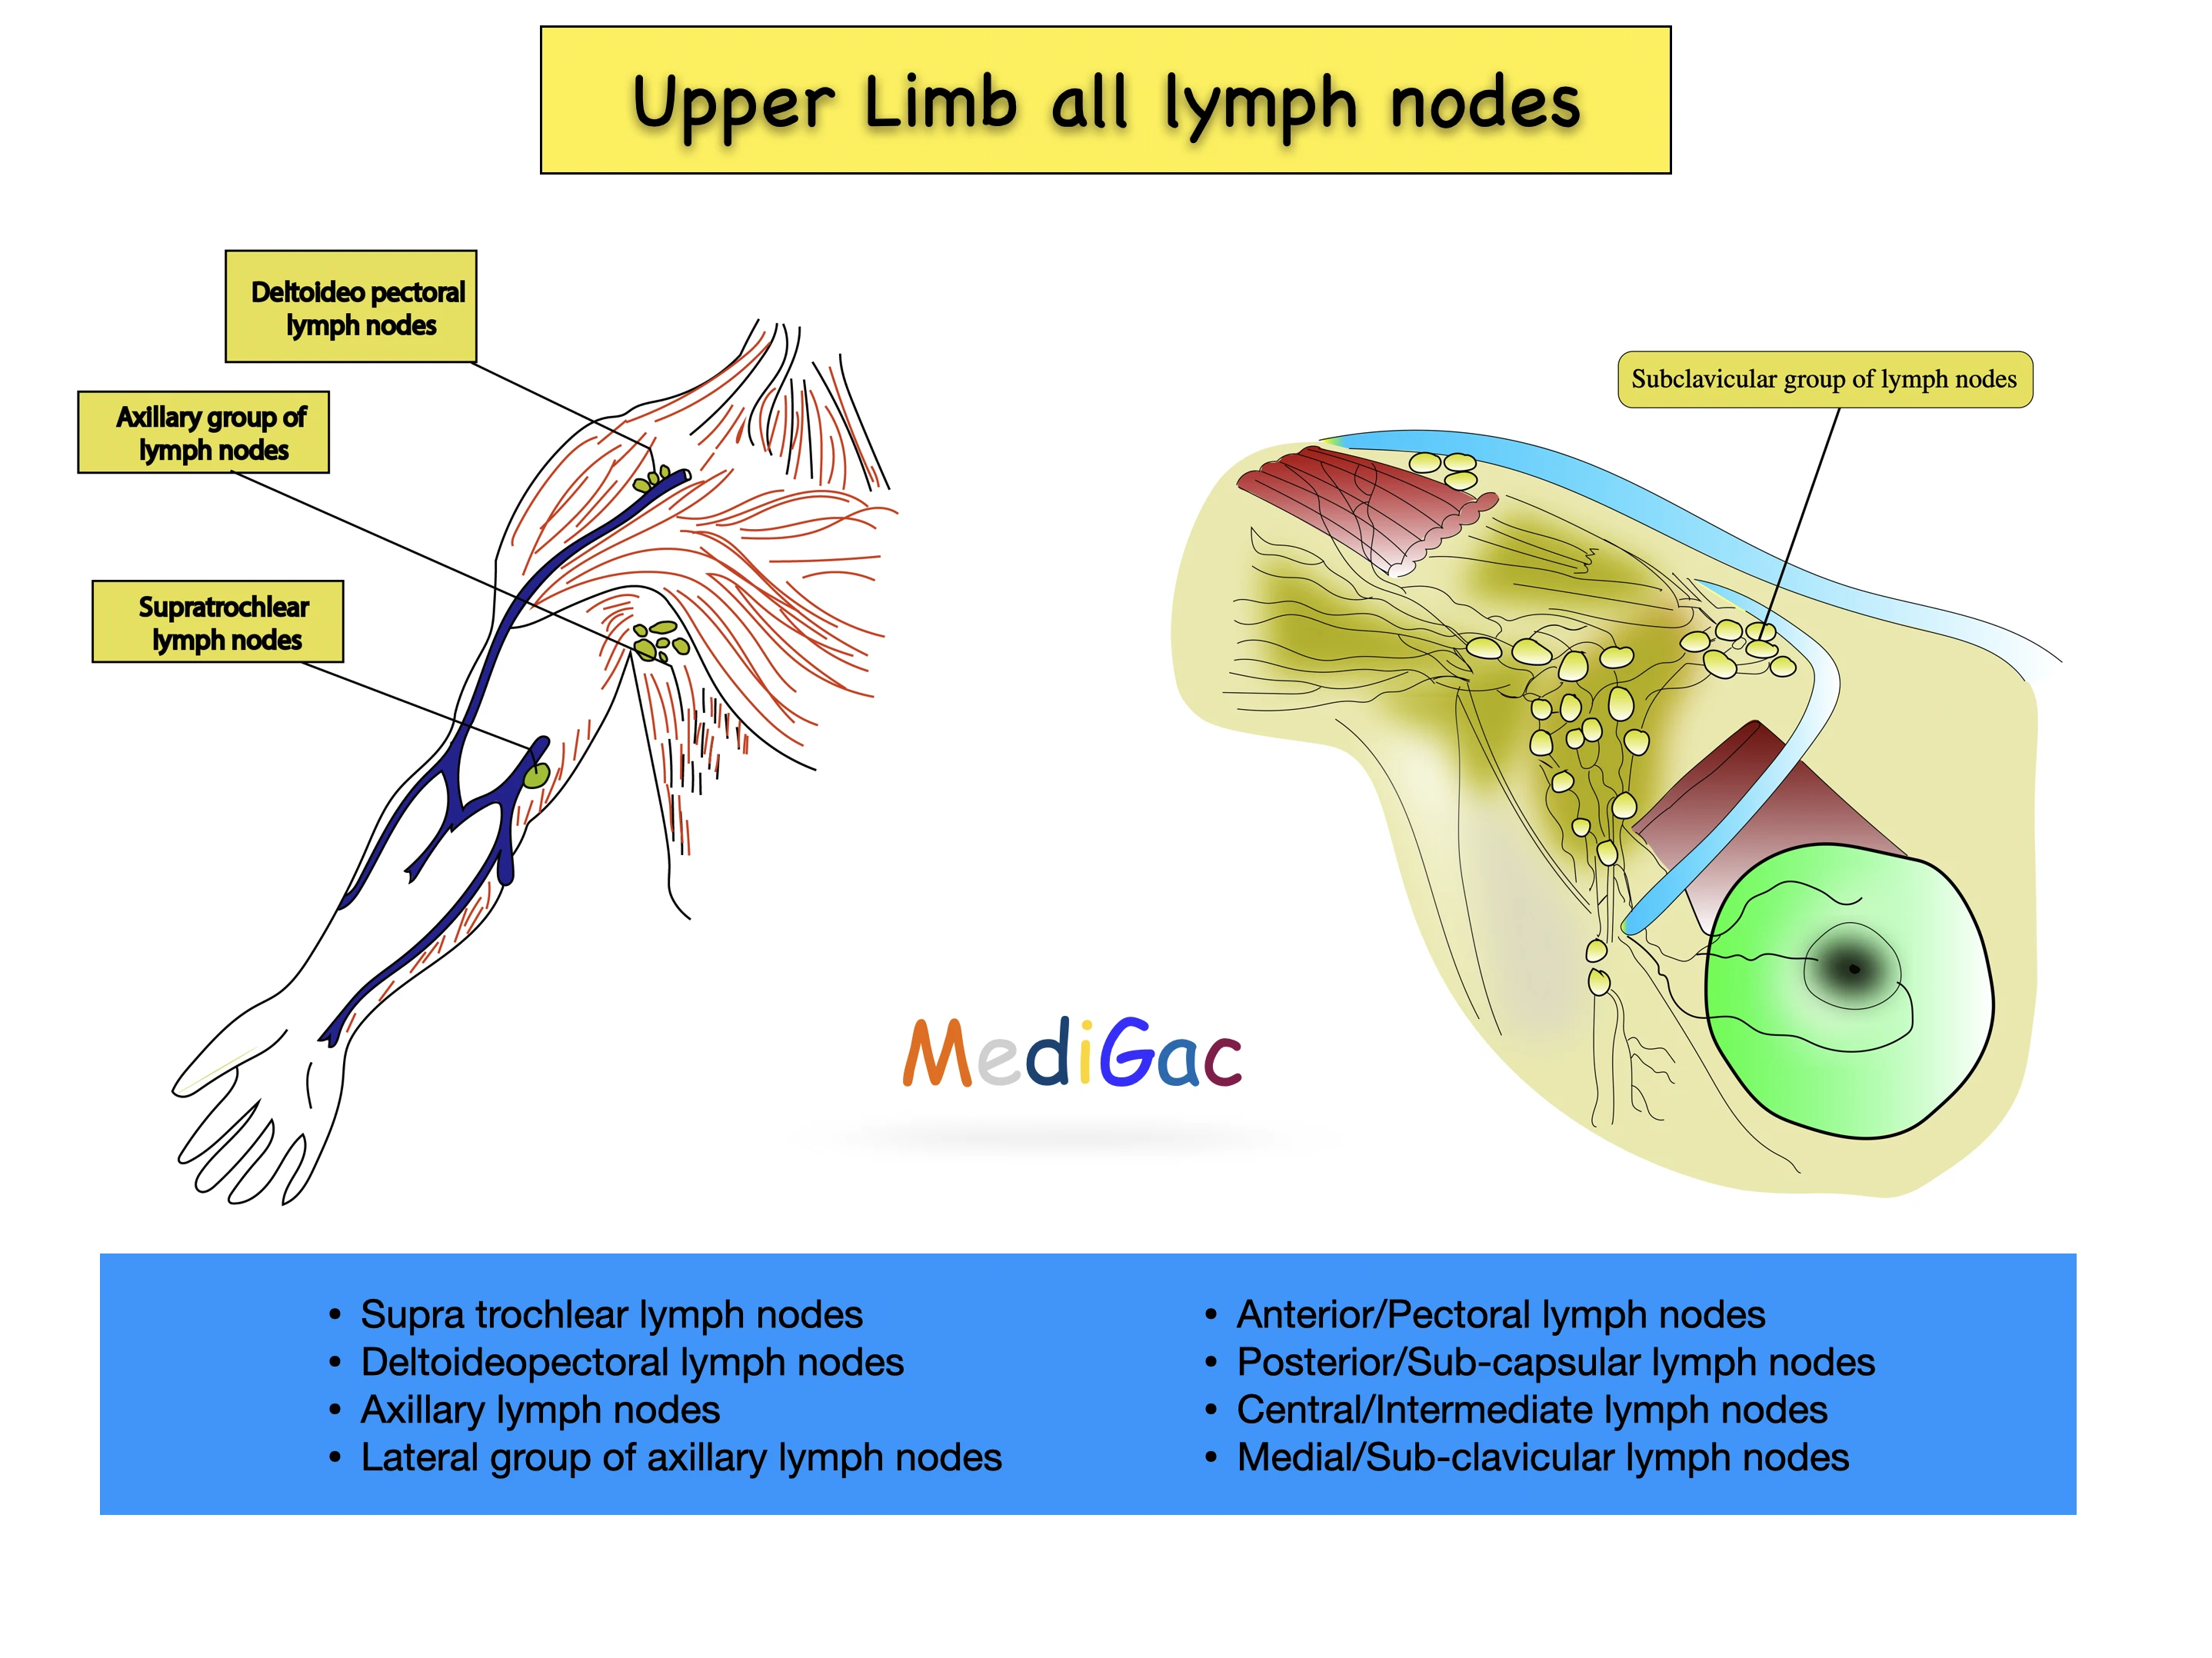
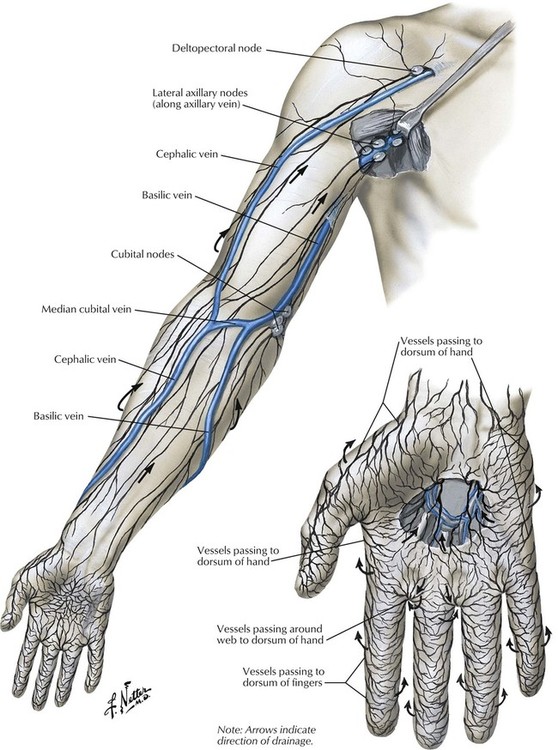
Most people have no idea where lymph nodes actually sit in their arm until something goes wrong. The axillary nodes are the main cluster, sitting in the armpit area, but there are also smaller chains running along the medial aspect of the upper arm and near the elbow crease. The lateral group near the cephalic vein is what people usually palpate first, followed by the epitrochlear nodes that sit just above the medial epicondyle of the humerus. When you're doing lymphatic assessment or need to reference Lymph Nodes Arm Location for clinical documentation, getting the anatomy right matters because missing a node in the wrong spot can throw off an entire staging evaluation. I start with the patient seated, arm resting on an exam table at about thirty degrees of abduction. You need the pectoral fascia relaxed to actually feel through the tissue. Press gently with the pads of your middle and index fingers in a rolling motion along the deltopectoral groove first. These are the pectoral nodes. Then move into the axillary tail, sweeping medially toward the lateral chest wall. The apical nodes sit deepest, behind the pectoralis minor, and honestly they're nearly impossible to palpate in anyone with even moderate subcutaneous tissue. I've found that having the patient place their hand on top of their own head opens up the axillary space enough to get better access to the central and subscapular groups. The epitrochlear node is a separate issue. It's normally non-palpable, and when it's enlarged it's almost always a sign of infection in the drainage field — ulnar forearm, hand, or occasionally a systemic process. I once had a patient with persistent epitrochlear enlargement that turned out to be early-stage sarcoidosis. The node was only about six millimeters, easy to miss if you're not specifically checking for it. Standard protocol is to palpate while the patient's elbow is flexed at ninety degrees and the forearm is supinated.
Common Clinical Scenarios
Post-mastectomy lymphedema is probably the most common reason patients and clinicians pay attention to arm lymph node anatomy. After axillary lymph node dissection, the remaining nodes have to handle increased lymphatic load, and that changes everything about how you assess the region. You're not just looking for enlarged nodes anymore. You're tracking drainage patterns, monitoring for recurrent disease, and differentiating between benign reactive changes and something more serious. I've seen too many practitioners skip the lateral axillary group during follow-up exams because they're focused on the central cluster. That's a mistake. The lateral group drains the entire upper extremity below the shoulder, and isolated enlargement there often points to a distal source — skin infection, insect bite, or malignancy in the arm itself. I typically document findings using a clock-face analogy with the patient's arm abducted. Twelve o'clock is the apex, six o'clock is the lateral chest wall, and so on. It keeps the record consistent across visits.
Imaging and Limitations
Ultrasound is the go-to imaging modality for superficial axillary and supraclavicular nodes. It's operator-dependent, which means your results vary depending on who's holding the probe and how experienced they are. I've had cases where a node measured 8mm on one visit and 12mm on the next, purely due to probe angle and pressure. The working hypothesis is that compression from the transducer displaces fluid within the node capsule, making it appear larger. That's why serial measurements should always use the same machine and ideally the same sonographer. MRI with contrast gives better visualization of the deep apical and subscapular groups, but it's expensive and takes longer. For routine surveillance, I rarely recommend it unless ultrasound findings are equivocal. CT scans have their place for staging, but they're terrible at characterizing individual nodes smaller than a centimeter. A node at 9mm on CT could be reactive, malignant, or nothing at all. On high-resolution ultrasound, you can see the fatty hilum and corticular symmetry, which gives you actual diagnostic information instead of just a measurement. The biggest blind spot in arm lymph node assessment is the infraclavicular and lower cervical region. These nodes don't palpate well in most people, and standard ultrasound protocols often don't cover them unless you're specifically looking for Pancoast tumor metastasis or lymphoma staging. I've learned to add a systematic scan of the supraclavicular fossa and the costoclavicular space during every comprehensive exam, even when the referral reason seems unrelated. You never know what you'll find until you look.
Get the Full Details