Palpation Technique and What You're Actually Looking For
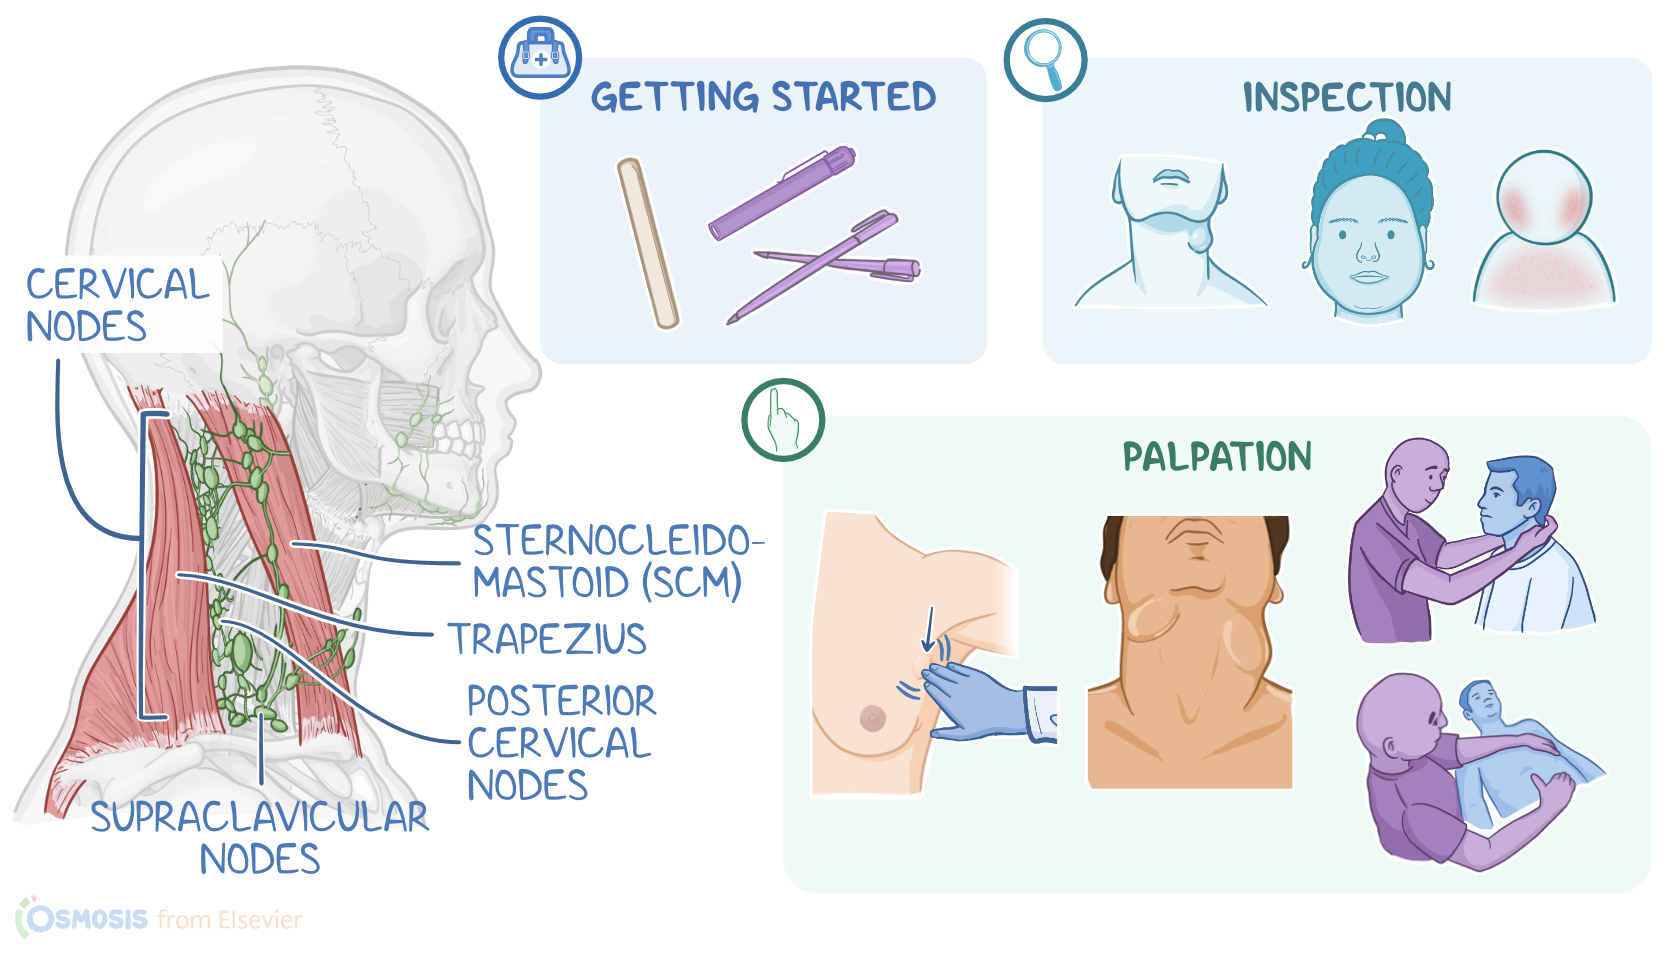
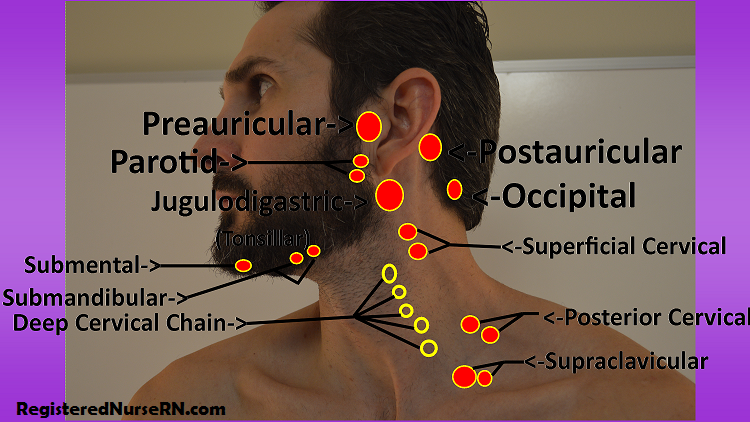
Start with the patient seated or supine, depending on which node group you're assessing. Use the pads of your fingers, not the tips. Most people press too hard at first, which buries the node under the muscle layer and makes it impossible to feel. I've watched nursing students fail to locate a supraclavicular node because they were grinding downward into the clavicle instead of rolling their fingers gently across the posterior triangle. The order matters more than people admit. Go cervical, then supraclavicular, then axillary, then inguinal. If you skip around, you'll lose your mental map of that patient's baseline. You need to know what their normal feels like before pathology stands out.
Lymph Nodes Nursing Assessment: Palpation Technique That Actually Works
Document node size in centimeters using the longest axis. Two centimeters is generally the upper limit of normal for most node groups, though epitrochlear and inguinal nodes can occasionally be larger without clinical significance. Consistency matters as much as size. Healthy nodes are soft, freely mobile, and non-tender. Enlarged nodes that are hard, fixed to surrounding tissue, and non-tender are far more concerning than tender nodes that are mobile and rubbery. I recall a patient a few years back during a med-surg rotation. She had a small, firm node near her right ear that I initially wrote off as reactive from a mild scalp irritation. A second-year nursing student on the unit mentioned she'd noticed it had been there for weeks and seemed fixed. We flagged it, the attending ordered an ultrasound, and it turned out to be a small metastatic deposit from a previously undiagnosed squamous cell carcinoma of the scalp. That encounter changed how I approach every posterior cervical node evaluation afterward. Size alone doesn't tell the full story. The axillary approach has a trick that most textbooks gloss over. Have the patient adduct their arm across their chest, which tension the pectoral fascia and brings the anterior axillary fold into sharper relief. Your fingers then glide along that ridge toward the axillary tail. The lateral node group sits against the humerus and is frequently missed when the patient's arm hangs at their side. You need the arm elevated and supported so the axillary tissues relax enough to permit deep palpation.
Supraclavicular nodes require the patient to be fully upright, head turned slightly away from the side being examined. Ask them to take a slow breath and hold it briefly. That momentary expansion of the thoracic inlet makes the triangle more accessible. Press deeply behind and just above the clavicle with a rolling motion. A positive Hallett's sign here—nodes that become more prominent with inspiration—suggests involvement of the thoracic duct or subclavian vein and warrants immediate further workup. For inguinal nodes, the patient must be supine with the hip and knee slightly flexed and externally rotated. This position relaxes the inguinal ligament and the surrounding fascia. Palpate both the horizontal and vertical chains separately. The horizontal chain runs just below the inguinal ligament along the saphenous vein trajectory. The vertical chain sits deeper along the femoral vessels and is more difficult to access without proper positioning. Many assessments skip the vertical chain entirely, which is where femoral nodes reside and where pathology related to lower extremity or pelvic drainage may hide. One thing that isn't discussed enough is the difference between a normal epitrochlear node and an abnormal one. Epitrochlear nodes are palpable in up to five percent of healthy adults, usually smaller than one centimeter and freely mobile. When they're larger than one centimeter or fixed, the sensitivity for underlying lymphoma or metastatic disease rises considerably. Don't ignore them because they're small. Their clinical significance flips depending on context.
Get the Full Details

A common pitfall I see repeatedly is documenting nodes as "non-palpable" without actually attempting the maneuver. If a patient is obese, has significant muscle mass, or is anxious and tense, you may not be able to palpate certain node groups even when they're enlarged. Note the limitation in your chart. "Posterior cervical nodes not clearly palpable due to patient body habitus and muscle tension" is far more useful than simply stating the nodes weren't found. Timing also affects what you'll feel. Acute infections produce tender, mobile, warm nodes that often regress within two to three weeks. Chronic pathology—malignancy, tuberculosis, autoimmune disease—tends to produce painless, progressively enlarging nodes that may coalesce into matted masses. The timeline of onset and evolution is a diagnostic clue that gets compressed when you rush through an assessment. A thorough lymph node exam takes about eight to twelve minutes if you're methodical. Rushing it to three minutes means you'll miss subtle findings. Use a consistent measurement tool. A ruler with millimeter markings is standard, but some clinicians prefer calipers for irregularly shaped nodes. Whichever you choose, measure the largest dimension and record it consistently across assessments. Tracking change over time is more clinically valuable than a single absolute measurement.
When you encounter a node that doesn't fit the expected pattern—fixed, hard, supraclavicular, or rapidly enlarging—document the features precisely and escalate. The decision to order imaging or refer for biopsy shouldn't hinge on whether the node is large. It hinges on the combination of characteristics and the clinical context surrounding the patient.