Understanding Lymphadenopathy: What Actually Happens Under the Skin
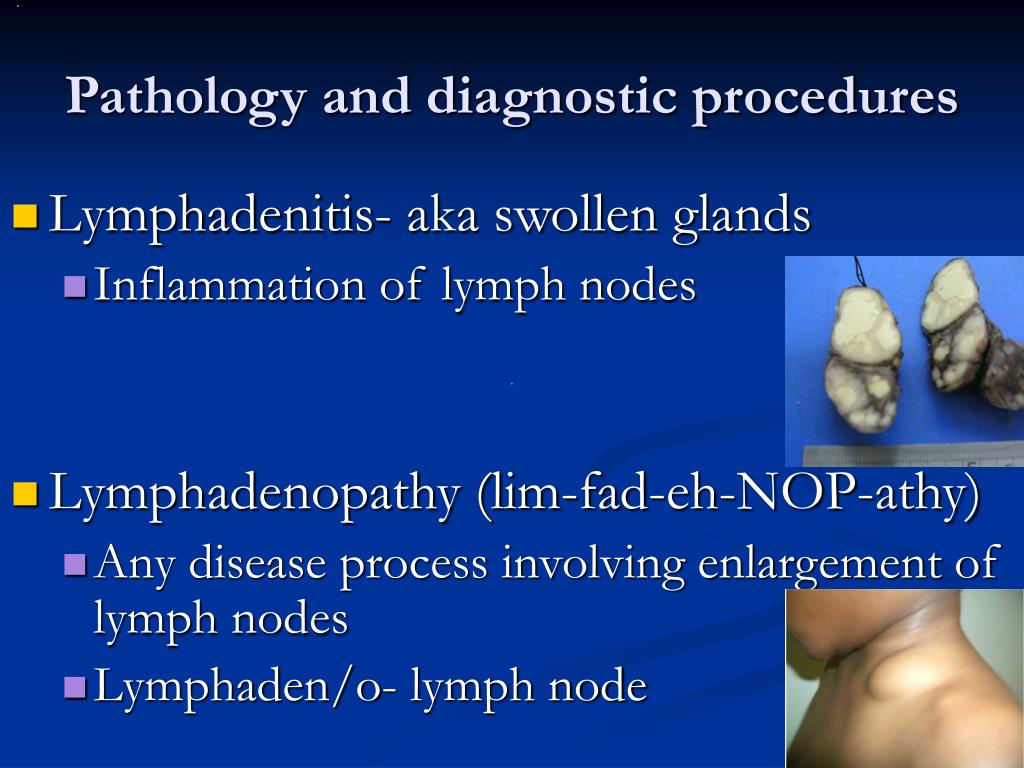
You will bump into lymphadenopathy fairly often in clinical practice, and it drives almost everyone nuts at first because the textbook presentation rarely matches what you see in real patients. I am not going to walk you through every possible cause — that would take 400 pages — but I will tell you what matters and how to actually work with this when it shows up on your service or in your own body. Before we go further, the phrase "Lymphaden O Medical Term" is just a shorthand people use when they are trying to say lymphadenopathy in a hurry. It refers to the enlargement or disease of one or more lymph nodes. The "O" is not a separate medical concept — it is a phonetic break that happens when someone says "lymphaden-" and then hesitates or adds "O" as a colloquial connector. The actual condition is lymphadenopathy, which can be localized or generalized. When I first started rounding, I kept missing the subtle differences between reactive hyperplasia and something more serious because I was focusing too much on size alone. A node that is 2 cm and firm in a patient with recent dental work is almost certainly reactive. A node that is 1.5 cm, rock-hard, fixed to surrounding tissue, and painless in a 62-year-old smoker? That needs imaging and likely a biopsy regardless of what the size charts say.
How to Approach a Patient With Suspected Lymphadenopathy
Start with a careful history. The history will tell you more than the physical exam in most cases, and that is counterintuitive for trainees who are taught to focus on palpation techniques. Ask about duration. Nodes that have been stable in size for more than three months without systemic symptoms are reassuring. Ask about recent infections, travel, animal exposure, occupational hazards, and medication history. Drug-induced lymphadenopathy from medications like phenytoin is real and completely under-recognized. Ask about B symptoms — fever, drenching night sweats, unexplained weight loss. These change the entire differential. On exam, map the location precisely. Cervical, supraclavicular, axillary, inguinal, popliteal. Supraclavicular nodes are the most concerning by far, especially on the left side. I had a patient with a left supraclavicular node that measured 1.2 cm. The size alone should not have triggered a CT, but location made it a different story entirely. We found an occult gastric malignancy.
Key Differentiators You Should Memorize
Not all enlarged nodes are created equal, and the clinical features carry diagnostic weight that most people underestimate. Tender, mobile, soft nodes are usually inflammatory or infectious. Think streptococcal pharyngitis, mononucleosis, cat scratch disease. Non-tender, firm, fixed nodes raise suspicion for malignancy — lymphoma, metastatic carcinoma, or less commonly, chronic granulomatous diseases like tuberculosis or sarcoidosis. But here is where beginners make mistakes: tenderness does not rule out cancer. I once saw a patient with metastatic thyroid cancer presenting with tender cervical nodes because there was rapid expansion causing capsular stretch. The tenderness fooled everyone including the attending who was called in for consultation. Size thresholds also vary by location. Inguinal nodes up to 1.5 cm can be normal in healthy adults. Axillary and cervical nodes over 1 cm warrant investigation. Popliteal nodes are almost always abnormal regardless of size.
Get the Full Details

Workup: What Actually Gets Ordered and Why
Initial evaluation should include CBC with differential, ESR or CRP, and LDH if malignancy is suspected. Chest X-ray is reasonable as a first-line imaging study. I prefer starting with ultrasound of the affected region when the nodes are peripheral and accessible because it gives you information about architecture — preserved fatty hilum suggests benignity, while loss of hilum and rounded morphology are red flags. CT or MRI comes next if ultrasound is indeterminate or if you need to evaluate deep nodal basins. PET scanning has a role in staging known lymphoma but is not a screening tool. When to biopsy: any node persisting beyond four to six weeks without an obvious infectious source, any supraclavicular node, any node larger than 2 cm, or any node accompanied by B symptoms. Fine needle aspiration has largely been replaced by core needle biopsy or excisional biopsy for initial diagnosis because architectural assessment matters for lymphoma classification.
A Real Case That Changed How I Think About This
Two years ago I evaluated a 34-year-old woman with bilateral axillary lymphadenopathy. The nodes were 1.8 cm, mobile, and mildly tender. She had been treated for presumed bacterial lymphadenitis with two courses of antibiotics without resolution. Her ESR was normal. An ultrasound showed preserved nodal architecture. I was tempted to observe, but something felt off — bilateral symmetric axillary adenopathy in a young woman with mild systemic symptoms. I ordered an excisional biopsy of one node. It came back as Kikuchi-Fujimoto disease, a rare form of histiocytic necrotizing lymphadenitis that is self-limiting but can mimic lymphoma clinically and histologically. She recovered spontaneously over eight weeks. The lesson: preserved architecture on ultrasound does not guarantee benignity, and persistent lymphadenopathy warrants definitive tissue diagnosis even when everything looks reassuring on paper.
When Lymphadenopathy Turns Out to Be Nothing
A significant minority of patients who present with lymphadenopathy end up with no identified cause after a thorough workup. This is called idiopathic lymphadenopathy. Most of these cases are benign and resolve on their own. The problem is the anxiety it causes and the difficulty of convincing patients — and sometimes colleagues — that observation is a valid strategy. If you are going to observe, document everything clearly. Set a timeframe for reassessment. Make sure the patient knows exactly which symptoms should trigger earlier evaluation. Vague reassurance without a concrete plan is irresponsible.
Common Pitfalls
One frequent error is attributing lymphadenopathy to stress or anxiety without adequate evaluation. Yes, anxiety can amplify somatic awareness, but it does not cause lymph node enlargement. Another pitfall is stopping the workup after the first negative test. A normal CBC does not exclude lymphoma. A normal chest X-ray does not rule out mediastinal involvement. A third pitfall is over-reliance on size criteria. Node characteristics matter more than dimensions. I have seen 3 cm nodes that were purely reactive and 0.8 cm nodes that were metastatic deposits.
Bottom Line for Dealing With Lymphaden O Medical Term Cases
The single most important skill is pattern recognition built through exposure. You will see enough reactive nodes to know what reactive looks like, and then when something deviates from that pattern it will stand out. Do not rush to biopsy everything, but do not ignore anything either. Take a thorough history, examine carefully, image when appropriate, and biopsy when the clinical picture does not resolve on its own. Most cases are benign, but the ones that are not benefit enormously from early recognition. If you want a practical reference to keep at hand, the UpToDate article on lymphadenopathy evaluation in adults is thorough and regularly updated. For a quick visual guide to nodal chains and their drainage patterns, the Radiopaedia lymph node anatomy page is reliable. And for understanding biopsy techniques and when each approach is indicated, the ASH educational program materials on lymphoma diagnosis are excellent and freely available online.