What Actually Happens When You Map a Family Structure
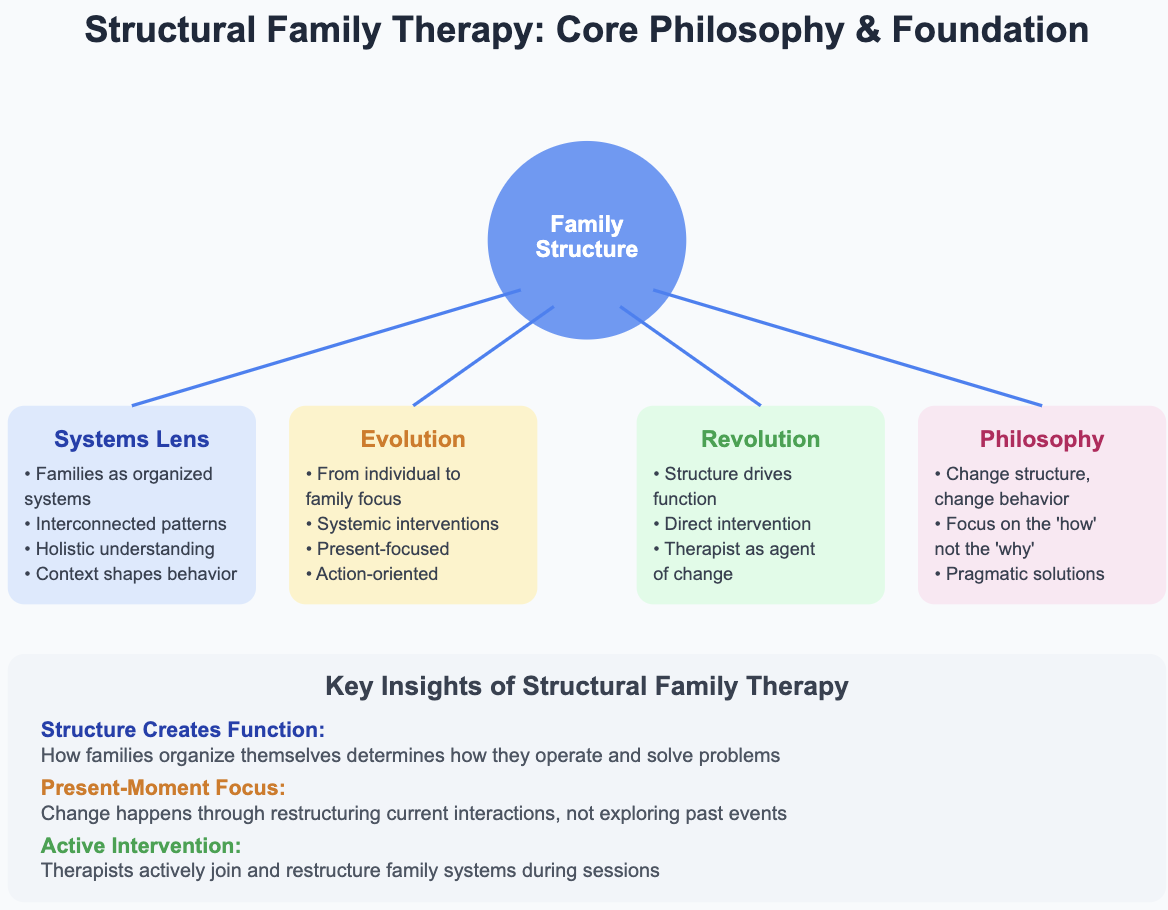
Structural Family Therapy mapping isn't about drawing cute diagrams to show in a session. It's a clinical tool for tracking how power, affection, and roles are actually distributed among family members, and it requires you to track patterns across multiple sessions before the map means anything useful. I keep coming back to this because most people learn the basic vocabulary — boundaries, subsystems, alliances, hierarchies — and then treat a static drawing as if it's the therapy itself. It isn't. The map is your working hypothesis. It's wrong half the time when you first draw it, and that's normal.
Mapping Structural Family Therapy: The Practical Process
The core of Mapping Structural Family Therapy involves identifying three things: the boundaries between subsystems, the hierarchy of authority, and the emotional alliances or triangles that hold the system together. You observe these during sessions, you sketch them on paper, and then you test whether your sketch predicts what will happen next. Here's how the process actually runs in a typical session: Step one: Watch the family interact without intervening. I usually let the first five minutes play out completely unchecked. This is where you see who speaks for whom, who gets talked over, who the children look toward when something tense happens. That look — a kid glancing at the most permissive parent when the strict one says no — is a boundary violation sitting in plain sight.
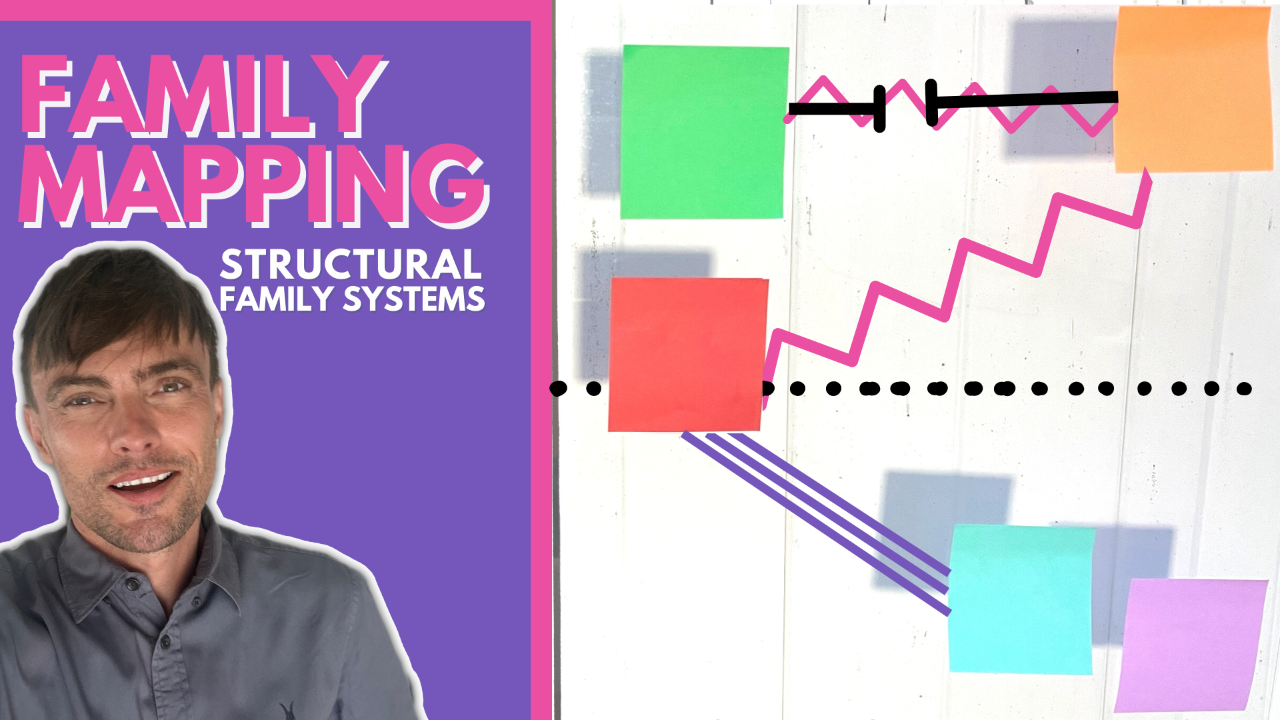
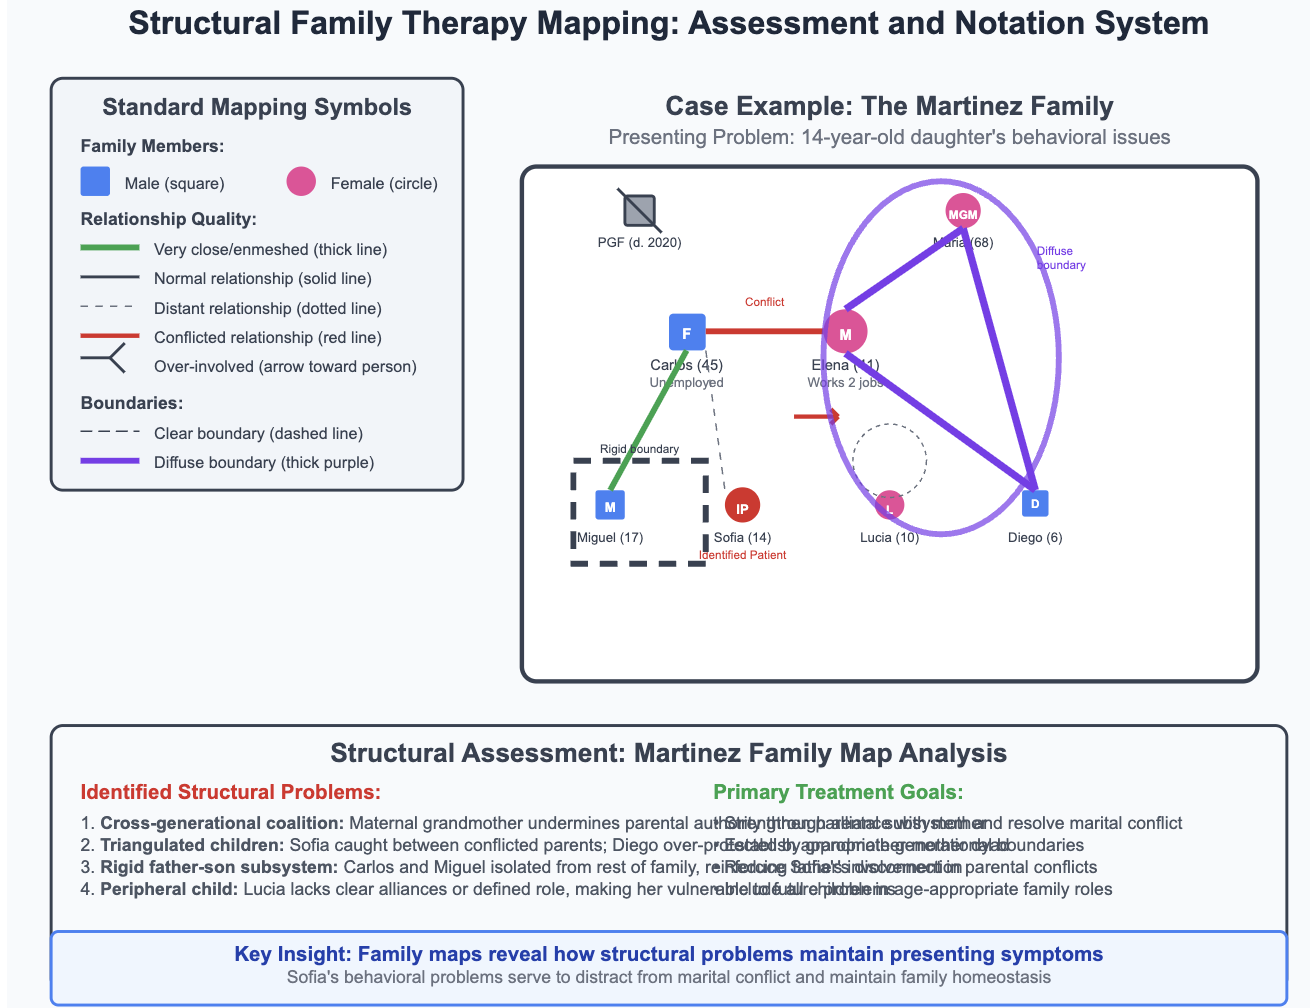
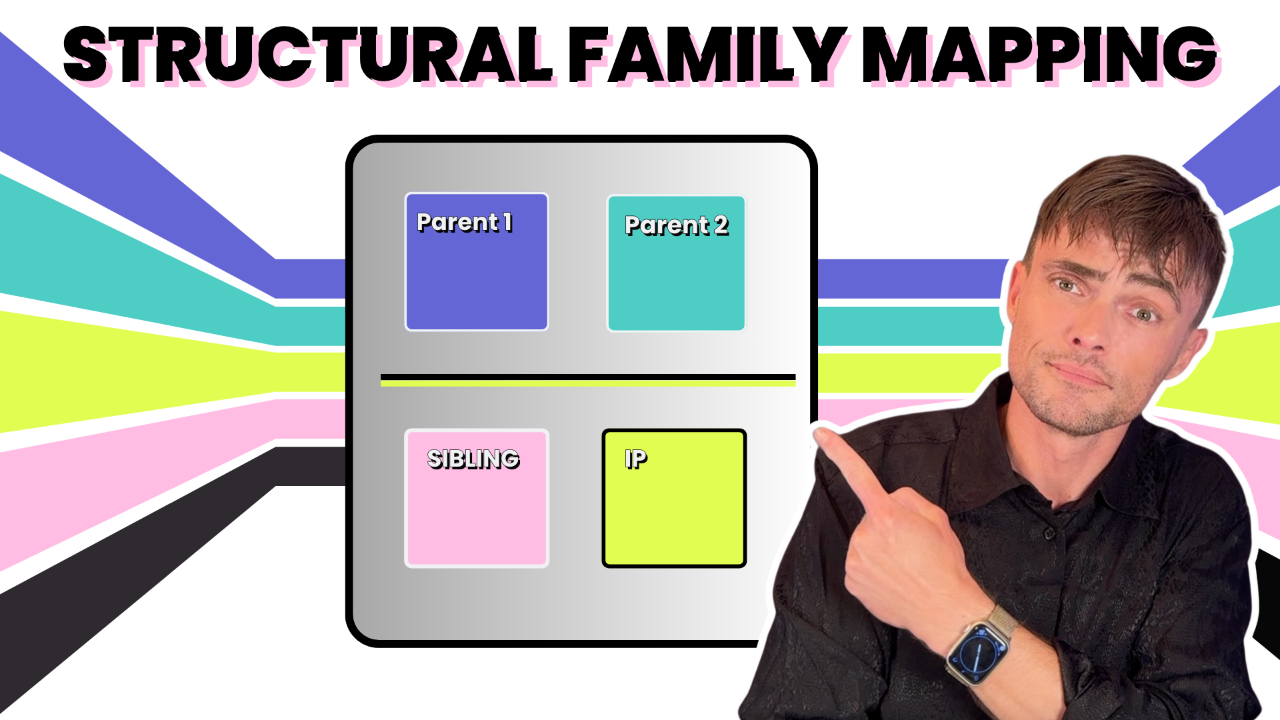
Step two: Draw the initial map using Minuchin's notation. Solid lines for clear boundaries, dotted lines for diffuse or enmeshed ones, arrows for cross-generational coalitions. You're not making art. This sketch takes about four minutes and should look rough. Step three: Test the map. Introduce a small perturbation — a direct question to the less-dominant parent, a redirection of a parent-child dyad — and watch whether the family reorganizes the way your map predicts they should. If they don't, your map is wrong. Redraw it. Step four: Intervene based on the updated map. Restructuring is the active part of this model. You might physically rearrange seating so a parent sits between two children, or you might direct a question to the parent rather than the parent's proxy child. The intervention is designed to shift the structure your map revealed.
Get the Full Details
I've seen therapists who map perfectly and then do nothing with it. That's not therapy, that's diagramming. The map only matters if you use it to change something.
Where Beginners Mess This Up Consistently
The biggest mistake I see is treating boundaries as binary. They're not. A boundary can be rigid, diffuse, or clear, and it can exist at different degrees along a spectrum at any given moment. I had a family once where the mother's boundary with her teenage daughter appeared enmeshed on the surface — they shared everything, laughed together constantly — but the grandmother was clearly the enmeshed one. The mother had formed a cross-generational coalition with the daughter that excluded the father entirely, and the daughter was functioning as an emotional spouse substitute. The map looked like a simple enmeshment at first glance. It took three sessions and a deliberate intervention where I asked the father directly about his role before the triangle became visible enough to redraw accurately. Another common error is mapping the present structure without tracking how it got there. Structural patterns persist because they serve a function. A child's acting out often maintains parental unity by redirecting conflict away from the marriage. If you map the symptom but miss the function, any intervention will collapse within a session or two. You also need to account for cultural variations in hierarchy and boundary norms. What looks like a rigid or disengaged boundary in one family structure might be the culturally expected arrangement in another. I worked with a family where the adult daughter lived with her parents and made all financial decisions while her mother handled domestic tasks. From a standard structural perspective this looked inverted and problematic. It wasn't. The arrangement reflected an extended family model with clear role differentiation that my initial map had misread as pathology. Correcting that interpretation saved us months of misdirected intervention.
What This Approach Cannot Do
Structural Family Therapy mapping has real limitations that textbooks don't always emphasize. It assumes a certain level of verbal coherence and family availability. If a family member has severe substance use, acute psychosis, or intellectual disability that prevents participation in session interaction, the mapping process loses its primary data source. You're left with collateral reports and projections, which are much less reliable. The model also struggles with non-traditional family configurations not because those configurations are inherently unmapable, but because the original theoretical framework was built around nuclear family assumptions. Blended families, multi-generational households with non-parental caregivers, and chosen families require you to be more deliberate about defining subsystems rather than assuming they map onto biological categories. Finally, structural mapping tends to underweight individual internal experience. Two family members can occupy the same structural position — say, the parentified child — and have completely different internal relationships to that role. One might resent it actively, the other might have fully internalized it as identity. The map shows the position. It doesn't capture the subjective experience. If you rely on the map alone, you'll miss the difference between compliance and identification, and that difference determines whether change sticks.

For those situations, I supplement structural mapping with brief psychodynamic assessment and sometimes bring in CBT techniques for individual symptom work. Structural mapping is strong on the relational layer. It's weaker on the intrapsychic layer. Acknowledging that keeps you from forcing a square peg into a round hole.
Getting Started with Your Own Maps
You don't need special software. A blank sheet of paper, a pen, and a timer for unstructured observation is sufficient. I recommend keeping a running session log alongside your maps rather than starting fresh each visit. Patterns emerge across three to five sessions, and the log lets you track which structural features are stable versus which shift after interventions. Download templates if they help, but don't let a formatted worksheet slow down your observation. The most useful maps I've ever made were sketched in the margins of my notes during a session. Accuracy matters less than speed in the first draft. You're capturing hypotheses, not producing records for a journal. The real skill develops through repetition and supervised review. Compare your map with a colleague's after the same session. You'll immediately see where your boundary interpretations differ, and that disagreement is usually where the actual clinical insight lives.