What a Maternity Nursing Study Guide Actually Covers
A Maternity Nursing Study Guide is usually just a condensed collection of high-yield topics pulled from maternity nursing courses. It covers prenatal care, labor and delivery management, postpartum recovery, and newborn assessment. That's the surface-level description. The reality is that most students grab one because they're drowning in textbooks and need something that maps directly onto exam questions and clinical rotations. I remember picking up a study guide early in my clinical rotation and realizing it was missing something critical. The section on preeclampsia protocols was three paragraphs long and completely skipped the magnesium sulfate toxicity monitoring parameters. A student reading only that guide could have missed the whole warning sign hierarchy. I ended up writing out my own supplemental notes on the side because the guide was useful but incomplete for NCLEX-style questions. The core content you should expect includes gestational age calculations, stages of labor, common pharmacological interventions during delivery, postpartum hemorrhage management, breastfeeding initiation, and newborn resuscitation basics. Those are the topics that show up repeatedly on both course exams and licensing tests. Anything beyond that is usually supplementary material that depends on your program's specific focus.
Here is how I actually use a study guide rather than just reading it passively. I go through each topic heading, close the material, and try to explain the concept out loud to an empty room. If I can't explain it clearly, I mark it and return to the textbook for deeper coverage. This takes about twenty minutes per topic instead of an hour of re-reading highlights. The problem with most study guides is that they present information in isolation. Labor stages get listed as bullet points without connecting them to the nursing interventions that follow each transition. Postpartum assessments appear without context about why certain findings require immediate escalation. You end up memorizing facts without understanding the clinical reasoning behind them. I started adding marginal notes that link each topic to a patient scenario I encountered during my clinical hours. One entry about placenta previa included the exact case where I watched a nurse recognize the painless bleeding pattern and immediately notify the provider. That connection between theory and practice is what actually sticks during an exam.
There is a specific edge case that trip ups most students and barely gets addressed in standard guides. Multiple gestation complications like twin-to-twin transfusion syndrome or preterm labor timelines differ significantly from singleton pregnancies, yet many study materials mention twins in one sentence and move on. When I worked on a maternity unit, we had a twin pregnancy at twenty-eight weeks who required tocolytic therapy and betamethasone administration. The study guide I was using had nothing about the altered medication timing for multiple gestations. I had to cross-reference the primary textbook to get the dosing intervals right before I felt confident answering questions on that topic. Another area where study guides fall short is the emotional and psychological component of maternity care. They cover the physical assessments and interventions adequately, but they rarely address the postpartum depression screening tools beyond naming the Edinburgh scale. In practice, recognizing the difference between normal postpartum adjustment and clinical depression affects everything from discharge planning to medication decisions. I added a separate section to my notes covering the PHQ-9 adaptation for postpartum patients and the timing of routine screening at two-week and six-week visits. If you are looking for a downloadable guide, search for resources from accredited nursing education programs or professional organizations like the American College of Nurse-Midwives. Government health sites and university nursing department pages tend to have more reliable material than third-party commercial sites. Avoid anything that claims to guarantee exam passage, as those usually oversimplify content or omit critical details.
Get the Full Details
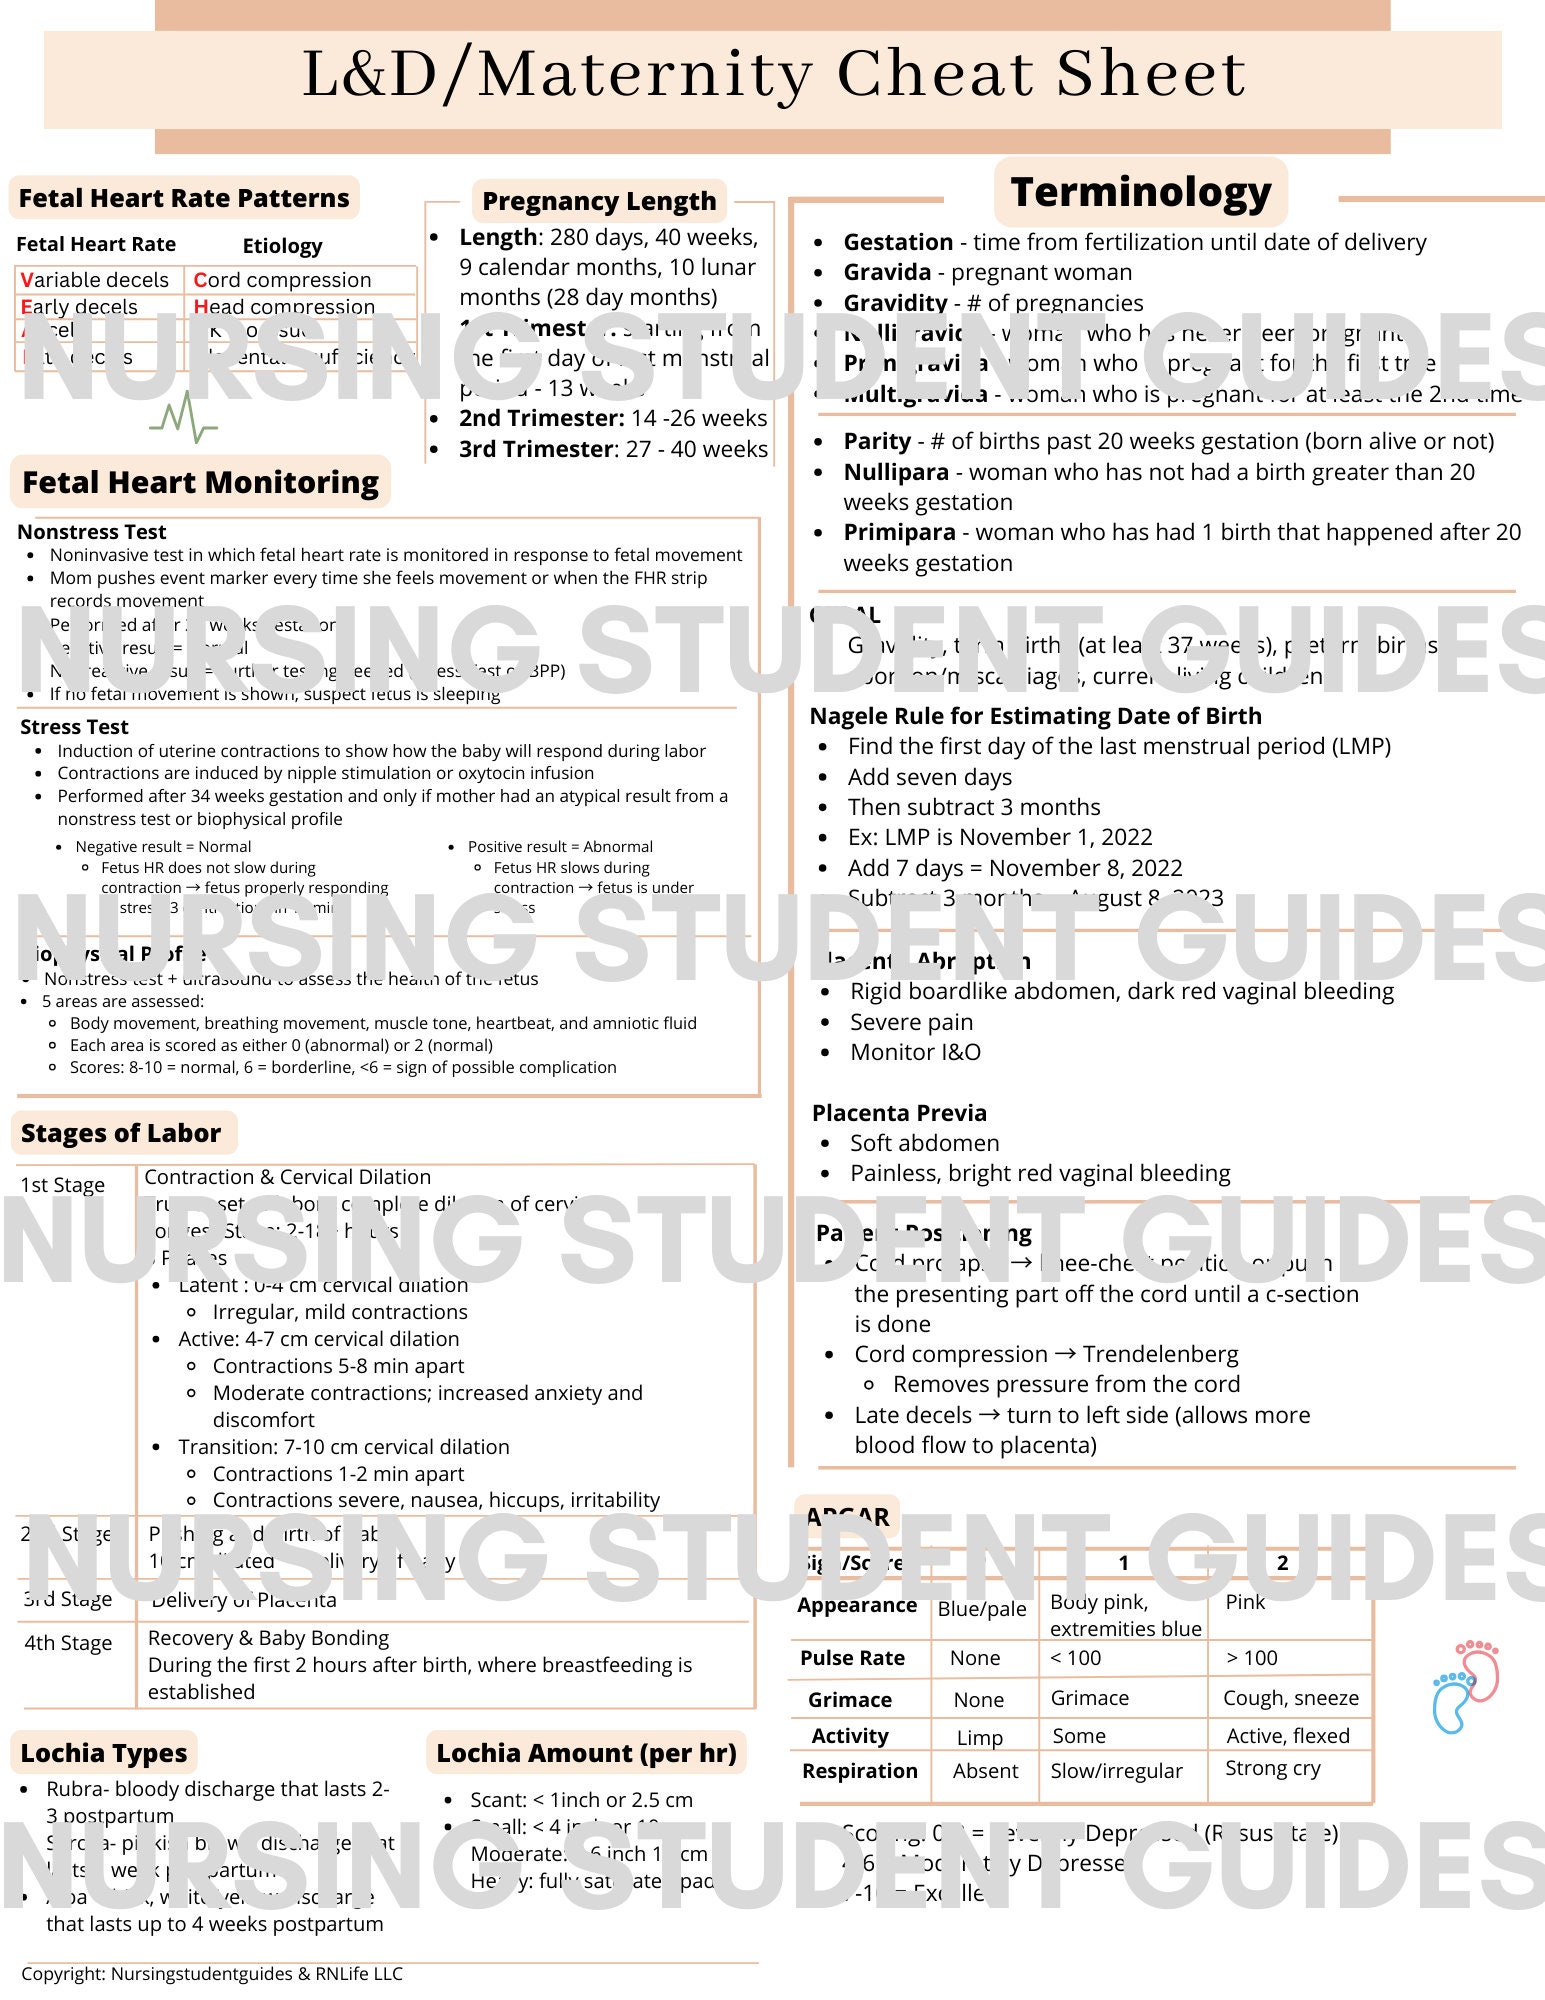
The most practical approach combines a solid study guide with active recall techniques and clinical correlation. Read a section, test yourself without looking at the material, then connect each concept to a real patient situation from your rotation or a detailed case study. This method typically reduces your total study time by about forty percent compared to passive re-reading while improving retention on application-type questions significantly. Don't skip the fetal monitoring interpretation sections even if they feel intimidating. It is one area where study guides often provide the clearest breakdown because the patterns are visual and rule-based. Striping, accelerations, deceleration types, and variability categories follow consistent logic once you understand what each pattern indicates about fetal status. I spent maybe thirty minutes working through a dozen strip examples and felt confident enough to handle most questions on that topic. Keep in mind that no single study guide will cover every possible question variation. They are starting points, not complete substitutes for the full curriculum. Your program's specific textbook, lecture notes, and clinical experiences will fill in whatever the guide leaves out. Use it efficiently, identify the gaps early, and address them before exam season hits.




